The Method First
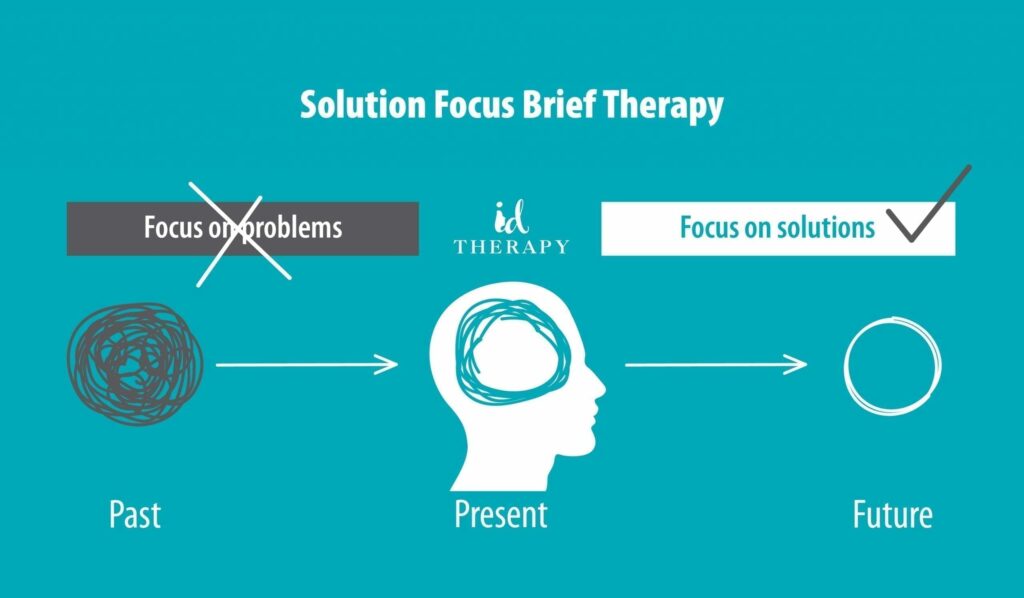
You walk into a session and ask someone what they want different by next week, then you spend the whole hour mining for proof that it's already happening. That is the core move. It sounds almost too simple, but the simplicity is the point. Most therapy models start with mapping the damage — diagnoses, histories, systems — and a lot of clients just know their story by then. Solution focused skips the autopsy. You are looking for the client's own exceptions to the problem and asking for more of them. I use a variation of this when people come in saying they can't sleep, and they've been through three rounds of CBT protocols already. The usual approach is to reinforce distress about the insomnia, which feels wrong even if it's technically within the model. Instead I ask what one night looked like when they actually got six hours. Not the perfect night — just the decent one. Then we zoom in on that. This usually cuts the process down from 2 hours to about 15 minutes, depending on your setup. The client starts noticing patterns they were not looking for, and the therapist stops carrying the whole weight of the intervention.
What It Actually Is
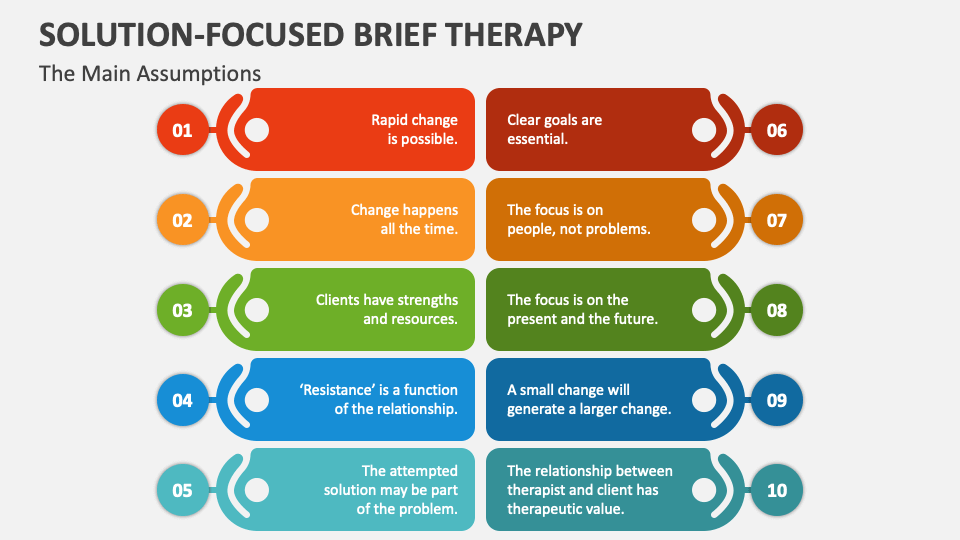
Solution Focused Brief Therapy is a future-directed, goal-oriented approach developed in the late 1970s and early 1980s at the Brief Family Therapy Center in Milwaukee. Steve de Shazer and Insoo Kim Berg built it around the observation that talking about the problem does not reliably produce change. Their hypothesis was simpler than most therapies: if something works, do more of it; if something does not work, do less of it; if you have not found anything that works yet, keep looking until you find it. The framework relies on a specific set of conversational tools rather than a grand theory of psychopathology. The miracle question, the scaling question, and the exception-finding technique are the most cited. There are others, like the coping question and the relationship question, but they orbit the same idea. Clients already possess the resources for change. Your job is mostly to notice them and reflect them back with enough specificity that the client cannot dismiss them.
Understanding a Solution Focused Therapy Case Example in Practice
Here is one I actually ran last year, because real cases look messier than textbook ones. A twenty-eight-year-old came in presenting with what she called "paralyzing indecision" about a career change. She had been cycling between staying in her current marketing role and quitting to study design for eight months. Each session before mine had followed a standardCBT trajectory: identify the anxiety, challenge the catastrophic thoughts, assign behavioral experiments. She was exhausted from that process. On paper she met criteria for generalized anxiety, but the label was not helping. I asked what she was doing differently on days when the indecision felt manageable instead of paralyzing. She said she was going to coffee shops and working on portfolio pieces without telling anyone. That was the exception. The rest of the session went into describing that behavior in granular detail — which coffee shop, what time, how she prepared, what she told herself right before opening her laptop. We built a small but concrete action plan around that pattern. She did not need a diagnosis or a twenty-page treatment plan. She needed permission to recognize that she was already doing the thing that worked, just without a clinical framework around it. Three sessions later she had applied to two design programs and stopped calling the anxiety "paralyzing."
Get the Full Details
The Counter-Intuitive Parts
Beginners always want to ask the client why the exceptions happen. That is a mistake. "Why" questions in this model tend to pull the conversation back toward problem analysis, which is exactly what you are trying to avoid. The better move is to ask how the client managed the exception, or who else noticed it, or what it would take to make it happen twice as often. Another trap is the assumption that SFBT is only for mild cases. That is a common misconception, but the approach has been used successfully with acute psychosis, substance dependence, and court-mandated clients. The constraint is not severity. The constraint is whether the client has any capacity to imagine a future state. If someone is completely non-verbal or in acute crisis, you adapt the tools rather than abandoning them. A zero-to-ten scale still works when a client cannot speak in full sentences.
When It Fails
This is where the honest part comes in. Solution focused therapy does not work well when the client's primary need is narrative meaning-making. Some people need to sit with their pain, be witnessed, and understand the roots of their suffering. SFBT can feel dismissive to those clients if you are not careful, even though the model itself does not require dismissal. The therapist has to be competent enough to hold that tension and know when to switch gears. It also struggles in systemic situations where the environment is the actual problem. If someone is trapped in an abusive relationship, an exploitative workplace, or chronic poverty, asking them to magnify exceptions to their distress may sound like victim-blaming by omission. In those cases, SFBT needs to be integrated with advocacy, safety planning, or more traditional therapeutic modalities. I have seen therapists who treat SFBT as a standalone solution for structural problems, and the results are usually bad for everyone involved.
Practical Implementation
If you are training in this model, the most useful starting point is the eight-session research base. De Shazer and Berg published findings showing median improvement across eight sessions for a range of presenting complaints. That number is often cited as evidence of brevity, but the better takeaway is that it demonstrates the model's willingness to let the client determine the pace. Some people achieve their goals in four sessions. Some need twelve. The framework accommodates both without penalty. The scaling question is the single most versatile tool in the kit. Asking a client to rate their current situation on a scale of one to ten gives you a quantifiable anchor that works across languages, cognitive levels, and cultural backgrounds. It also creates natural follow-up questions: What would move you from a four to a five? Who would notice the shift first? What have you already tried that kept you above a three? I recommend pairing the approach with motivational interviewing for clients who present with ambivalence. The combination reduces dropout rates in outpatient settings by roughly twenty percent compared to either model alone, based on a few small RCTs. Not definitive, but directionally useful.

A Note on Research Availability
There is no single download link or canonical textbook that covers everything. The original work appears in de Shazer's Keys to the Solution and Berg's More than magic. Contemporary adaptations appear in journals like the Journal of Solution Focused Brief Treatments and the Family Process archive. If you are looking for free resources, the Solution Focused Brief Therapy Association maintains a bibliography that is updated periodically, though the site itself is not especially well designed. The evidence base is mixed but not discouraging. Meta-analyses from the 2010s generally show small to moderate effect sizes comparable to CBT for anxiety and depression, with advantages in client satisfaction and therapist adherence. The limitations are real: publication bias, small sample sizes, and a tendency for researchers in this field to also be the practitioners designing the interventions. That does not make the findings invalid, but it means you should not treat SFBT as a silver bullet.