
Why Most SFBT Treatment Plans Miss the Point
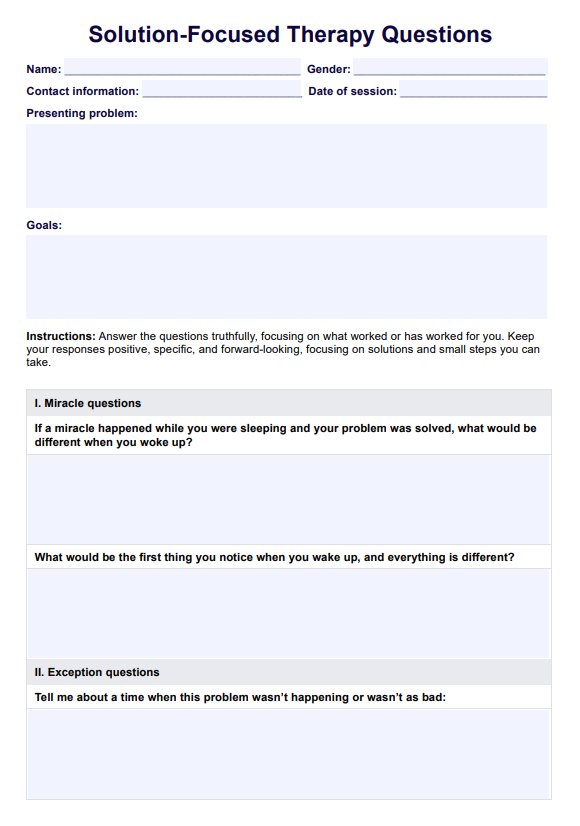
I have spent more hours than I care to count watching therapists struggle with solution focused therapy treatment plan example documents that read like generic templates stamped with the SFBT label but missing everything that makes the approach actually work. The standard form asks for problem statements and goals. That is the wrong ask. SFBT does not work from problems. It works from desired futures and client exceptions. When you build a treatment plan around what the client wants instead of what is broken, everything else clicks into place faster. Here is the basic structure I use now after going through three different electronic health record systems that made this harder than it needed to be: Presenting Concern: One sentence. No diagnosis bloat. Example: "Client reports difficulty engaging with teenagers in the home, resulting in repeated arguments."
Goal Statement: This is where most people mess up. The goal has to be something the client can do, observable, and framed positively. Not "reduce conflict." That is vague and negative. Write "Client and teenagers will identify three mutually agreeable household routines within two sessions." Current Functioning Baseline: A single scaling question result. Ask the client to rate their current situation on a zero to ten scale. Write down the number. That number becomes your baseline and your progress marker. Nothing else needed here. I used to try to fill pages with behavioral descriptions. Scaling questions replaced all of that and took thirty seconds instead of twenty minutes per session note. Exceptions: List any times in the last month when the problem was absent or less severe. Even small exceptions matter. If the client says their teenager walked into the kitchen and talked normally once last week, that goes here. That exception is your intervention material.
Interventions: Keep this section thin. SFBT interventions are things like the miracle question, scaling questions, exception finding, and the coping question. Write exactly which one you used and what the client said in response. Do not write a paragraph describing your therapeutic philosophy. That is not a treatment plan entry. That is padding. Homework: Any assignment given to the client between sessions. The task should be small, concrete, and tied directly to an exception or goal. "Notice what happens differently when you ask your teenager what they want instead of telling them what to do." Write the exact homework. Clients remember vague assignments poorly. Specific homework gets done. Progress Notes: Update the scaling number at the start of each session. That is your primary progress metric. Watch the number move. If it stays flat for three sessions, something is wrong with the goal or the approach, not the client.
Get the Full Details

I learned this last year when I had a client whose scaling numbers refused to budge for four sessions straight. The number stayed at a three the entire time. I was frustrated. I went back to the goal statement and realized it was framed around what I wanted, not what the client wanted. The teenager's behavior was not the client's problem to fix directly. The goal was about the parent changing how they initiated conversations. Once I reframed the goal around the parent's actions rather than the teenager's reactions, the scale moved from three to five over the next two sessions. The lesson was that SFBT requires goals the client controls, not outcomes they hope for.
What Beginners Miss About SFBT Documentation
The biggest mistake I see is treating the treatment plan as a compliance document rather than a working tool. The plan is supposed to get thinner as therapy progresses. If your plan looks the same in session eight as it did in session one, you are not doing SFBT. You are doing problem-focused therapy with a different name. The plan should show fewer exceptions needing documentation, shorter intervention descriptions, and a scaling number that has moved. Another thing nobody tells you about SFBT treatment plans is that the goal statement should be written in the client's language whenever possible. If the client says they want their house to feel less tense, do not rewrite that as "decrease household conflict." Keep the word "tense" or find the closest word the client used. Clients notice when you paraphrase their words into clinical jargon. It makes them shut down faster than you might expect. Scaling questions deserve more attention than they get in the literature. Most therapists ask one scaling question and move on. But the scaling question is the backbone of progress tracking. Start every session with a check-in scale. End the session with a closing scale. The difference between the opening and closing number tells you whether the session was productive without writing a single subjective impression. I have found that comparing opening and closing scales across sessions gives me a clearer picture of progress than any narrative note I have ever written.
There is a limitation worth noting. SFBT treatment plans do not handle acute crisis well. If a client presents with active suicidality, domestic violence, or severe substance withdrawal, a solution focused approach is not the primary intervention. You need a risk assessment, safety planning, and possibly medical evaluation first. SFBT assumes the client has enough stability to focus on goals and exceptions. When that stability is absent, the approach breaks down. I have seen colleagues try to run SFBT with actively suicidal clients and it went poorly for everyone involved. Use standard crisis protocols first. Bring in SFBT only after safety is established.
Practical Workflow for Building the Plan
Here is the sequence I follow now: Session one: Listen for the client's words. Write down three phrases they used. Pull the goal statement from those phrases. Ask the opening scaling question. Record the number. Identify one exception, even a small one. Assign one small homework task tied to that exception. Fill in the rest of the plan after the session when the initial notes are fresh. Session two and beyond: Start with the scale. Compare to last session's closing number. Ask what is different since last time. Look for new exceptions. Update the plan. If the number has moved up, note what specifically contributed to the movement. If it has stayed the same or gone down, adjust the goal or the homework immediately. Do not keep doing the same thing and expect different results.
The total time to complete a fresh treatment plan from scratch using this method is roughly twelve to fifteen minutes. The first session takes longer because you are building the foundation. Subsequent sessions require maybe five minutes to update. That is significantly faster than narrative-based approaches that demand two hundred words per session note minimum. Your billing department will not complain, and you will actually finish documentation on time. If you want a downloadable template, I use a simple table format in Google Docs. It has columns for session number, goal status, scale number, exceptions noted, interventions used, and homework assigned. One row per session. That is it. No fancy fields. No required diagnostic codes unless your insurance demands them. The template lives on my desktop and takes two clicks to open each morning. The most important thing to remember is that the treatment plan is a living document, not a filing requirement. It should change, shrink, and become simpler as therapy progresses. If it stays complex and detailed through the entire course of treatment, review your approach. The plan should reflect the work, not replace it.



