Understanding Prenatal Development Stages
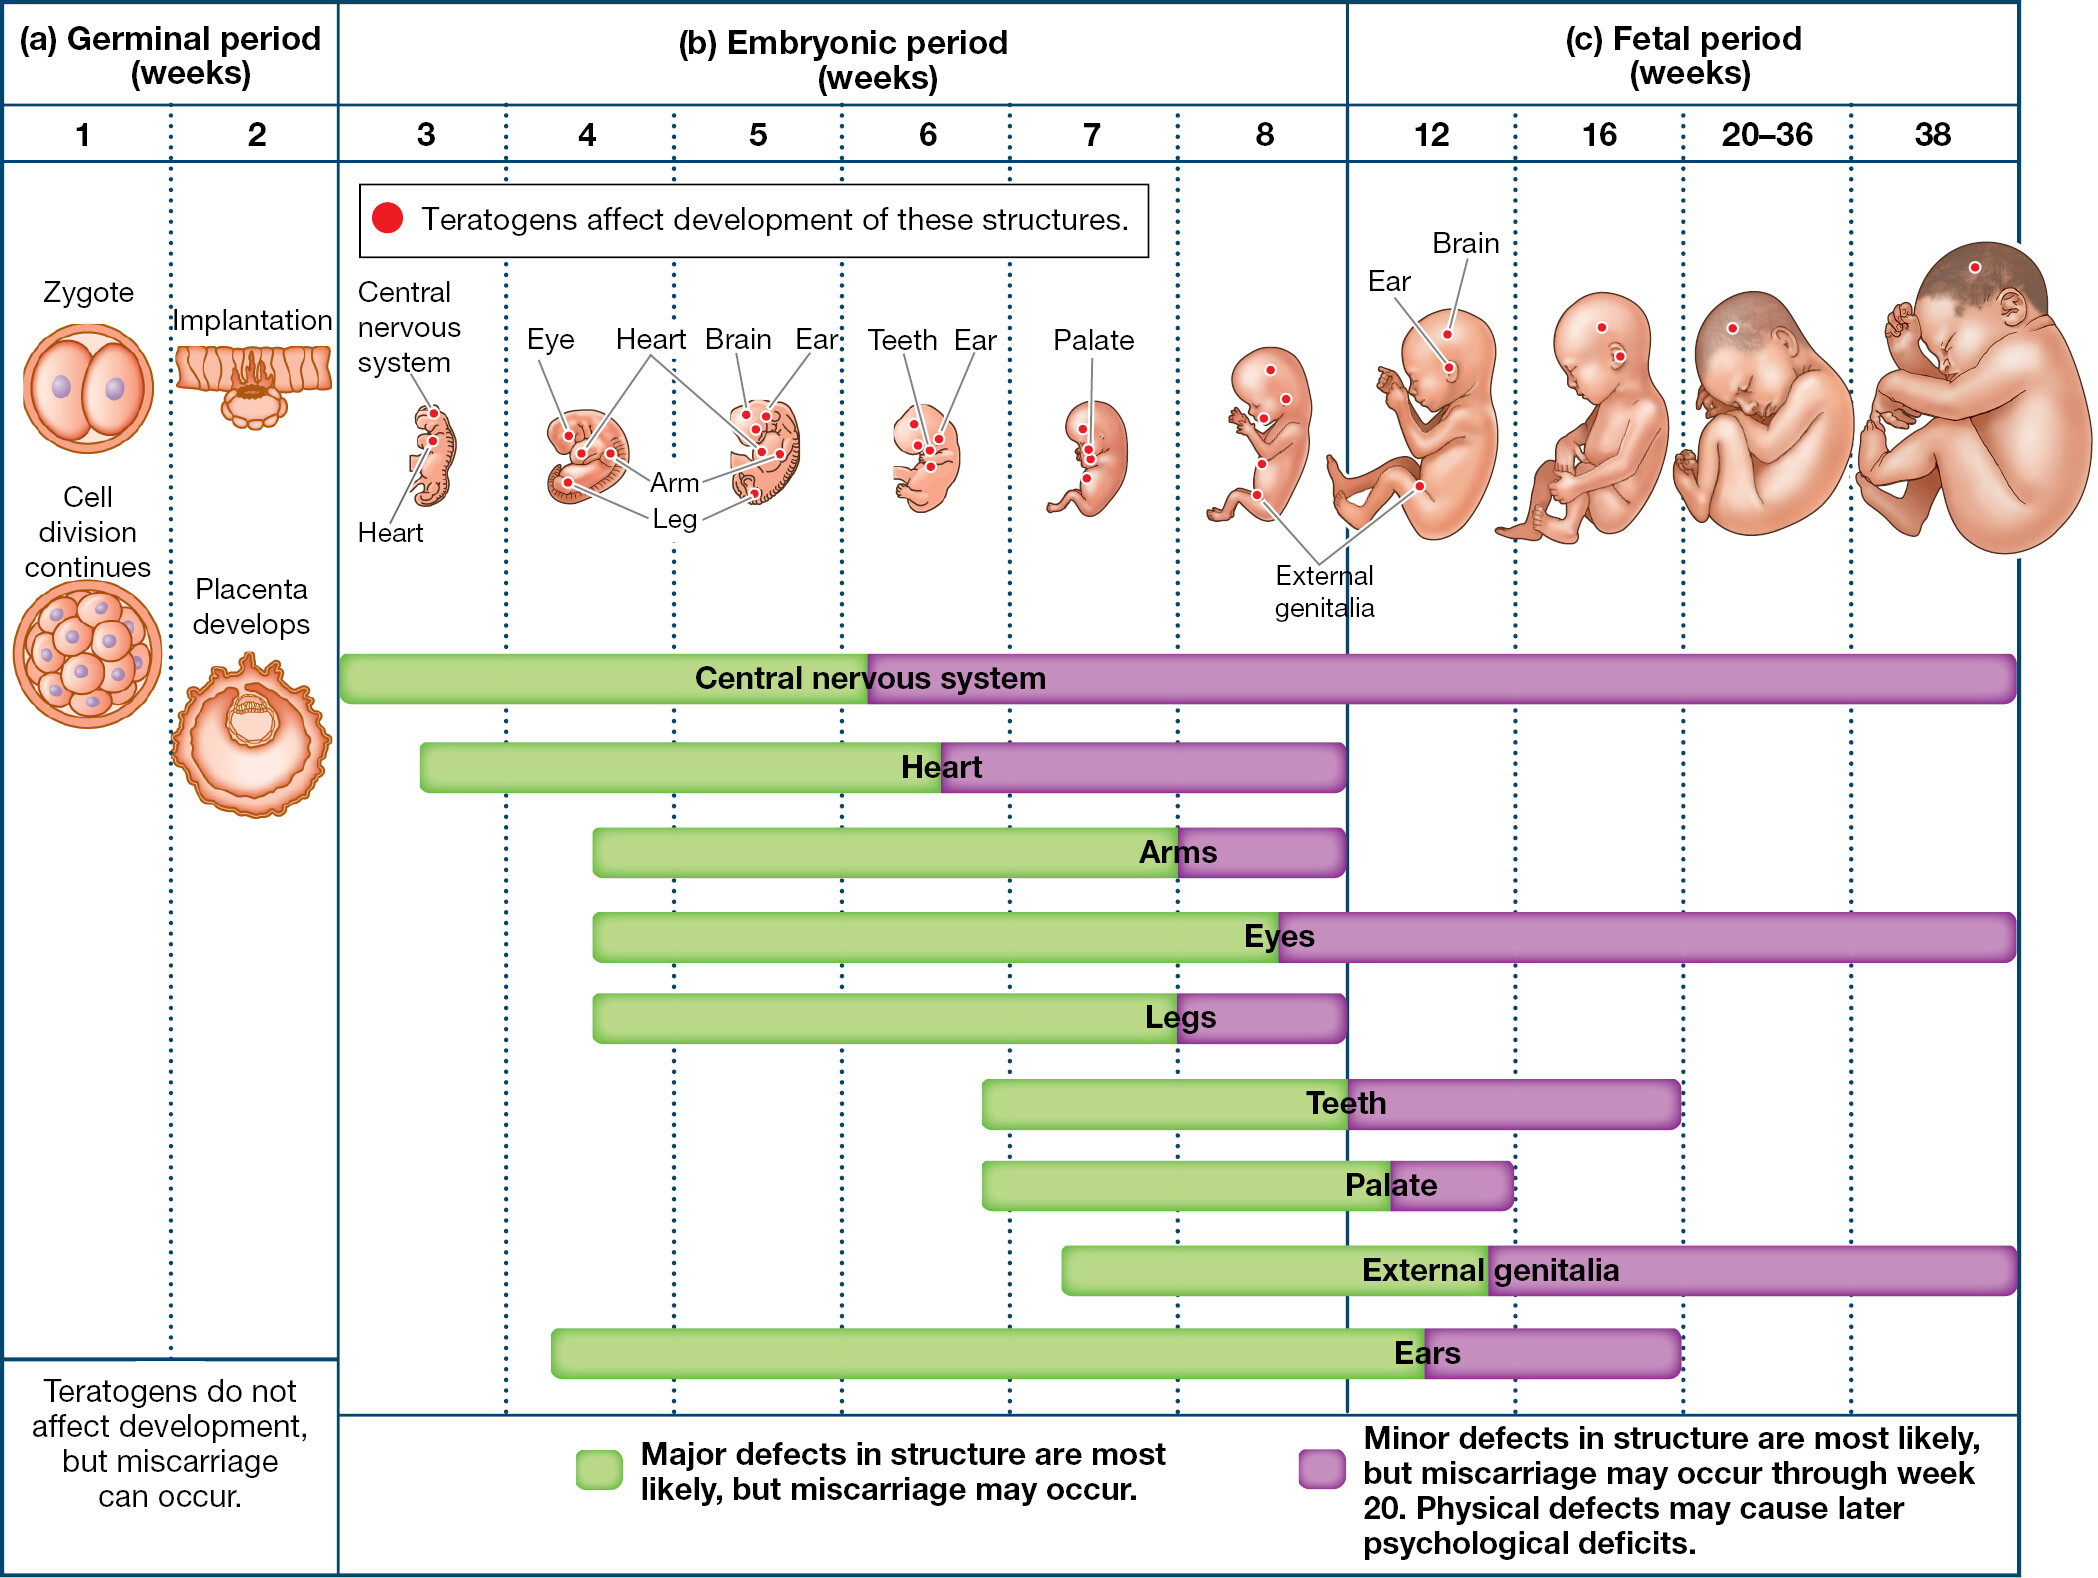
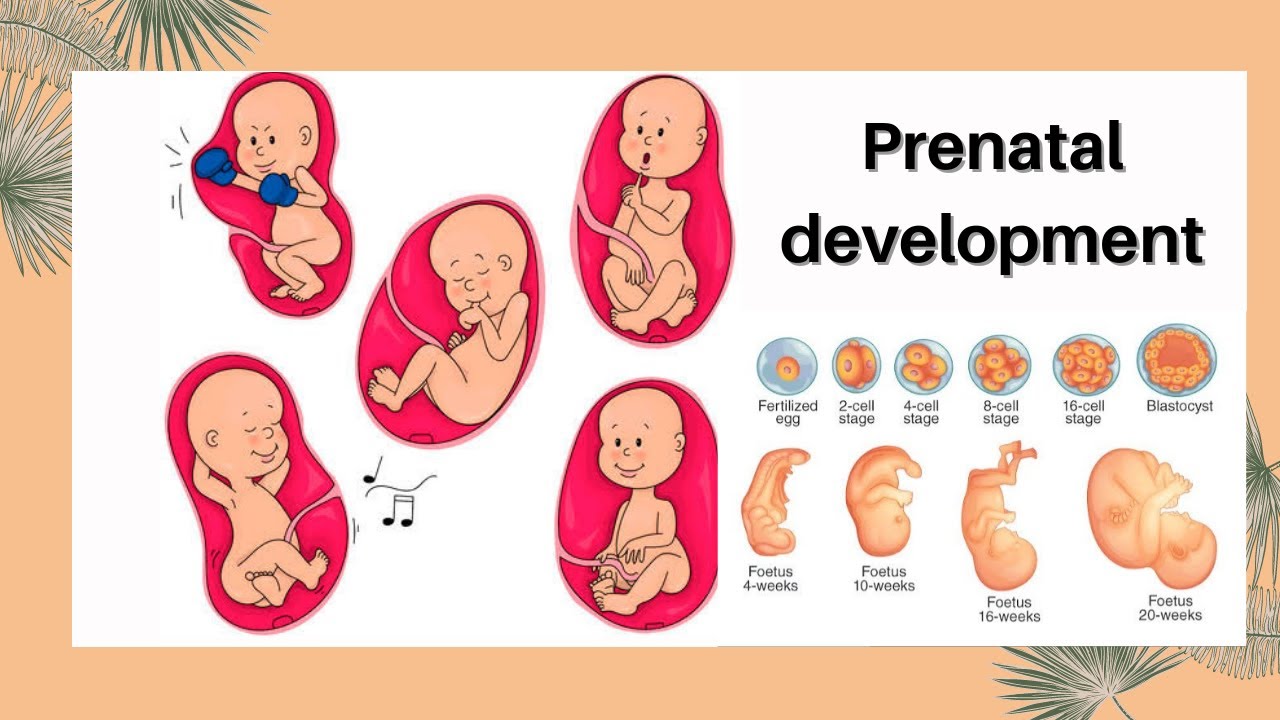
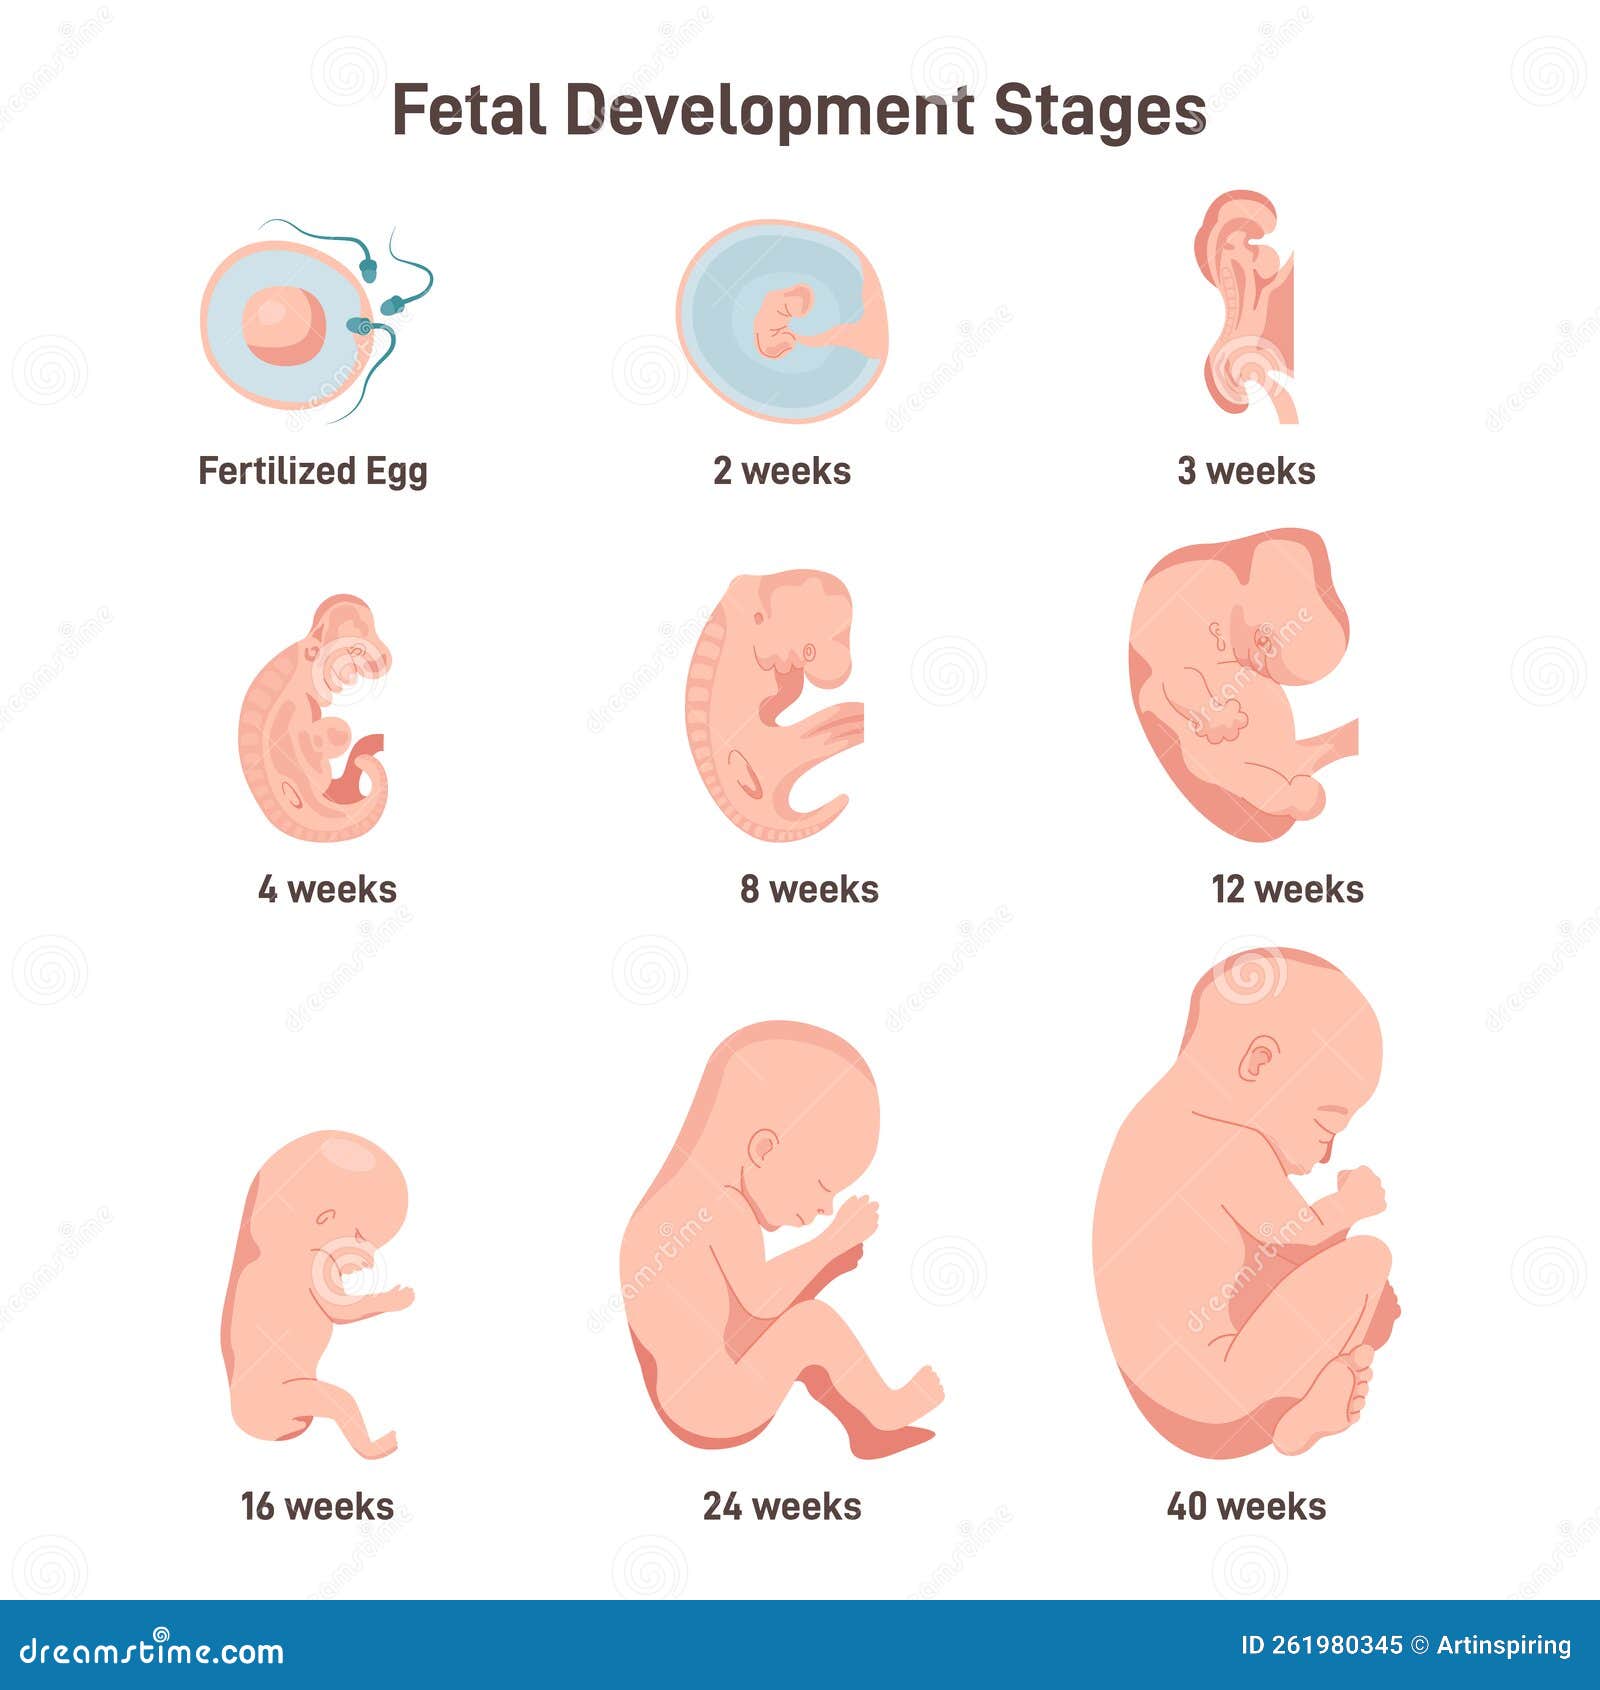
Prenatal development is the biological process that occurs from conception to birth, and it is typically divided into three major phases. The stages are well-documented in medical literature, but the way they present in clinical practice can differ from what you see in introductory textbooks. Here is how it actually breaks down, along with some things that people tend to get wrong about it. The first stage is the germinal period, which runs from fertilization through approximately day 14. The fertilized egg — now called a zygote — undergoes rapid cell division while traveling down the fallopian tube. It implants into the uterine lining around days 6 through 10. This is the most fragile phase, and most non-viable pregnancies fail here without anyone ever knowing. The body often sheds the tissue during what looks like a slightly late or heavier period. Next comes the embryonic period, spanning roughly weeks 3 through 8. This is where organogenesis happens. The neural tube closes around day 28. The heart begins beating near the end of week 4. Limb buds form, the eyes, ears, and nose take shape, and the basic architecture of every major organ system is laid out. This is also the period of highest teratogenic sensitivity — meaning exposure to certain substances, infections, or medications during these weeks carries the greatest risk of structural birth defects. After week 8, the same exposures are less likely to cause major malformations, though they can still affect function and growth.
The fetal period runs from week 9 until birth. The focus shifts from building organs to growing and maturing them. The lungs begin producing surfactant around week 24, which is why preterm births before that point carry such high mortality. Brain development continues aggressively through the third trimester. Myelin formation ramps up significantly in the last 10 weeks of gestation. Weight gain accelerates most in the final two months, with the fetus typically gaining about half its birth weight during that window. One thing that is not widely understood is that dating matters enormously for interpreting what is normal at any given point. A standard ultrasound used for dating measures the crown-rump length in the first trimester. If that measurement is off by even a few millimeters, the estimated due date shifts. I had a case where a clinic used a second-trimester biparietal diameter scan to establish gestational age instead of the recommended first-trimester crown-rump length measurement. The resulting due date was off by nearly two weeks. That small shift cascaded into unnecessary interventions later — inductions being proposed prematurely and growth scans being flagged as abnormal when the fetus was simply younger than calculated. Always insist on first-trimester dating when possible. Another common misunderstanding involves the timeline for "viability." Many people assume viability is a fixed threshold, like week 24. In reality, viability is a gradient, not a line. Outcomes at 22 weeks vary wildly by hospital, region, and the specific circumstances of the pregnancy. Some centers report survival rates below 20 percent at 22 weeks with significant morbidity. Others with advanced neonatal intensive care units may show better numbers. The concept of viability is more useful as a rough benchmark than a clinical boundary you can depend on.
Here is a practical note about monitoring: the standard prenatal visit schedule is not arbitrary. It is designed around the pace at which changes become detectable and actionable. In the first and second trimesters, visits are roughly every four weeks. At 28 weeks, they shift to every two weeks, then weekly after 36 weeks. This compresses the timeline right before the period when the most acute risks — preeclampsia, growth restriction, preterm labor — tend to surface. Skipping those late visits is one of the most common reasons serious complications go undetected until they are advanced. If you are looking for a structured reference, the most reliable resource is still the American College of Obstetricians and Gynecologists patient education materials, which are free online. The WHO also maintains detailed gestational development charts that are widely used internationally. Both are updated periodically as research on fetal programming and early-life health influences improves our understanding of what happens during each stage. There is a limit to what prenatal development frameworks can tell you. They describe typical trajectories. They do not account well for the effects of maternal health conditions like diabetes, hypertension, or autoimmune disorders, which can alter the timing and course of development significantly. They also do not capture the full range of outcomes from substance exposure, since the impact depends heavily on dosage, timing, and individual biological factors. For those variables, you need clinical evaluation, not just stage charts.
Get the Full Details