A Practical Guide to the Stanford Shoulder Exam
The Stanford shoulder exam is essentially a refined version of the standard orthopedic shoulder assessment, pulled together at Stanford University to standardize how residents and attending physicians evaluate rotator cuff pathology, labral tears, and AC joint issues. It's not some radical new invention. It's mostly clinical tests you've already seen in textbooks, organized into a logical sequence with slightly more attention to specificity than your average quick assessment.The core idea is systematic. You don't jump around testing things randomly. You follow a flow: inspection, palpation, range of motion, then specific provocative maneuvers in order of likelihood and clinical yield. Start with observation. Look for atrophy of the supraspinatus or infraspinatus fossa. That tells you something about chronicity. Then check for scapular winging and any obvious deformity at the AC joint. A swollen joint isn't hiding anything. Next is active and passive range of motion. You note pain arcs, restrictions, and the quality of movement. If someone can't abduct past 90 degrees, you're dealing with something real, not just tightness. Active abduction that's normal but painful with resisted abduction changes the picture entirely. That's where you start thinking rotator cuff.
The Provocative Tests and What They Actually Mean
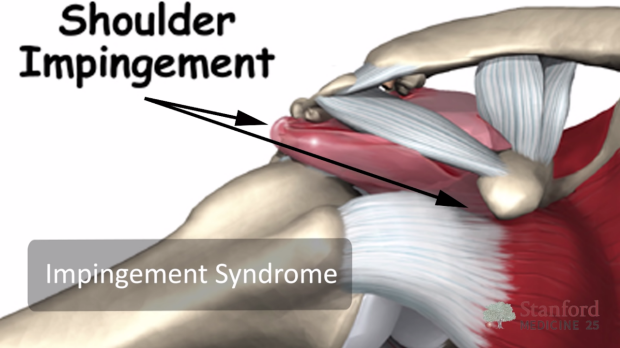
Neer's impingement test and Hawkins-Kennedy are workhorses. You do them early because they take ten seconds and rule things in or out pretty reliably. A positive Neer's means the humeral head is compressing the supraspinatus against the acromion when you passively forward flex the arm with the thumb down. Positive test shows up roughly 90% of the time with subacromial impingement, but it's not specific. Rotator cuff tears, calcific tendinitis, and even biceps tendonitis can trigger a false positive. The Jobe or empty can test isolates the supraspinatus. Arm at 90 degrees abduction, 30 degrees horizontal adduction, thumb pointing down. Push down while they resist. Weakness here compared to the other side is a good sign. But here's the thing most people miss: grip strength matters. If the patient can't grip your hand because they're guarding on the affected side, the resistance isn't reliable. I learned this the hard way with a construction worker who had a painful shoulder and a surprisingly weak empty can test. His grip on that side was shot from manual labor. Retracted the elbow, had him brace against the table, and the test became meaningful. The drop arm test is brutal but simple. Abduct the arm to 90 degrees and ask them to lower it slowly. If it drops straight down uncontrollably, that's a full-thickness supraspinatus tear. Sensitivity is around 57%, so a negative doesn't rule it out. I once dismissed a drop arm test as negative because the patient was just being careful, slowly lowering through pain rather than letting it drop. Asked them to relax completely, and sure enough, the arm cascaded down. Second look at the MRI confirmed the tear.
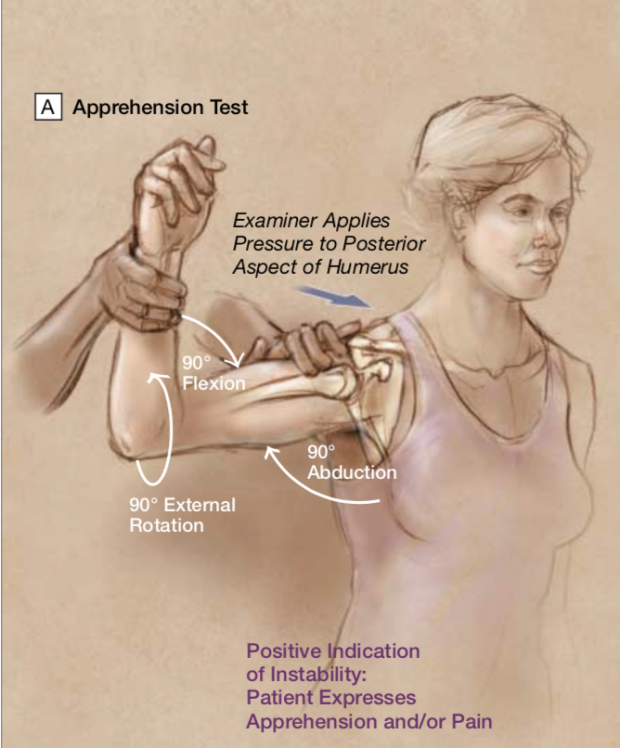
For labral pathology, you're looking at the O'Brien active compression test and the crank test. O'Brien's is done with the arm forward elevated at 90 degrees, adducted 10-15 degrees, thumb down. You apply downward pressure and they resist. Then repeat with the thumb up. Pain with thumb down but not thumb up points to a superior labrum tear. It's specific but not sensitive, which means a negative O'Brien's proves nothing. Sensitivity sits around 58%, specificity around 94%. The apprehension test is for anterior instability. External rotation with the arm abducted to 90 degrees. If the patient looks like they think the shoulder is going to pop out, that's positive. Relocation test follows — you apply posterior pressure with the other hand and confirm that external rotation improves. This combo is useful for diagnosing anterior shoulder instability. Bankart lesions, Hill-Sachs deformities, the whole anterior curtain.
Get the Full Details
Pitfalls You Won't See in the Literature
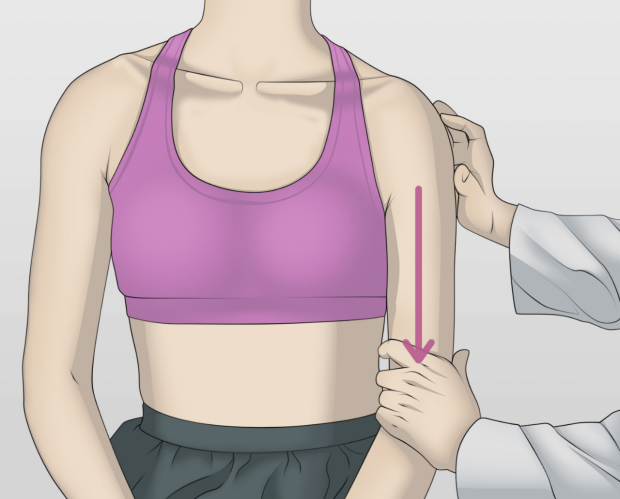
One thing the Stanford protocol emphasizes that many general programs gloss over: compare everything to the contralateral side. Not just for weakness, but for end-feel and pain reproduction. A patient with bilateral hypermobility might show a positive apprehension test on both sides, but only one is symptomatic. Context matters more than the test result alone. Another issue is examiner variability. Neer's test and Hawkins-Kennedy are notoriously operator-dependent. One person does a slow, controlled impingement maneuver while another just yanks the arm forward. The Stanford exam stresses standardized speed and force. You're not supposed to slam the arm into impingement. You're supposed to bring it there deliberately and see what happens. Also worth noting: body habitus skews results. Larger patients with more subcutaneous tissue give you less tactile feedback on bony landmarks. You lose the ability to palpate the bicipital groove cleanly. You work around it by using the patient's own anatomy — having them internally and externally rotate while you trace the groove with both hands instead of trying to pinpoint it with one finger.
Where It Falls Short
The Stanford shoulder exam is a clinical tool, not a diagnostic finale. Imaging beats physical exam for structural pathology. An MRI will show you a partial-thickness supraspinatus tear that every maneuver in the book missed. Ultrasound done by someone competent is nearly as good and costs less. The exam narrows the differential. It doesn't replace imaging when you suspect a significant structural problem. The exam also struggles with concurrent pathologies. A patient can have both rotator cuff tendinopathy and a SLAP tear, and the tests overlap. Positive Neer's, positive O'Brien's, painful arc, weakness on Jobe. Now you're guessing. That's when imaging becomes mandatory. If you're looking for a downloadable reference sheet, Stanford University's orthopedic and sports medicine department publishes pocket guides and pocket cards for these exams. They circulate widely among residency programs. The exact PDF isn't hosted publicly on a single URL that stays stable, but searching for the Stanford Shoulder Exam pocket card or the Stanford orthopedic clinical skills guide gets you to what you need.
The bottom line: learn the tests, learn their sensitivity and specificity, and use them as a funnel. Not a verdict.