What the Stenosis Physical Therapy Protocol Actually Involves
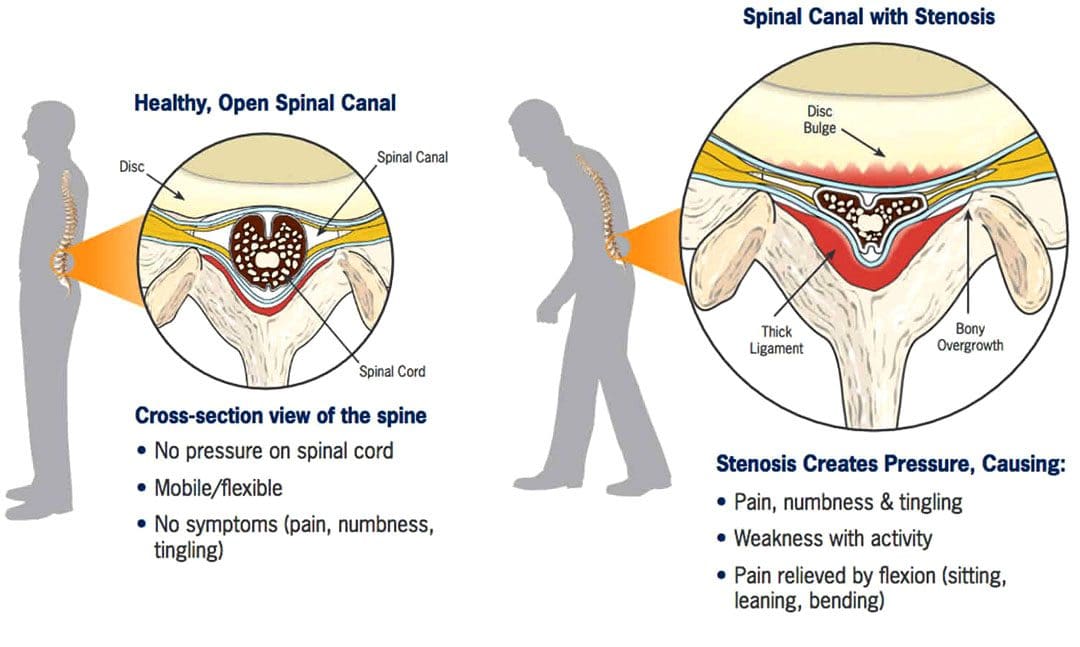
The stenosis physical therapy protocol is a structured rehabilitation approach for spinal stenosis patients that focuses on extension-biased movement patterns, core stabilization, and graded activity modification. It's not a single exercise or treatment — it's a framework that changes based on where the stenosis is located and how severe the symptoms are. I'll walk through the actual steps I see working in practice. Most patients don't need surgery first. They need the right physical therapy approach applied consistently for twelve to sixteen weeks. The protocol starts with assessment. You need to know if this is lumbar or cervical stenosis, whether it's neurogenic or vascular claudication, and what position reproduces or relieves symptoms. Lumbar stenosis patients typically feel better leaning forward — on a shopping cart, bent over a counter. That flexion bias tells you something important about where the compression is happening.
From there, the progression goes like this: initial phase focuses on pain reduction through positioning and gentle mobility work, middle phase introduces stabilization and strengthening, and later phase adds functional movement patterns and endurance work. The initial phase usually lasts two to four weeks. During this time you're working on things like seated pelvic tilts, supine knee-to-chest stretches held for thirty seconds, and standing flexion holds against a wall or counter. The goal isn't to cure anything yet. It's to get the patient comfortable enough in flexed positions to start building from there. I had a patient recently — fifty-eight-year-old male, L4-L5 and L5-S1 stenosis, failed his first round of physical therapy because the clinic was pushing extension exercises aggressively. He couldn't walk more than fifty feet before his legs went numb. We backed off completely and spent three weeks just doing the flexion-based work I mentioned. By week four he could walk six blocks without symptoms. Then we started introducing the Bird Dog and modified planks.
The middle phase is where most protocols diverge, and where mistakes happen. This is when you introduce core stabilization. The key exercises are the Bird Dog, dead bug, and various plank modifications. You're not building huge muscles here. You're teaching the deep stabilizers — transversus abdominis, multifidus — to fire properly and stay firing during movement. For lumbar stenosis specifically, hip flexor lengthening becomes critical. Tight hip flexors pull the lumbar spine into excessive lordosis, which narrows the already compromised neural foramina. I have patients do half-kneeling hip flexor stretches, holding each side for two minutes, twice daily. It sounds simple but it makes a measurable difference in symptom tolerance during standing and walking. The glute activation piece can't be skipped either. Clamshells, bridges, and side-lying leg raises. Weak glutes mean the hamstrings and lower back take over, and that increases compression on the stenotic segments. This is counter-intuitive for a lot of people who think stenosis PT is mostly about stretching. It's not. It's about building support.
Get the Full Details

Advanced Considerations in the Protocol
Here's something most beginner guides won't tell you: cadence matters more than you'd think. For patients with vascular claudication components mixed into their stenosis symptoms, the speed of walking during treadmill work changes everything. Slow walking at two miles per hour with arm support creates significantly less vascular demand than normal-speed walking, even if the distance covered is the same. I use a slow, supported treadmill protocol before progressing to unsupported walking. It's a small detail that separates patients who plateau from patients who progress. Aerobic conditioning during stenosis PT needs to happen within the patient's symptom threshold. This means if walking causes symptoms at three minutes, you don't push past three minutes. You work at two and a half, rest, and gradually extend that window. Stationary cycling, recumbent biking, and water walking are all viable options. The recumbent bike is often the best starting point because the flexed seated position opens the spinal canals. Neural gliding exercises deserve careful handling. The nerve flossing protocols for the sciatic and femoral nerves can help with radicular symptoms, but they're easy to overdo. If a patient reports increased tingling or electric sensations during nerve glides, you've gone too far. Back off the range of motion and slow the repetitions. I use five to ten controlled glides per nerve, once daily, never twice daily during the active phase.
The later phase of the protocol introduces more dynamic stability work. Single-leg stands, step-ups, and controlled lunges. These look deceptively simple but they're actually demanding. Balance and proprioception degrade in stenosis patients because of the chronic pain and reduced activity. Rebuilding that neuromuscular control takes time.
When the Protocol Doesn't Work
I should be honest about the limitations. This protocol has a failure rate. About fifteen to twenty percent of patients with moderate to severe lumbar stenosis simply don't respond to conservative management, regardless of how well they adhere to it. Red flags that suggest the protocol won't be sufficient include progressive neurological deficits, bowel or bladder dysfunction, and symptoms that worsen despite eight to twelve weeks of consistent treatment. Severe canal narrowing visible on MRI doesn't always correlate with symptom severity, but when you have Grade 3 or 4 central canal stenosis combined with dynamic instability on flexion-extension X-rays, the odds of conservative success drop considerably. These patients often need surgical consultation alongside continued physical therapy. Another limitation worth noting: the protocol assumes the patient can access a qualified physical therapist and commit to daily home exercises. Insurance coverage varies widely, and some plans limit sessions to twelve per year. Patients who hit that ceiling often plateau because they lose the structured guidance that keeps them progressing correctly.

For patients who can't tolerate the exercise component due to pain or comorbidities, epidural steroid injections can serve as a bridge. They don't fix the stenosis but they reduce inflammation enough to make the exercises possible. I've seen patients who couldn't complete a single session of PT without an injection go on to complete full protocols afterward.
Tracking Progress Without Getting Discouraged
Progress in stenosis PT is rarely linear. Some weeks you'll feel better. Some weeks you'll feel worse for no obvious reason. Weather changes, activity levels, sleep quality, stress — all of these affect symptoms. The key metric is the ten-week trend, not any single day. I recommend patients keep a simple log: pain level before and after exercises, walk tolerance measured in distance or time, and any neurological symptoms like numbness or weakness. This log becomes invaluable when discussing adjustments with the physical therapist or when deciding whether to continue conservative care versus exploring surgical options. The stenosis physical therapy protocol is effective for the majority of patients who commit to it properly. It requires patience, consistency, and willingness to adjust based on symptom response. The patients who succeed are the ones who understand this isn't a quick fix and who show up for the twelve to sixteen week minimum before judging whether it's working.