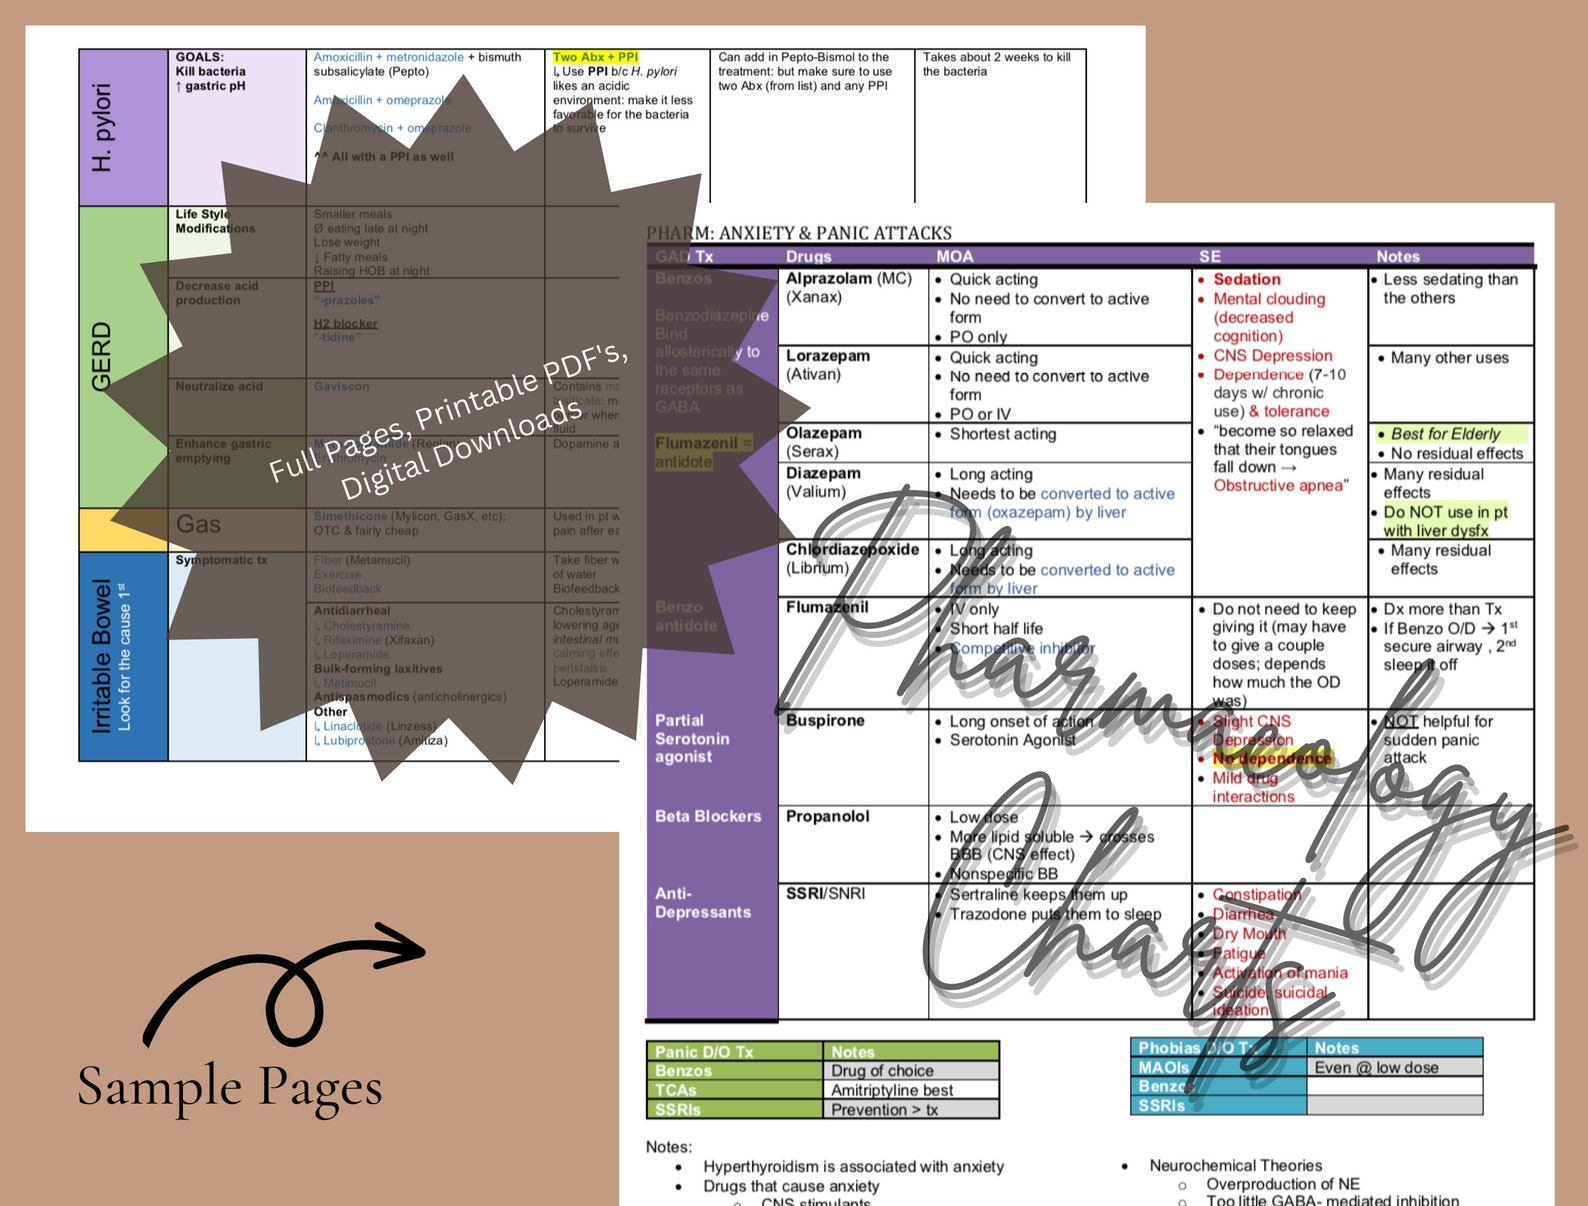
The brutal truth about studying pharmacology
Most students approach pharmacology the wrong way from day one. They try to memorize drug names like they're vocabulary lists, which is a guaranteed path to forgetting everything by midterms. I watched this happen repeatedly during my time tutoring pharmacy students. The ones who actually retained information did it differently. The system I'm about to describe isn't a shortcut. It's a method that took me years to refine after failing multiple comprehensive exams using conventional study habits. It works because it mirrors how pharmacology actually gets tested and applied in clinical settings.
Step By Step For Pharmacology Comprehensive
The foundation of any solid pharmacology review is understanding classification systems. You cannot reasonably memorize 500 drugs if you haven't already grouped them into their therapeutic categories and subcategories. This is where most study guides fail. They list drugs alphabetically or by trade name. That's lazy and ineffective. Start by building your own hierarchical maps. Use a blank page or a digital whiteboard. Write the main therapeutic class at the top — let's say ACE inhibitors for hypertension. Underneath, list every drug in that class. Not the trade names. The generic names. Caprilapril, enalapril, lisinopril, ramipril, quinapril. Then add the mechanism under each one. Then add the key side effect under that. You're building a mental scaffold, not a list. The second step is pharmacokinetics, and this is where students consistently lose points on exams. Absorption, distribution, metabolism, excretion. The PK parameters like half-life, volume of distribution, clearance rates, and bioavailability aren't optional details. They're the reason two drugs in the same class behave completely differently in real patients. I learned this the hard way during a clinical rotation when I nearly recommended a dosing adjustment for a patient with renal impairment based on a drug's half-life that I had conflated with a similar medication in the same category. The drug in question was renally cleared while its look-alike counterpart was hepatically metabolized. One dosing error away from an adverse event.
The workaround I use now is simple. Every drug I study gets a PK profile card. Front side has the four parameters with specific numbers where relevant. Back side has the clinical implications — what organ dysfunction requires dose adjustment, what food interactions matter, what CYP enzyme is involved. It takes more time upfront but eliminates the confusion between similar drugs later. Pharmacodynamics is the next critical piece. Mechanisms of action at the molecular and cellular level. Receptor binding affinities. Agonist versus antagonist behavior. Inverse agonists. Partial agonists. These distinctions matter enormously on comprehensive exams and even more in practice. A partial agonist like buprenorphine behaves fundamentally differently from a full agonist like morphine, and that difference has real clinical consequences for pain management and addiction treatment. Here's something textbooks don't emphasize enough: the therapeutic index. Drugs with narrow therapeutic windows — warfarin, lithium, digoxin, phenytoin, theophylline — require a completely different study approach than drugs with wide safety margins. For narrow-therapeutic-index drugs, you need to know the exact monitoring parameters, the signs of toxicity at the clinical level, and the antidotes or reversal agents. This isn't nuance. This is the difference between passing and failing the clinical portion of comprehensive exams.
Get the Full Details

The third major component is adverse effects and drug interactions. This is where comprehensive exams tend to separate the students who truly understand pharmacology from those who just memorized facts. You need to know the most common side effects for every drug class, but more importantly you need to understand why those side effects occur. A side effect you understand mechanistically is nearly impossible to forget. A side effect you memorized in isolation will vanish from your recall within weeks. Drug interactions require the same mechanistic understanding. CYP450 induction versus inhibition. P-glycoprotein interactions. Pharmacodynamic synergism and antagonism. When you understand that fluconazole inhibits CYP2C9 and therefore increases warfarin levels, you don't need to memorize that specific interaction separately. It follows logically from the mechanism. Therapeutic applications come next. For each drug class, you need to know the first-line indications, the alternative indications when first-line therapy fails or is contraindicated, and the special populations where the drug is particularly useful or particularly dangerous. Pregnancy categories used to be the standard framework for this. The newer Pregnancy and Lactation Labeling Rule is more detailed but less intuitive. Either way, you need to know which drugs are teratogenic and which are relatively safe.
Let me address a common pitfall here. Many students spend disproportionate time on brand name drugs and commercial combinations. This is inefficient. Comprehensive exams test on generic names and individual components. If you know that metformin is a biguanide that decreases hepatic glucose production and increases peripheral insulin sensitivity, you understand the entire class. You don't need to separately memorize every combination product that includes metformin. The fourth component is anti-infective pharmacology, which is its own beast. Antibiotics, antivirals, antifungals, antiparasitics. The sheer volume of material here is staggering. The most efficient approach is to study by mechanism of action rather than by organism. Learn how beta-lactams work — cell wall synthesis inhibition. Learn which bacteria are susceptible and which have resistance mechanisms. Then move to macrolides — protein synthesis inhibition at the 50S subunit. The pattern becomes obvious quickly. Antimicrobial resistance deserves more attention than most students give it. MRSA, VRE, ESBL-producing organisms, carbapenem-resistant Enterobacteriaceae. Knowing the resistance mechanisms — beta-lactamases, efflux pumps, target site modification — is more valuable than memorizing which drug treats which organism. Resistance patterns change. The mechanisms don't.
One practical note about study materials. The current comprehensive exam blueprints change periodically. The NAPLEX and other licensing exams update their content specifications. I've found that relying solely on a single review book creates blind spots. Cross-reference at least two resources. When the information conflicts, investigate why. The discrepancy usually reveals a concept you haven't fully grasped yet. The scheduling aspect matters more than students realize. Pharmacology content is cumulative. Today's material builds on yesterday's. Spaced repetition is non-negotiable. Review drug classes from two weeks ago every third day. Review from one month ago every five days. This isn't theoretical. Students who use spaced repetition systems retain roughly three times more material over a semester compared to cramming, and the retention persists well past the exam date. Flashcards work if used correctly. Digital systems with algorithmic scheduling are better than physical cards for this volume of material. The key is active recall. Don't flip the card immediately. Force yourself to retrieve the answer before checking. The struggle of retrieval is what builds long-term memory. Passive recognition on a flipped card tells you nothing about whether you can actually recall the information under exam conditions.
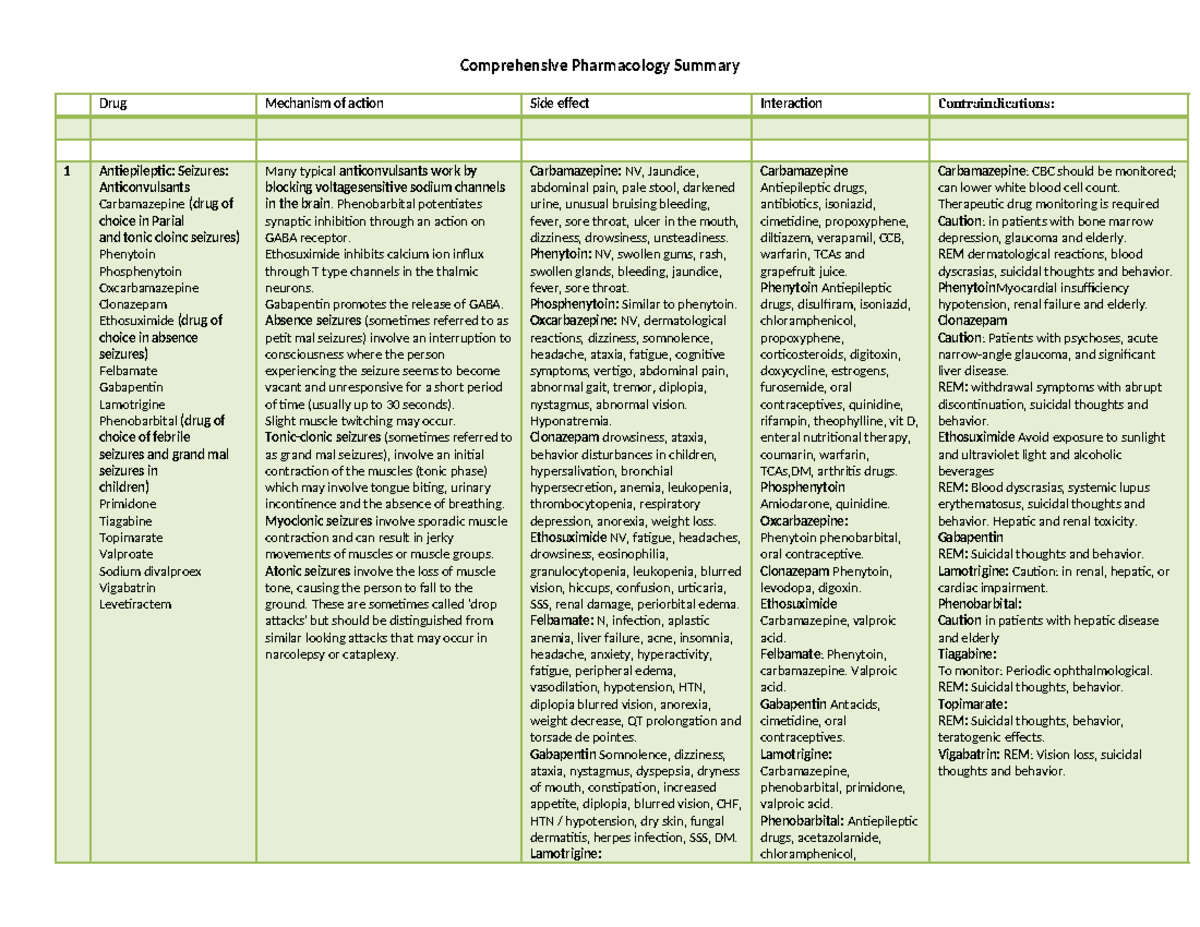
Practice questions are essential but require careful use. Many review question banks contain questions that are either too simplistic or oddly specific. Focus on questions that test your ability to apply knowledge to clinical scenarios. The comprehensive exams increasingly use case-based questions. If you've only studied fact sheets without clinical context, you'll struggle with the application questions even if you know all the facts. I should mention a limitation that most study guides won't address. This method requires significant initial investment of time. Building your classification maps, creating PK profile cards, and maintaining spaced repetition schedules adds roughly two hours per week to your study routine during the first month. Students who are already behind on coursework often find this unsustainable alongside their regular class load. In those cases, prioritize mechanism-based understanding over comprehensive card creation. Understanding why a drug works will carry you further than having an elaborate filing system you never maintain. Another constraint worth noting. This approach works exceptionally well for students who already have a foundation in physiology and biochemistry. If those subjects are weak, pharmacology will feel impossibly abstract. Mechanisms of action don't make sense if you don't understand normal cellular function. I've seen students attempt this method while simultaneously struggling with basic physiology courses. It doesn't work well. Those students benefit more from a simplified classification approach first, then layering in mechanisms once their foundational knowledge strengthens.
The most counter-intuitive insight I can share is this: spending extra time on drug classes with few members is usually more efficient than spending equal time on massive classes with dozens of drugs. The minority of drugs account for the majority of clinical use and exam questions. Master the high-yield classes thoroughly — antihypertensives, antibiotics, analgesics, psychiatric medications — before diving deep into obscure drug classes that appear infrequently on exams. Comprehensive pharmacology study is ultimately about pattern recognition. Once you've studied enough drug classes, you start seeing similarities. Beta-blockers all share class effects regardless of selectivity. SSRIs all share mechanism regardless of half-life differences. Recognizing these patterns reduces the cognitive load dramatically and makes recall under pressure significantly more reliable. The final thing to keep in mind is that pharmacology is a living field. New drugs enter the market regularly. Old drugs get new indications or safety warnings. No study method can make you current with everything. Focus on building durable mechanistic understanding that will let you reason through unfamiliar drugs when you encounter them in practice or on exams you haven't specifically prepared for.