Where You Actually Find Stratified Columnar Epithelium in the Body
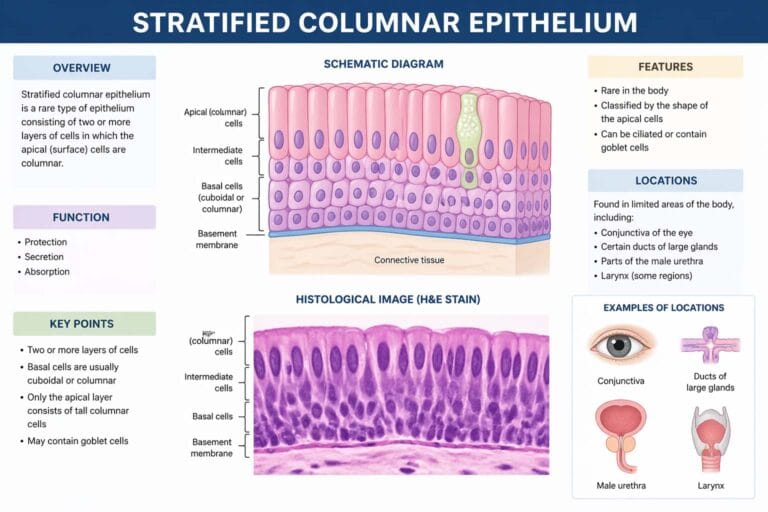
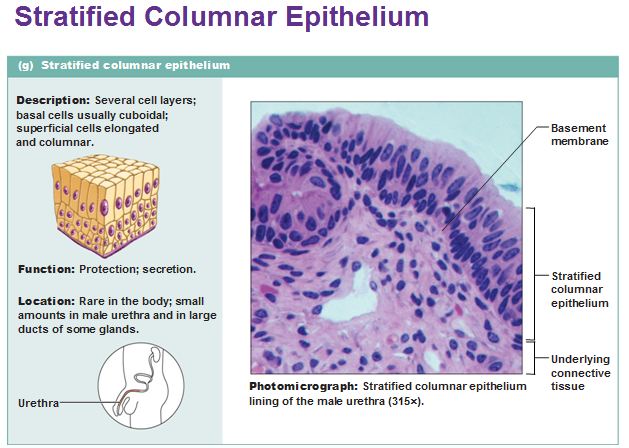
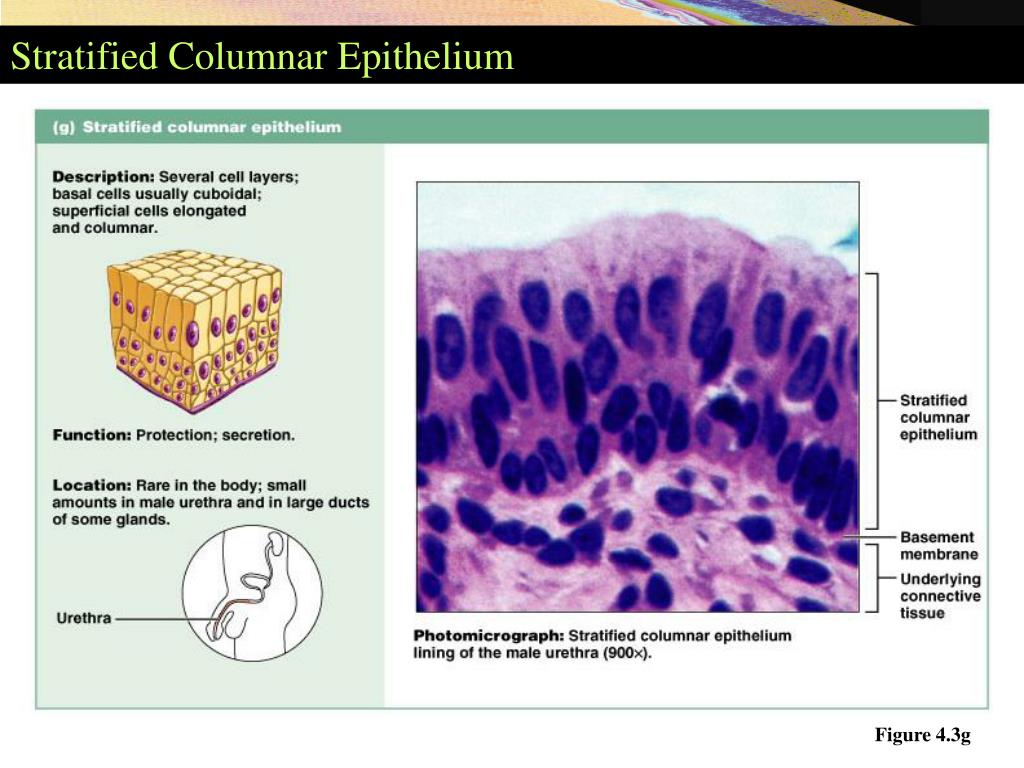
Most histology students spend more time looking at stratified squamous epithelium than anything else because it is everywhere. Skin, esophagus, vagina, anal canal. Stratified columnar epithelium is a different story. It is genuinely rare and if you are hunting for it in slide quizzes you will probably get confused about what you are even looking at. It appears in a handful of specific sites. The male urethra, particularly the membranous and spongy portions, contains patches of it. The large excretory ducts of certain glands like the parotid and submandibular salivary glands have localized regions. The conjunctiva of the eye, specifically the palpebral and fornical regions, shows stratified columnar epithelium with goblet cells interspersed. A small portion of the pharynx has this tissue type as well. The anal canal near the dentate line can show transitional zones where this appears. That is it. That is basically the complete list of clinically relevant locations. Every textbook mentions the same four or five sites and moves on quickly because there is not a lot to say about it.
Here is the practical problem that caught me off guard when I was reviewing biopsy slides from a urology rotation. The stratified columnar epithelium in the male urethra is patchy and discontinuous. On a low-power scan it looks like normal transitional or pseudostratified epithelium until you commit to high power and start counting layers. I spent a full block period trying to distinguish between normal stratified columnar and what I thought was metaplastic change in a post-instrumentation specimen. The key was recognizing that the superficial cells were truly columnar with basal nuclei aligned in a single layer rather than the irregular nuclear stratification you see with metaplasia. If the apical surface shows stereocilia, that is another marker for the distal urethral segment. One thing nobody emphasizes enough is that stratified columnar epithelium is often found in combination with other epithelial types at transition zones. The conjunctiva example is the cleanest one. You will have stratified columnar epithelium with goblet cells anteriorly, then it transitions abruptly into stratified squamous non-keratinized epithelium at the corneoscleral junction. On a histology exam if they give you a section of conjunctiva and ask you to identify the epithelium, picking just one type will make your answer incomplete. The tissue is almost never purely one type in those regions. Another counter-intuitive detail is that some of these locations undergo epithelial metaplasia under chronic irritation. The conjunctiva can develop squamous metaplasia with prolonged exposure to irritants or vitamin A deficiency. The urethral epithelium can similarly shift toward stratified squamous after repeated catheterization or infection. So when you identify stratified columnar epithelium on a slide, context matters enormously. The patient history and the anatomical level of the biopsy determine whether you are looking at normal tissue or a reactive change.
For anyone studying this for board exams, the high-yield fact is that stratified columnar epithelium is rare and mostly confined to the locations I listed above. Do not overcomplicate it by searching for it in places where it does not normally occur. The conjunctiva and male urethra are the two sites you are most likely to encounter on actual exam questions. The salivary gland ducts are mentioned less frequently but worth knowing for completeness.
Get the Full Details