Student Athlete Cardiac Assessment Module: A Practical Walkthrough
Most sports programs use some version of a cardiac screening process, but few do it consistently well. I spent years running these assessments across high school and collegiate programs, and what I'm about to describe is what actually works on the ground, not what looks good on paper. The module is essentially a structured screening tool designed to identify potential cardiac risk factors before an athlete is cleared for competition. It combines personal and family history questionnaires with basic clinical evaluation and, in some protocols, ECG interpretation. The goal isn't to catch everything - nothing does that - but to surface red flags that warrant further cardiology workup. I've seen programs treat this as a checkbox exercise and miss genuine pathology. I've also seen programs that over-screen and overwhelm their resources. The sweet spot is in the middle.
How to Set It Up Without Losing Your Mind
Start with the history questionnaire. This is where 80 percent of useful information lives. American Heart Association guidelines recommend specific questions about syncope, exertional chest pain, known cardiac conditions, and family history of sudden cardiac death or cardiomyopathy before age 50. Write those out clearly. Don't let parents interpret "heart trouble in the family" and leave it at that. Ask for specifics. Names. Ages. Causes of death if known. Next layer is the physical exam. Blood pressure in both arms, cardiac auscultation with the athlete positioned supine and standing, pulses in all four extremities. That's it. You're not doing a full medical here. You're looking for hypertrophic cardiomyopathy signs, murmurs, Marfanoid features, blood pressure abnormalities. The ECG piece is where things get complicated. Not every program should do ECG screening. The Italian model works because they have centralized interpretation infrastructure. If you're a single high school district without cardiology support, an ECG requirement will create more false positives than it solves. False positives mean referrals, waitlists, parental anxiety, and kids missing tryouts. I watched one program get 40 percent of their screened athletes flagged as abnormal on ECG, and after cardiology review, less than 5 percent actually had pathology. That's not a failure of screening. That's a failure of infrastructure to support the screening.
The Problem I Actually Faced
One year, I ran our Student Athlete Cardiac Assessment Module across three schools with about 1,200 athletes total. Everything was going fine until we hit a kid with a borderline QTc of 460 milliseconds. Normal variant in a lot of young male athletes, but the protocol flagged it. The cardiology referral queue was already six months deep from the false positive flood. His parent was panicking. He was panicking. We couldn't get him in for another four months. Here's what I did instead. I had the athletic trainer recheck the QTc using a different lead placement technique - some programs don't account for subtle electrode placement differences, and that shifts the measurement by 10 to 15 milliseconds. It came back to 442. Cleared. No cardiology referral needed. I documented everything, updated our screening SOP to include a mandatory recheck protocol before any automated flag triggers a referral, and stopped wasting specialist time on tech artifacts.
Get the Full Details

Things Nobody Tells You
First, the standard risk questionnaire has a sensitivity problem. Studies consistently show it misses about 50 percent of cardiac conditions that present during athletic participation. The Bethesda and AHA questionnaires are screening tools, not diagnostic tools. They catch the obvious stuff - the kid whose uncle died at 28 from arrhythmia, the one who passes out during sprints. But they won't catch the kid with early-stage ARVC who has no family history and no symptoms yet. Acknowledge this limitation to your program administrators. They need to know what this module can and cannot do. Second, echocardiogram thresholds matter more than most programs realize. If your protocol says "any abnormal ECG gets an echo," you'll drown your local echo lab. Most programs should establish clear pre-test probability criteria before ordering imaging. The Seattle Criteria for ECG interpretation in athletes exist for this reason. Use them. They were specifically designed to reduce false positives in young athletes by accounting for athletic heart remodeling patterns. Third, don't skip the second-year reassessment. A lot of programs do an initial screening at freshman entry and then assume the kid is fine for four years. Cardiac conditions develop. A normal ECG at 14 doesn't guarantee anything at 17. My program added a light-touch reassessment in the sophomore year - new questionnaire, BP check, symptom interview - and caught two kids who'd developed significant issues between screenings.
Download and Implementation Notes
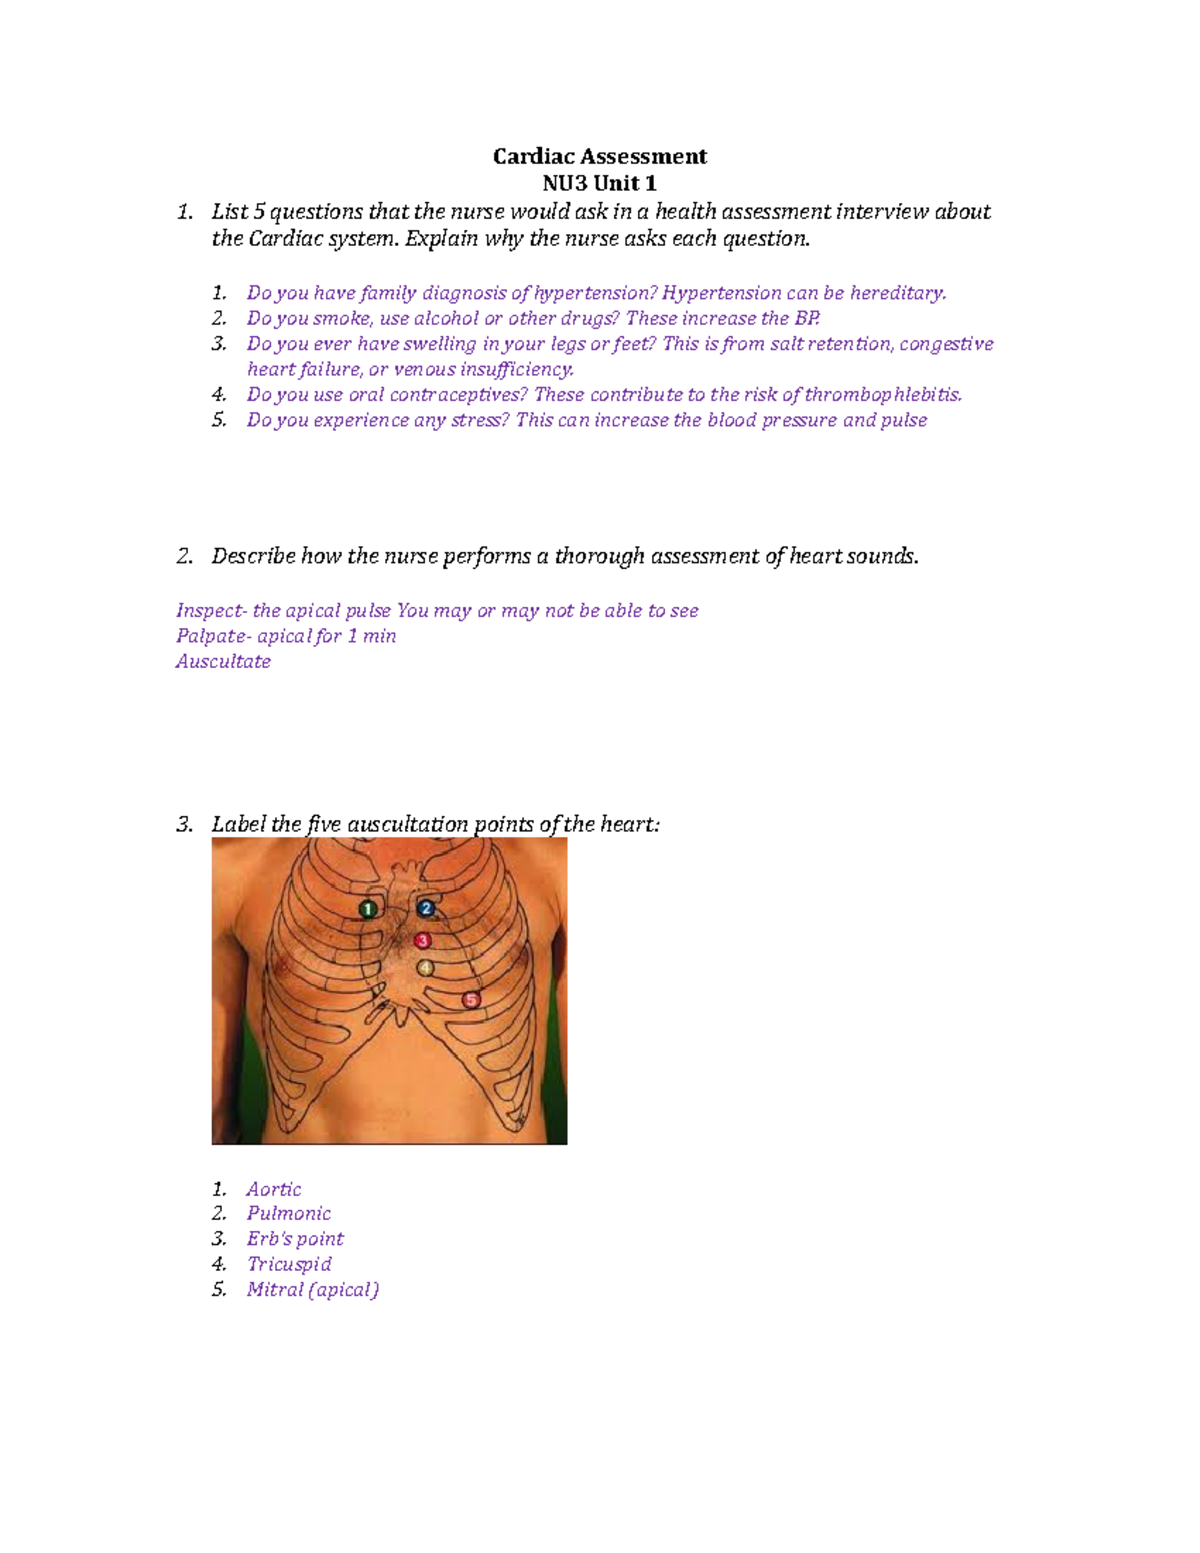
The base questionnaire templates are available through the AHA website and various state athletic associations. I'd recommend starting with the AHA 14-element screen as your foundation and layering your local protocol on top. The raw template is free. Customizing it for your population takes a bit more work. For the electronic version, some programs use platforms like MyPlayReady or state-specific systems. Others build their own forms in Google Forms or Microsoft Forms with conditional logic. I prefer building custom versions with conditional branching because you can make the workflow match your actual clinical process rather than forcing your process to fit someone else's form design. If a parent answers yes to syncope, the form should immediately pivot to follow-up questions about timing, context, and recovery. Generic linear forms don't do that well. Training is the part everyone underestimates. Your athletic trainers need to know how to actually perform the physical exam components, not just hand out clipboards. I've seen ATCs skip auscultation entirely because they didn't feel confident finding the right listening position. Spend one afternoon having them practice on each other. Five minutes per person. It makes a real difference in detection rates.
When This Module Fails Completely
It fails when you have low compliance. No amount of protocol design matters if half the parents don't return the questionnaire. We had a season where only 60 percent of incoming athletes had completed screening by the first practice. The remaining 40 percent were cleared with a simplified interim screen, but we missed two kids with concerning findings that would have been caught with full documentation. Go hard on compliance. Make it a condition of participation. Send reminders. Call parents directly. It also fails when your referral network is nonexistent. I worked at a program in a rural area where a genuinely positive screening result landed the family in a 90-mile drive to a pediatric cardiologist. The family dropped out of the referral chain because of logistics, not medical disagreement. If you're in a similar situation, build relationships with telecardiology services or partner with a university hospital that can do remote ECG review. It's cheaper than managing a kid who falls through the cracks. Finally, don't let a clean screening create false confidence. Sudden cardiac events in athletes do occur in previously screened individuals. The module reduces risk substantially but doesn't eliminate it. I'd rather have a program that screens rigorously and still experiences an event than one that skips screening entirely. But the data should inform how much you rely on the results, not how much you ignore ongoing vigilance.