Setting Up NG Tube Suction in Practice
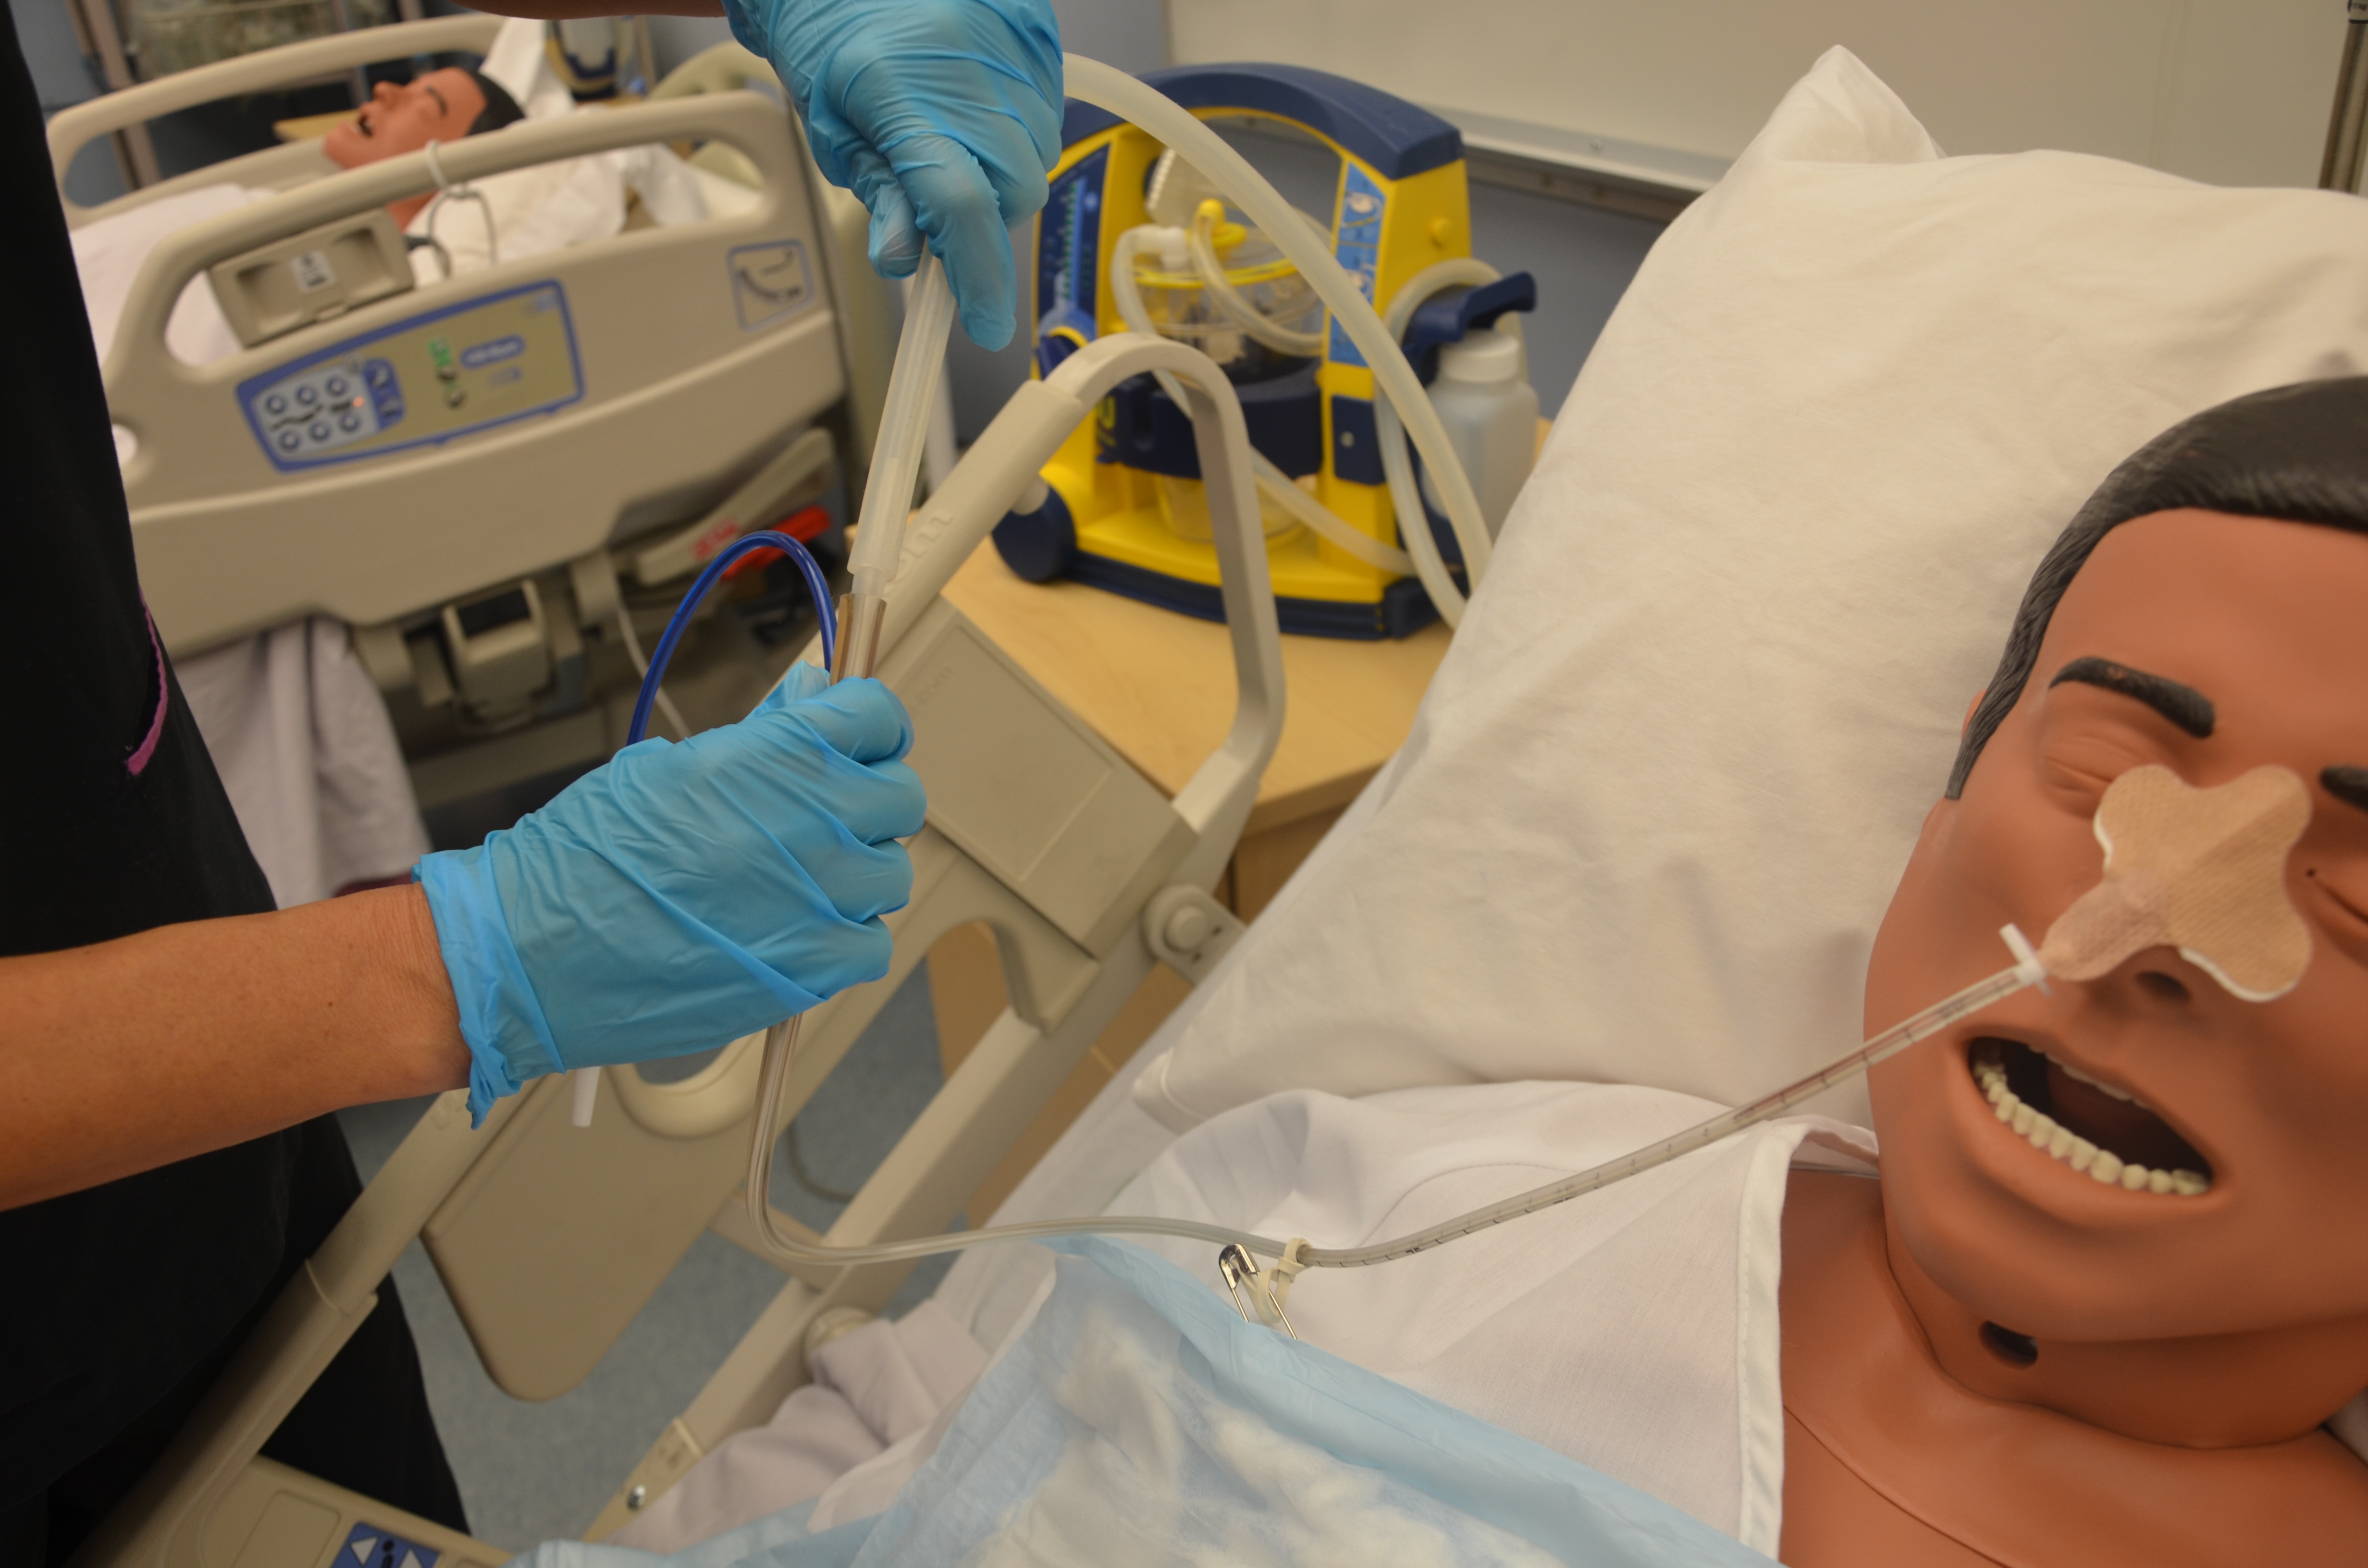
The basics: you have a nasogastric tube that's already in the stomach and you need to keep it decompressed. This isn't rocket science, but getting the pressure wrong can cause real problems fast. What you need on hand: The NG tube, a suction canister with measuring graduations, connecting tubing, a wall suction source with an adjustable regulator, and 50mL syringes filled with normal saline for flushing. Make sure the suction canister is rated for the pressure range you're working with—most hospital units handle this fine, but you'd be surprised how often someone grabs the wrong canister from the supply cart. Setting up the system: low-intermittent suction is the standard approach. You want a regulator set between 40-120 mmHg typically. Wall suction machines usually max out around 500+ mmHg, so the regulator is doing the heavy lifting to protect the gastric mucosa.
Suction For Ng Tube: The Procedure
Here's how I approach it, step by step. First, confirm the tube is actually in the stomach. pH testing of aspirate should read below 5.5 if it's gastric content. If there's any doubt, get an X-ray before connecting suction. I've seen cases where the tube tip was curled up in the esophagus and suction was applied anyway, causing nothing but patient discomfort and minimal drainage. Position the patient semi-Fowler's at 30-45 degrees or on their right side. Gravity helps drainage more than you'd think. Connect the NG tube to the suction apparatus. Turn the wall suction on and set the pressure. The regulator should be adjusted with the tubing disconnected from the patient—this lets you verify the actual pressure being delivered. I always check the gauge reading with the patient end open to air before connecting to the tube, just to make sure the needle moves and the mechanism isn't stuck. Set the pressure between 40 and 120 mmHg depending on clinical indication. Lower pressures for routine decompression, higher if you're clearing thicker material. Clamp the tube periodically during the day to let the gastric mucosa recover from continuous negative pressure. Leave it unclamped overnight in most post-operative cases.
Flush with 30-60mL of normal saline every 4 to 6 hours, or whenever drainage slows. Use a gentle push-pull technique with the 50mL syringe. Don't force it. If you meet resistance, don't increase pressure—that's how you irritate the gastric lining. Reposition the patient and try again. Sometimes the side hole is just abutting the gastric wall. Monitor the output. Note the volume, color, and character. Document everything. The canister has measurement lines for a reason—use them. If you're pulling more than 500mL in a single hour consistently, that's worth flagging. Expect 500-1500mL per day in typical post-op cases, but this varies wildly based on the underlying condition.
Get the Full Details
What Most People Get Wrong
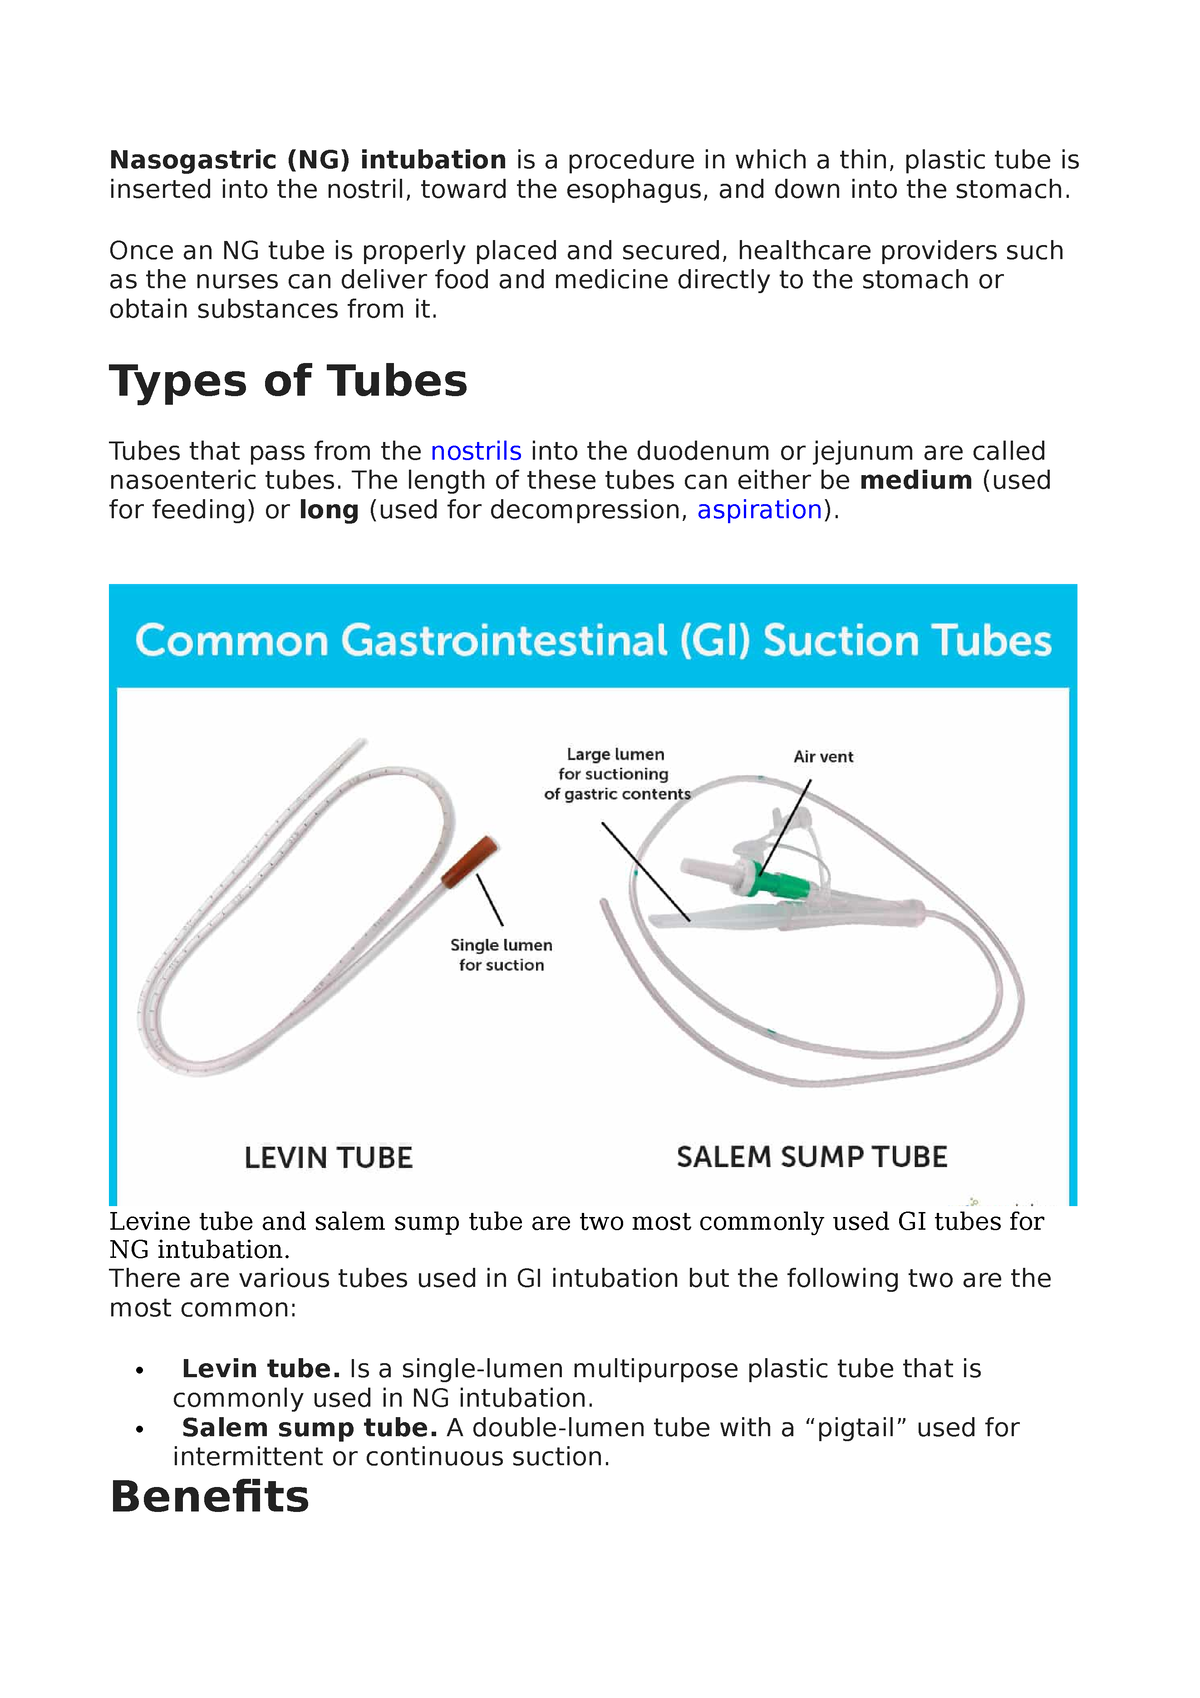
The biggest mistake I see is crimping the tube too far down. When you connect the tubing to the NG tube, people tend to pinch or clamp too close to the patient end. The drainage holes on a Salem sump or similar double-lumen tube are near the tip, not at the very end. If the crimp blocks those holes, you've effectively sealed the tube and suction becomes useless. I've traced back three separate "non-functional" suction setups in one week and found the same issue each time—a few inches of tubing crimped flat, right above the flared connector. Another thing: the double-lumen design of a Salem sump tube isn't just a design preference. The second lumen is an air vent, and it has an orange antireflux valved attachment at the end. This allows air to enter the stomach as fluid is withdrawn, preventing the tube from adhering to and abrading the gastric mucosa. If that vent lumen is blocked or kinked, you're essentially creating a continuous negative pressure environment, which significantly increases the risk of mucosal damage. Check that vent line is open and unobstructed. I once had a nurse tape the vent end shut "to keep it clean," and the patient developed a small gastric erosion within 12 hours. Gastric suction removes hydrochloric acid continuously. This can lead to hypochloremic metabolic alkalosis over time, especially in patients who are also on diuretics or have poor oral intake. It's counterintuitive, but patients on IV bicarbonate for stress ulcer prophylaxis who also have an NG tube on suction may be getting more base than they need, since they're actively losing acid through the tube. I've adjusted PPI dosing and monitored bicarbonate levels in these cases without checking, leading to unnecessary alkalosis that took days to correct.
Electrolyte monitoring matters. Potassium often drops alongside chloride loss. Check a basic metabolic panel at baseline and then every 24 to 48 hours depending on the duration of suction and the patient's clinical status. If potassium dips below 3.5 mEq/L, replace it. Don't wait for arrhythmias to show up on the monitor.
When This Doesn't Work and What to Do Instead
NG tube suction has real limitations. It won't decompress a completely obstructed bowel past the ligament of Treitz in most cases—you need a longer tube like a Miller-Abbott or Cantor for that, or surgical intervention. Small bowel obstructions distal to the duodenum often don't respond well to standard NG suction alone. If the stomach is packed with solid material like a phytobezoar or food residue from a gastric outlet obstruction, suction through an 18-22 French tube will clog repeatedly. In those cases, you're better off with larger-bore tubes or endoscopic intervention rather than spending hours flushing and refushing with minimal results. Continuous suction versus intermittent suction is a debate that comes up constantly. Continuous low suction is simpler to manage but causes more mucosal irritation. Intermittent suction—either via a dedicated intermittent suction device or by manual clamping and unclamping—reduces mucosal trauma but requires more nursing time and vigilance. I typically use intermittent protocols when the tube will stay in place more than 48 to 72 hours.
If the patient is actively vomiting or the NG tube keeps getting blocked by thick material despite regular flushing, consider switching to a larger bore tube or evaluating for a mechanical obstruction that requires surgical consultation. No amount of suction management will fix an anatomical blockage. The tube should not remain in place indefinitely. Most guidelines suggest removing it as soon as the underlying indication resolves—usually 24 to 72 hours post-operatively for elective cases. Prolonged placement increases the risk of sinusitis, nasal alar necrosis, and aspiration. If you need longer-term gastric access, a surgically placed gastrostomy tube is a more appropriate option.
Practical Reminders
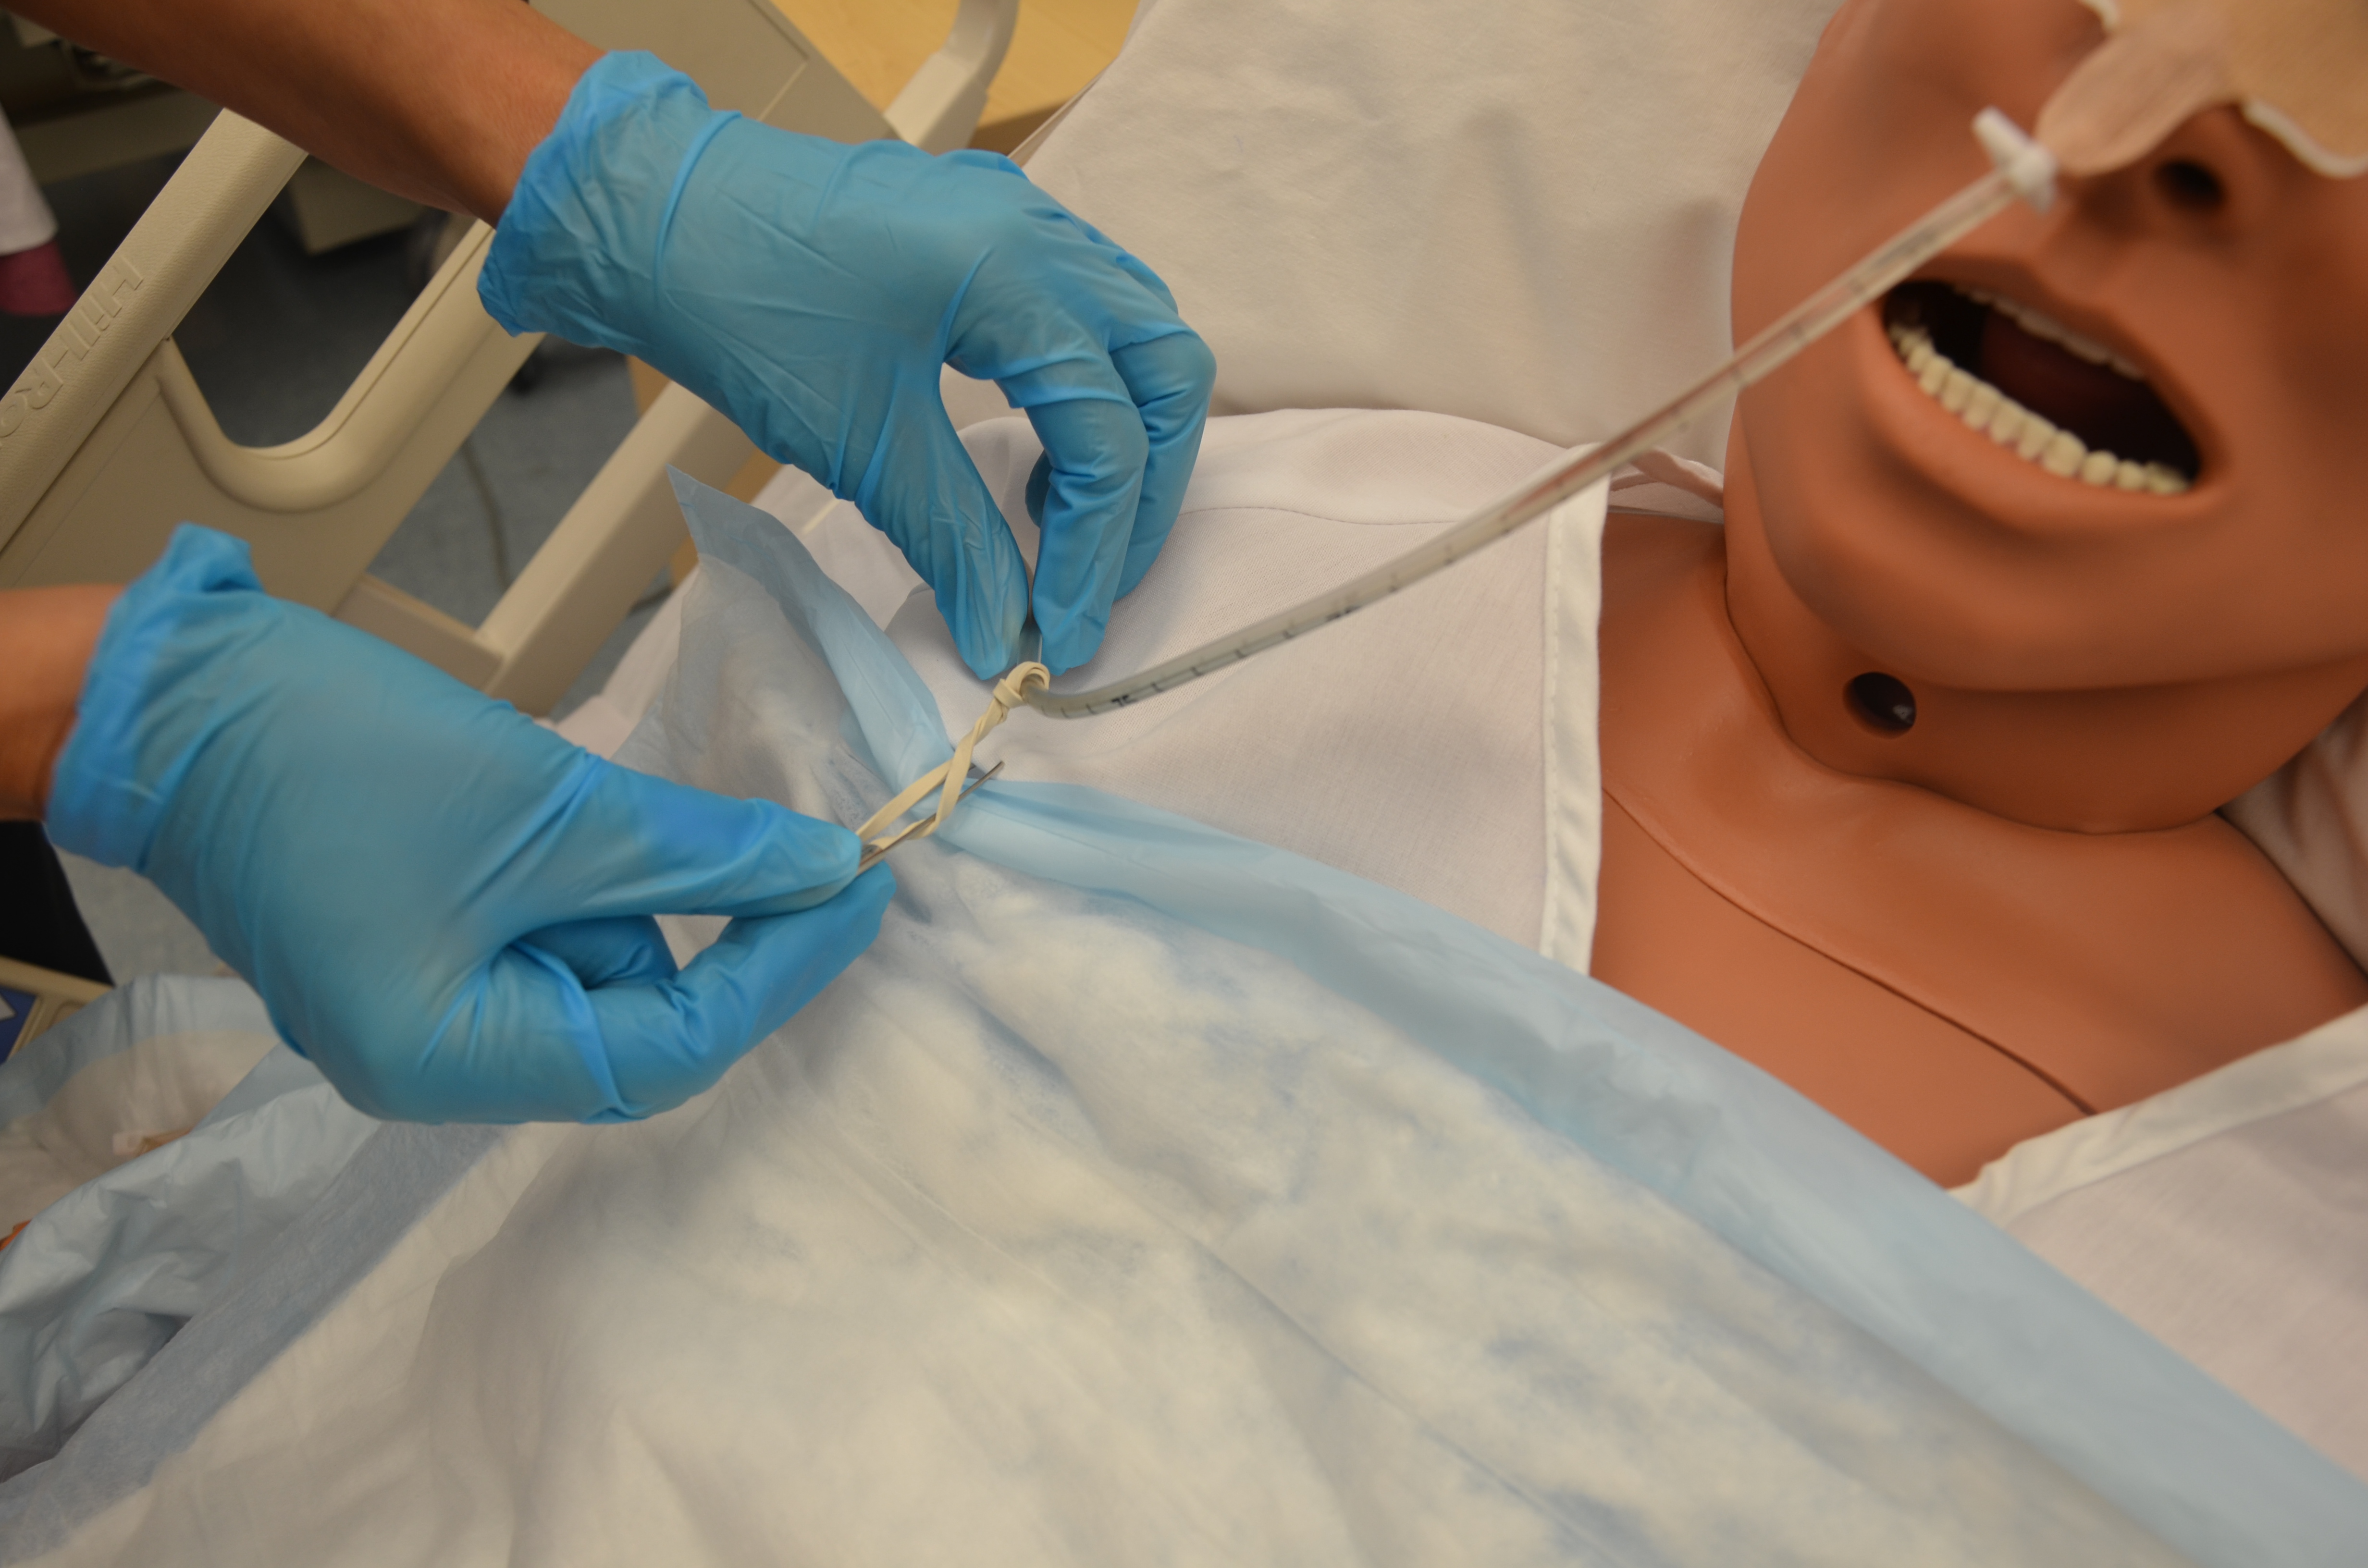
Secure the tube to the nose with proper adhesive or a commercial nasal securing device. I prefer transparent dressings that allow you to inspect the nasal septum daily without removing the tube. Check the nostril every shift for pressure injury. Redness that doesn't resolve after repositioning the tube to the other nostril needs attention immediately. Oral care is essential. Patients with NG tubes can't drink water for comfort. Provide mouth rinses and lip moisturizer regularly. Dry oral mucosa is a risk factor for infection and significantly impacts patient comfort. Don't irrigate with anything other than normal saline unless specifically ordered. Water can be absorbed through the gastric mucosa in significant quantities and cause hyponatremia, especially in vulnerable patients. Stick with isotonic solution.
If you're ever unsure about tube placement after repositioning or flushing, get an X-ray. Clinical signs like coughing or cyanosis during insertion are more reliable indicators of tracheal placement than gastric aspirate pH, but once the tube is in and being used, pH testing and radiographic confirmation are your standards. Clinical judgment about bubbling in the stomach upon auscultation while injecting air is unreliable and shouldn't be the sole method of verification. The bottom line: set the right pressure, maintain the tube patency with regular flushing, watch the electrolytes, and remove it as soon as clinically appropriate. Everything else is detail work that prevents complications.


