What Actually Happens in a Suicide Risk Assessment Training Program
I keep seeing people treat these programs like they're checking a compliance box. They're not. The difference between a trained clinician and someone who just went through the slides usually shows up within the first five minutes of an actual interview. The tool might be the C-SSRS or the SAFER-R framework, but the real work is in how you listen to what isn't being said. A typical program runs about 8 to 12 hours total, split between online modules and a live practicum session. The online part covers framework basics, risk and protective factor identification, documentation standards, and escalation pathways. The live portion is where most people struggle. You sit across from a standardized patient or a peer and you have to ask the direct questions out loud. Not in your head. Out loud. "Are you having thoughts of killing yourself?" That sentence is harder to say than it looks when you're being recorded and your trainer is watching.
How to Build Your Own Suicide Risk Assessment Training Framework
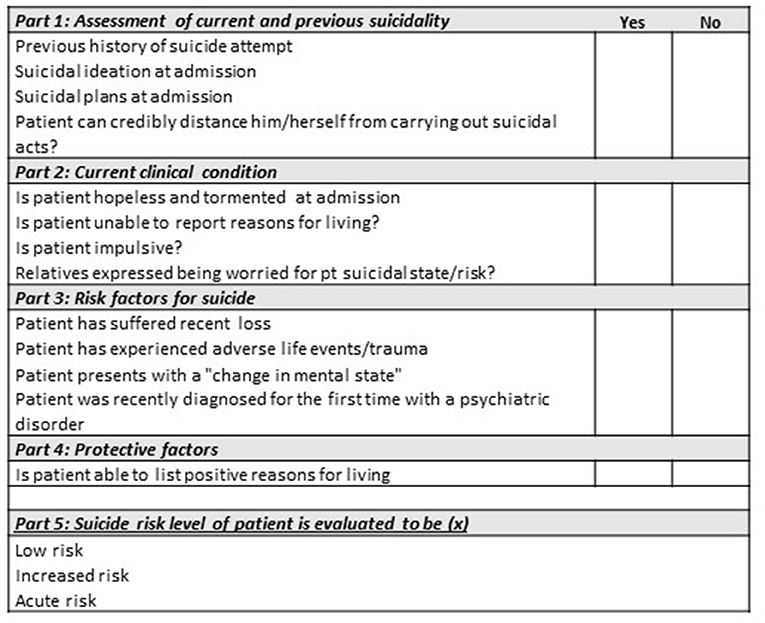
The structured part is straightforward. You pick an established tool, commit to using it consistently, and practice until asking the screening questions stops feeling like you're reading a script. The unstructured part is the hard one. You learn to notice micro-hesitations, deflections, sudden shifts in topic, and the way some people describe future plans in a present tense that doesn't actually include them. These signals rarely show up on the screening form. Here is something beginners consistently miss. A negative result on a suicide risk screening does not mean zero risk. It means the current snapshot does not indicate imminent danger. Risk is dynamic. Someone can score low in the morning and escalate by evening after a triggering event. I had a trainee once who confidently documented a patient as low risk because every box checked out clean, and then that same patient attempted two days later after a relationship breakup. The screening tool had been administered correctly. The training hadn't failed. What failed was the assumption that one data point predicts future behavior. I now require all my team to re-assess at minimum weekly for anyone flagged as moderate risk, and to document the last triggering event in the notes regardless of how minor it seems. The practical workflow goes something like this. Start with the screening instrument. Ask the direct question. Follow up with intent, plan, means, and timeline. Then pivot to protective factors. Reasons for living, social connections, religious or cultural beliefs, future goals, access to care. Then assess recent behavior changes. Sleep disruption, giving things away, sudden calm after a period of agitation. Those last items are where most incomplete assessments fall apart.
The Edge Case That Changed How I Train People
About three years into running sessions, I ran into a patient who was skilled at gaming the screening questions. Not in a manipulative way. In a way that revealed a flaw in how I was conducting the assessment. She knew what answer she was supposed to give. Every question about plan or intent, she responded with the lowest possible endorsement. But her body language told a completely different story. She was fidgeting constantly. Avoiding eye contact. And when I asked about protective factors, she gave short, rehearsed answers that didn't match the depth of her affect. The workaround was to change the questioning sequence. Instead of moving linearly through the tool, I started embedding contextual questions throughout. Rather than asking "Do you have a plan?" I would ask "Walk me through what a typical day looks like for you right now." The answer revealed she had already acquired pills and was waiting for the right moment. She never would have disclosed that through direct questioning because she was terrified of hospitalization. Switching to narrative-based exploration during the risk assessment training process caught what the standardized tool missed entirely. I now build that technique into every training module. The validated instrument stays. It is still the backbone of documentation and legal protection. But I teach people to use it as a starting point, not the endpoint. The real assessment happens in the thirty seconds after someone finishes answering a question and before they move to the next one. That silence contains information.
Get the Full Details

What Most Programs Get Wrong
There are two common failures I see repeatedly. The first is over-reliance on a single tool. No screening instrument accounts for every demographic or clinical scenario. The Columbia-SUicide Severity Rating Scale was originally developed and validated in specific populations. Applying it without understanding those boundaries reduces accuracy. The second is documentation drift. Clinicians start documenting thorough assessments and gradually slide into copy-pasted notes that don't reflect the actual conversation. This is both a quality problem and a liability problem. If you didn't document it, you didn't do it, and in court or a credentialing review, that distinction matters enormously. Another counter-intuitive finding from the research. The presence of a support system does not necessarily reduce acute risk. A person can have strong family ties and still attempt suicide. Protective factors matter for long-term recovery and ongoing monitoring, but they are not a shield against imminent danger. I see this conflated all the time in training sessions. People hear "protective factors" and assume they've found safety. They haven't. They've found a variable that influences outcomes over months, not minutes.
Pick a Tool, But Understand Its Limits
The C-SSRS is the most widely adopted instrument in the United States. It is free, publicly available through the FDA website, and comes in versions for adults, adolescents, and self-report. It takes approximately 5 to 10 minutes to administer properly. The SAFER-R model, developed at the Veterans Affairs system, takes longer. About 15 to 20 minutes, sometimes more depending on the complexity of the case. It is more of a decision-making framework than a questionnaire. Both are valid. Neither is sufficient on its own. If you are building a program from scratch, I recommend starting with the C-SSRS for screening and the SAFER-R for comprehensive assessment. That combination covers both speed and depth. Budget about 40 hours total for initial competency development, including supervised practice cases. Not all of that has to be synchronous. Some of it can be asynchronous video review where a trainee records themselves conducting an assessment and a supervisor provides feedback. That reduces costs significantly compared to in-person practicum only models.
Where the Model Breaks Down
No training program, no matter how well designed, can account for every situation. Cultural differences in how distress is expressed are a major gap. In some communities, direct questions about suicide are interpreted as invasive or shameful, and the person may refuse to engage fully. The tool was not built for that context. Somatic presentations are another blind spot. A patient who reports severe physical pain, chronic insomnia, and social withdrawal without mentioning suicidal ideation is still potentially at high risk, and most screening tools will miss that presentation unless the clinician knows to look beyond the explicit questions. The biggest limitation is probably the most obvious one. A trained clinician using a validated tool is still a human being working within a broken healthcare system. Caseloads, burnout, administrative burden, and insufficient follow-up infrastructure all degrade the quality of any assessment regardless of training quality. No amount of suicide risk assessment training can compensate for a system that schedules 15-minute follow-up appointments for people who may need daily check-ins. The training is necessary. It is not sufficient. For organizations looking to implement this, the practical steps are specific. Audit your current documentation practices first. You will likely find gaps between what is being assessed and what is being recorded. Then select a primary tool and commit to it for at least six months before switching. Consistency matters more than choosing the "best" instrument. Invest in the live practicum component. Online modules alone produce false confidence. Have clinicians observe each other conducting assessments. Peer feedback catches errors that supervisors miss because they've seen too many cases to notice subtle deviations. Finally, build in quarterly refreshers. Competency decays without reinforcement, and the skills that feel natural after your first training session will become mechanical within a year if you stop practicing them deliberately.