What Actually Happens During the First Few Days After Delivery
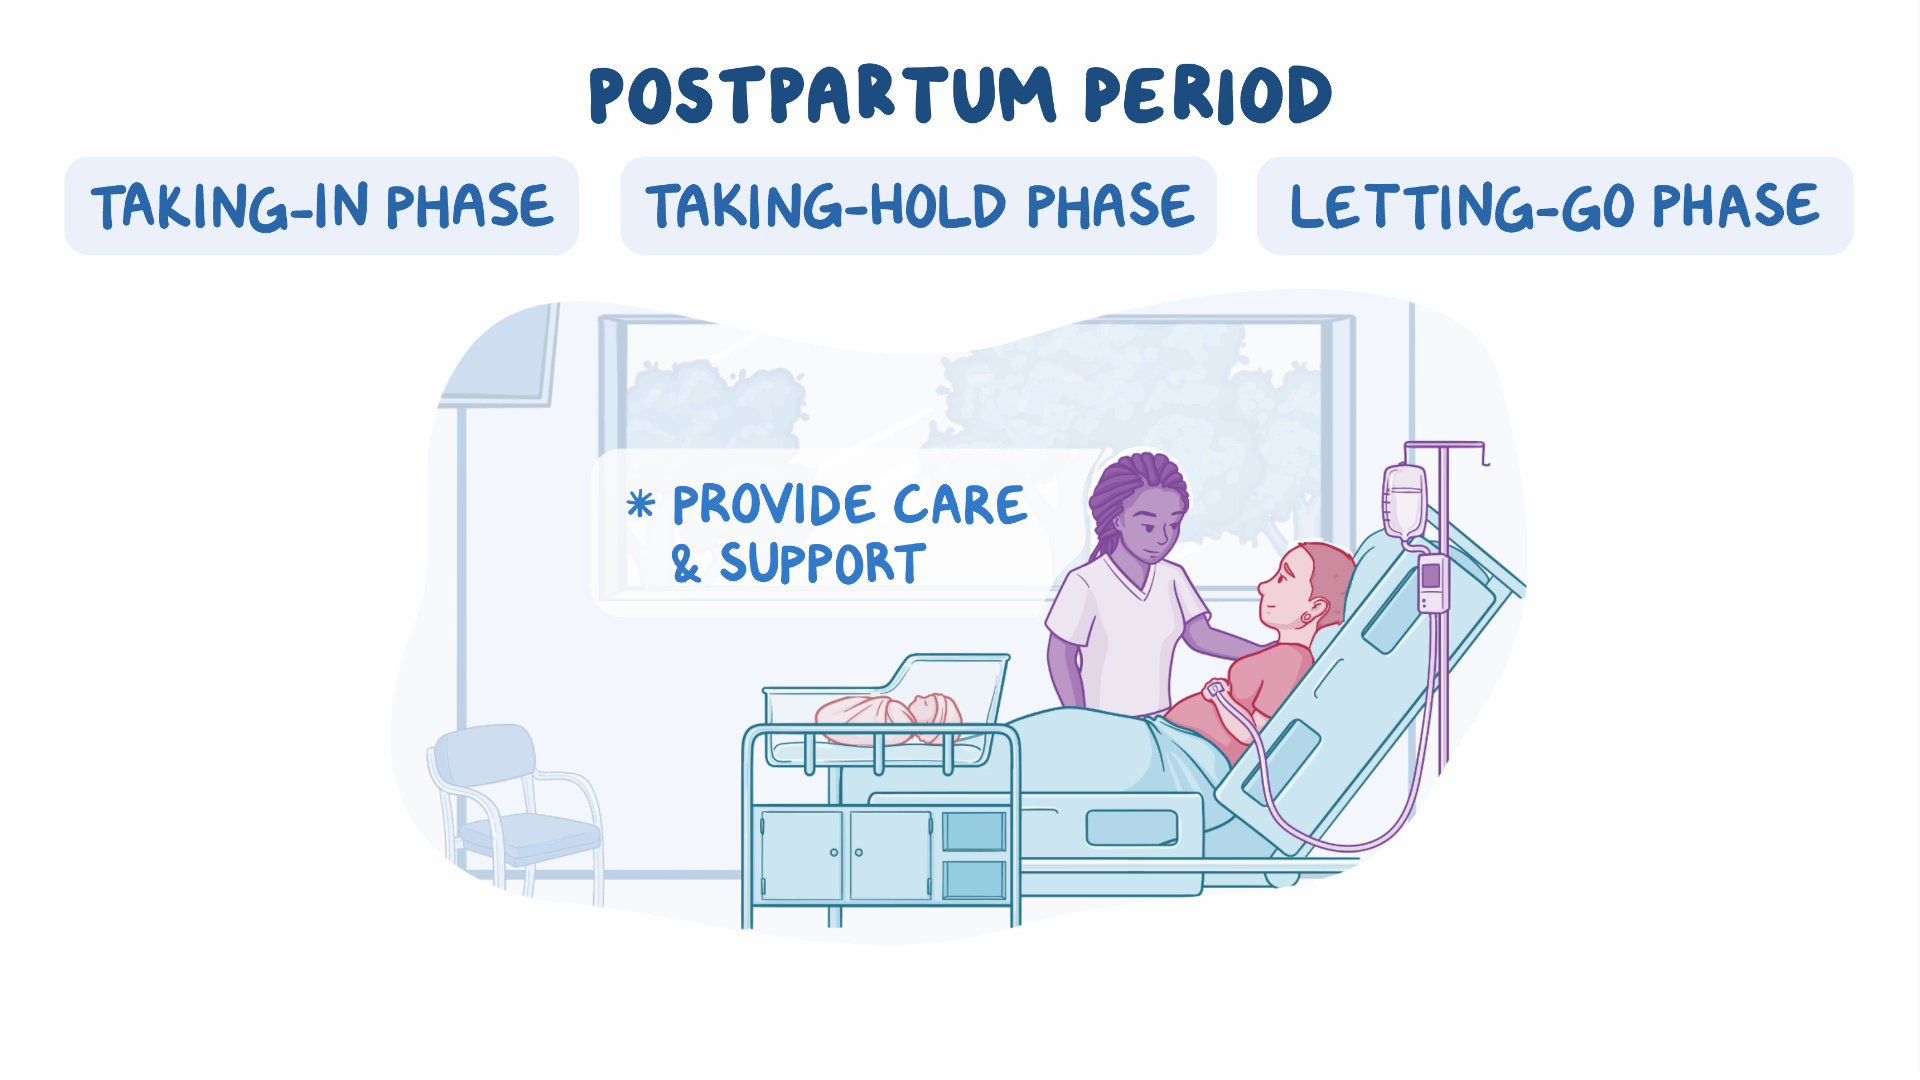
Most people don't prepare for how dependent and detached they feel right after birth. You're physically raw, your body is processing a massive hormonal shift, and everything around you feels slightly overwhelming. This isn't a character flaw. It's a documented phase of postpartum adjustment, and understanding it can save you from a lot of unnecessary guilt. The Taking-In Phase, also called the "taking hold" period in some older texts, is the first phase of postpartum psychological adjustment as described by nurse-theorist Reva Rubin back in the 1960s. It spans roughly the first two to four days after delivery, though the timeline varies considerably depending on whether the birth was vaginal or surgical, whether there were complications, and what your support system looks like. During this phase, the mother is primarily focused on her own survival and recovery. She tends to be passive, verbalizes her experience of the birth in detail (sometimes repeatedly), and relies heavily on others to meet her needs. Feeding decisions, baby care questions, and household logistics all feel like too much to manage at once. This is normal. It's also where a lot of friction starts if people expect the new mother to immediately "bounce back" into an active, decision-making role.
I've seen this go sideways when well-meaning family members or even hospital staff push for early feeding or quick bonding activities while the mother is still in a regressed, exhausted state. One patient I worked with was pushed to try latch-on breastfeeding within three hours of an epidural-assisted vaginal delivery. She was completely drained, not ready, and it created a cascade of anxiety that made the entire process miserable for weeks. The workaround was simple: delay intensive baby care instruction until she was more alert and rested, usually 24 to 36 hours in. Let her sleep. Let her talk about the birth. Let her be passive. It actually makes the transition to the next phase smoother.
How It Manifests in Practice
The physical signs are obvious — you're bleeding, you're sore, you're probably dehydrated. But the psychological component is what catches people off guard. You might find yourself replaying the birth over and over, not because you're anxious, but because your brain is processing what just happened. You may cry without knowing why. You might not care much about the baby in those first hours, and that doesn't make you a bad mother. It makes you a human being going through a major physiological event. Feeding dynamics during this phase are worth noting. Some mothers breastfeed successfully right away. Others have zero interest in it during the Taking-In period and that's fine. The American College of Obstetricians and Gynecologists notes that the first 48 hours are not the time to make rigid feeding decisions if the mother is exhausted or unclear-headed. Delaying a firm commitment until you're past this phase usually results in better outcomes across the board. A counter-intuitive thing I've noticed: the mothers who verbalize the most during this phase — who talk extensively about their birth experience, who recount every detail — tend to transition into the next phase more easily. The act of telling the story seems to be a form of cognitive processing. Suppressing it or being told to "rest quietly" can actually prolong the discomfort. It's not about performance. It's about integration.
Get the Full Details
Common Pitfalls and When This Approach Breaks Down
The main risk during the Taking-In Phase is misreading normal behavior as a problem. Withdrawal from the baby, lack of eye contact, apparent disinterest in newborn care — these are typical and usually resolve on their own within a few days. The problem arises when clinicians or family members pathologize normal rest and regression, pushing intervention before the mother is ready. I've watched mothers be labeled as "detached" or "at risk for bonding issues" when they were simply in a normal recovery phase and needed sleep, not a psychiatric evaluation. There are also edge cases where the phase doesn't follow the textbook trajectory. Postpartum preeclampsia can develop up to six weeks after delivery and can present with headaches, visual changes, and mood symptoms that overlap with or worsen postpartum adjustment. If someone in the Taking-In phase has a severe headache that won't quit, visual disturbances, or sudden blood pressure spikes, that's not emotional — that's medical and needs immediate attention. I had a case where a mother was dismissed as "just overwhelmed" when she actually had delayed postpartum preeclampsia. The workaround was insisting on blood pressure checks for anyone presenting with persistent headache plus postpartum status, regardless of how "normal" their phase appeared. Cesarean deliveries complicate this phase significantly. The physical pain is higher, mobility is limited, and the hormonal cascade is slightly different. The Taking-In phase still applies, but the duration often extends longer because the body needs more time for basic functioning. Expecting a C-section patient to participate in the same level of active newborn care on day one as a vaginal delivery patient is unrealistic and usually counterproductive.
The biggest limitation of the Rubin model is that it assumes a relatively straightforward birth and recovery. It doesn't account well for traumatic births, stillbirth, neonatal ICU admissions, or pre-existing mental health conditions. In those cases, the phase model becomes less useful and clinical screening for postpartum depression and PTSD is more appropriate. The model works best as a baseline expectation for uncomplicated births, not as a diagnostic tool for complicated ones.
What Actually Helps During This Phase
Practical support matters more than advice. The mothers who do best are the ones whose partners or family members handle meals, household tasks, and gatekeeping — keeping well-meaning but exhausting visitors away. Medical staff who allow extended skin-to-skin contact without pressure, who let the mother set the pace for feeding and bonding, and who don't treat passivity as laziness tend to see smoother transitions into active parenting roles. Hydration and nutrition are frequently overlooked. The postpartum period increases fluid needs, and dehydration amplifies fatigue and mood instability. I always recommend keeping water within arm's reach and having simple protein-rich snacks available. This is not optimization advice — it's basic physiology. Dehydrated people in this phase feel worse, cry more, and take longer to transition out of the regressed state. Sleep is the single most important factor. Real sleep, not napping while the baby cries. If there's anyone who can take the baby for a three-hour stretch so the mother sleeps uninterrupted, that's worth more than any bonding activity or feeding technique discussion. Sleep deprivation during this window directly correlates with longer phases, more difficulty transitioning, and higher rates of postpartum mood disorders later on.