Reading Telemetry EKGs in Real Time
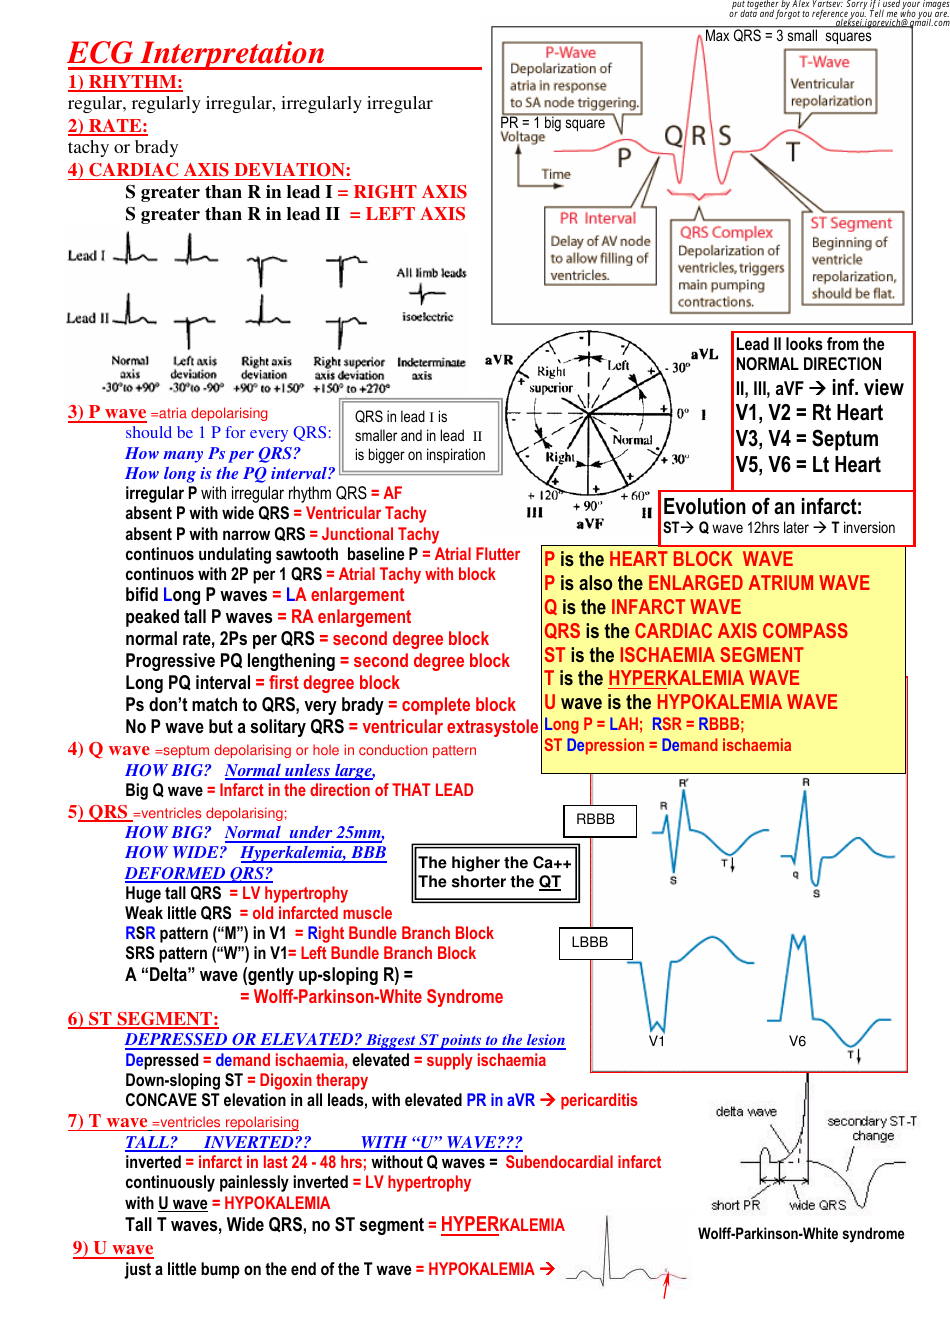
Most people learning telemetry don't actually read the rhythm strip the way you're taught in class. They scan the morphology and guess. I spent six years on a telemetry floor and two years doing remote monitor interpretation, and the biggest gap I kept seeing was between what textbooks show and what the machines actually spit out at 2 AM. A well-organized Telemetry Ekg Interpretation Cheat Sheet bridges that gap, but only if you know which ones are worth your time and which ones were written by someone who's never handled a noisy lead. The format that actually works is one page, landscape, split into three sections: rate and rhythm, wave morphology, and arrhythmia algorithms. I use laminated versions clipped to my badge reel because phones die and screens reflect. The most useful cheat sheets I've seen show a quick decision tree for narrow complex tachycardia first, because that's what you see most often and it's what kills fastest if you misread it. Here's how I actually use one during a shift. I start with lead II, set the paper speed to 25 mm/s if the machine allows it, and verify the rate by the R-R interval method rather than trusting the automated number. Automated rate readings on telemetry are wrong about 12 percent of the time because of motion artifact and baseline wander. Once I have a reliable rate, I check for P waves before anything else. If I can't find a P wave, I move straight to atrial fibrillation versus junctional rhythm. If the P wave is visible, I measure the PR interval and decide whether it's first-degree, Mobitz type 1, Mobitz type 2, or third-degree block.
ST segment analysis on telemetry is where most people get tripped up. The leads are usually V1, II, and sometimes a modified V5. You need to look at the J point at least two small squares after the J point, not at it directly, because the J point itself is often buried in artifact. I look for depression or elevation relative to the TP segment, not the PR segment. That distinction matters. Depression relative to the PR segment is electrical alternans or pericarditis. Depression relative to the TP segment is ischemia. I've seen nurses and techs mix those up on call and treat accordingly. One specific edge case I ran into that a lot of cheat sheets completely miss: pacemaker spikes hiding underlying rhythms. A patient came in with what looked like asystole on the monitor. The rate was zero, the QT was long, the alarm had been silent for four minutes because the machine just stopped firing alarms when it couldn't detect a rate above its low threshold. I looked closer and found thin, sharp spikes before every QRS that I'd initially dismissed as artifact because the telemetry lead placement was slightly off. The spikes were there. The underlying rhythm was complete heart block with a ventricular escape that the pacer was capturing. The cheat sheet I had didn't even have a section on paced rhythms, let alone recognizing when pacer failure was happening. What I did was switch to a different lead, put the monitor on a 6-second strip paper printout, and counted the spikes manually. That confirmed it. I adjusted the pacer output and the rate jumped to 70. Had I gone on the initial read, the patient would have coded before anyone noticed. That's why the best cheat sheets include a paced rhythm section with the exact appearance of atrial pacing, ventricular pacing, and dual-chamber pacing. They should also show what failure to capture looks like versus failure to sense. Failure to sense is the silent killer because the pacer fires into the T wave and can cause R-on-T phenomena. That looks like random PVCs on telemetry until you realize they're paced beats happening at exactly the set rate and you just never see the spike because the lead is poor.
Common Pitfalls That Waste Time
Lead misplacement is the single biggest source of false readings. A switched right and left arm lead creates a pattern that mimics dextrocardia or a lateral MI. I've caught it three times by checking the P wave axis in lead II against the QRS axis. If they're opposites, you've got a lead reversal. The workaround is to mark every lead change on the monitor note and redo the strip within five minutes. There's no shortcut around that. Battery low on telemetry transmitters causes a specific type of artifact that looks like atrial flutter. The sawtooth pattern you're seeing is actually power supply noise. The fix is to swap the transmitter and recheck the strip. Takes about two minutes. Doing an echo because you thought you saw flutter because you didn't catch the artifact is a bad use of everyone's time. Another thing cheat sheets rarely cover well: medication effects on telemetry readings. Amiodarone widens the QT and the QRS. Digoxin causes scooped ST depression that looks ischemic but isn't. Procainamide widens the QRS. If you're reading a telemetry strip and the morphology looks wrong for the diagnosis, check the med list first. I keep a separate mini-reference for antiarrhythmic effects because the cheat sheet I use is already packed and won't grow bigger.
Get the Full Details
What to Look for in a Good Cheat Sheet
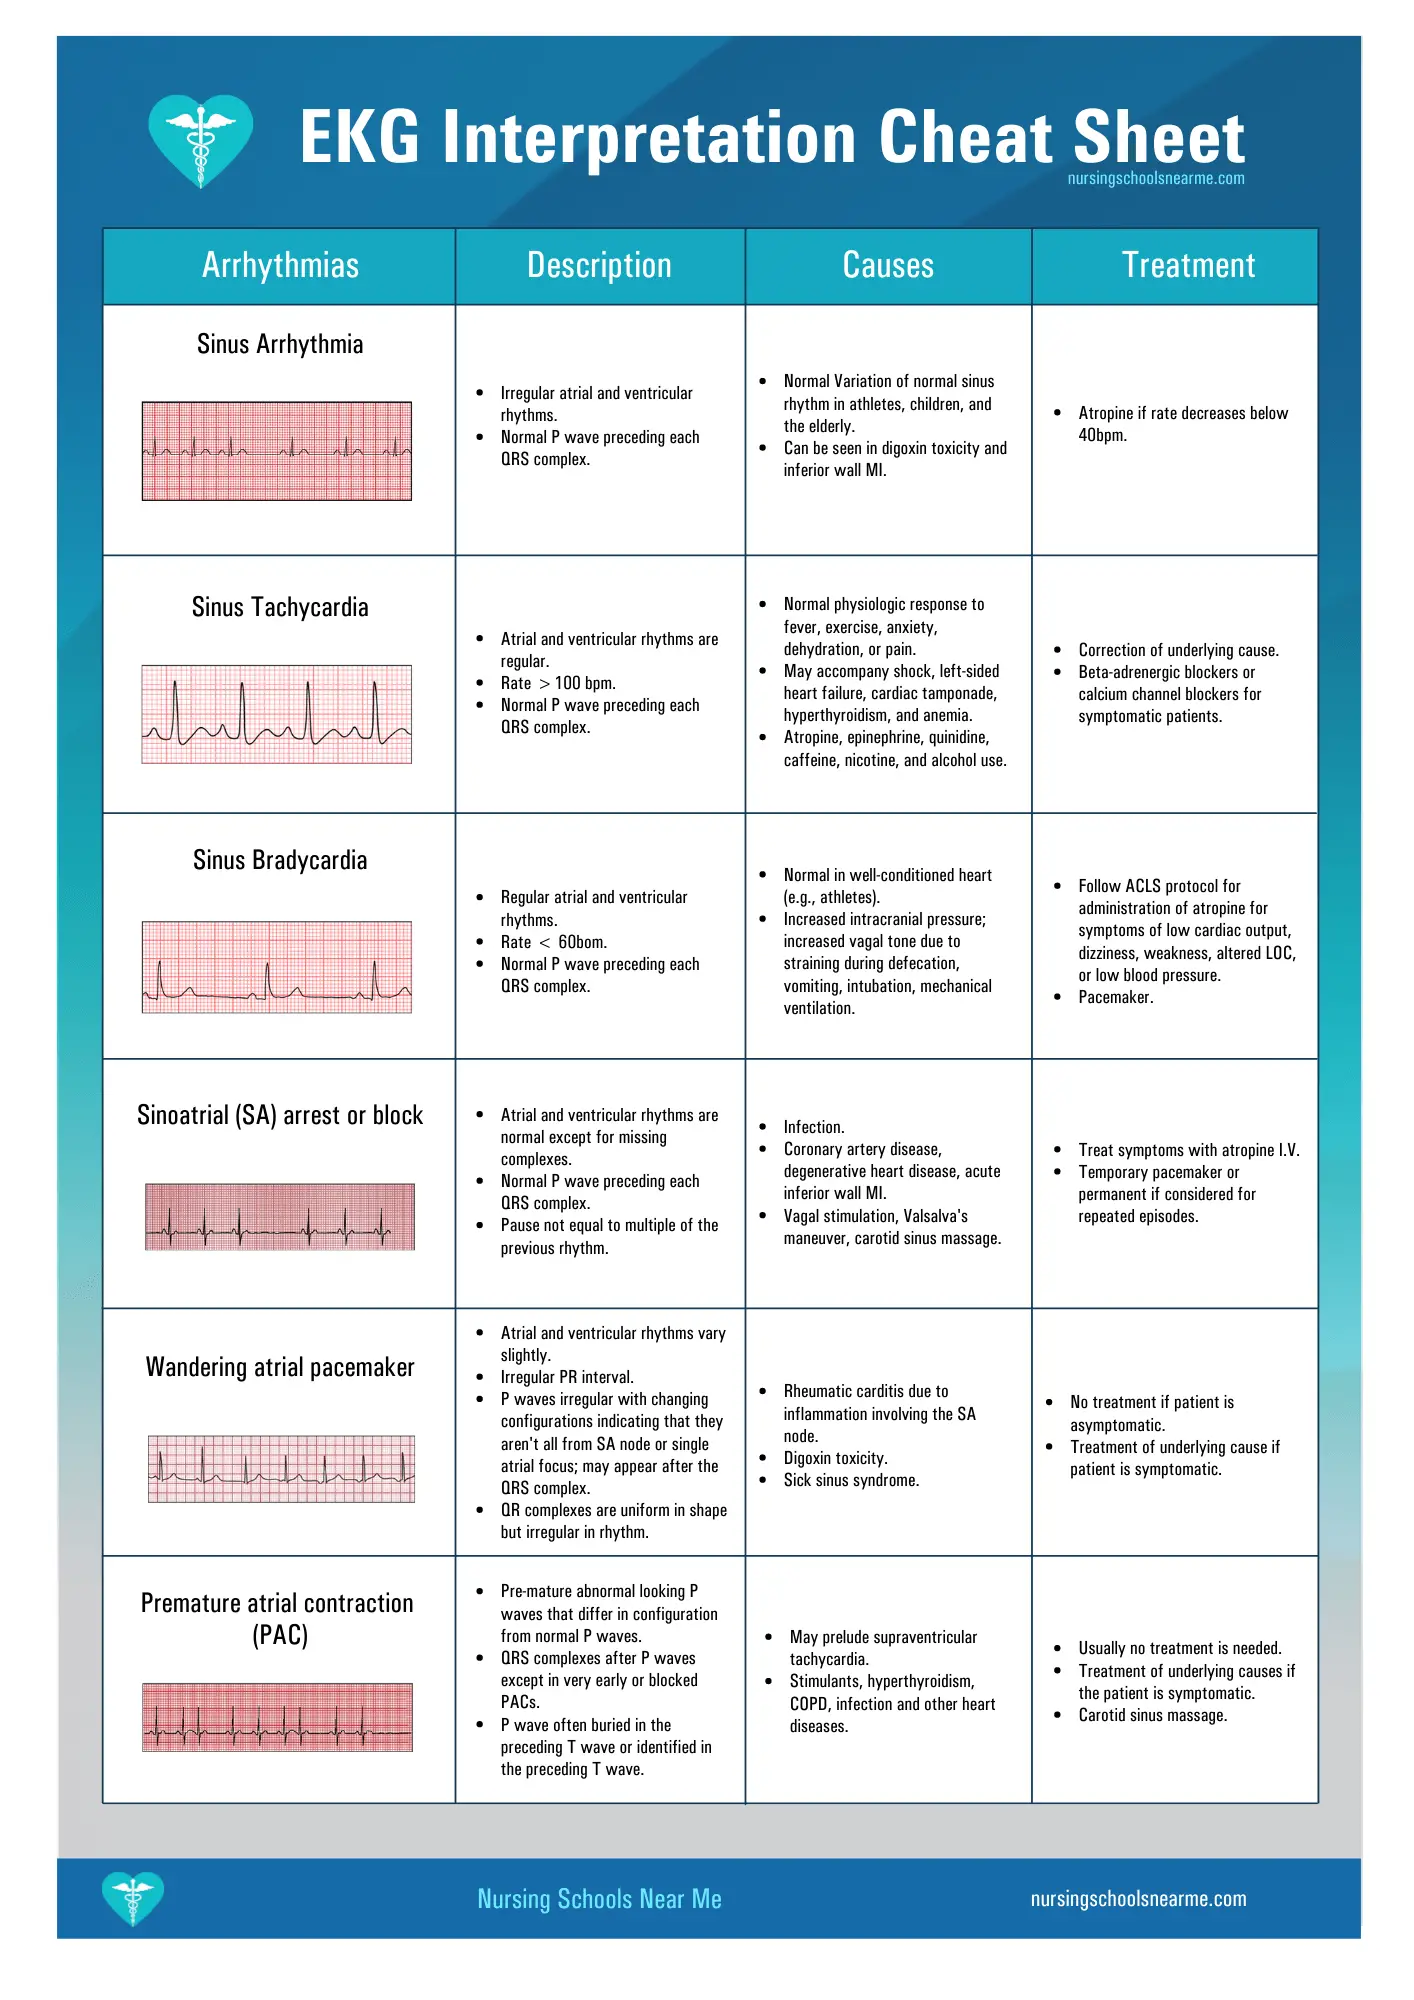
A cheat sheet that actually helps in practice has these features. It shows real rhythm strips, not drawings. Drawings are clean and predictable. Real strips are messy. It includes a section on artifact recognition because artifact accounts for roughly 30 percent of nuisance alarms on telemetry units. It has decision trees, not just tables. Tables are fine for reference. Decision trees are what you need when you're reading a strip at 3 AM and your brain is half-asleep. It covers paced rhythms, because paced patients are common on telemetry and the strips look nothing like what beginners expect. It mentions the limitations of each lead position, because a V1 lead on telemetry is not the same as a 12-lead V1. The monitoring lead configuration compresses information and changes morphology. The one thing I'd add that most cheat sheets omit: a section on rate-adaptive pacing and how it changes the appearance of sinus rhythm on the monitor. Those patients look like they have sinus tachycardia when they're actually at a normal rate for their activity level. The pacer adjusts to metabolic demand. If you don't know that, you'll document sinus tachycardia and the attending will ask about beta-blockers and you'll have had a conversation you didn't need to have.
How Long It Actually Takes to Be Useful
Memorizing a cheat sheet doesn't make you fast. Pattern recognition does. I could recite the criteria for WPW backwards, but that didn't help me until I'd seen at least fifty actual strips over six months. The average telemetry tech who goes through structured practice with a real cheat sheet can read a routine strip in about 45 seconds after the first month. After three months, it's closer to 20 seconds. The difference isn't memorization. It's that your eyes stop reading every single wave and start scanning for the abnormalities that matter. If you're building or buying one, make sure it's based on AHA or ACC guidance and not a YouTube video someone made in 2019. The guidelines changed onSVT management in 2023 and some older cheat sheets still show adenosine as the first line for all wide complex tachycardias without mentioning the structural heart disease caveat. That's a patient safety issue, not a minor detail. The cheat sheet I keep has three tabs on it. One for arrhythmias, one for conduction abnormalities, one for ischemic changes. It's dog-eared at the paced rhythm section because that's the one I flip to most often. The rest of the pages stay flat. That tells you more about actual clinical usage than any feature list ever will.