Why Standard Hospital Templates Don't Work for Nursing
I've been doing nursing documentation for about eleven years now, and the biggest problem I see isn't that people don't fill out their paperwork. It's that the paperwork they're forced to use doesn't match what actually happens on a shift. You start at 0700, handoff takes forty-five minutes, you chart during lunch because the unit is too busy to stop, and by the time you hit your 1500 documentation window, you're running on caffeine and instinct. A template for nursing monthly that works in theory falls apart the second you try to use it on a med-surg floor with twelve patients and two code blues. Most nursing documentation systems are built by committees. They're safe, compliant, and completely disconnected from how nurses actually think during a shift. I used to work at a hospital that required separate documentation for wound care, pain management, intake and output, fall risk, skin integrity, and medication administration, each in its own module, and the worst part was none of them talked to each other. You could mark a patient as high fall risk in one system and still forget to put up the bed alarm because the alert didn't carry over. That gap is where most errors happen.
What Your Template For Nursing Monthly Should Actually Look Like
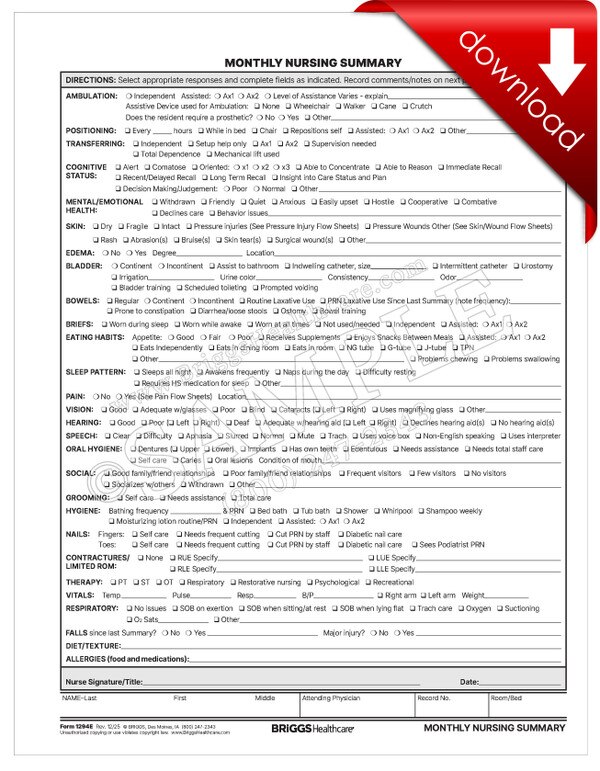
The monthly nursing template I use has five sections. There's the shift snapshot, which is a single line per patient covering acuity, major changes, and discharge status. Then there's the medication reconciliation log, which tracks anything that changed dose, route, or timing since the last shift. Third is the incident and near-miss tracker. This isn't optional, even though most people skip it. Fourth is the handoff summary, and fifth is the unit-level metrics, counts of falls, medication errors, pressure injuries, and any joint commission observations that came up. I built this after spending three months watching my colleagues try to use the official electronic health record. The EHR was fine for billing compliance but terrible for clinical thinking. Nurses would spend twenty minutes in the med admin section just to give a one-line update. That's not sustainable. The template I landed on takes about eight minutes to fill out per shift per patient at full census. On a typical 4 PM entry, that's roughly an hour and twelve minutes for a full floor, which is reasonable when you compare it to the average forty-five minutes per nurse that official charting demands. Not a huge reduction, but the difference is that this version stays in the nurse's head while it's being written. The EHR version forces you to navigate twelve screens to say the same thing. One thing nobody tells you about monthly nursing templates is that they need to be living documents. I learned this the hard way when our quality department sent down a new template that added fifteen fields I'd never seen before. None of those fields corresponded to anything we tracked clinically on the floor. We spent two weeks filling them out, then six more weeks realizing the data wasn't actually being used for anything. The workaround was simple. I took the template, kept only the fields that matched actual clinical workflow, and turned the rest into footnotes. Quality didn't like it at first, but they also didn't have a better option. After three months of actual use, the data was cleaner and our incident reporting went up because nurses were finally entering things they noticed instead of ignoring the form entirely.
How to Set Up a Template That Actually Gets Used
The first thing you need to understand is that a template is only as good as its integration into workflow. If it requires extra clicks, extra screens, or extra thinking, people will find a way around it. I've seen nurses use shorthand on sticky notes and transfer it later. I've seen people copy-paste the same assessment from Monday into every day of the week. These aren't compliance failures. They're system failures. The template asks for something that doesn't match how the work actually happens. Start by listing the documentation requirements that are non-negotiable. These are things you must capture for legal, regulatory, or clinical safety reasons. Fall risk scores. Pain reassessments within the required window. Skin assessments for high-risk patients. Medication reconciliations on transfer. These are your anchors. Everything else in the template should support these, not compete with them for attention. Then build backwards from those anchors. I structure my monthly template with a header that shows date, shift, unit census, and nurse identifier. The body has a grid layout with patient name, medical record number, acuity level, key intervention, response, and next action. Acuity levels in my system run from one to four. Level one is stable. Level two has one active change. Level three has two active changes or one unstable condition. Level four is critical or rapidly deteriorating. This isn't a perfect system, but it's fast and it gives the next nurse something to react to without reading a novel. The response field is short, one sentence maximum. Next action tells the incoming shift what needs to happen before they leave. That last part is the most important. Most handoffs tell the next person what happened. This template forces them to specify what comes next.
Get the Full Details

Here's a detail that trips people up: the monthly component. A monthly nursing template shouldn't just cover a single shift. It needs a rolling summary that aggregates the daily entries. I use a separate sheet that tallies total interventions per patient, tracks trends in acuity levels, flags any recurring issues like repeated medication errors or repeated fall risks, and notes any patterns that might need a care plan revision. This takes about ten minutes a month per patient if your daily entries are clean. I've seen units skip this step entirely, which means they're missing trends that would be obvious if someone looked at the data across a full month instead of evaluating each day in isolation.
Common Problems and What Actually Works Around Them
The biggest issue I deal with is documentation drift. This happens when a template starts working well and then slowly becomes worse because someone adds a field here or changes a label there. It rarely feels like a big change. It's always small. A new dropdown menu. An extra checkbox. A field that used to be optional becomes mandatory. Over six months, the template becomes twice as long and twice as frustrating. The workaround is to schedule a quarterly review of whatever template you're using. Sit down with three nurses who actually fill it out, not administrators or charge nurses, and ask them to cross off anything they haven't used in the past thirty days. Then ask them to add back anything they actually needed but couldn't find. This process usually cuts the template length by forty percent within one cycle. Another problem is overlap between the monthly template and the EHR. When you're required to use both, you end up documenting the same thing twice. I solved this by making my monthly template a mirror of the EHR fields rather than a replacement. I read the EHR first, pulled the relevant entries, and formatted them into the monthly template layout. This took longer initially but reduced my total documentation time over the month because I stopped switching back and forth between two systems. The EHR gets its mandatory fields. The monthly template gets the clinical summary. They're separate documents that serve separate purposes, and keeping them separate avoids the double-entry trap. There's also the problem of shift variance. Night shift and day shift document differently because they see different things. A template designed for day shift will miss critical night shift events like overnight desaturation episodes, PRN medication use for anxiety or insomnia, or family complaints that only surface when the unit is quieter. My solution was to add a shift-specific override section at the bottom of the template. It's two lines. One for night-specific events and one for day-specific events. The next nurse reads the override first before anything else. This has caught missed findings more times than I can count.
Practical Example of a Completed Monthly Entry
Here's a real example from my last rotation. Patient was a sixty-eight-year-old male admitted for pneumonia. Acuity started at level three on day one due to oxygen requirement and infection parameters. The monthly template tracked him across fourteen days. On day five, his acuity dropped to level two after antibiotics kicked in. Day seven he spiked a fever again, acuity went back to three. Day ten he was transferred to telemetry for a new arrhythmia, acuity level four. The daily entry for each day was one to three lines. The monthly summary captured the trend: initial improvement, secondary deterioration, acute event, transfer. Without the monthly view, each individual day entry would have looked isolated and less informative. The trend is what matters for the care team and for discharge planning. The handoff summary in this case flagged the arrhythmia as pending cardiology follow-up, noted that the pneumonia treatment was still active but the patient was transitioning, and specified that the next nurse should confirm telemetry telemetry lead placement and monitor for recurrent episodes. This replaced what would have been a ten-minute verbal handoff with a three-minute written reference. The verbal handoff still happened, but now it was focused on clarification instead of recreation. I should mention one limitation here. This template works well for stable unit transfers and standard shifts. It does not work well for rapid resuscitations, mass casualty events, or when a nurse is covering a floor they don't normally work on. In those situations, the structured format slows you down because you're trying to fit chaotic events into a rigid grid. I use a completely different approach for those, usually free-form notes with timestamps and a priority flag. The monthly template is for the steady-state documentation that makes up most of the work, not the emergencies that make up the stories. Knowing when to use which system is part of what makes the template useful.
Where This Template Falls Short
No template is complete. The main weakness I've found is that it depends on consistent daily entry. If a nurse skips three days and fills it out on the fourth, the trend data gets noisy. You lose the day-to-day granularity that makes the monthly view valuable. Another weakness is that acuity levels are subjective. Two nurses can look at the same patient and assign different levels. I deal with this by having the charge nurse review the level assignments weekly and correct any outliers. It adds ten minutes to the weekly meeting but keeps the system honest. The template also doesn't replace legal or billing documentation. It's a clinical tool. If your facility requires specific billing codes or compliance reports, you'll still need to maintain those separately. The monthly nursing template is for clinical communication and trend tracking. It's not a substitute for the formal record. Mixing the two purposes creates confusion and weakens both. For facilities that want to go further, there are electronic versions of this concept. Some hospitals have built dashboard-style monthly views that pull from the EHR automatically. These are ideal if your system supports it, but they're not universal. The manual template I described works in any environment, including places that still use paper-based or semi-electronic documentation. The cost is time. The benefit is consistency and clarity.
If you're building your own version, start small. Don't try to create a comprehensive system on day one. Build the core five sections, test it for two weeks with a small group, iterate based on what actually gets used, and expand from there. Templates that launch fully formed usually fail because nobody bothered to test them with the people who would actually use them. The best template I've ever used is a simplified version of what I described here, and it took me four months and three failed iterations to get to it. The final version is eight screens in the EHR, two pages if printed, and takes about twelve minutes per shift per patient at full capacity. It's not elegant. It's functional. That's what matters.