What Actually Makes Male Anatomy Worth Studying Carefully
Most people learn enough about male anatomy to pass a biology quiz and then never think about it again. That approach breaks down the moment you need to do anything precise with it, whether that means designing a prosthetic, training someone through a injury, reading imaging, or building a realistic figure from reference material. The difference between surface-level knowledge and actually understanding how it works shows up fast in practice. I spent years doing anatomical reference work for character design, and I quickly learned that textbook diagrams lie to you about proportions. Cadaver drawings show idealized symmetry and average measurements. Real bodies don't work that way. The left and right sides of a man's torso are rarely equal. The clavicle on one side sits higher. One shoulder is usually broader from dominant-side use. When I started ignoring those textbook proportions and actually measured living subjects, my work went from stiff to convincing overnight.
Learning The Anatomy Of A Mans Body Through Practice
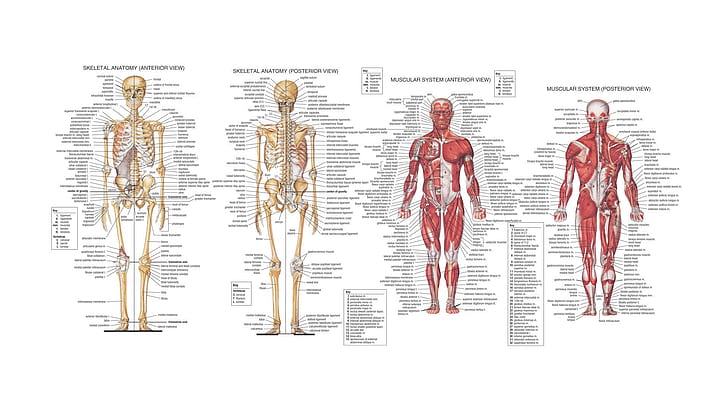
Here is the method I use when approaching anything new in male anatomy. I don't start with textbooks. I start with physical palpation. You find your own body, run your hands over the landmarks, and map them onto a diagram. The sternoclavicular joint sits right where your collarbone meets your breastbone. The anterior superior iliac spine is the bony bump at the front of your hip. The acromion is the point at the top of your shoulder. Once you can name these points on yourself without looking, everything else layers on faster. After that, I cross-reference with a good atlas. Gray's Anatomy or Netter's Atlas of Human Anatomy both work. I read the relevant section after I've already touched the structures, not before. The learning sticks because you have a tactile anchor for every label on the page. A visual-only approach leaves too many connections vague.
Structural Layers You Should Know Before Going Further
Male anatomy follows the same basic architecture as everyone else's. Skin, subcutaneous fat, fascia, muscle, connective tissue, bone. But the distribution of those layers changes dramatically depending on region and individual. Some guys carry most of their fat in the abdominal area. Others store it in the chest, the lower back, the upper arms. This isn't just cosmetic. It affects how you read surface form, how injuries present, how garments or armor sit on the body. The pectoralis major has three heads. The clavicular head, the sternocostal head, and the abdominal head. They insert together on the lateral lip of the bicipital groove of the humerus. Most beginner artists and even some trainers collapse this into a single flat chest muscle. That flattening removes the visible separation between the upper chest and the lower chest, which is one of the most noticeable tells of amateur work. In reality, the line between those two heads creates a horizontal crease that shifts position with arm angle and body fat. Another thing people consistently get wrong is the oblique region. The external oblique fibers run downward and medially, like your hands in your pockets. The internal oblique runs in the opposite direction. They interdigitate with the transversus abdominis. That means the midsection doesn't move as a single sheet. It moves in coordinated layers. When a guy does a side bend, only certain fibers engage visibly. When he twists, a different set shows. Understanding that layering matters whether you are drawing him, training him, or diagnosing a core issue.
Get the Full Details

Counter-Intuitive Things That Textbooks Don't Emphasize Enough
The first thing most people miss is that male and female anatomy differ more in proportion and fat distribution than in fundamental structure. The skeleton is the same. The muscle insertions follow the same rules. What changes is scale and emphasis. The male pelvis is narrower. The male ribcage is wider relative to the waist. The male shoulder is broader. Those differences create the visual silhouette most people associate with masculinity, but the underlying mechanics are nearly identical. The second thing is fascial continuity. Fascia isn't a passive wrapper. It is a tension network. A restriction in the thoracolumbar fascia can change how the latissimus dorsi behaves all the way up to the humerus. I once had a subject whose shoulder mobility was the worst I'd seen, and we spent weeks working on rotator cuff exercises before realizing the real bottleneck was a fascial adhesion in the mid-back from an old sports injury. Release the fascia, and suddenly the shoulder moved normally. Isolated muscle work wouldn't have touched it.
A Specific Problem I Ran Into and How I Fixed It
I was working on a character rig for an animation project and kept hitting the same wall. The torso deformation looked wrong when the model turned past about forty-five degrees. The ribcage twisted as a solid block instead of separating into upper and lower segments. I had modeled everything correctly at rest. The problem only appeared in motion. Turns out I hadn't accounted for the costal margin's independent movement from the lower ribs during rotation and lateral flexion. The twelve pairs of ribs don't all move the same way. The floating ribs have more mobility than the true ribs. The costal cartilages allow the lower ribcage to expand and shift independently of the sternum. My workaround was to split the torso mesh into distinct bone-separated regions: upper thoracic, lower thoracic, lumbar, and pelvic. Each region got its own deformation rig with carefully weighted influence zones. I then used motion capture data from real subjects turning and twisting to validate the ranges. The result wasn't perfect, but it was close enough that no one on the team could point at the torso and say it looked broken. That was a massive improvement over where we'd been stuck for months.
Where This Knowledge Breaks Down
Self-studying anatomy from books and observation has hard limits. You can learn a lot about surface landmarks and gross structure, but you will never fully understand the brachial plexus, the autonomic nervous pathways, or the microvasculature without hands-on dissection or clinical training. Books can show you what things look like. They can't teach you the tactile variation you only get by handling real tissue. If your goal is clinical work, this path won't replace proper education. It can supplement it, but the gap is real. There is also a risk of over-applying generalized anatomy to individuals. Every body is different. A textbook description of the male pelvis assumes an average sample. Real pelvises vary in shape, size, and orientation. Athletes who do heavy rotational work often develop asymmetric hip structures from years of specialized loading. Diabetics may present with different fascial stiffness patterns. Aging changes everything from skin thickness to spinal curvature. The framework helps you understand the baseline. It doesn't replace looking at the actual person in front of you. If you need clinical-grade anatomical knowledge, the practical alternative is investing time in a proper program like a medical assisting course, an EMT certification, or a physical therapy assistant degree. Those programs give you supervised dissection labs, imaging practice, and case-based learning that self-study simply cannot replicate. For creative or fitness applications, the layered approach I described above covers the vast majority of real-world needs. Just know where the method ends and the real expertise begins.