
Understanding What Actually Drives Compulsive Behavior
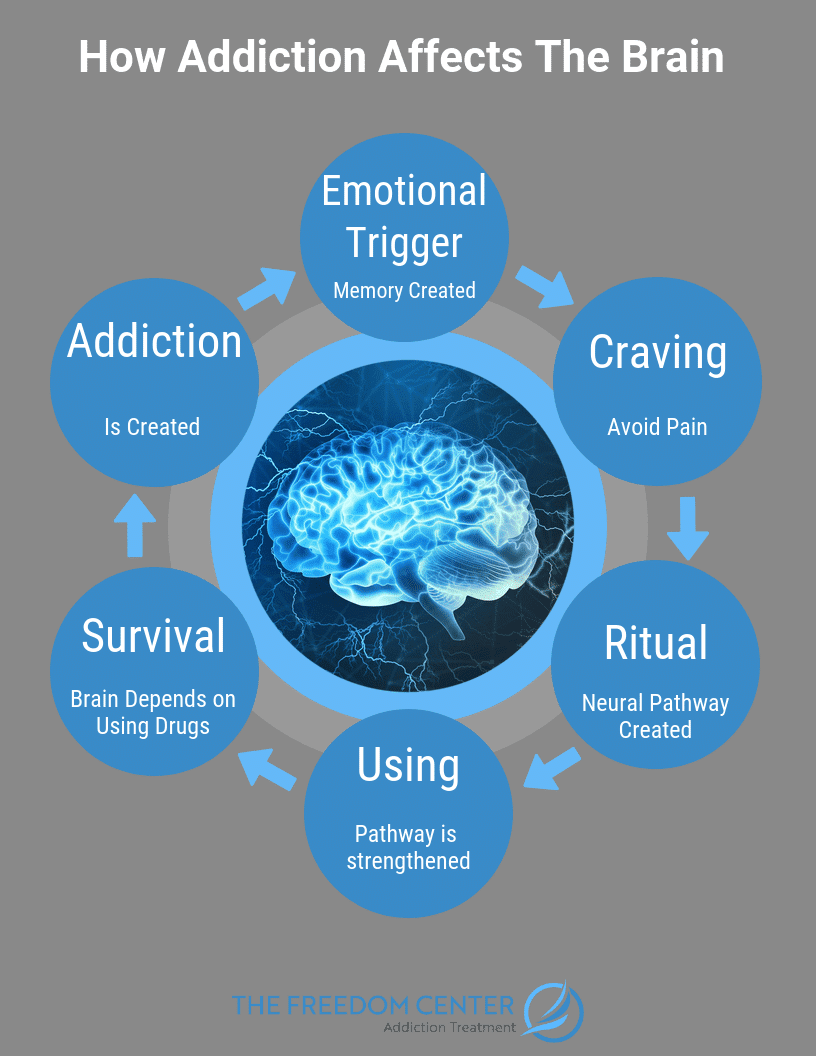
Addiction isn't primarily about willpower or moral failure. It's about how certain stimuli hijack the brain's reward circuitry and rewire learning pathways over time. The core mechanism involves dopamine release patterns that are different from normal reinforcement. When a substance or behavior produces a dopamine spike that's both rapid and predictable, the brain starts treating it as a survival priority, similar to how it processes food or water. This is why withdrawal feels so physically unpleasant, not because the person is weak, but because their nervous system genuinely perceives absence of the substance as a threat. Most people think addiction psychology comes down to pleasure-seeking. It doesn't. The research consistently shows that chronic substance use shifts the brain from seeking pleasure to avoiding discomfort. This is called negative reinforcement, and it's a fundamentally different motivation than the positive reinforcement that starts the cycle. I've seen clients who were clear-eyed about the fact that drinking wasn't fun anymore, they just couldn't function without it. That distinction matters enormously for treatment approaches. There's also a component involving the prefrontal cortex, the part of the brain responsible for decision-making and impulse control. Long-term addiction literally degrades the connectivity in this area. It's not that the person can't think clearly, it's that the neural pathways supporting executive function have been compromised. This is why even someone who genuinely wants to stop can find themselves acting against their own interests. The hardware is partially impaired, not just the motivation.
The environmental triggers are another piece that people consistently underestimate. Classical conditioning plays a massive role here. If someone has repeatedly used a substance in specific contexts, those contexts alone can trigger cravings through conditioned responses. I once worked with a client who hadn't used in nearly two years but would get an immediate, intense craving simply from walking past a particular pharmacy on his commute. It took about six weeks of deliberately rerouting his drive to break that association. The craving itself faded after roughly the third week.
How Treatment Actually Works in Practice
Cognitive behavioral therapy remains the most well-supported intervention, but it's not a magic bullet. CBT helps people identify the thought patterns that lead to substance use and develop alternative responses. The key insight is that cravings are time-limited. They peak and then subside, usually within 20 to 30 minutes. Most people don't know this, so they sit with the craving until they give in, which reinforces the behavior. Learning to wait out the urge without acting on it actually rewires the response over time. Medication-assisted treatment is another option that gets dismissed too often. Buprenorphine for opioid use disorder, naltrexone for alcohol, varenicline for smoking. These aren't replacements or cheating, they're tools that stabilize the neurochemistry so the person can engage in therapy effectively. Trying to go through behavioral change while the brain is in full withdrawal is like trying to learn a language while someone is set off fireworks next to you. The capacity to form new associations is significantly reduced. A relapse isn't treatment failure. That's a crucial point that people in recovery need to hear repeatedly. The average person with a substance use disorder experiences four or five episodes before achieving sustained remission. Each attempt teaches something about what triggers the person and what strategies don't work for them. The data shows that each prior attempt actually increases the likelihood of eventual success, not decreases it. That's counterintuitive for most people.
Get the Full Details
Common Misunderstandings That Cause Real Harm
The abstinence violation effect is a well-documented psychological phenomenon where a single lapse leads to complete abandonment of recovery efforts. Someone has one drink after months of sobriety and thinks, well I've already failed so I might as well binge. This is actually more destructive than the initial lapse because it reinforces the all-or-nothing thinking that maintains the addictive cycle. Therapists often spend significant time addressing this pattern directly. Another major misunderstanding is the assumption that detox equals treatment. Medical detox handles the physical withdrawal symptoms. It does nothing for the behavioral and psychological components that maintain addiction. Someone can be completely sober after a medically supervised detox and return to use within days because the underlying patterns haven't been addressed. Detox is a starting point, not a solution. Most people who go through detox without follow-up care relapse within a month. There's also a dangerous myth that you need to hit bottom before you can recover. The literature doesn't support this. Waiting for catastrophic consequences before engaging with treatment often means waiting too long. Damage to organs, relationships, employment, and legal standing accumulates over years. Intervening earlier, even when the person is still functioning reasonably well, leads to significantly better outcomes across nearly every measure studied.
What Helps and What Doesn't
Social support is one of the strongest predictors of long-term recovery. Not just general support, but specific recovery-oriented social networks. AA and similar mutual aid groups work for some people because they provide both accountability and a structured framework for understanding the problem. They don't work for everyone, and the religious framing is a barrier for some. The mechanism that matters is community, not doctrine. People who maintain regular contact with others who understand addiction recovery have substantially better outcomes than those who try to do it alone. Exercise has real effects on early recovery, though it's not a replacement for treatment. Physical activity increases dopamine receptor sensitivity and reduces anxiety, both of which are problematic during the first few months of sobriety. Even moderate exercise three times a week shows measurable improvements in craving management. It's a small tool, but the barrier to entry is low enough that most people can start immediately. Tracking triggers is useful but most people do it wrong. They write down "stressed" or "sad" as triggers, which is too vague to be actionable. The specific trigger is usually something like "argument with my partner followed by driving past the bar on the way home." The granularity matters. I found that a simple smartphone note-taking system where people logged the exact context, time, and emotion before each craving helped them identify patterns within two weeks that they'd been missing for years.
The Hard Limitations
No current intervention works for everyone. About 40 to 60 percent of people who enter treatment achieve meaningful improvement, which is comparable to outcomes for other chronic conditions like hypertension or diabetes. But a significant minority don't respond to standard approaches. For those people, the options are limited and research is ongoing. Experimental treatments like psychedelic-assisted therapy show promise but aren't widely available and still lack long-term safety data. Relapse rates remain high regardless of approach. Any treatment that claims otherwise isn't being honest. Addiction changes the brain in ways that persist long after active use stops. Trigger sensitivity can last for years, sometimes decades. This means recovery is a ongoing process, not a problem that gets solved and put behind you. People who treat it as a permanent condition to manage rather than a disease to cure tend to do better over the long term. The biggest limitation is probably the lack of access. Effective treatment requires trained therapists, medication, and time. Most health insurance plans provide inadequate coverage for substance use disorders. Many people simply can't afford the level of care that evidence-based practice recommends. This is a structural problem that no individual intervention can solve, and it's why outcomes vary so dramatically depending on socioeconomic status.


