Why People Can't Just Stop, Even When They Want To
Drug addiction rewires the brain's reward circuitry. That's the textbook answer. But the textbook doesn't tell you what it actually looks like when someone sits in your office at 3pm on a Tuesday, hands shaking, telling you they don't want to use anymore but their body is screaming at them to find whatever's left in the drawer. I spent years working in substance abuse counseling before moving into clinical supervision. The people who walk through those doors already know the facts. They've read the pamphlets. They've sat in group sessions where someone five years sober talked about craving so bad they considered breaking a window to get to their car. What they don't know, and what most people outside this field genuinely misunderstand, is how the psychology actually works under the surface.
The Psychology Behind Drug Addiction
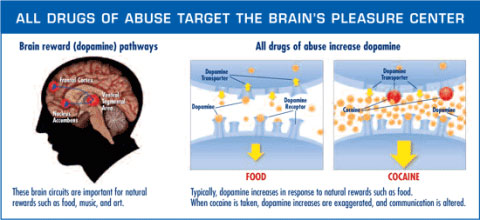
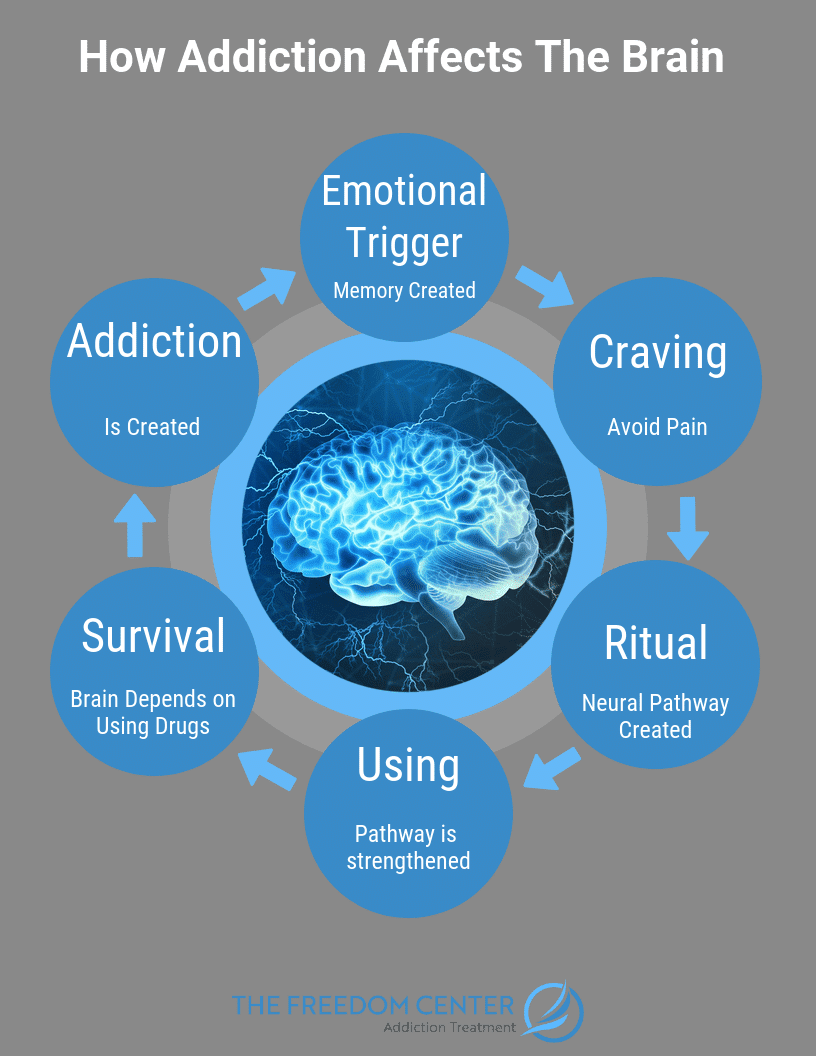
At its core, addiction hijacks the mesolimbic dopamine pathway. Drugs cause dopamine to flood the system far more than natural rewards ever do. Over time, the brain compensates by reducing its own dopamine production and downregulating receptors. This isn't willpower failing. This is neurochemistry changing the person's operating system. Here's what most guides miss: the craving isn't just about pleasure anymore. After repeated use, the brain shifts from wanting the high to wanting to not feel terrible. That's the difference between positive reinforcement in early use and negative reinforcement driving compulsive use. The person isn't chasing euphoria at six months in. They're chasing relief from a state their own nervous system has created. I remember one patient, let's call him Marcus, who was stuck in a cycle of opioid relapse every fourteen days. We mapped his triggers for weeks and kept coming up empty. No obvious stressors, no social situations that consistently led back to use. Then I asked him one specific question: what does he do between 9pm and 11pm on weeknights? Turns out, that two-hour window was completely unstructured. No obligations, no support check-ins, just him alone with his thoughts. The dopamine baseline had dropped so low during those hours that his brain was essentially begging for stimulation of any kind. We didn't need a deeper psychological breakthrough. We needed him to have a community meeting at 7:30 and a responsible friend checking in by phone at 9pm. Fixed the pattern. He's been clean four years now.
That's the thing about the psychology behind drug addiction. The mechanisms are well documented, but the application is messy. Every person's trigger architecture is different. Some people relapse because of emotional pain. Some because of environmental cues. Some because of something as simple as boredom at an hour when nobody's around to notice they're struggling.
Get the Full Details

How Treatment Actually Addresses the Root Causes
Standard programs focus on behavioral interventions because those are measurable and fundable. Cognitive behavioral therapy helps people identify the thought patterns that lead to use. Contingency management uses tangible rewards to reinforce sobriety. Both work, both have evidence behind them, and both have limitations that anyone who's actually run a program will tell you about. The limitation with CBT alone is that it assumes the person has the cognitive bandwidth to engage in introspection. During active withdrawal or early recovery, that bandwidth is severely reduced. The prefrontal cortex, which handles executive function and impulse control, is still recovering from the neurological damage. Expecting someone in that state to do cognitive restructuring is like asking someone with a concussion to solve algebra. Affectionately called "boredom protocols" in some of the programs I consulted on, the workaround is simpler than it sounds. You build structure around the weak points in someone's day. For Marcus, it was the evening gap. For others, it's mornings, weekends, or transitions like getting off work or ending a family visit. You identify the slots where the brain is most vulnerable and fill them with predetermined actions.
Medication-assisted treatment changes the conversation entirely for certain substances. Buprenorphine for opioids, naltrexone for alcohol, varenicline for smoking. These aren't crutches. They're medical tools that stabilize the neurochemical baseline so the psychological work can actually happen. The resistance to MAT in some circles is frustrating because the data is clear. People who use MAT alongside counseling have significantly better outcomes than either approach alone.
What Nobody Tells You About Relapse
Relapse rates for substance use disorder sit around 40 to 60 percent. That sounds like failure. It isn't. It's the same range as other chronic conditions like hypertension or asthma. When someone's blood pressure spikes, you don't say the treatment failed. You adjust the plan. Addiction psychology works the same way. The most dangerous misconception is the exception principle. Someone uses once after being clean for three months and decides they're back at zero. That's not how the psychology works. The neural pathways don't reset. The coping skills they built during those three months are still there, even if they forgot them in the moment of use. The key is preventing the single use from becoming a full relapse, which usually comes down to how quickly and compassionately the person re-engages with support. I've seen too many people spiral from a lapse into a full relapse because the shame was too heavy to carry back into a recovery community. The psychology here is cruel in its simplicity: addiction thrives on isolation, and shame guarantees it. The practical fix is building a support system where talking about a slip doesn't feel like a death sentence.
Another counter-intuitive point: not all cravings need to be fought. Some of the most effective approaches I've seen teach patients to observe the craving without acting on it. The craving peaks, it passes. Usually within twenty minutes. Fighting it gives it power. Noticing it without judgment strips away the secondary anxiety that makes cravings feel unbearable.
Practical Steps If You're Dealing With This
If you or someone you know is struggling, the first step is acknowledging that willpower alone won't fix it. That's not pessimistic. It's accurate. The brain has been chemically altered. Treating it requires tools that address both the chemistry and the behavior. Start by identifying the specific substance and the pattern of use. When does it happen. Where. Who's around. What happens in the hour before. Keep a log for two weeks. The data will show you something you might not have noticed. Patterns emerge that aren't obvious in the moment. Reach out to a professional who specializes in substance use. Not a general therapist. Someone who treats this regularly. The difference matters because the nuances of withdrawal management, medication options, and relapse prevention are specialized knowledge. A good provider will talk to you about all of these, not just one.
If you're supporting someone else, stop trying to manage their addiction. You can't. What you can do is set boundaries that protect your own wellbeing while encouraging them to seek help. Enabling and supporting are not the same thing. Enabling removes consequences. Supporting removes shame. Knowing the difference saves relationships. The psychology behind drug addiction is complex but not mysterious. The brain changes, the behavior adapts, and recovery means rebuilding both on new terms. It's hard work. It's not heroic. And it's absolutely possible, one day at a time, for people who stick with it long enough to see the neuroplasticity work in their favor.