Most people in psych nursing never really learn this in school. They just pick it up by doing it wrong for a few years.
Therapeutic communication isn't about reciting textbook phrases at a patient. It's about knowing what to say, when not to say anything at all, and how to read the gap between what someone is telling you and what they're actually feeling. I spent about eight years on a med-psych unit before moving to outpatient work. The patients who got better weren't the ones I had the most sophisticated language for. They were the ones I listened to correctly. Let me start with something that surprised me when I first started: validation and empathy are not the same thing. Validation says "it makes sense you feel this way given what happened." Empathy says "I can imagine how hard that must be for you." Both have their place. But I learned the hard way that leading with empathy too early can come across as patronizing. A patient who's been hospitalized three times for the same issue doesn't need you to imagine how hard it is. They need you to acknowledge the pattern without flinching. Here's how the actual techniques break down in practice, not in a textbook:
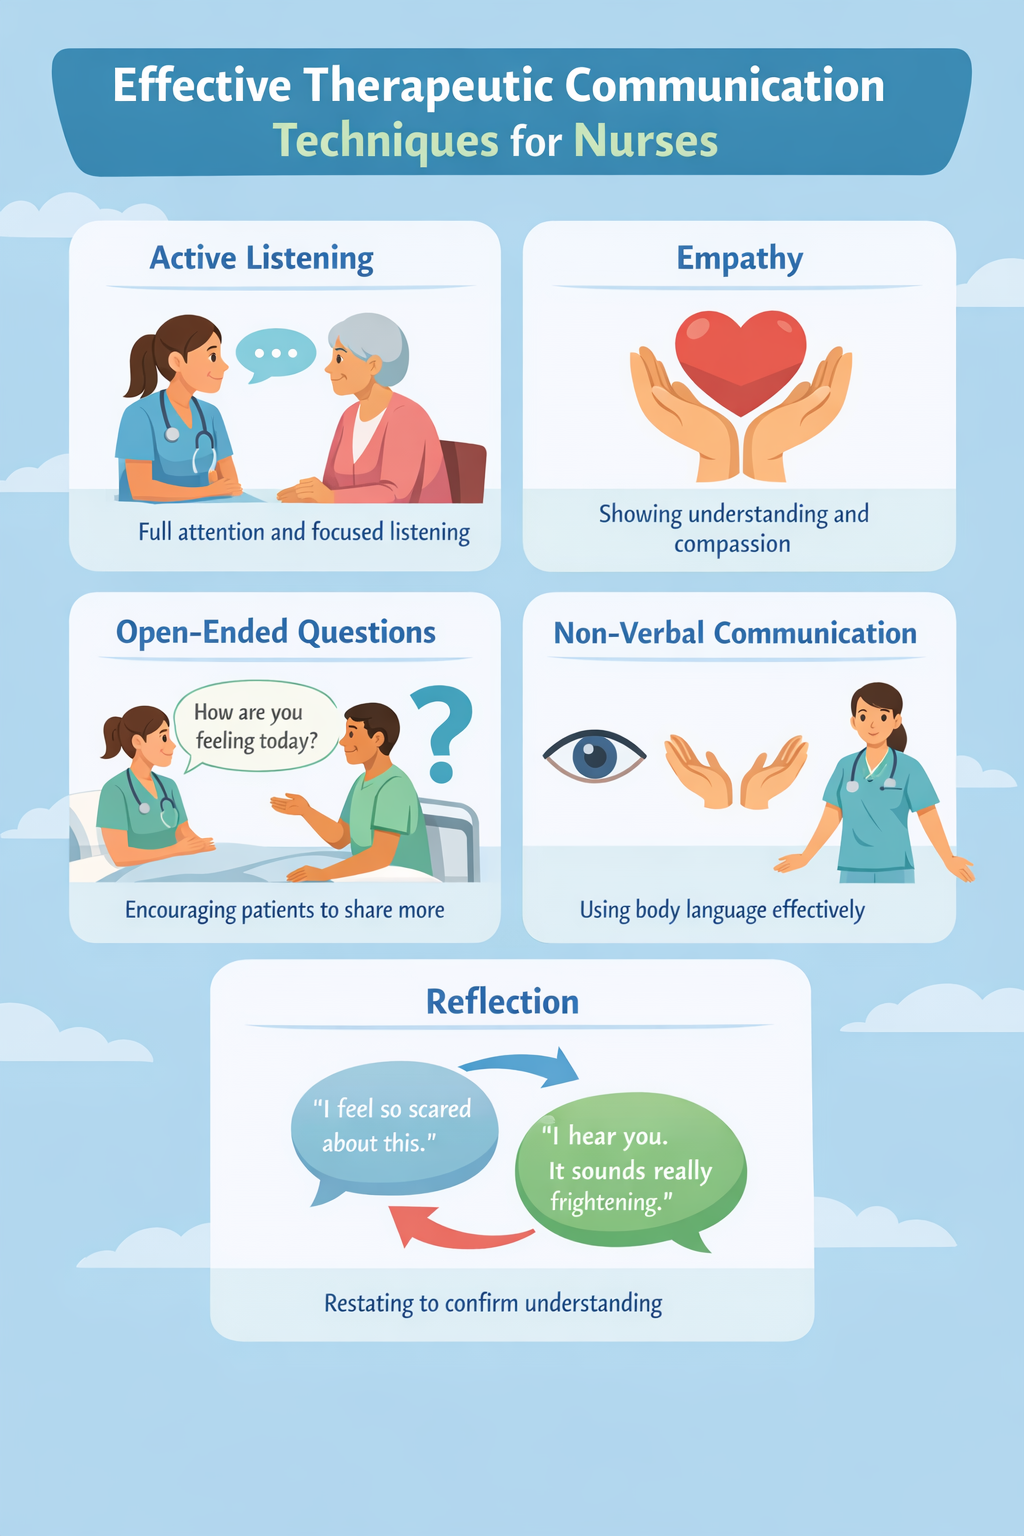
Open-ended questions — This is the bread and butter. "Tell me more about that" or "What was that like for you?" works because it can't be answered with a yes or no. But the trap here is asking too many of them in a row. I had a patient on the acute floor who got agitated when I kept probing. She'd answer honestly, then I'd pivot to another open question and she'd shut down. The workaround was to mix in some reflective statements between questions so she felt heard before being asked to go deeper. One open question, one reflection, then pause. Restating and paraphrasing — Repeat back the core of what the patient said in your own words. "So what I'm hearing is that you felt abandoned when your visit was cancelled." This does two things. It confirms you understood correctly. It also gives the patient a chance to correct you, which builds trust faster than any reassurance you could offer. The version I see most often done wrong is the one where the nurse restates verbatim instead of paraphrasing. That reads as robotic and makes patients feel like they're talking to a recording device. Offering self — This technique means disclosing a small amount of your own experience when it serves the patient. "I've noticed you seem to get quiet every time we talk about family. I'm curious if that's something that comes up for you." It's different from sharing your own personal problems, which is non-therapeutic. The boundary is thin and people mess it up constantly. I once had a new nurse tell a depressed patient "I know exactly how you feel, my grandma went through the same thing." That's not offering self. That's redirecting the conversation to herself. The patient's response was immediate withdrawal. Don't do that.
Using silence — This is the hardest one to master because it feels uncomfortable. Silence in a therapeutic context isn't awkward waiting. It's an active technique. You sit with the patient and give them space to process. Most nurses fill silence within three seconds because they're uncomfortable. That's usually when the patient is actually about to say something important. I used to pace myself by counting to ten silently before speaking after a patient shared something heavy. Ten seconds feels like an eternity in a busy shift but it makes a measurable difference in what patients volunteer next. Reflecting feelings — Name the emotion you're observing. "You sound frustrated" or "It seems like you're feeling hopeless about this." The key is guessing the feeling, not the content. If you reflect content back ("So your mother called and that upset you"), you're just restating. If you reflect feeling ("That conversation left you feeling hurt"), you're going one level deeper. Patients will often correct you on this and then clarify what they actually feel, which is progress in itself. Broad openings — Start conversations with "What would you like to talk about today?" instead of leading with your agenda. This gives the patient control over the direction, which matters enormously for people who have spent weeks or months having their daily routines dictated by staff. I've seen patients on locked units become visibly more cooperative simply because you asked their input first instead of announcing what you needed to accomplish.
Get the Full Details

Now let me address the part nobody talks about enough: these techniques fail in specific scenarios and you need to know when to stop using them. Poor judgment or acute mania — Open-ended questions with a manic patient who's racing through thoughts will either escalate them or frustrate them into silence. During acute mania, short direct statements work better. "Take your medication now" or "Let's sit here together for a few minutes." Save the reflective listening for when the episode has calmed. Paranoid psychosis — Asking a paranoid patient to elaborate on their delusions sounds therapeutic but it actually reinforces the psychotic framework. I worked with a patient who had elaborate beliefs about surveillance. A well-meaning colleague kept asking "What makes you feel like they're watching you?" which only gave the delusion more airtime. The workaround was gentle reality grounding without confrontation. "I don't see any cameras in this room, but I understand that you feel watched. Let's focus on what's happening right now between us."
Catatonic or severely withdrawn patients — Traditional therapeutic communication requires some level of verbal engagement. With a catatonic patient, your presence matters more than your words. Sitting nearby, using a calm tone, and offering simple yes-or-no questions is more effective than pushing for open-ended dialogue. I had a schizophrenic patient who hadn't spoken in four days. I stopped asking her to talk and just narrated what I was doing while making her tea. On day six she said her first words: "How did you know I take it with honey?" Small wins matter. One counter-intuitive thing I want to mention: documentation and therapeutic communication exist in tension. Every time you stop to chart during a conversation, you break the therapeutic alliance. I learned to do my notes in shorthand during the interaction itself and expand them afterward. A quick scribble of "Pt denies SI/HI, affect congruent" takes two seconds and preserves the flow. If you wait until after the session to document everything, you'll either rush it or forget details. The tradeoff is your handwriting might be illegible, but your patient will be more engaged. Another nuance beginners miss: matching the patient's communication style. A patient who speaks in short blunt sentences doesn't need a long reflective response. Mirror their brevity. A patient who talks in circles and details needs you to gently redirect, not match their tangential style. I found that adjusting my verbal pace and length to match the patient within reason made them feel understood faster than any specific technique. It's basically conversational rapport building adapted for clinical settings.
The biggest limitation of all these techniques is that they require time. Real time. Not the eight minutes you have between rounds on a 24-bed unit with three patients in crisis. When staffing is short, therapeutic communication becomes triage communication. You identify who can engage meaningfully and who needs a quick check-in, then allocate your attention accordingly. This isn't ideal but it's reality. Some hospitals try to solve this with scripted interventions and patient education packets. Those help with consistency but they don't replace actual human connection. I've seen well-staffed units with excellent communication skills produce better outcomes than under-staffed units with rigid protocols, and I've seen the opposite happen when protocol became a checkbox exercise. If you're trying to actually improve your skills, the most efficient method I found was peer observation with structured feedback. Spend one shift watching a senior nurse run a therapeutic interaction, then debrief for fifteen minutes. Ask them specifically what they noticed about the patient's body language and why they chose that particular response. This is faster and more effective than any workshop I attended. Reading about techniques gives you vocabulary. Watching someone use them in real time gives you judgment. A final note on what these techniques are not: they are not a substitute for medication management, they are not therapy in the psychotherapy sense, and they are not a guarantee of positive outcomes. A patient can respond perfectly to every technique and still not improve. Psychiatric nursing is part art, part science, and part acceptance that you cannot control another person's healing. Your job is to create the conditions where healing becomes possible, then document what you did and move to the next patient.