So You Want to Run a Group
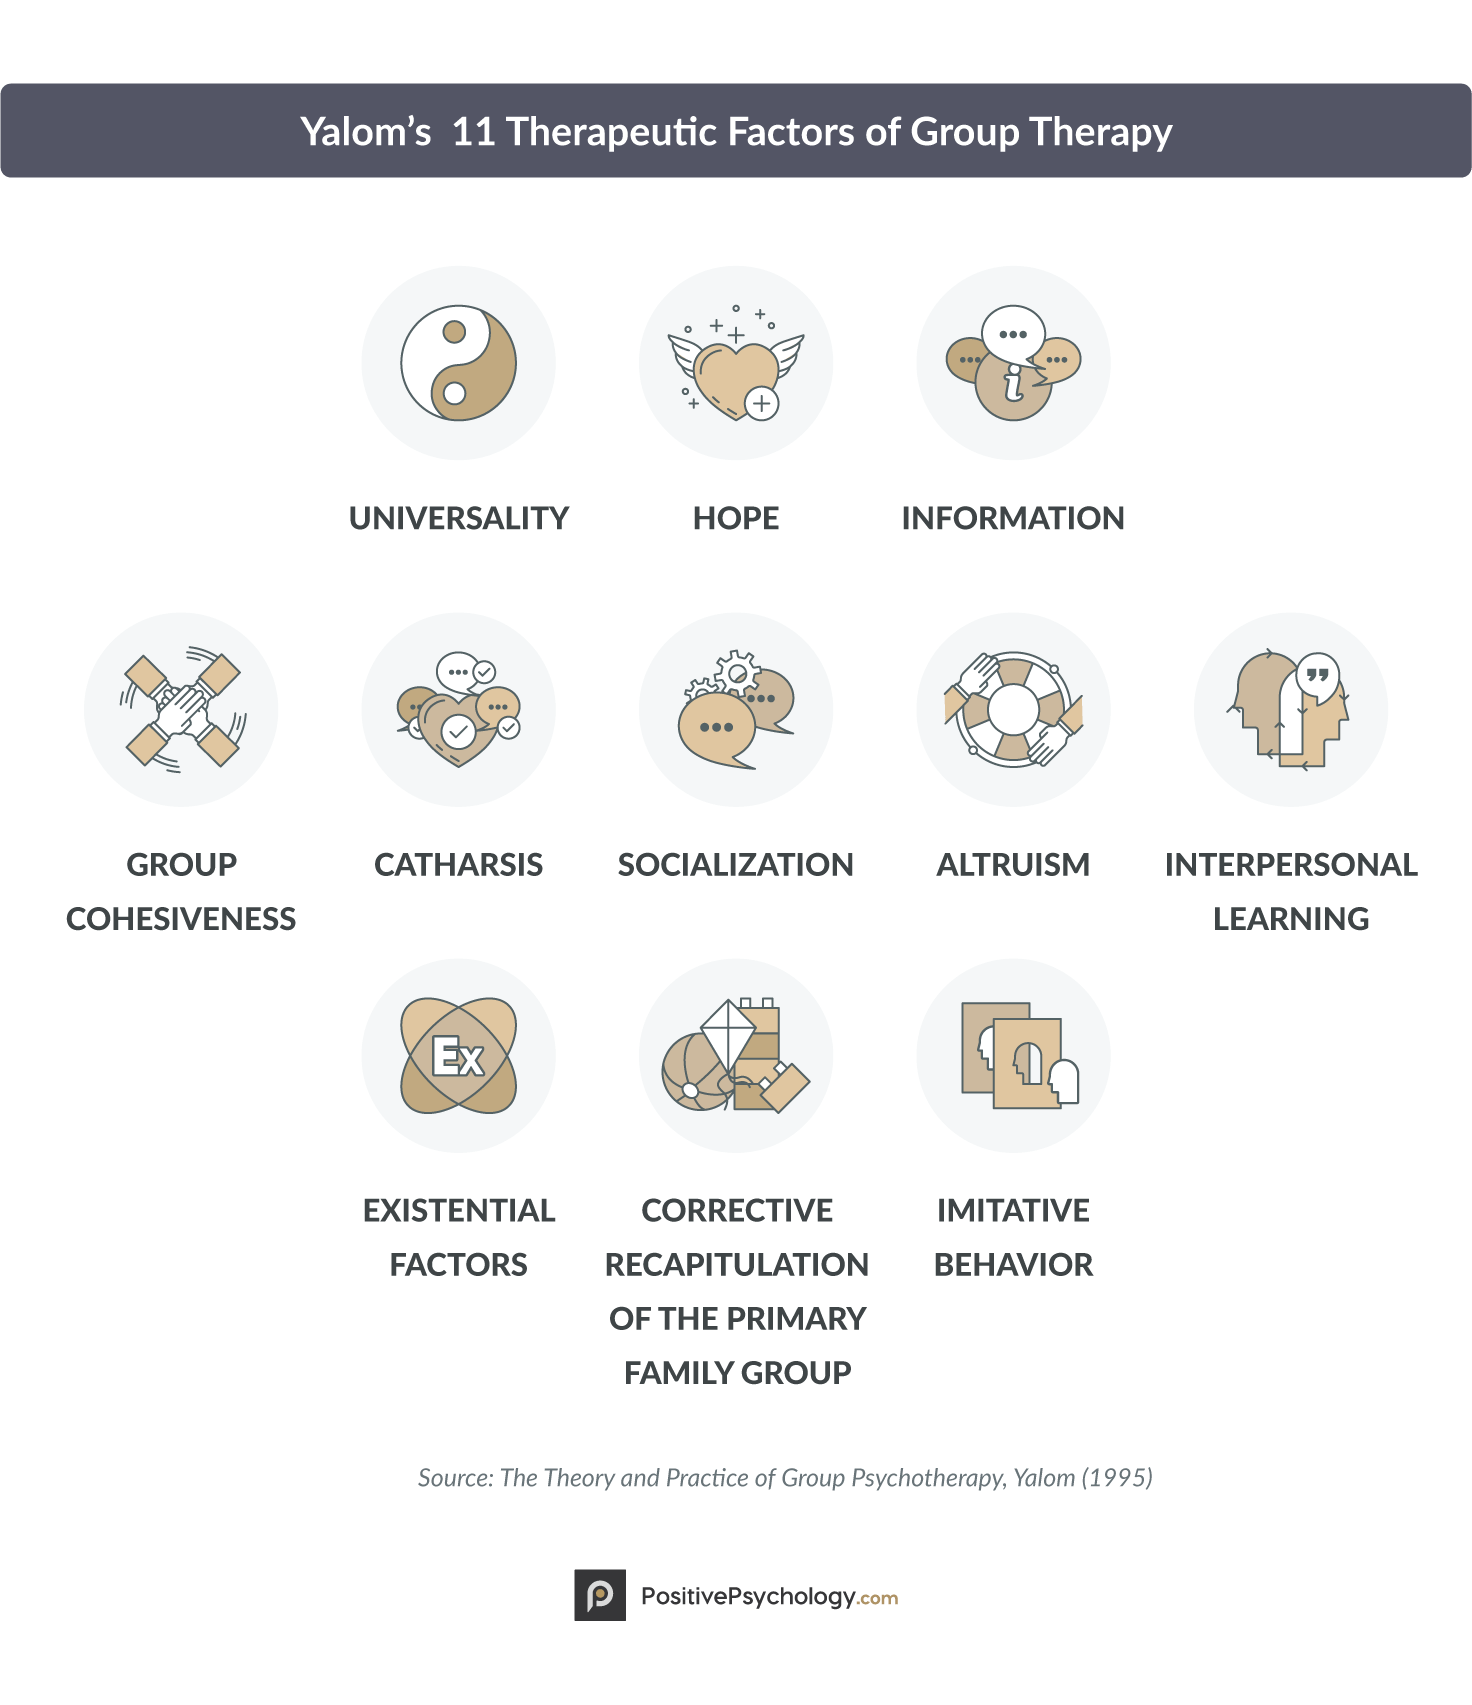
Most people come into group therapy thinking it is just several individuals in a room sharing problems together. That is the surface description. The real work happens in the interactions between the members, not inside any single person's head. Yalom mapped this out decades ago, but the map is not the territory. When you are actually sitting in that circle watching dynamics unfold, you need to understand which levers are pulling and which ones are just making noise. Instillation of hope is usually the first thing that kicks in. Someone new walks in thinking they are broken beyond repair. They watch another member three sessions back who was in similar shape and is now functioning reasonably well. That observation does more for them than any therapist's reassurance ever could. I had a borderline personality client once who refused to believe progress was possible until she saw someone with a diagnosis worse than hers hold down a job and maintain a relationship. That one data point shifted her entire trajectory. Universality is the relief that comes from discovering your shameful secret is not actually unique. This factor hits hardest early on. A member will say something they have never voiced aloud — infidelity, a violent impulse, a deep-seated hatred toward a parent — and the room stays silent for a beat before someone else nods and admits to something equally dark. That moment of shared humanity reduces isolation faster than any interpretation. The catch is that universality can also reinforce pathology if the group becomes a mutual admiration society for shared maladaptive patterns. You have to keep the focus on change, not just validation.
Altruism sounds touchy-feely until you see it work. A member who has spent their life feeling worthless starts giving useful feedback to someone else. They feel competent. Their self-image shifts from defect to resource. I once had a chronic depressive in my group who was completely inactive outside sessions. When another member was struggling with a social anxiety situation, this depressed client offered concrete advice that actually helped. The look on his face afterward — he could not stop looking at his hands — told me everything about what had just happened neurologically. Development of socializing techniques is where the actual skills get built. You are not discussing communication theoretically. You are practicing it in real time with real emotional stakes. A member who has always avoided conflict will find themselves in a micro-confrontation with another group member. The therapist's job is not to rescue them from it but to make sure they stay in it long enough to learn something. Corrective recapitulation of the primary family group is the factor that makes group therapy controversial and powerful at the same time. The group naturally organizes itself around roles that mirror family dynamics. There is usually a parental authority figure, a scapegoat, a favorite child, a rebel. Members replay childhood relational patterns with genuine people rather than abstract memories. This means the emotional charge is much higher than in individual therapy because the "family" is sitting right there reacting in real time.
Cohesion is the group equivalent of the therapeutic alliance in individual work. It is the glue that holds everything together. Without sufficient cohesion, the other factors have nothing to attach to. But cohesion that gets too strong without enough challenge becomes a supportive bubble that protects members from growth. I once ran a group where the cohesion was so high that members started socializing outside sessions and the group dissolved into a friendship circle. Therapy stopped happening. I had to explicitly intervene and redirect the energy back toward interpersonal work. Imitative behavior means members absorb models from the therapist and from more advanced group members. A shy person will pick up coping strategies by watching someone bolder handle the same situation. This is why group composition matters enormously. Mixing members at very different stages of interpersonal development creates natural modeling opportunities that would take months to engineer in individual work. Interpersonal learning is arguably the single most important factor. It operates through two channels: the group-as-microcosm and feedback from members. People discover how they come across to others. Their interpersonal problems that manifested outside the group show up inside the group almost immediately. A controlling manager will start controlling the group. A passive-aggressive employee will find their passivity becoming visible to everyone. The learning happens not from being told but from experiencing the consequences of your behavior in real time.
Get the Full Details

Catharsis is the expression of previously suppressed emotion. It is often mistaken for the main point of group therapy by outsiders, and sometimes by novices in the field. Catharsis without cognitive restructuring is just emotional purging. It feels good in the moment and then nothing changes. The breakthrough comes when the emotional expression is followed by insight about why that emotion was being suppressed and how it connects to current relational patterns. Existential factors deal with the ultimate concerns: responsibility, freedom, isolation, and death. Members confront the fact that no one else can live their life for them. The group cannot save them. They are responsible for their own choices. This sounds abstract until someone realizes that attending group consistently is actually their choice and that showing up or not showing up communicates something about how they show up in every other area of life.
What Actually Happens When You Start Running These
The first session always goes differently than you planned. You will sit there with your carefully prepared introduction about confidentiality and group norms and someone will immediately violate one of them. Not maliciously. Just because that is how they operate in the world. Your job is not to police compliance but to use the violation as material for the group to explore. By session three you will notice the hierarchy forming. There is always a most talkative person, a most quiet person, and a person the group gravitates toward for advice even though you never appointed them as a leader. If you try to manually redistribute speaking time you will create resistance. The more effective move is to draw the quiet person out by asking specifically for their reaction to what the talkative person just said, and to gently interrupt the dominant speaker by noting the pattern you are observing. Session five is usually when the real work begins. The polite phase is over. Members start pushing against each other. Someone will challenge another's perspective and defensiveness will rise. This is the moment most therapists either retreat into directing too much or fail to contain adequately. The sweet spot is letting the conflict happen while making sure nobody gets abandoned emotionally in the process.
I learned the hard way about cross-talk. Early in my career I had two members who would talk past each other in a way that was fascinating to watch but produced zero therapeutic value. They were performing for the group rather than connecting. I spent thirty minutes trying different interventions before realizing I needed to simply name what was happening in the room and ask if anyone else had noticed the same pattern. Once I verbalized it, the group collectively saw the avoidance and the dynamic shifted toward something productive.

The Edge Cases And When This All Falls Apart
Group therapy does not work for everyone. Active psychosis is an obvious exclusion. Acute suicidal crisis is another. But the subtler exclusions are things like severe narcissistic personality disorder where the person cannot tolerate any feedback that does not align with their self-image, or severe antisocial traits where the person will manipulatively use group insights against other members. I once had a client with traits of both who pretended to be moved by another member's vulnerability and then referenced it later in a completely different context to undermine them. That group never recovered its trust. I should have screened more carefully. The biggest mistake I see therapists make is assuming that because individual therapy works for a client, group therapy will automatically work too. The skills required are different. Some people are exquisitely functional in one-on-one settings and completely disorganized in groups. The reverse is also true. Screening should include an assessment of interpersonal functioning, not just symptom severity. Another pitfall is starting with a homogeneous group. Two trauma survivors together sounds like a good idea. What actually happens is they reinforce each other's victim narrative and nothing moves forward. Heterogeneity in diagnoses and backgrounds creates more friction, yes, but friction is the point. It generates the heat for change.
There is also the issue of group size. The research literature generally settles on six to eight members as optimal. Anything larger and the speaking time fragments to the point where meaningful interaction becomes impossible. Anything smaller and the group loses resilience when one member misses a session. I ran a seven-person group where one member was chronically absent and it effectively became a six-person group. That worked fine. But when a different member dropped out unexpectedly, we went to five and the group felt fragile and overextended. We stopped accepting new members until we could stabilize.
A Practical Note On Structure
You need some structure or the group will drift into complaint session territory within twenty minutes. A simple opening round where each person states what they want to focus on takes about ten minutes and sets the direction. Mid-session check-ins every twenty minutes prevent anyone from monopolizing or completely disengaging. Closing with a brief round of what each person is taking away anchors the learning. The actual therapeutic factors do not require elaborate technique. They emerge from the natural life of the group when the therapist creates conditions for them to surface and knows how to use them when they do. Your interventions are mostly about timing and precision, not about having a large toolkit. Name the pattern. Point to the here and now. Ask what the person in front of you is experiencing. Repeat until something shifts. The factors I described above are not checklist items to tick off. They are interdependent processes that reinforce each other. Cohesion enables interpersonal learning. Interpersonal learning generates catharsis. Catharsis deepens cohesion. Hope grows when you see someone model a new way of being. The system is self-correcting once it gets enough momentum. Your main job is keeping the engine running long enough for that momentum to build.