What Lymphoma Treatment Actually Looks Like in Practice
Getting Your Therapy For Lymphoma Sorted
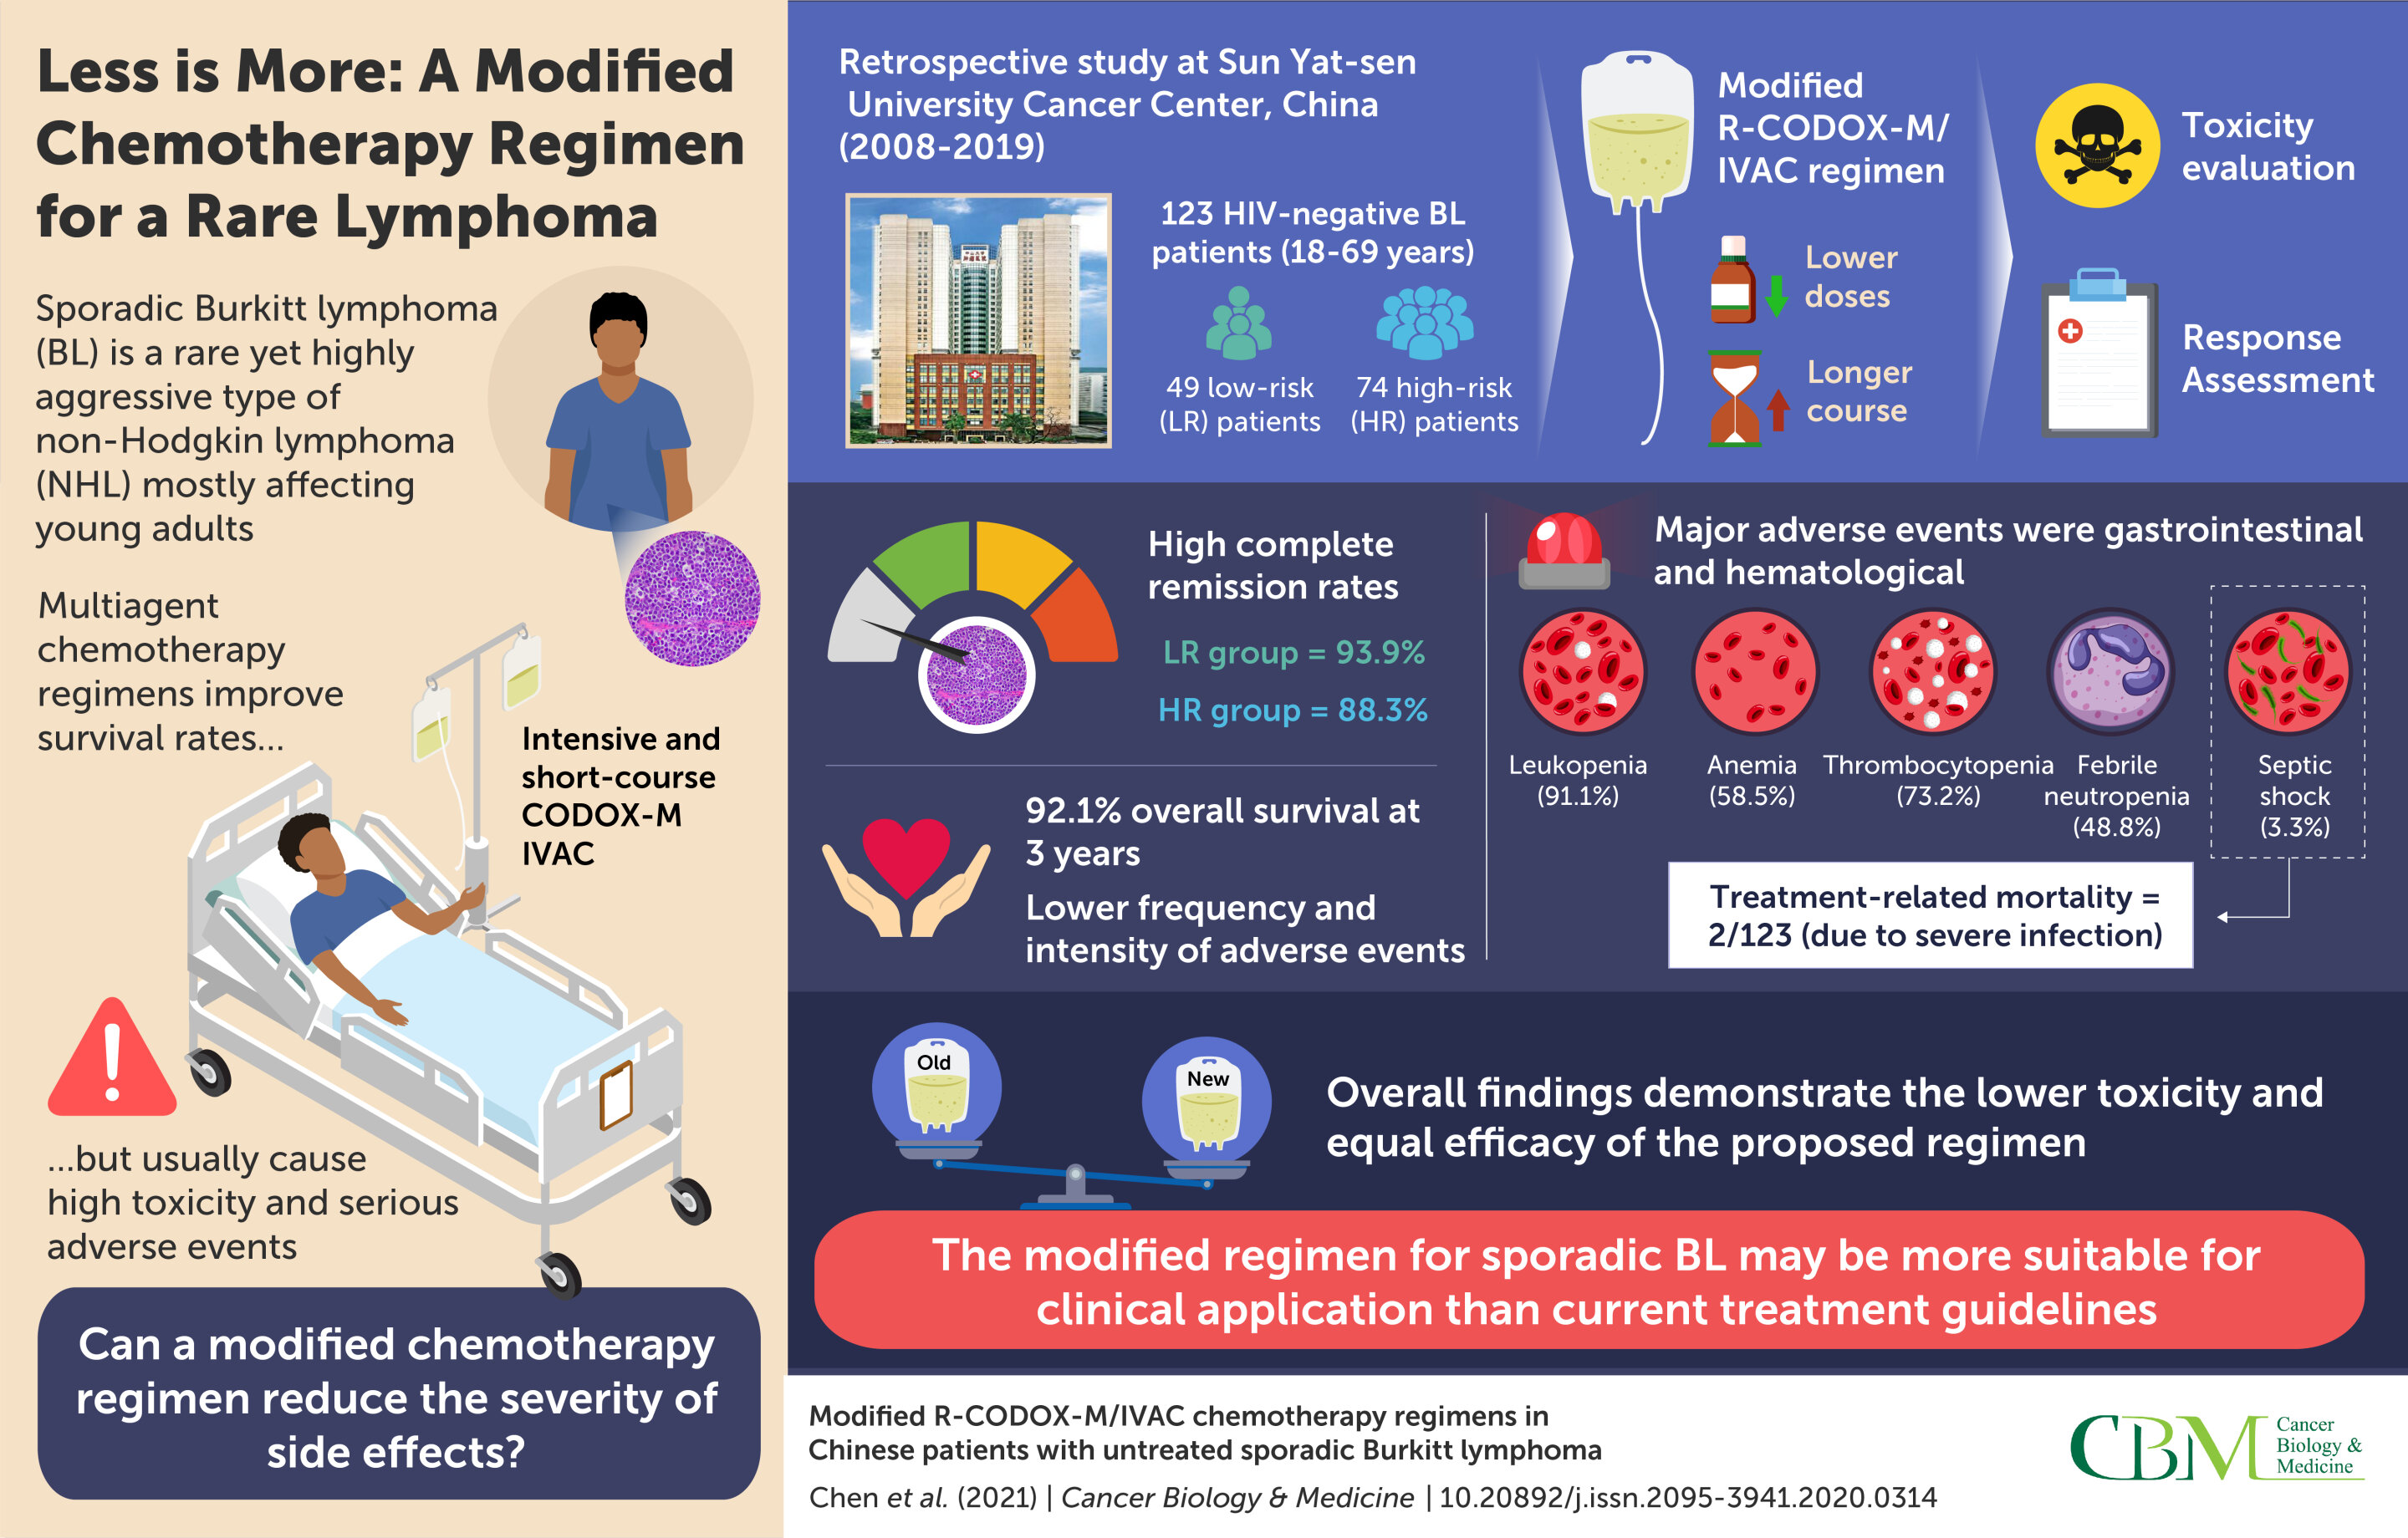
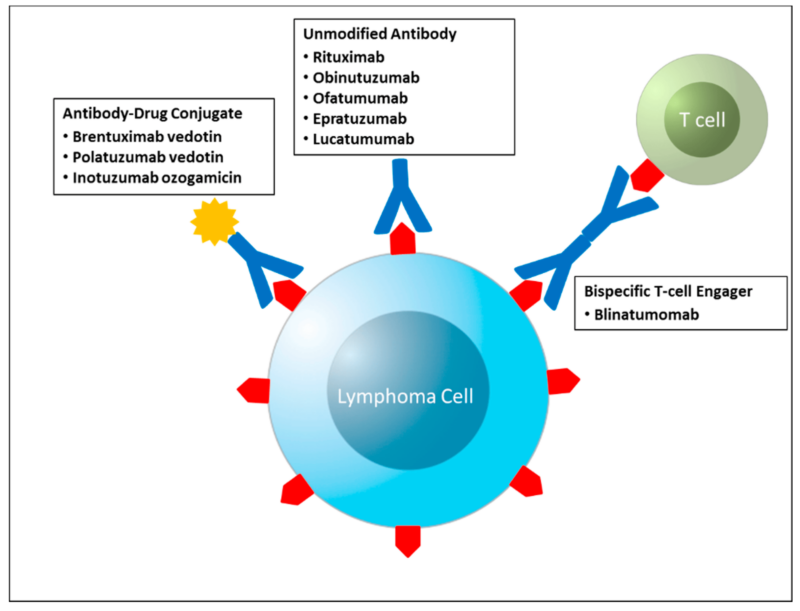
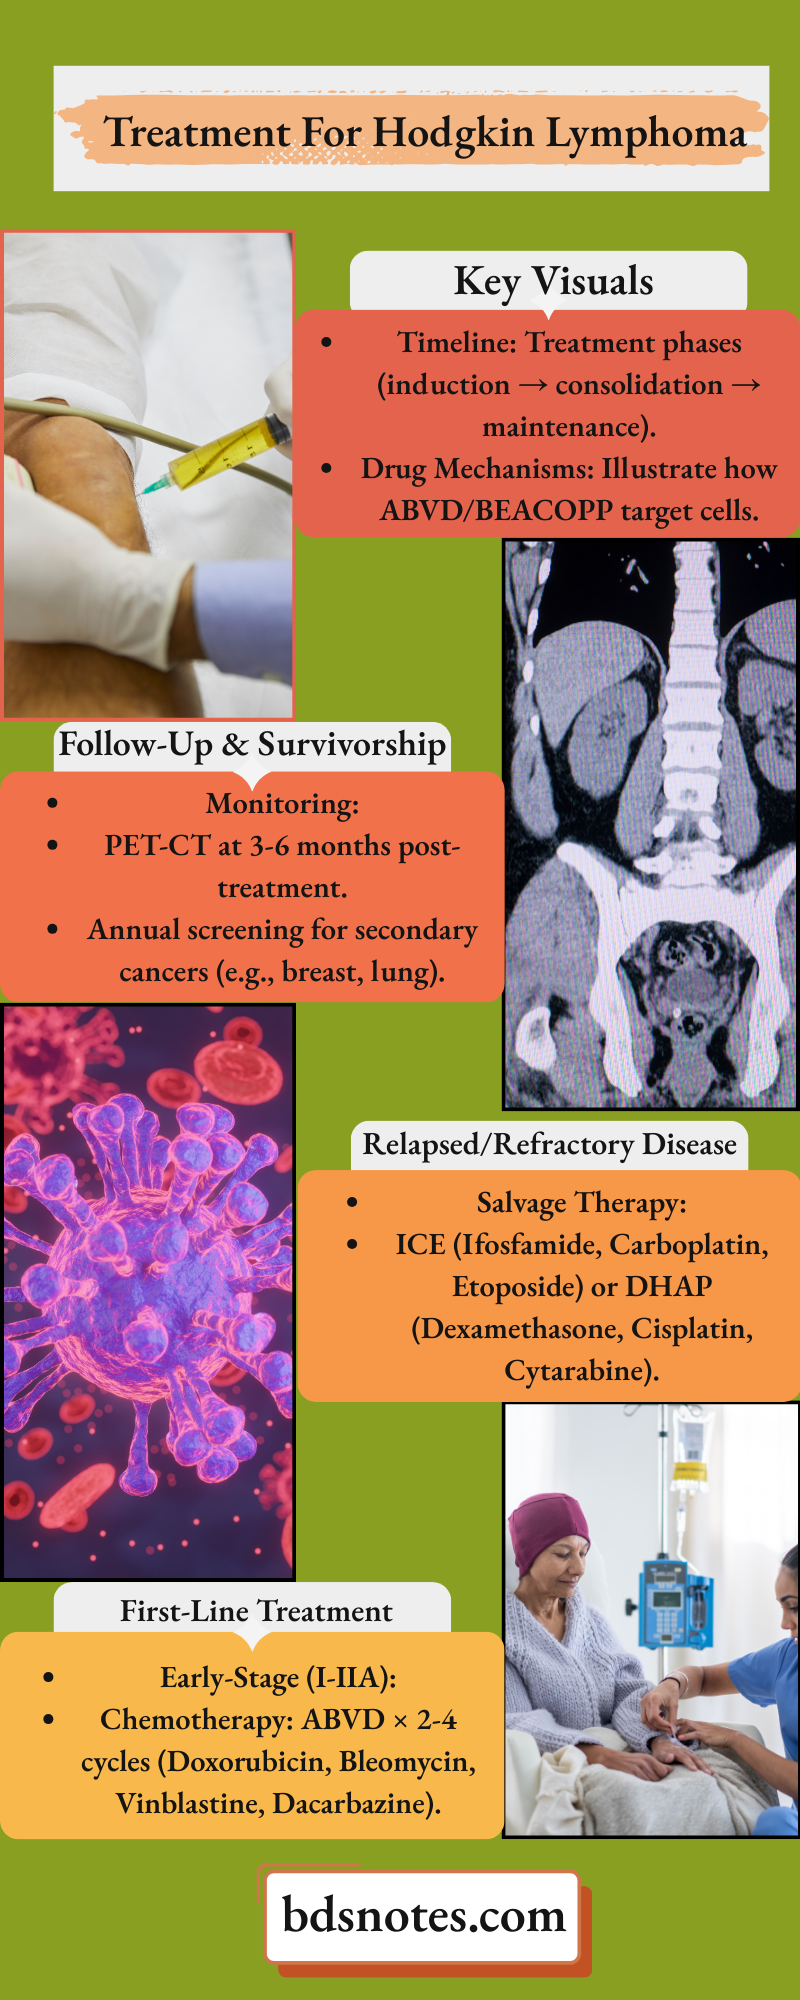
Most people find out they have lymphoma and immediately start Googling, which is fine until they realize there are about fourteen different treatment protocols depending on subtype. Hodgkin and non-Hodgkin lymphomas are handled completely differently. I spent years watching patients get steered toward one-size-fits-all advice online when the reality is much more specific. The first thing you need is your exact subtype and stage. Without those two data points, every treatment discussion is just noise. Chemotherapy remains the backbone for most aggressive lymphomas, and R-CHOP is the standard regimens people know about. It's a combination of rituximab, cyclophosphamide, doxorubicin, vincristine, and prednisone given in cycles typically three weeks apart. The cycle length matters because it gives your bone marrow time to recover between doses. Some patients do better with dose adjustments early on rather than pushing full doses through side effects. I've seen oncology teams stick rigidly to protocols when the patient was clearly deteriorating, and the adjustment wasn't made until week three instead of week one. Immunotherapy has changed the landscape considerably. Brentuximab vedotin targets CD30-positive cells and has become a standard option for certain subtypes where chemotherapy alone wasn't cutting it. CAR T-cell therapy is another development that's reshaped treatment for relapsed cases. It's not a first-line approach usually, but for patients who've exhausted standard options it can be the difference between progression and remission. The manufacturing process alone takes about two to three weeks, so timing and logistics matter more than most people realize.
Radiation therapy plays a role, particularly for early-stage disease or when specific nodes need consolidation after systemic treatment. It's not as aggressive a tool as it used to be because of late-side effect concerns. Secondary cancers and cardiovascular damage from mediastinal radiation are real considerations, especially in younger patients. I worked with a case where a patient in their twenties got involved in a debate about whether post-chemo radiation was necessary. The answer depended heavily on the initial response to chemo and the specific lymph node involvement. Skipping radiation when it would have helped led to a local recurrence within fourteen months. Stem cell transplantation is on the table for certain situations, usually autologous transplants for eligible patients who relapse. Allogeneic transplants are rarer and carry more risk but offer a graft-versus-lymphoma effect that can be curative. The conditioning regimen before transplant is brutal. You're essentially wiping out your immune system completely. Recovery takes months, not weeks, and infections during that window are the primary danger rather than the lymphoma itself. Watchful waiting is a legitimate approach for indolent lymphomas like follicular lymphoma. These grow slowly and don't respond well to aggressive treatment upfront. Starting chemo too early in these cases doesn't improve overall survival and just exposes the patient to toxicity without benefit. I saw this happen repeatedly. Patients would get anxious about the diagnosis and push for immediate treatment, only to face side effects that reduced their quality of life for no measurable gain. The data is clear on this one, but the emotional pressure to "do something" is real and often overrides what the guidelines say.
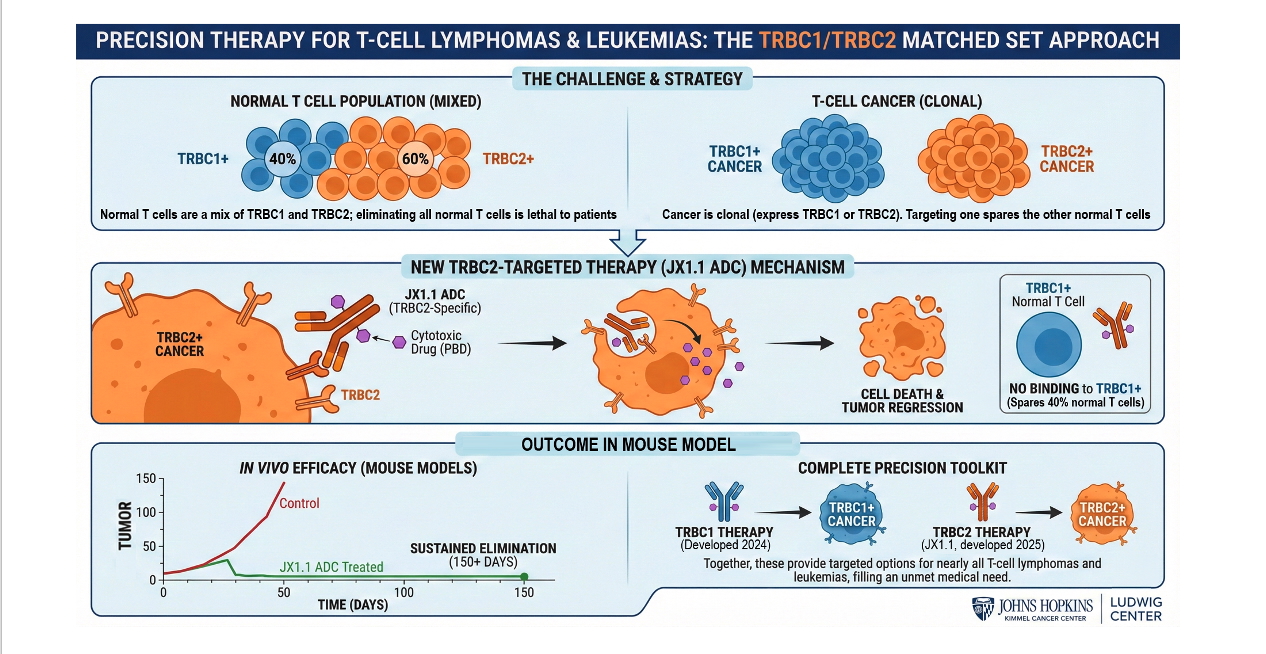
Targeted therapies like BTK inhibitors have opened up options for mantle cell lymphoma and other subtypes. These are oral medications taken continuously rather than in cycles. The tradeoff is that they control the disease but rarely cure it. Stopping them usually means the lymphoma comes back. I had a patient manage this for nearly four years before resistance developed, which is about the average lifespan on these drugs before progression sets in. The psychological component of treatment is something nobody prepares you for. Missing work, hair loss, the nausea that doesn't fully go away even with modern antiemetics, the fatigue that makes simple tasks exhausting. These aren't side effects you push through quietly. They're cumulative. I've watched patients skip follow-up scans because the anticipation of the results was paralyzing, and by the time they showed up something had changed that might have been caught earlier. One practical issue that comes up constantly is drug access and insurance authorization. R-CHOP is generic, so that's straightforward. But rituximab biosimilars, brentuximab, and CAR T-cell therapy all face authorization hurdles that can delay treatment by weeks. Having your oncology team's navigator or social worker on the case from day one makes a measurable difference. I once traced a three-week delay back entirely to an insurance pre-authorization that could have been filed on the same day the diagnosis was confirmed if someone had just started the paperwork immediately.
Get the Full Details

Second opinions are worth getting, but you need to bring your actual pathology slides and imaging, not just the reports. Pathology review changes the diagnosis in a notable percentage of cases, and treatment decisions based on an incorrect subtype are wasted effort. Bring everything to the consultation. Don't assume the new oncologist will request the records themselves. There's no single path that works for everyone. The treatment you end up on depends on subtype, stage, age, comorbidities, and how your body responds cycle by cycle. The information online is useful for understanding options, but the actual decisions happen in rooms between you, your oncologist, and sometimes a multidisciplinary tumor board. Knowing what questions to ask beforehand saves time and reduces the chance of leaving that appointment with more confusion than clarity.