Getting Thyroid Weight Loss Success Is Harder Than People Think
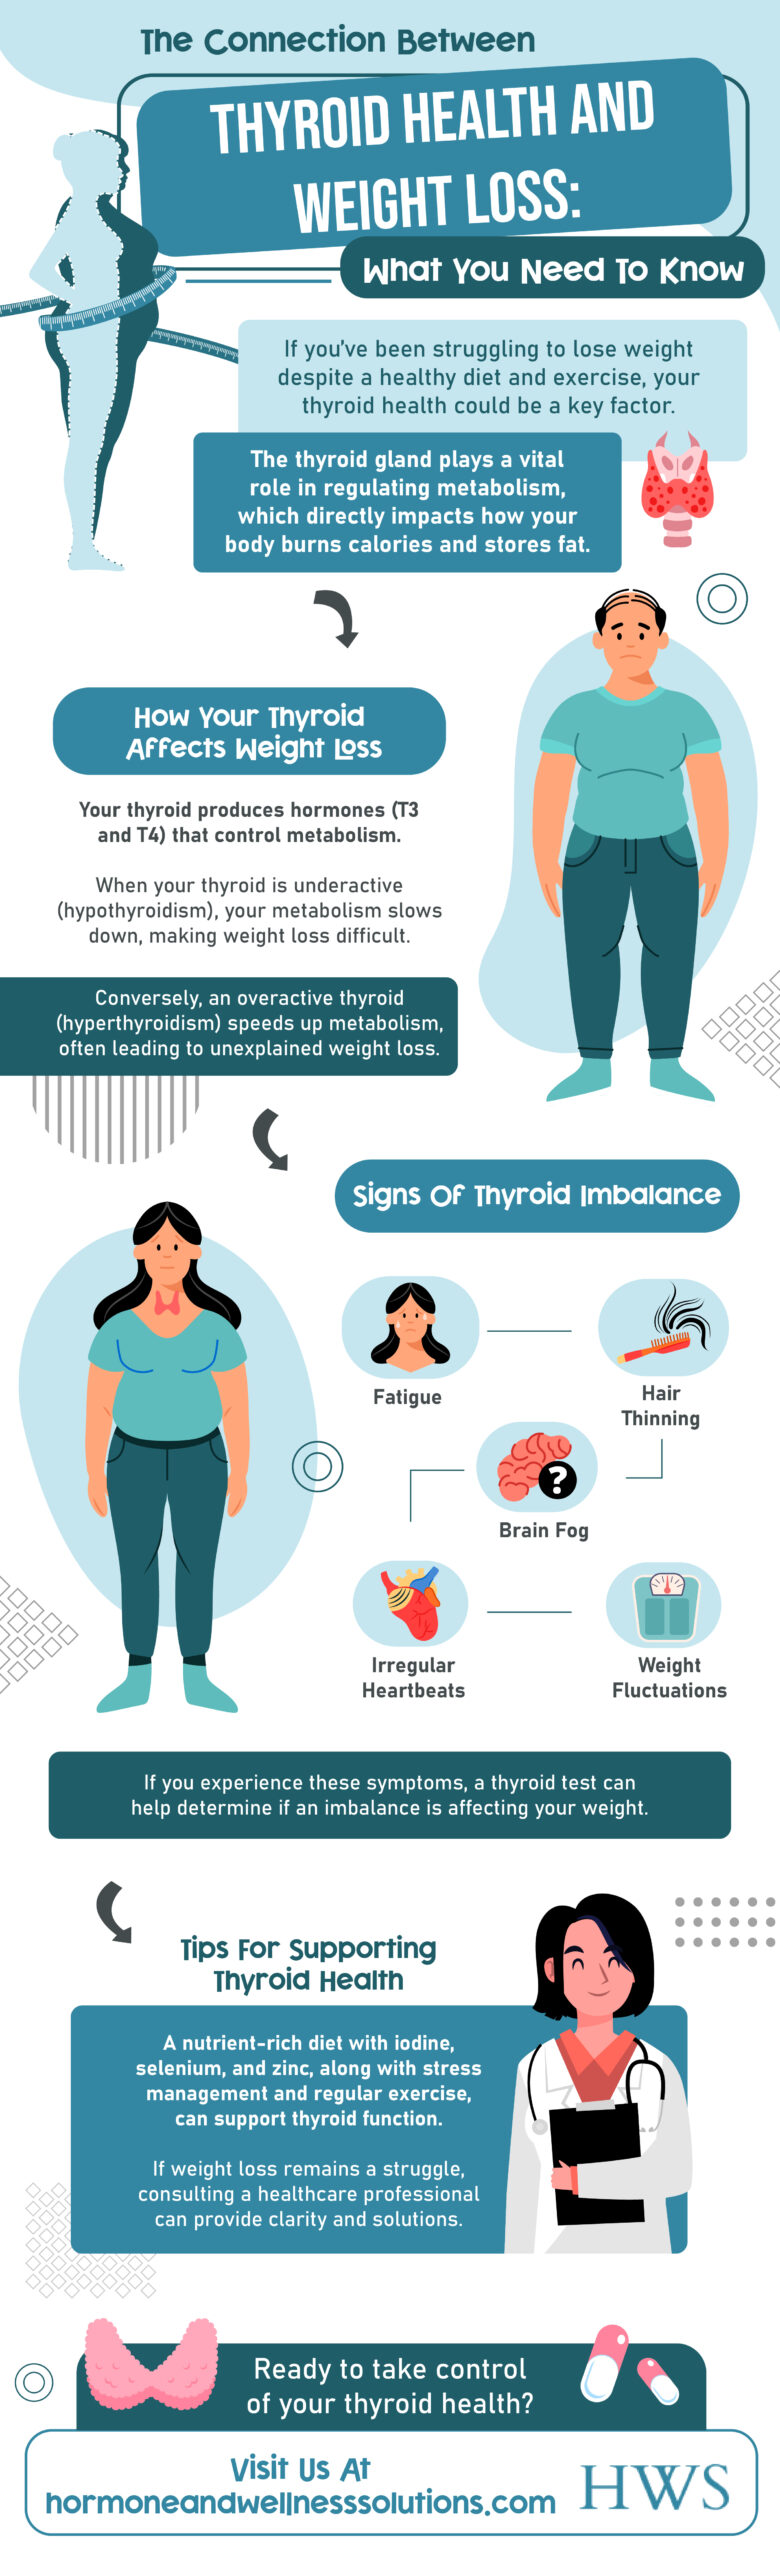
I spend most of my days reviewing blood panels and medication logs from people who were told their thyroid was "fixed" but still couldn't drop weight. There's a reason for that. Treating hypothyroidism doesn't automatically unlock weight loss, and most guides online completely gloss over that fact. Success here means getting your TSH into the optimal range, which is roughly 0.5 to 2.5 mIU/L for most people on treatment, then watching what actually happens. The drug of record is levothyroxine, a synthetic T4. You take it once daily, fast, and wait six to eight weeks before rechecking. That's the standard protocol. Most people who chase thyroid weight loss skip the waiting period and blame the medication when their labs haven't stabilized yet. I had a client last year who was taking her levothyroxine with her morning coffee. Not because she wanted to, but because she was already drinking coffee anyway and the pill just... sat there. Her TSH was 8.2 despite being on 100 micrograms. She switched to taking it with water only, at least 30 minutes before food, and her TSH dropped to 1.9 within two months. No diet change, no exercise change, just the absorption issue resolved. That's how common this mistake is.
The deeper problem is that not everyone responds the same to T4 monotherapy. Some patients convert T4 to T3 poorly due to genetic variations in deiodinase enzymes. When that happens, TSH looks fine but free T3 stays low. Weight stalls. These people don't get better on levothyroxine alone and often need liothyronine or compounded T3/T4 combinations, which requires an endocrinologist willing to actually manage that rather than just checking a box.
The Realistic Path to Thyroid Weight Loss Success
Here's what the actual process looks like, stripped of the supplement company marketing: Get a full thyroid panel first. TSH alone is insufficient. You need free T4, free T3, and thyroid antibodies at minimum. If your antibodies are elevated, you have Hashimoto's, which is the most common cause of hypothyroidism in developed countries and adds an inflammatory layer that makes weight loss harder regardless of medication. I usually recommend starting with reverse T3 as well, though not every clinic runs it. High reverse T3 can block thyroid hormone receptors and create a euthyroid sick syndrome pattern where labs look reasonable but the patient feels like garbage and can't lose weight. Once you have results, work with a provider who will actually adjust the dose. The typical starting dose for adults under 60 without heart disease is 1.6 micrograms per kilogram of body weight. A 70-kilogram person starts around 112 micrograms, usually rounded to 100 or 113 depending on what tablets are available. You take it on an empty stomach, ideally 60 minutes before eating, and keep calcium supplements, iron supplements, and proton pump inhibitors at least four hours away from the dose. Those three categories alone account for most of the absorption failures I see in practice.
Get the Full Details

Recheck labs at six to eight weeks after any dose change. Don't recheck at three weeks. Don't recheck at twelve weeks and wonder why nothing changed. The half-life of levothyroxine is about seven days, so steady state takes roughly five to six weeks. Testing too early gives you noise. Testing too late just wastes time. When your labs are in range, weight loss follows the same rules as everyone else's. Caloric deficit, adequate protein, resistance training, sleep, stress management. The thyroid treatment removes one obstacle but doesn't replace the fundamentals. I've seen too many people treat thyroid optimization as the finish line instead of the starting line. One edge case worth mentioning: women over 50 with long-standing hypothyroidism sometimes find their levothyroxine requirement drops significantly after menopause. I had a patient whose dose went from 125 micrograms down to 75 micrograms over eighteen months as her body weight and metabolic demands shifted. If you're gaining weight despite stable-looking labs, the dose might actually be too high now, not too low. It sounds backwards but it happens regularly enough that rechecking everything every six months once stable is standard practice.
What Actually Works and What Doesn't
Desiccated thyroid extract, like Armour Thyroid, contains both T4 and T3 derived from pig thyroid tissue. Some patients do better on it, particularly those with conversion issues. The downside is batch variability and the fixed ratio means you can't adjust T4 and T3 independently. Synthetic T3, liothyronine, can be added to levothyroxine as a separate tablet for more flexibility. That's usually the cleaner approach if you need T3 support. Biotin supplementation interferes with thyroid lab tests, causing falsely low TSH and falsely high T4 and T3 readings. If you're taking biotin for hair or nails, stop it 48 hours before blood work. I've seen more patients misdiagnosed as hyperthyroid because of this than anything else. It's a stupidly simple fix that nobody thinks about until labs don't match symptoms. Selenium supplementation, 200 micrograms daily, has some evidence for reducing thyroid antibodies in Hashimoto's. It won't make you lose weight directly but lowering inflammation may improve how your body responds to thyroid hormone over time. Zinc and iron status also matter for T4 to T3 conversion, so checking those is reasonable if you're stuck despite normalized TSH.
The hard truth is that thyroid-related weight gain is usually modest, maybe five to ten pounds for most people. Anything beyond that suggests additional metabolic, hormonal, or behavioral factors are at play. Treating the thyroid optimally is necessary but rarely sufficient on its own. If someone promises dramatic thyroid weight loss success with supplements or protocols outside standard medical care, they're selling something. Not necessarily a lie, but certainly an oversimplification. Track your weight weekly, not daily. Track your symptoms alongside the numbers. And keep seeing an endocrinologist or a primary care provider who will actually read the full panel instead of justing TSH and calling it good. That last part matters more than most people realize.