Understanding the Space-Making Principle in Dental Surgery
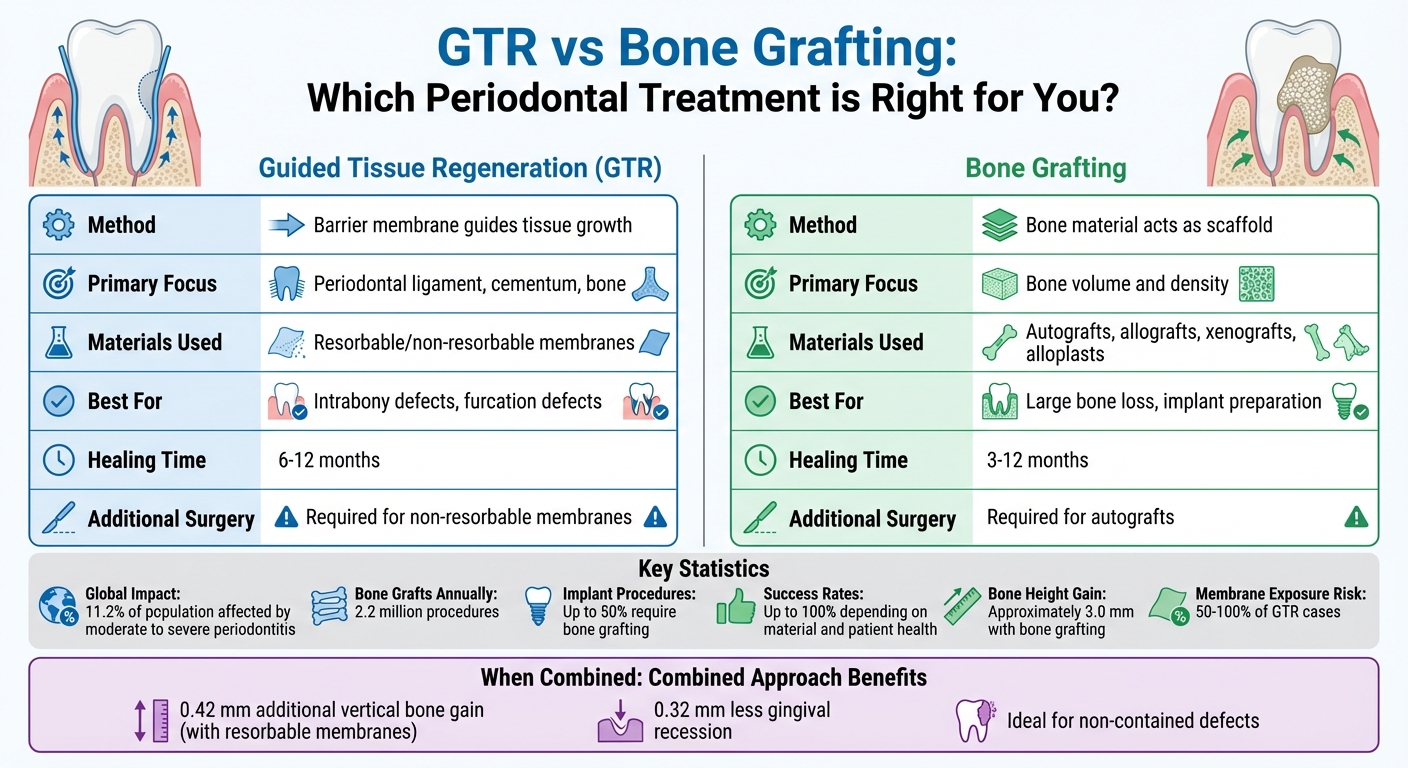
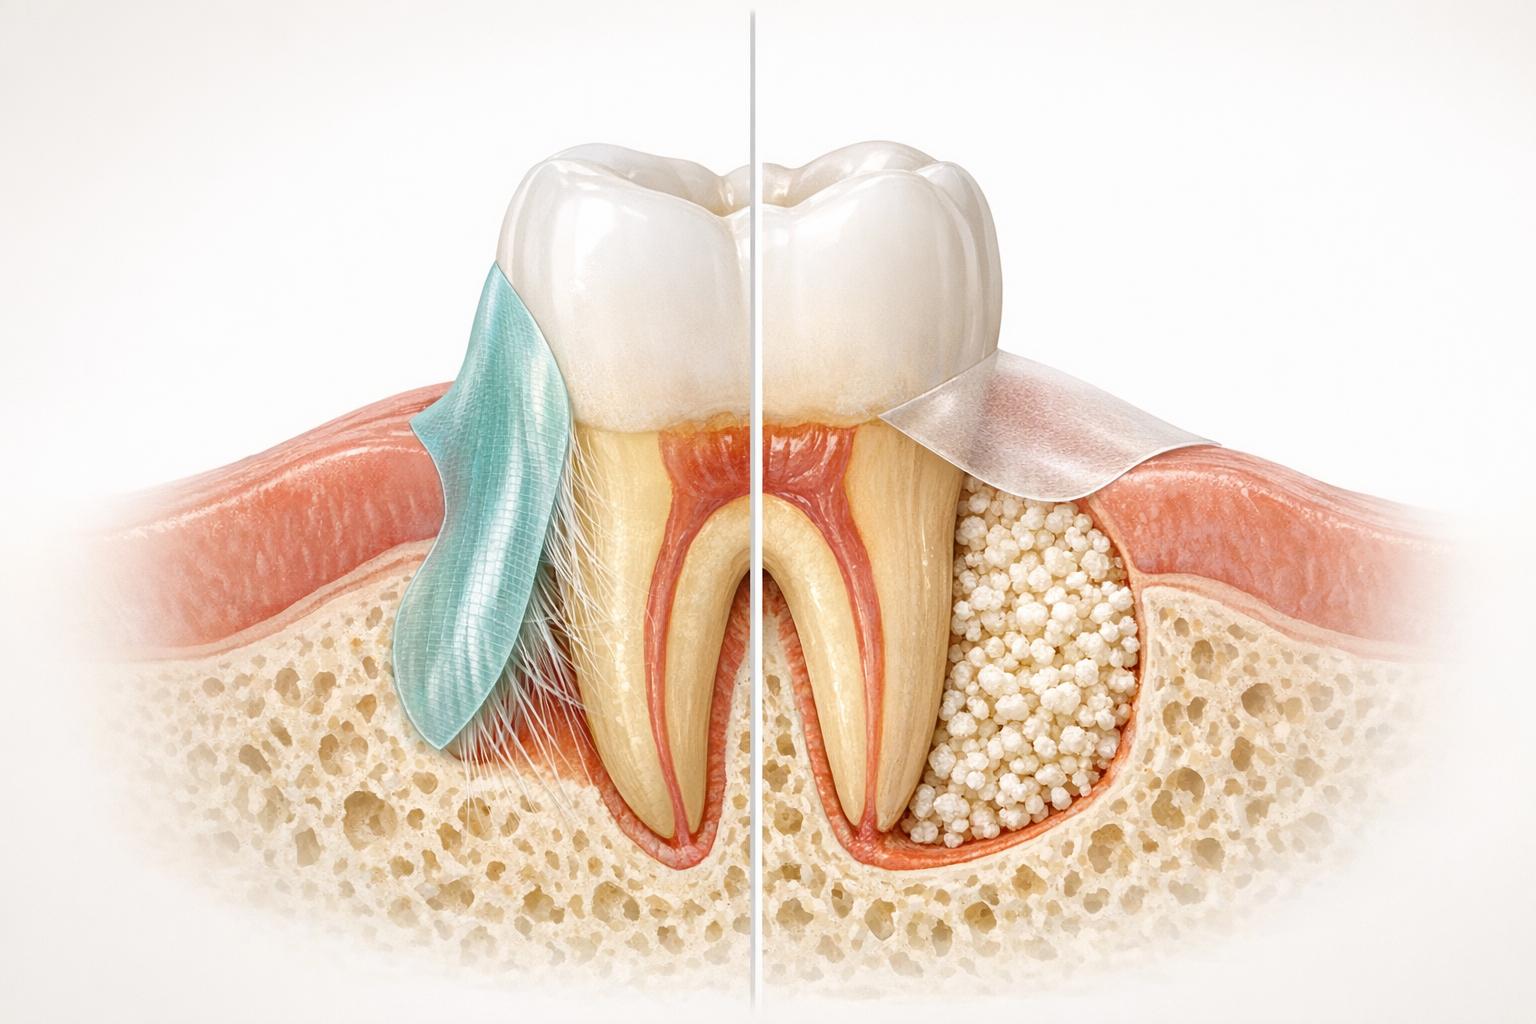
Bone grafts and guided tissue regeneration are two tools in a periodontist's kit. They solve related but distinct problems. A bone graft is filler. It occupies space so your body has something to build on. GTR is a physical barrier. It keeps gum tissue away from a defect so bone and ligament have a chance to grow into the space instead of being crowded out by faster-healing soft tissue. In my experience working through complex site development cases, these two are rarely competitors. They are complementary. But there are moments when choosing one over the other matters a great deal. Let me walk through how I think about this and where the real friction shows up.
Tissue Regeneration Vs Bone Graft: When to Pick Which
I get asked this constantly on forums. The honest answer is that the choice depends on defect anatomy, not on preference or cost alone. Here is the breakdown that actually works in practice. A bone graft is a scaffold. It provides a three-dimensional structure that holds space and gives osteoprogenitor cells somewhere to migrate into. The graft material itself can be autogenous, allograft, xenograft, or alloplastic. Each has different resorption rates and handling characteristics. I typically use a mix. In a fresh extraction socket I might pack the apex with particulate allograft and cap the crest with a block autograft. The block provides immediate structural integrity while the particulates integrate over months. Pure particulate grafts in an extraction socket will compact and settle. You need to overfill slightly to account for consolidation during the first six to eight weeks. I usually add about twenty percent volume to compensate.
Common pitfall: placing a collagen membrane directly over a graft without adequate soft tissue coverage. If the flap is under tension or the graft particles are fine and loose, the membrane can become exposed within days. I've had to debride exposed xenograft and restart healing several times because I underestimated how thin the buccal plate was. Now I check the flap mobility with a bone scalpel before I even cut the incision. If the mucosa won't lie flat without pulling, I'm not attempting primary closure. I either do a pedicle flap or I stage the procedure and let the site mature before re-entering.
Get the Full Details
What Guided Tissue Regeneration Actually Does
GTR works on the principle of selective cell repopulation. Periodontal ligament cells migrate slower than gingival epithelial cells and faster than bone-forming cells. When you place a barrier membrane over a defect, the membrane physically blocks the fast-growing epithelium and gingival connective tissue from migrating into the space. The slower cells get a window to repopulate the defect. This is not about regenerating a perfect periodontium every time. The classic work by Nyman, Karring, and Sun showed that GTR could produce new attachment in intrabony defects, but the clinical reality is messier. You will frequently get a long junctional epithelium rather than true new cementum with inserting collagen fibers. That still counts as a successful outcome by most standards because it stabilizes the tooth. But do not expect a histological replica of a healthy root surface in every case.
The Overlap Zone: Where Both Techniques Meet
This is where most of my actual clinical time is spent. Most of the defects I see in practice are combined. A patient has an intrabony component and a horizontal loss. A ridge augmentation after extraction needs both space maintenance and soft tissue management. In these situations, I use bone graft to rebuild the volume and a membrane to protect it. The membrane is the difference between a grafted site that collapses and one that stays open long enough for osteogenesis to occur. I prefer resorbable membranes for most cases. Collagens like Bio-Gide or cross-linked collagen variants work well and eliminate a second surgery for removal. The downside is that cross-linked membranes stay intact longer, which is good for stability but can delay remodeling if the defect is shallow. For a shallow defect with minimal bulk needed, a non-cross-linked collagen is sufficient and resorbs predictably in four to six weeks. For a deep angular defect, I use a denser membrane that maintains barrier function for eight to ten weeks.
A Problem I Ran Into That Changed My Approach
Years ago I had a case where I placed a small particulate allograft in a Class II furcation of a mandibular molar and covered it with a collagen membrane. The flap closed primarily, everything looked good at two weeks, and then at four weeks I noticed a subtle swelling over the furcation area. When I aspirated, it was serous fluid. The membrane had been the wrong size. It was too small to achieve the required overhang of two millimeters beyond the defect margins. The gingival connective tissue was seeping underneath through the periphery and the graft was becoming encapsulated by fibrous tissue rather than integrating. I removed the membrane and graft material, cleaned the furcation entrance thoroughly, and redone it with a larger membrane that extended three millimeters beyond every margin of the defect. This time I used a titanium-reinforced membrane to prevent collapse. The second attempt healed cleanly. The lesson was not that GTR doesn't work for furcations. It does, when done correctly. The lesson was that membrane sizing is more critical than graft selection. I now measure the defect with a periodontal probe before I ever open the box of membranes. I pick the membrane based on the defect dimensions, not the other way around.

When Bone Graft Alone Is the Right Call
Not every situation needs a membrane. Ridge preservation after extraction, particularly in the aesthetic zone, often requires only graft material and a collagen plug or suture-driven membrane that is so fine it functions more as a barrier seal than a true GTR device. If the buccal plate is intact and the extraction socket is complete, you do not need a substantial barrier. The intact bone walls themselves act as the barrier. Adding a large membrane in these cases can create unnecessary bulk and complicate flap management without adding benefit. I also skip membranes in cases where the soft tissue envelope is thick and biotype-dense. A thick gingival phenotype naturally resists epithelial migration into underlying defects. The biology does some of the work for you. I have found that in these cases, graft alone produces comparable results to graft plus membrane, with fewer variables to manage.
When GTR Alone Makes Sense
There are defects where adding graft material is not the priority. A shallow intrabony defect with good bony walls and a thin buccal plate might respond adequately to membrane placement alone. The body's own progenitor cells in the defect walls are sufficient if you simply prevent the soft tissue from taking over the space. Adding a large volume of graft material in a shallow defect can actually hinder resolution by creating a gap between the graft and the defect walls that becomes a niche for bacterial colonization. I see this most often in retreatment cases after endodontic surgery. A small periapical osseous defect that persists after apicoectomy sometimes resolves with GTR alone. I place a collagen membrane, secure it with a few horizontal mattress sutures, and let it heal for six months. No graft, no complication, no second procedure. The defect fills with bone from the surrounding vital tissues.
What Beginners Miss About Timing
The biggest mistake I see in forum discussions is people treating these as interchangeable options. They are not. The indication drives the technique, not the other way around. Before you decide between tissue regeneration and bone graft, you need to answer three questions: What is the defect morphology, what is the soft tissue thickness, and what is the timeline you are working with. If you are short on time, autogenous block grafting moves the clock faster than any graft substitute. It is vascularized bone. It integrates directly. But it requires a donor site and adds surgical complexity. If you are not comfortable with harvest sites, stick to particulate allograft and accept the longer integration period. I have seen clinicians attempt block grafts who should have stuck to particulate. The outcomes were worse because the block was poorly adapted and the soft tissue dehisced. A well-packed particulate graft with a collagen membrane beats a poorly placed block every time.

Practical Notes on Membrane Selection
Cross-linked collagen membranes like Geistlich's Collagen Matrix resist resorption longer than standard collagen. This is valuable in defects that need prolonged barrier function. But in areas where the soft tissue is thin and blood supply is tenuous, a slow-resorbing membrane can become a nidus for biofilm accumulation if any dehiscence occurs. I reserve cross-linked collagen for defects with robust soft tissue coverage and use standard collagen for compromised sites where early resorption reduces infection risk. Titanium meshes are another option for large volume augmentation. They provide rigid space maintenance but require a second surgery for removal and carry a higher dehiscence rate. I use them selectively when the defect is so large that resorbable barriers cannot maintain the space. For routine ridge augmentation in the posterior maxilla, a particulate graft with a resorbable membrane handles most cases without needing titanium.
The Bottom Line Without Being Preachy
Bone graft and guided tissue regeneration are not opponents. They are instruments. The question is never which one is better. The question is which combination addresses the specific defect in front of you. Most of my cases use both. Some use one or the other. A few use neither and heal with simple closure. Knowing which category your case falls into takes more time than reading about it here. Clinical judgment built from watching what fails is what actually guides the decision.