Cellular Transportation In Biology: How Things Actually Move Across Membranes
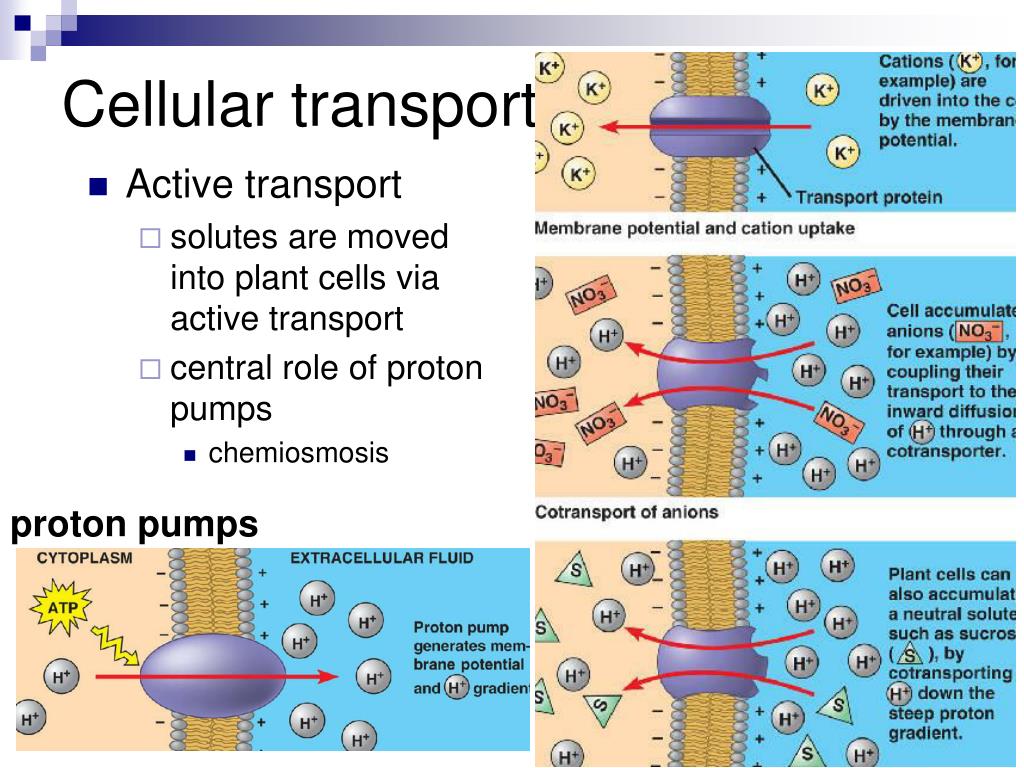
Most introductory biology classes present membrane transport as a neat checklist: passive goes with the gradient, active goes against it, vesicular is for big stuff. That's technically true and completely insufficient if you actually need to predict what happens when you add an inhibitor to a real system. Transportation In Biology is better understood as a set of competing forces. Every molecule crossing a membrane is subject to concentration gradients, electrical potentials, solvent drag, and the kinetic properties of whatever protein happens to be nearby. The textbook version leaves out the electrical component entirely for glucose transport, which is fine until you're working with neurons or epithelial cells where the membrane potential fundamentally changes everything.Facilitated diffusion through channel proteins operates differently than carrier-mediated transport even though both are passive. Aquaporins, voltage-gated channels, and ligand-gated receptors all follow simple diffusion kinetics at low substrate concentrations but saturate just like enzymes do. The Michaelis-Menten equation applies here. You'll see this in patch-clamp experiments where the current plateaus as ion concentration increases because the channel is fully occupied or maximally open. Beginners often conflate facilitated diffusion with simple diffusion because both don't require ATP. They're mechanistically distinct and behave differently under experimental conditions. Active transport has two subcategories that students routinely blur together. Primary active transport directly hydrolyzes ATP to move ions against their gradient. The sodium-potassium pump is the classic example, exchanging three sodium ions out for two potassium ions in per ATP molecule consumed. Secondary active transport couples the movement of one solute down its electrochemical gradient to another solute moving uphill. SGLT1 in the intestinal epithelium uses the sodium gradient established by Na+/K+ ATPase to pull glucose into the cell against its concentration gradient. This is how oral rehydration therapy works. The sodium and glucose cotransport mechanism is conserved across the small intestine and kidney proximal tubule.
I spent a week trying to figure out why glucose uptake in cultured enterocytes wasn't responding to phloridzin inhibition the way the literature predicted. Phloridzin blocks SGLT1 and SGLT2, so if your model depends on sodium-glucose cotransport, adding it should shut uptake down nearly completely. It didn't. The cells were still pulling in glucose at about forty percent of baseline. What actually happened is the culture medium had been prepared with a standard bicarbonate-buffered composition, and under those conditions the cells upregulated GLUT2 expression on the basolateral membrane as a compensatory mechanism. The facultative glucose transporter kicked in because the primary active route was blocked. The fix was switching to a HEPES-buffered medium and confirming GLUT2 expression with a western blot before running the assay again. I lost three days to this. You won't if you check transporter expression under your specific conditions before assuming the textbook mechanism is the only one operating.Endocytosis and exocytosis handle bulk transport for molecules too large or too polar to pass through any membrane protein. Receptor-mediated endocytosis is the most regulated form. LDL particles bind to LDL receptors on the cell surface, the complex clusters in clathrin-coated pits, and the membrane invaginates to form a vesicle. The clathrin triskelia disassemble once the vesicle pinches off, and the receptor-ligand complex gets routed to an endosome where the acidic pH causes LDL to dissociate from its receptor. The receptor recycles back to the membrane while the LDL goes to the lysosome for degradation. Defects in this pathway cause familial hypercholesterolemia because the liver can't clear LDL from the blood efficiently. Molecular trafficking through the secretory pathway follows a predictable route but has multiple checkpoints where things can go wrong. Proteins destined for secretion or the plasma membrane enter the rough ER, get glycosylated and folded, then move through the Golgi apparatus where further modification occurs. From the trans-Golgi network they're sorted into vesicles for either constitutive secretion or regulated secretion. The secretory signal peptide at the N-terminus directs the ribosome to the ER membrane via the signal recognition particle. If that signal peptide is mutated or cleaved prematurely, the protein stays in the cytoplasm and gets degraded by the proteasome. This is one reason why misfolded protein diseases exist and why quality control in the ER matters more than most people realize. There's a common misconception that osmosis is a type of diffusion. It's not. Osmosis is the net movement of water across a semipermeable membrane driven by a difference in solute concentration on the two sides. Water moves from the hypotonic side to the hypertonic side. The driving force is the chemical potential gradient of water itself, not the solutes. Solutes don't pull water. The math works out to the van 't Hoff equation for osmotic pressure, but conceptually it's important to keep straight that water is the molecule doing the moving, not the solutes.
Much of the complexity in real biological systems comes from transporters that don't fit the categories textbooks give them. The ABC transporter superfamily includes over forty human genes, many of which pump xenobiotics out of cells using ATP hydrolysis. P-glycoprotein (MDR1) is one of them and it's responsible for multidrug resistance in cancer cells. Chemotherapy drugs get pumped out faster than they can accumulate to toxic levels. This is a clinical reality, not a theoretical concern. Similarly, some ion channels are gated by mechanical force rather than voltage or ligands. Piezo1 and Piezo2 respond to membrane tension and are found in endothelial cells, proprioceptive neurons, and red blood cells. Their discovery in 2010 changed how we think about mechanotransduction, and there's still ongoing debate about their exact gating mechanism. Transport rates are rarely constant in living tissue. Local pH shifts, membrane potential changes, and post-translational modifications like phosphorylation can modulate transporter activity within minutes. The insulin signaling cascade rapidly translocates GLUT4 vesicles from intracellular stores to the plasma membrane in muscle and adipose tissue. Without insulin, those transporters sit in endosomes. With insulin, they insert into the membrane and glucose uptake increases dramatically. This is why type 1 diabetes causes hyperglycemia at the cellular level even though glucose is abundant in the blood. The transport machinery is there but it's locked away. If you're designing an experiment around membrane transport, the thing that will go wrong most often is assuming the transport mechanism based on textbook models rather than measuring it directly. Use inhibitor panels with known specificity. Measure transport at multiple substrate concentrations to check for saturation kinetics. Test whether the process is energy-dependent by running it under metabolic inhibition. Check if it's sodium-dependent by substituting choline for sodium in your buffer. These are basic controls but they catch more mistakes than people expect. The literature is full of papers that claim a novel transporter without ruling out the possibility that the observed uptake is actually through an endogenous pathway that was already there.
Get the Full Details