How to Actually Use the Stages of Change in Practice
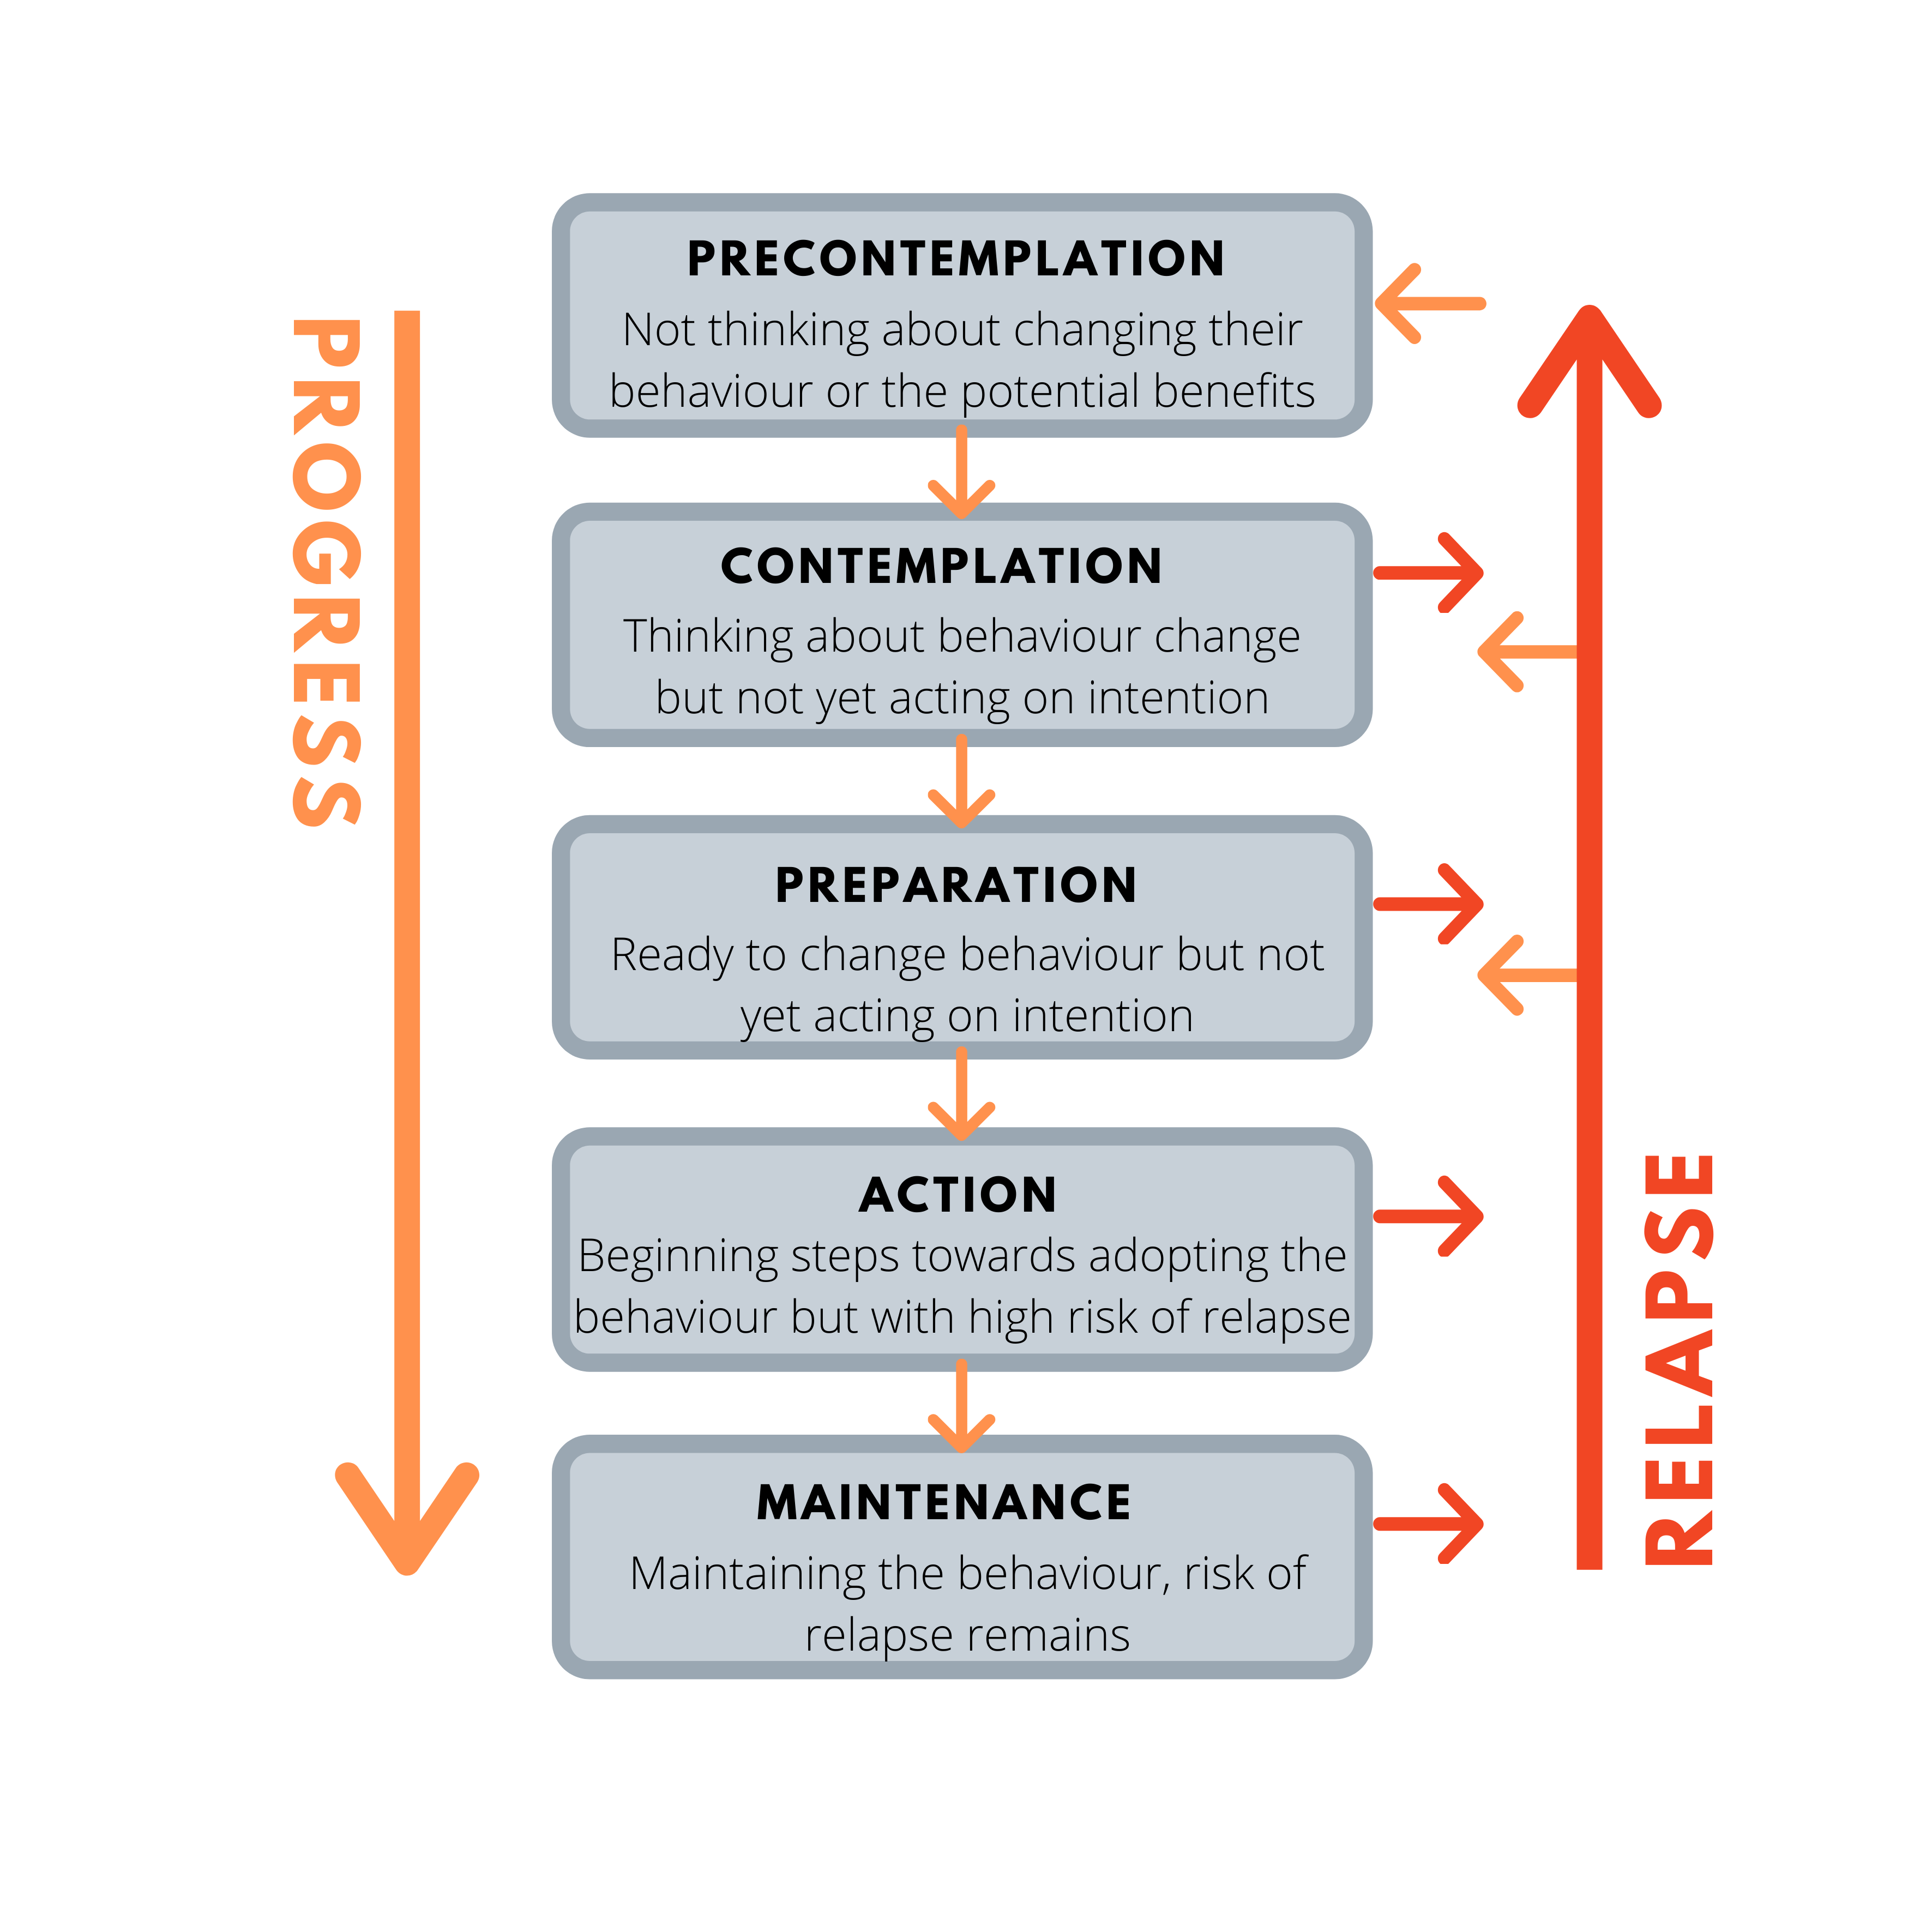
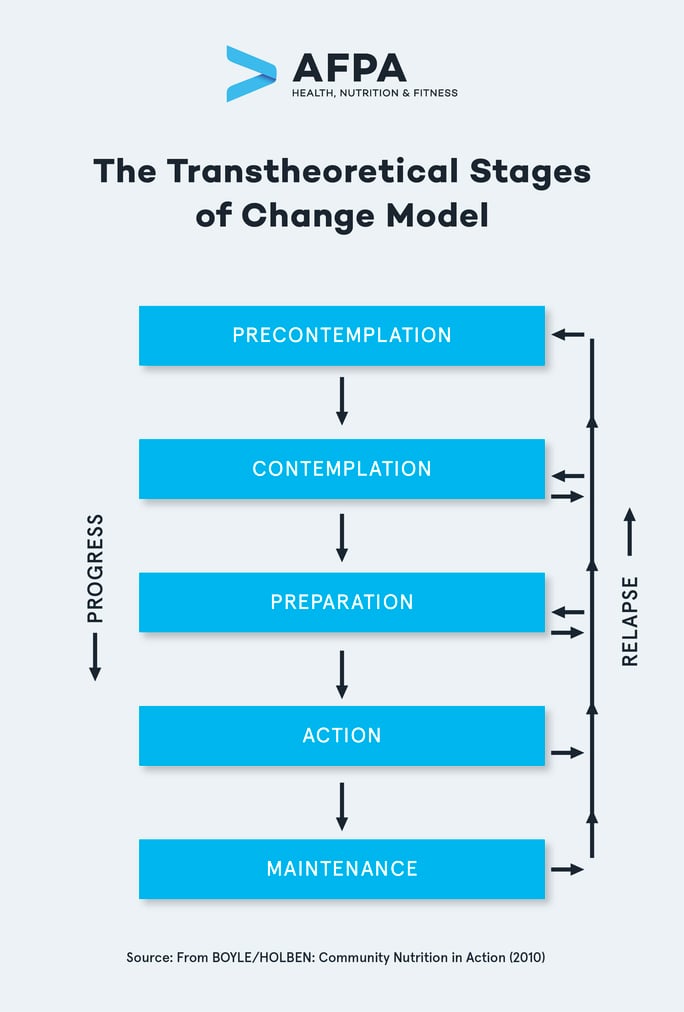
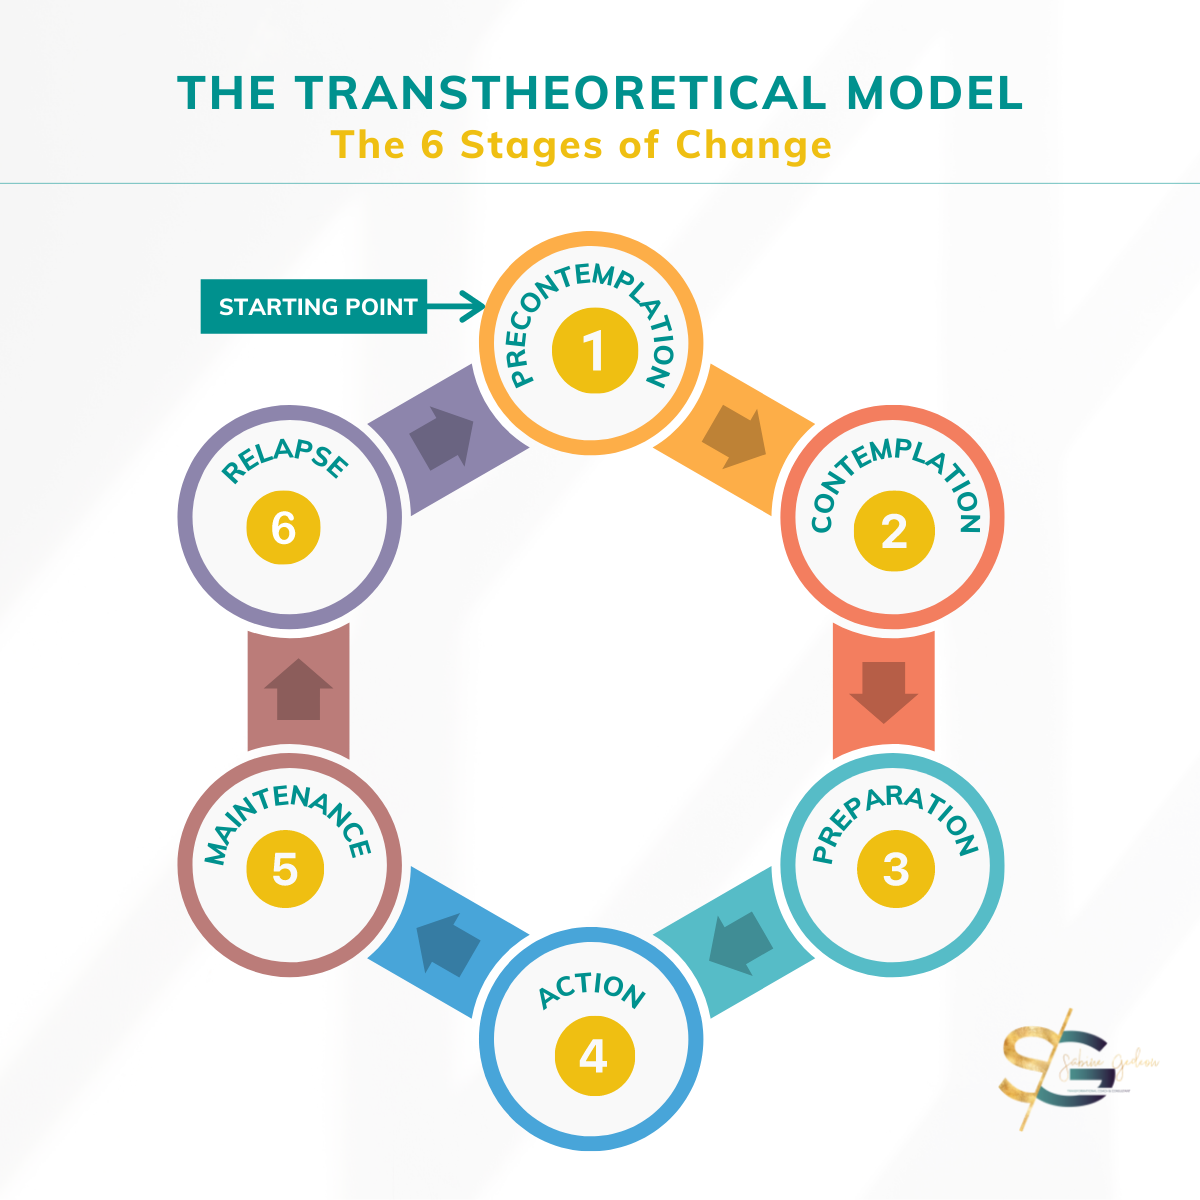
The Transtheoretical Model Of Behavior Change was developed by Prochaska and DiClemente in the late 1970s when they were trying to figure out why people who read self-help books and attended seminars still weren't sticking with any of it. The core insight is that behavior change isn't a single decision you make. It's a sequence of stages, and most people jump between them repeatedly before anything actually sticks. The five stages are precontemplation, contemplation, preparation, action, and maintenance. Precontemplation means the person has no intention of changing in the next six months. Contemplation means they're thinking about it but haven't committed. Preparation is when they've made a small step forward. Action is active modification of behavior. Maintenance is sustaining that change over time. Here's what the model gets right that most people miss: the stages aren't linear. People cycle through them constantly. I've seen clients in maintenance for three years of sobriety who then hit a stress trigger and drop back to contemplation overnight. That's not failure. That's how the model works. The original papers from the 1980s actually acknowledged this cycling pattern, but every pop-psychology summary of the TTM glosses right over it.
The real diagnostic tool inside the model is called the Decisional Balance. It's just a concept that describes weighing the pros and cons of changing versus staying the same. In precontemplation, the cons of changing usually outweigh the pros. By the time someone reaches action, that balance has shifted. What I found useful was tracking it quantitatively. I started having clients rate their perceived pros and cons on a 1-10 scale for each relevant behavior. The numbers gave me a concrete way to see where someone actually sat, not where they said they sat. There's also a second construct most people don't know about: the Processes of Change. These are the cognitive and behavioral activities people use to move through the stages. There are ten of them, split into experiential and behavioral categories. The experiential ones include things like conscious encouragement, environmental reevaluation, and self-liberation. The behavioral ones include stimulus control, helping relationships, and reinforcement management. Early-stage clients benefit most from the experiential processes. Later-stage clients need the behavioral ones. Mixing those up is a common mistake that wastes intervention time.
Applying the Transttheoretical Model Of Behavior Change to Real Work
I ran a program for a healthcare network where we applied the TTM to smoking cessation across about 400 patients. The standard approach was to screen everyone and then hand them a pamphlet. We changed that to staging every patient into their current stage and matching the intervention to that stage. Precontemplation patients got feedback about their health data without any push to quit. Contemplation patients got decisional balance exercises. Action and maintenance patients got coping strategy coaching. The results were measurable. The stage-matched group had a 23% six-month abstinence rate compared to about 14% in the pamphlet-only group. That's not groundbreaking, but it's significant for a population where most interventions produce single-digit improvements. The key was the staging. Most programs skip that step entirely and assume everyone is in contemplation when they walk in the door. Here's an edge case I ran into that the standard TTM literature doesn't address well. Chronic conditions like diabetes or hypertension create ongoing behavior demands that reset people to earlier stages repeatedly. A Type 2 diabetic might be in maintenance for medication adherence for eight months, then experience a stressful life event and regress to contemplation about whether they should even bother taking the pills. The TTM was built around one-off behaviors like quitting smoking, not chronic disease self-management where the target behavior is perpetual and relapse is structurally inevitable.
Get the Full Details

The workaround I used was to treat the regression not as a failure but as a signal. When a diabetic dropped back to contemplation after a life stressor, I didn't try to push them straight back to action. We spent two or three sessions re-establishing the pros and cons, then set a micro-goal that was impossible to fail. Sometimes that meant just taking the pill at the same time as an existing routine. Small anchors. It cut the time from regression to re-engagement from about six weeks down to roughly two. There are real limitations to the model. The staging instruments are self-report, which means people in precontemplation often self-diagnose as contemplation because that's the more socially acceptable answer. You'll get inaccurate stage assignments if you rely solely on the questionnaire without clinical observation. The model also doesn't account well for structural barriers. Someone who can't afford fresh food or doesn't have safe places to exercise is going to struggle regardless of which stage they're in. The TTM treats behavior change as primarily an intrapersonal process, which leaves little room for environmental and economic factors. Another practical issue is the time it takes to do proper staging. A validated stage assessment for any given behavior takes about 15 minutes. If you're working with a caseload where you need to address multiple behaviors per client, that adds up fast. I found that using a brief four-question screen to approximate stage placement, then confirming with the full instrument only when the screen was ambiguous, brought the average assessment time down to about four minutes per behavior without a meaningful drop in accuracy.
The model also has a cultural blind spot. The individualistic framing assumes personal agency is the primary driver of change, which works fine in contexts where people have control over their environment. It breaks down in collectivist cultures or in situations where family or community norms are the dominant behavioral constraint. I worked with a client from a background where extended family expectations around eating practices were the real barrier, not her own motivation. Pushing her through the standard TTM stages was useless until we addressed the family dynamics directly. If you're looking to implement this, start by picking one behavior and staging your entire population into it before doing anything else. Don't try to apply all five stages across a dozen behaviors at once. Pick the behavior that matters most to your outcomes, validate your stage assessment tool against actual behavior change rates in your context, and track stage transitions over time rather than just stage placement at intake. The transition data tells you more about your intervention effectiveness than any single stage score ever will. The Research on TTM continues to accumulate. A 2018 meta-analysis in Health Psychology Review found moderate effect sizes across physical activity and dietary behaviors, with slightly smaller effects for substance use. More recent work has focused on integrating the model with implementation science frameworks, which is useful because the TTM tells you what stage someone is in but not how to deliver the intervention at scale. Combining staging with a structured implementation approach tends to produce better real-world results than either framework alone.