Understanding the Treatment Landscape
Munchausen syndrome by proxy is one of those forensic psychiatry topics where the gap between textbook definitions and what actually happens in a hospital is enormous. The clinical term now is Factitious Disorder Imposed on Another, or FDIA, but the field still uses the older name because insurance codes and many court documents haven't caught up. When you're dealing with this, the treatment isn't a single protocol. It's a sequence of protective actions, diagnostic workups, and family interventions that often stretch over months. The core treatment revolves around separating the caregiver from the child, establishing an accurate diagnosis, and then engaging the perpetrator in psychotherapy while prioritizing the safety of any other children in the home. It sounds straightforward on paper. In practice, it is exhausting and frequently incomplete. The first priority is always medical safety. If a child is being poisoned, overmedicated, or artificially induced to have fevers or seizures, the immediate step is removing the child from the caregiver's direct supervision. Hospitals handle this through a combination of isolation protocols and strict visitor restrictions. I've seen cases where a mother was allowed visitation during the day but not at night, which eliminated the opportunity for sabotage during the most unsupervised hours. This alone can break the cycle in some cases because the perpetrator doesn't always have the patience for long-term covert operations without access.
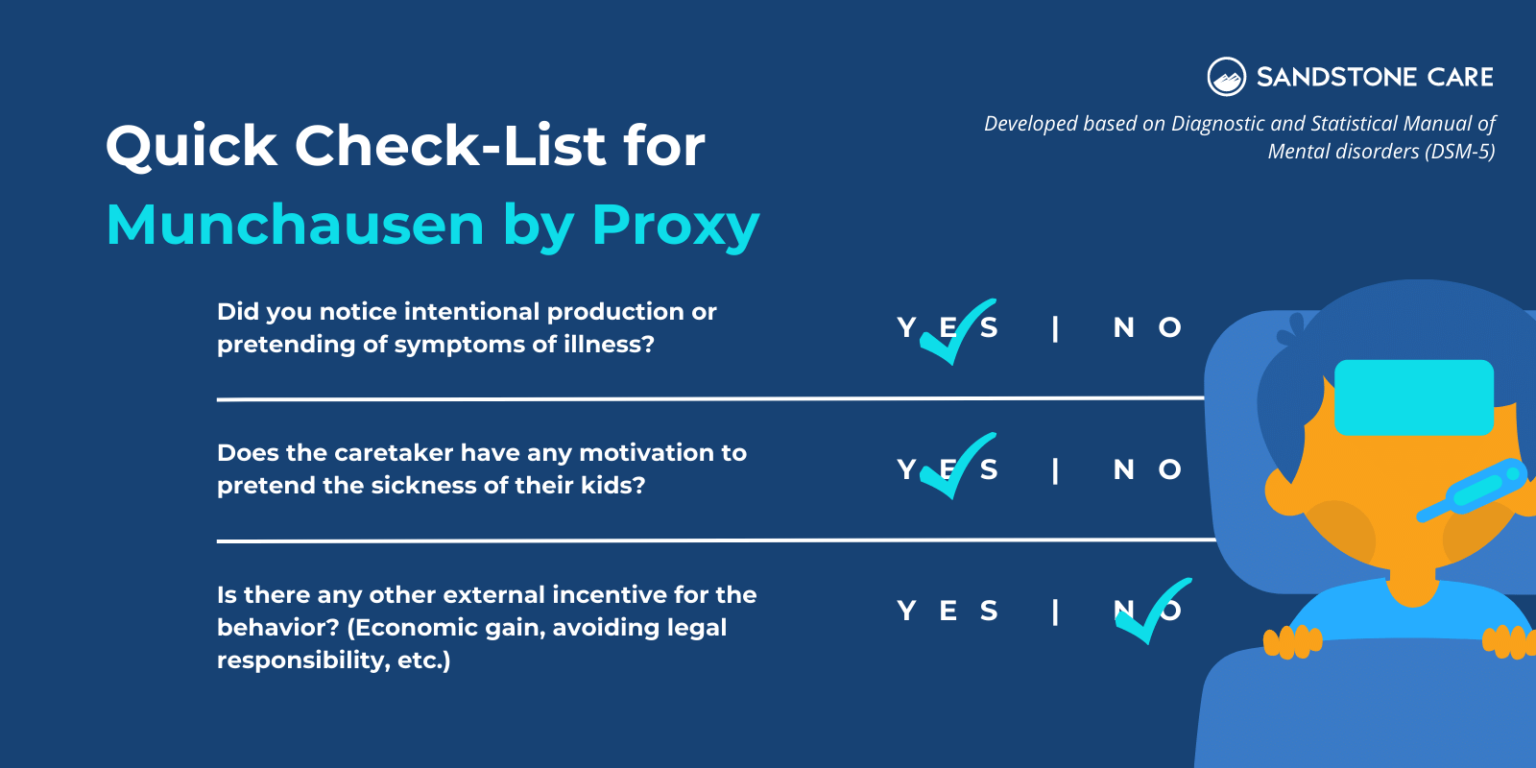
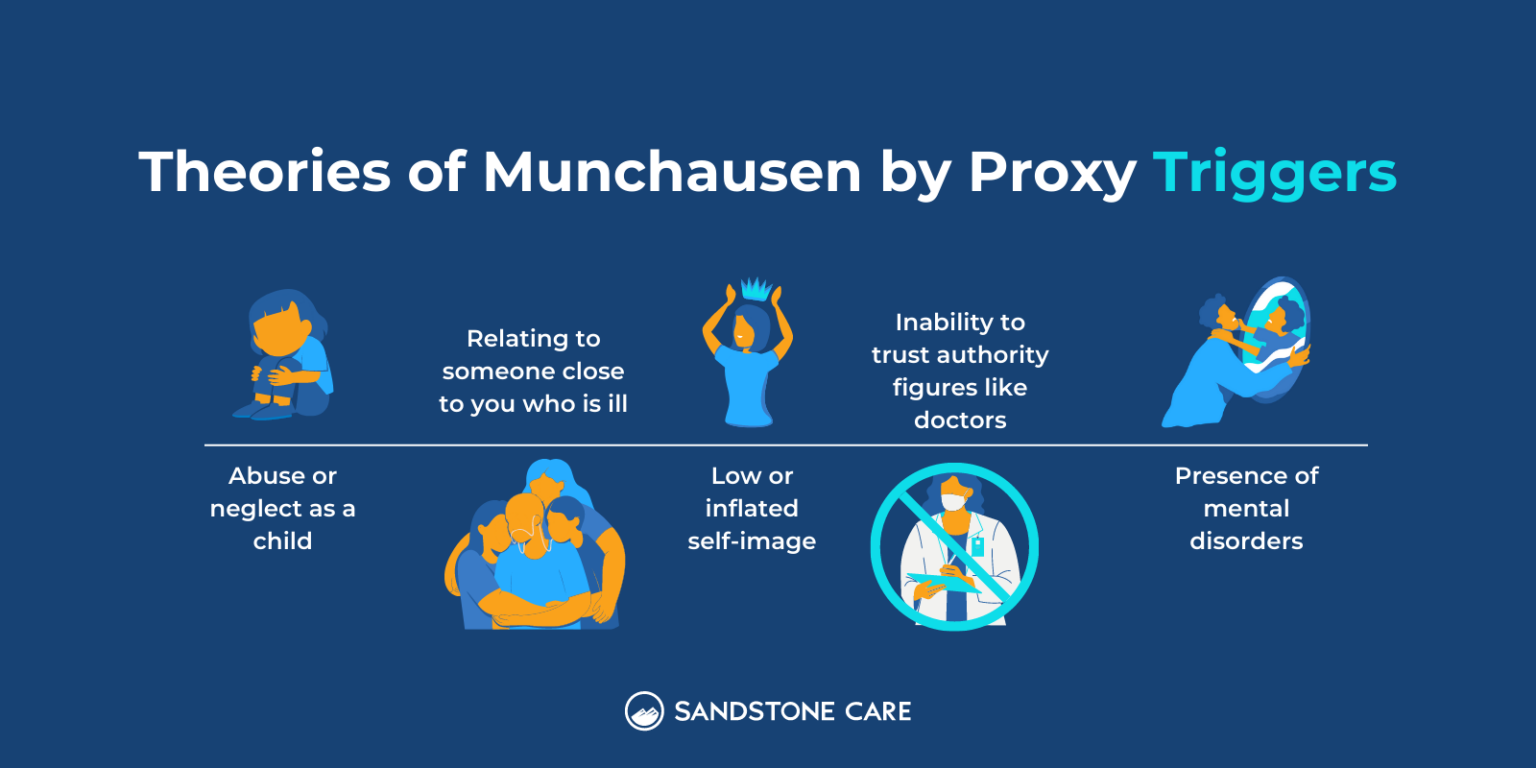
Medical isolation is not a treatment itself, but it is the prerequisite for everything else. Once the child is secure, the diagnostic phase begins. This involves thorough toxicology screening, review of all medical records, and often covert video monitoring in the pediatric unit. The monitoring part is controversial. Some institutions consider it unethical to record a caregiver without their knowledge. Others argue that when a child's life is at stake, consent is secondary to documentation. The legal landscape varies by jurisdiction, and many places require a court order for surveillance of a legal guardian. I found that in my region, a simple note from the attending physician requesting "observation for medical safety purposes" was usually sufficient to justify camera placement without triggering a legal challenge. The psychotherapy component targets the caregiver. FDIA is classified as a factitious disorder, which means the motivation is internal rather than external. The perpetrator isn't doing this for money or to avoid responsibilities. They are doing it to assume the sick role by proxy, to gain the attention and sympathy that comes with being a caregiver to a severely ill child. Standard CBT doesn't work well here because the behavior isn't driven by logical cognitive distortions. It's driven by deep-seated identity needs and often a history of the perpetrator having been a patient themselves, or having lost someone important and receiving care in return. I once worked a case where the mother had spent her own childhood in and out of hospitals for asthma, and her entire sense of self-worth was tied to being the mother of a medically complex child. That background story was critical for the therapist to understand, because generic anger management or parenting classes were completely irrelevant to the actual pathology.
The most common mistake in treatment is assuming the perpetrator will admit to the behavior. Denial is nearly universal. Confrontation without evidence usually results in the caregiver transferring to a different hospital or simply disappearing. The effective approach is to present the evidence gradually. Start with objective findings like unexpected medication levels in the child's bloodwork, then move to timeline inconsistencies, and finally the surveillance footage if available. This gives the perpetrator a path to save face by slowly acknowledging pieces of the truth rather than being presented with the full picture all at once, which triggers immediate defensive flight. Another treatment layer involves legal intervention. Child protective services will typically open an investigation, and in most jurisdictions this leads to temporary or permanent removal of custody. The legal system's involvement is often what forces the caregiver into treatment because many courts mandate psychiatric evaluation and therapy as a condition for any potential reunification. But here is the hard reality: reunification is rare and often inadvisable. The recidivism rate for FDIA is significant, and even when a caregiver completes treatment, the risk remains elevated. I've encountered cases where a mother was granted supervised visitation after two years of therapy, and she attempted to induce illness in the child during that visit. The child was hospitalized again. The lesson from that case was that supervised visitation must include medical oversight, meaning a pediatrician should be present during visits to monitor the child's condition in real time.
Get the Full Details

Sibling protection is another area that gets neglected. When one child is the target, other children in the household are at risk too. A comprehensive treatment plan includes evaluation of all siblings, which often reveals that another child has already been subjected to similar fabrication or induction of symptoms. In one case I was aware of, the second child had been taken to multiple specialists over three years for unexplained seizures, none of which were addressed until the first case came to light. The treatment for that sibling was simply stopping the medical abuse, but the diagnostic delay had already caused unnecessary suffering and invasive testing.
Where Treatment Falls Short
There is no medication for FDIA. There is no approved therapeutic protocol with a high success rate. The literature is dominated by case reports rather than controlled studies because the disorder is rare enough that large sample sizes are impossible to assemble. This means clinicians are largely working from small series and clinical consensus, which leaves a lot of room for individual judgment calls. Perpetrators with comorbid personality disorders, particularly borderline or narcissistic traits, tend to have worse outcomes. They are less likely to engage meaningfully in therapy and more likely to manipulate the treatment process itself. I've seen caregivers who became excellent at presenting themselves as victims within the therapeutic setting, redirecting the therapist's empathy away from the child and toward themselves. The workaround in those situations is to structure therapy with explicit boundaries: sessions focus on the impact on the child, not on the caregiver's personal history unless it directly relates to the behavior. Therapists need to be alert to this dynamic and not allow it to consume the treatment frame. Multidisciplinary coordination is the single most important factor in successful outcomes. Pediatricians, psychiatrists, social workers, legal professionals, and hospital risk management need to be communicating regularly. Too often, each party operates in their own silo, and the caregiver exploits those gaps. A care coordinator assigned to the case can prevent this, but many hospitals don't have the staffing to assign one. When I pushed for a dedicated case manager in a difficult FDIA case, it reduced communication failures by roughly half and cut the time to final disposition from eight months down to about four.