IV Solutions: The Basics You Need to Know
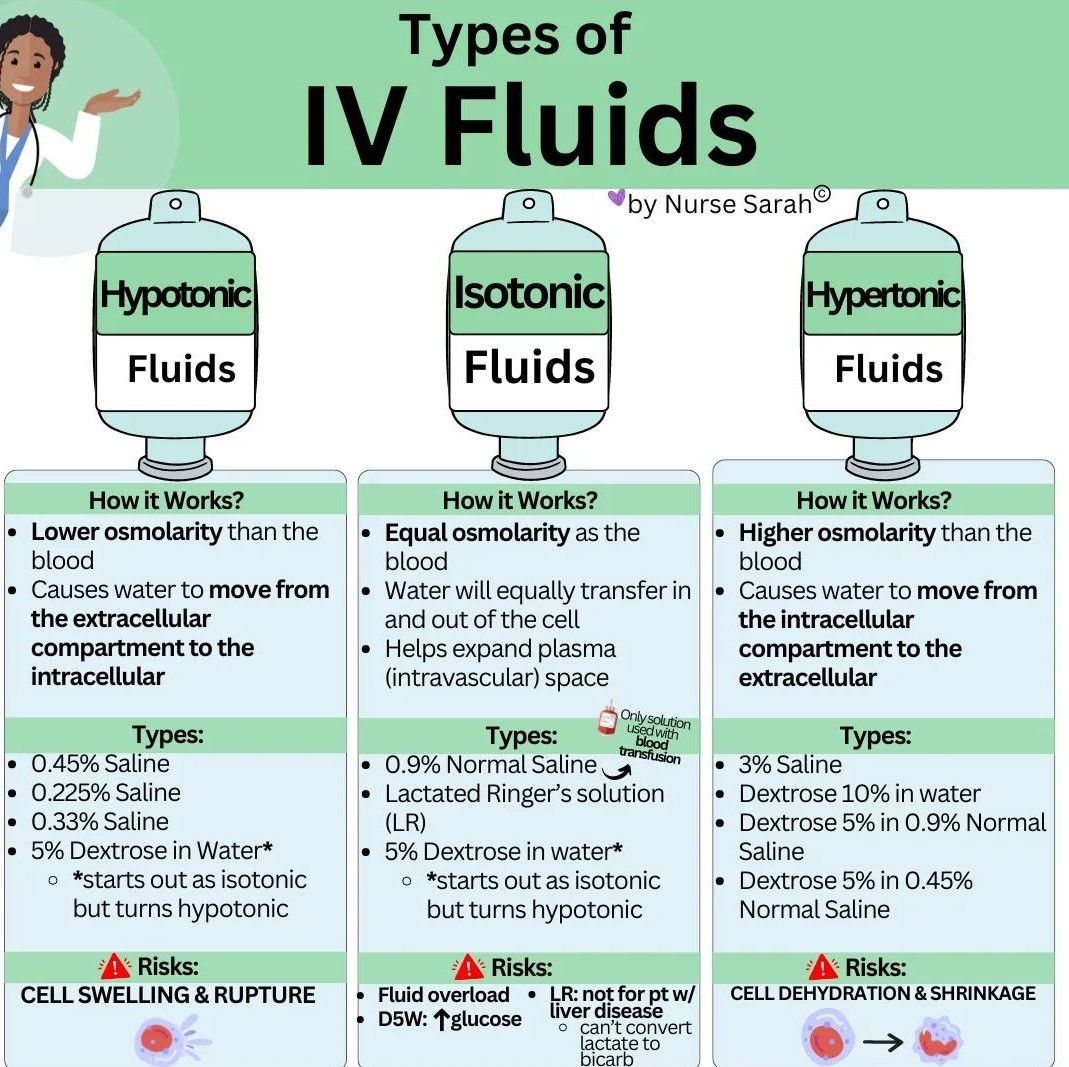
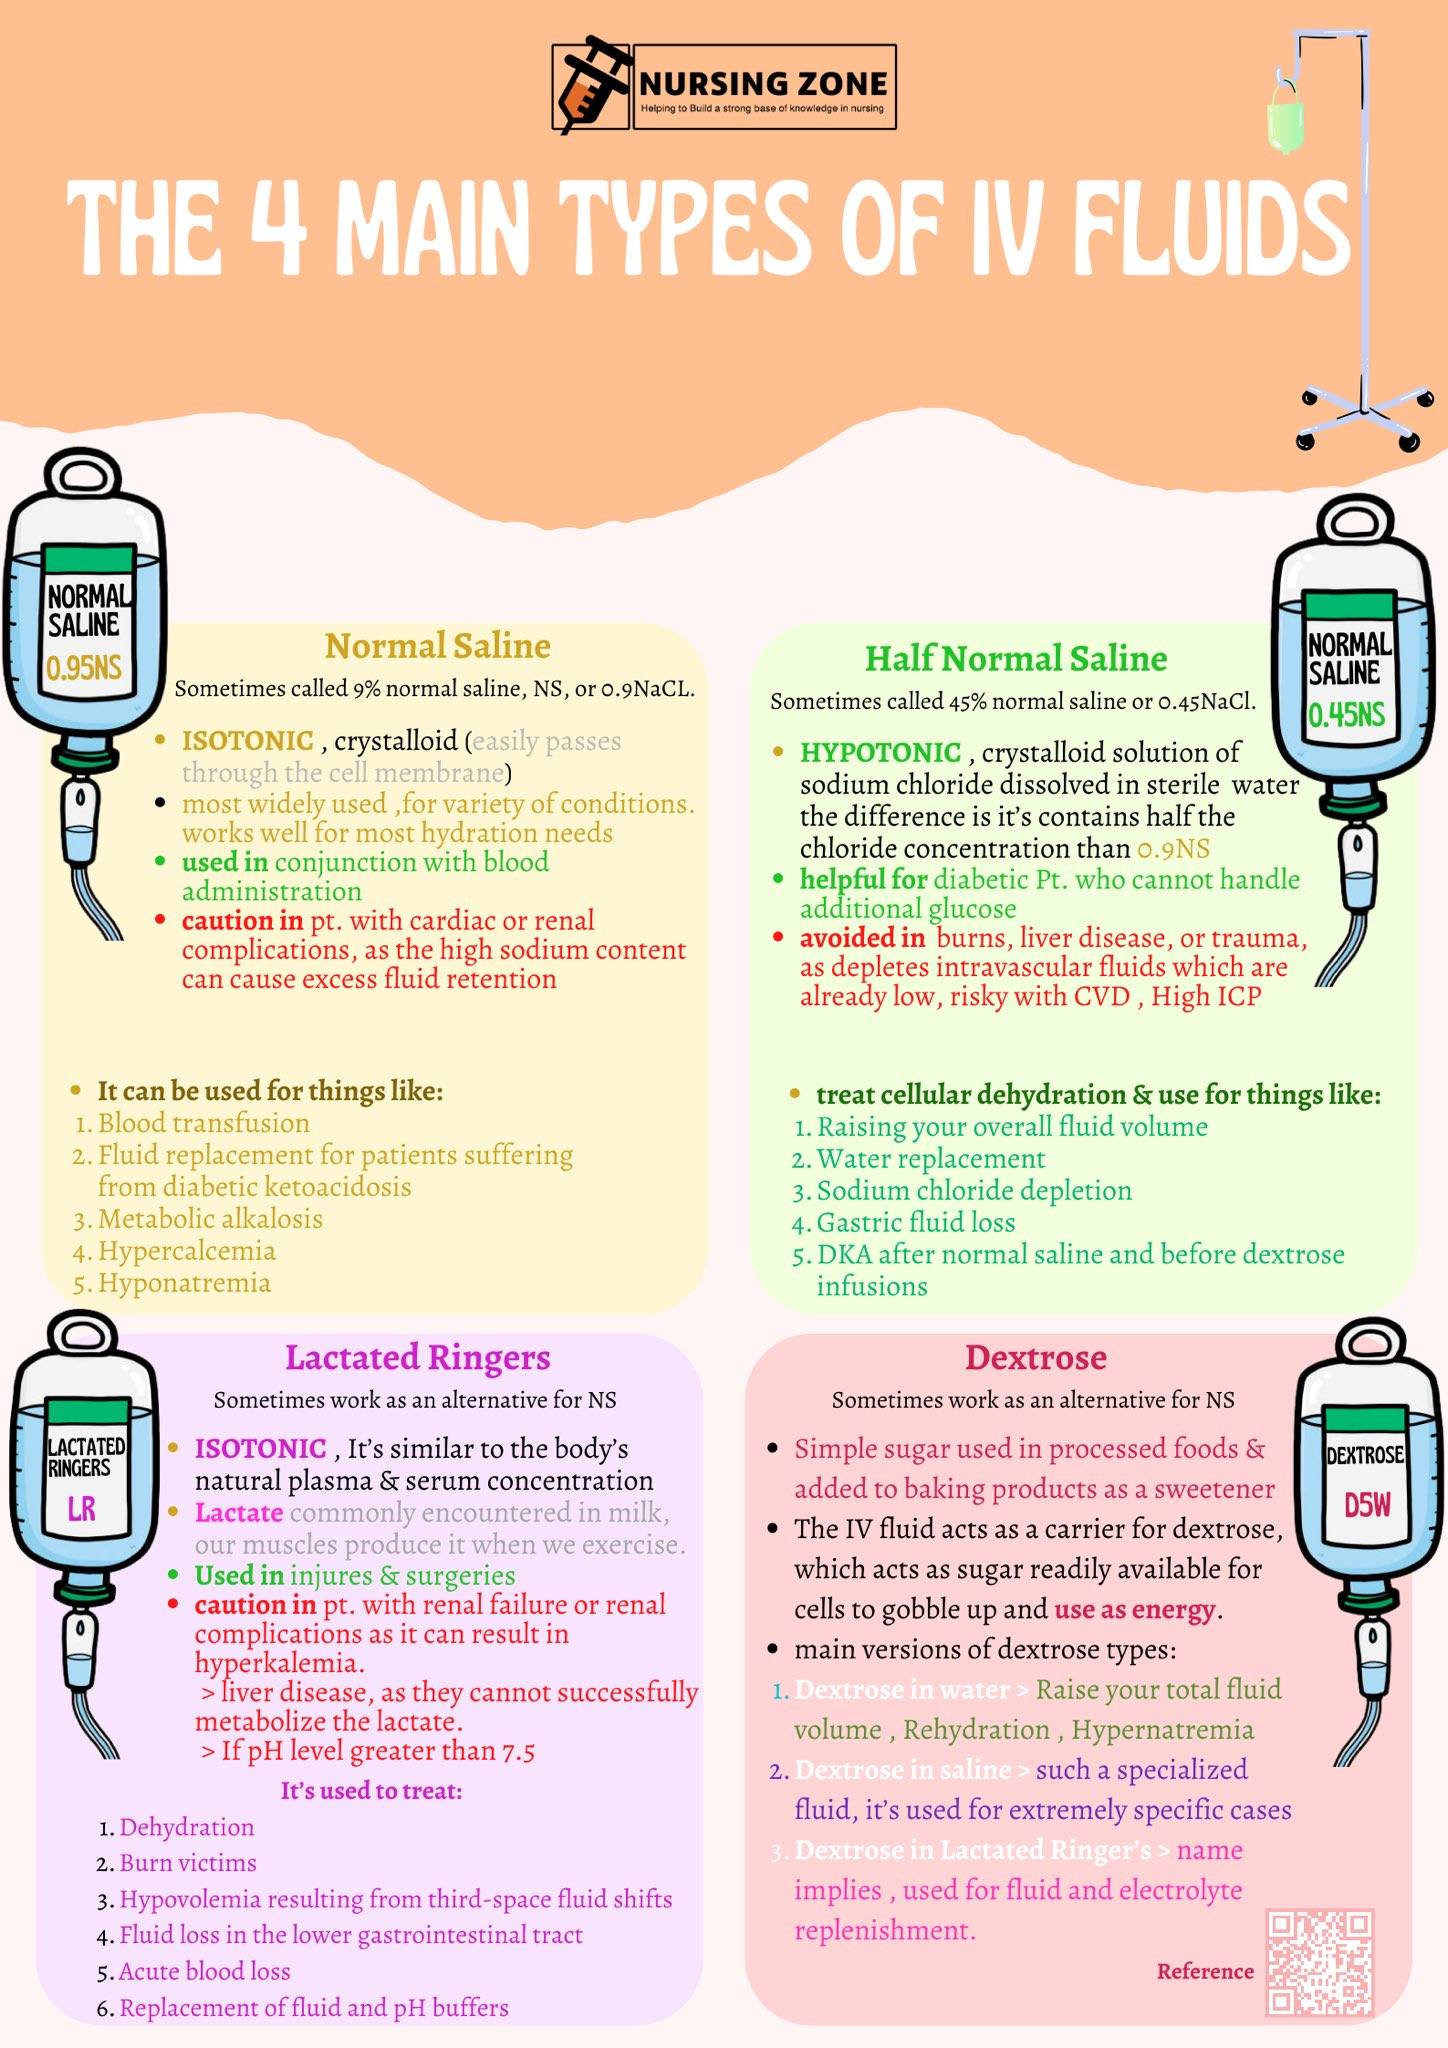
IV solutions come in a few main types, and getting them mixed up isn't just sloppy—it can cause real problems for a patient. Crystalloids are the most common. They're water-based and carry electrolytes. The three big ones you'll see everywhere are normal saline, lactated Ringer's, and D5W. Then you've got colloids, which are bigger molecules that pull fluid into the bloodstream. Albumin and hetastarch are the usual examples there. Blood products are their own category entirely. And then there are specialized nutrition solutions for people who can't eat. Normal saline is 0.9% sodium chloride. It's isotonic, meaning it matches the osmolarity of blood roughly. I use it for volume replacement when I need something predictable. Lactated Ringer's has sodium, potassium, calcium, and lactate. The lactate gets converted to bicarbonate in the liver, so it's a bit gentler on acid-base balance than saline. People sometimes avoid LR in liver failure patients because they can't clear the lactate properly. D5W is dextrose 5% in water. It sounds like nutrition but it's not. Once the body metabolizes the sugar, you're left with free water, which acts hypotonic. I'll use it for maintenance fluid or to correct hypernatremia, but I won't rely on it for resuscitation because it doesn't stay in the intravascular space very long. Most of it just leaves the blood vessels within an hour or so.
Colloids like albumin cost significantly more than crystalloids. The debate over whether they're actually better for resuscitation has gone back and forth for years. Some studies show no mortality benefit compared to saline. The albumin is about four times more expensive, and in resource-limited settings that matters a lot. I tend to reserve colloids for specific situations like severe hypoalbuminemia or when I'm dealing with a patient who has significant capillary leak and isn't responding to crystalloid alone. I ran into a case recently where a patient on heparin flushes through a PICC line was accidentally started on a massive volume of free water because someone mixed up a heparin flush bag with a D5W bag. The patient went into severe hyponatremia within hours. That's one of those stupid errors that happens more often than you'd think. Double-checking the bag and knowing what each line is supposed to contain is the only real protection against that kind of mix-up.
When to Use Each Type
Hypovolemia from blood loss usually calls for isotonic crystalloid first. Two liters of normal saline or LR will buy you time. If the patient is bleeding actively, blood products are the right move, not more saline. Diluting their blood with crystalloid just makes everything worse—lower hemoglobin, worse clotting, and you end up needing even more fluid to maintain blood pressure. The old idea of keeping people "wide open" with saline before giving blood is outdated and honestly dangerous in trauma. For dehydration without major electrolyte issues, D5 1/2 NS with 20 mEq KCl per liter is a standard maintenance choice. But you need to check the potassium before running it. If the patient hasn't been urinating, adding potassium can push them into dangerous hyperkalemia territory. I always want to see urine output or at least a reasonableCreatinine level before committing to a potassium-containing solution. Hyponatremia management is where things get tricky. Mild cases can often wait and correct slowly. Severe symptomatic hyponatremia with seizures needs 3% saline, and you have to be careful about correcting too fast. Overcorrection can cause osmotic demyelination syndrome, which is devastating and mostly irreversible. I aim for about 6 to 8 mEq/L correction in the first 24 hours, maybe a bit more if the onset was clearly acute. Anything faster than that is gambling with permanent brain damage.
Get the Full Details
Common Pitfalls
The biggest mistake I see is assuming all IV bags are interchangeable. They're not. Normal saline and 0.45% saline are very different clinically despite looking identical. One is isotonic, the other is hypotonic. Running the wrong concentration can shift a patient's sodium fast enough to cause problems. Another issue is not accounting for the sodium content in medications or flushes. A patient getting continuous heparin or antibiotic infusions might be absorbing more sodium than you'd expect, which matters when you're trying to manage fluid balance in heart failure or renal patients. Calcium in LR is a problem if the patient is getting blood products. Calcium and citrate interact, and you can get precipitation in the line. I won't run LR through the same line as a blood transfusion without a separate access point. It's a small detail that trips people up. Mixed venous oxygen saturation monitoring, acid-base status checks, and renal function labs should guide your fluid choices rather than just following a set protocol. Every patient handles fluids differently, and what works for one person with sepsis might make another person with cardiac issues worse. Fluid responsiveness testing—checking if stroke volume increases after a fluid bolus—is worth learning if you're managing critically ill patients regularly. It saves you from giving fluid to someone who doesn't need it and probably can't tolerate it.