How Drains Actually Work In The Body
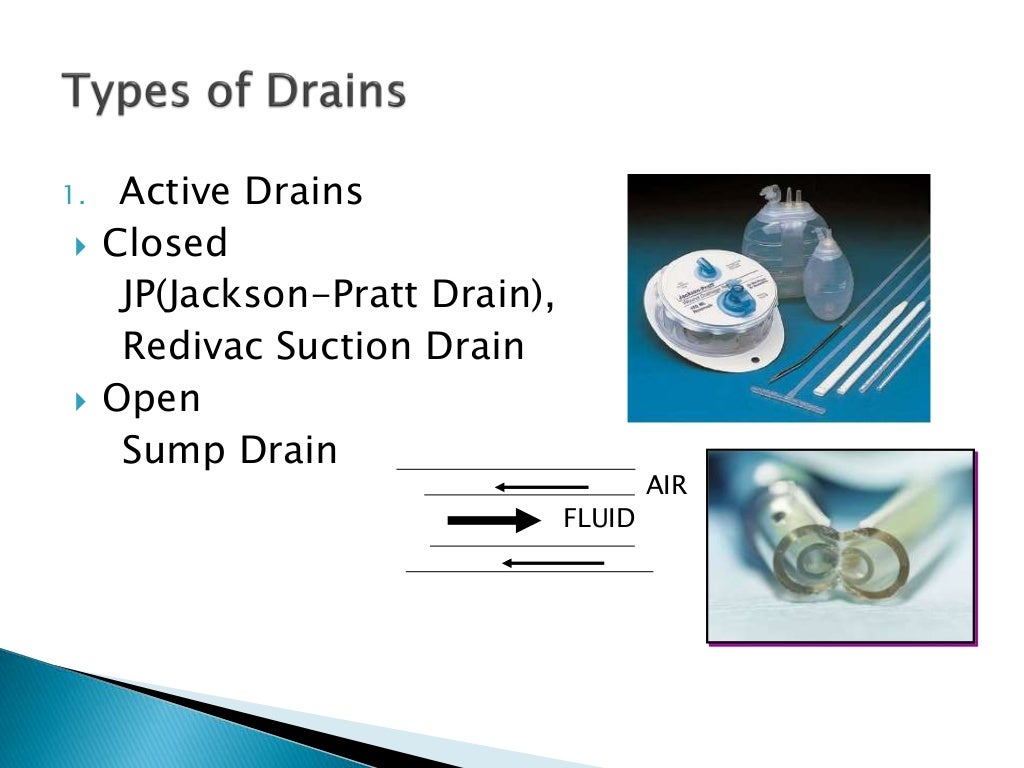
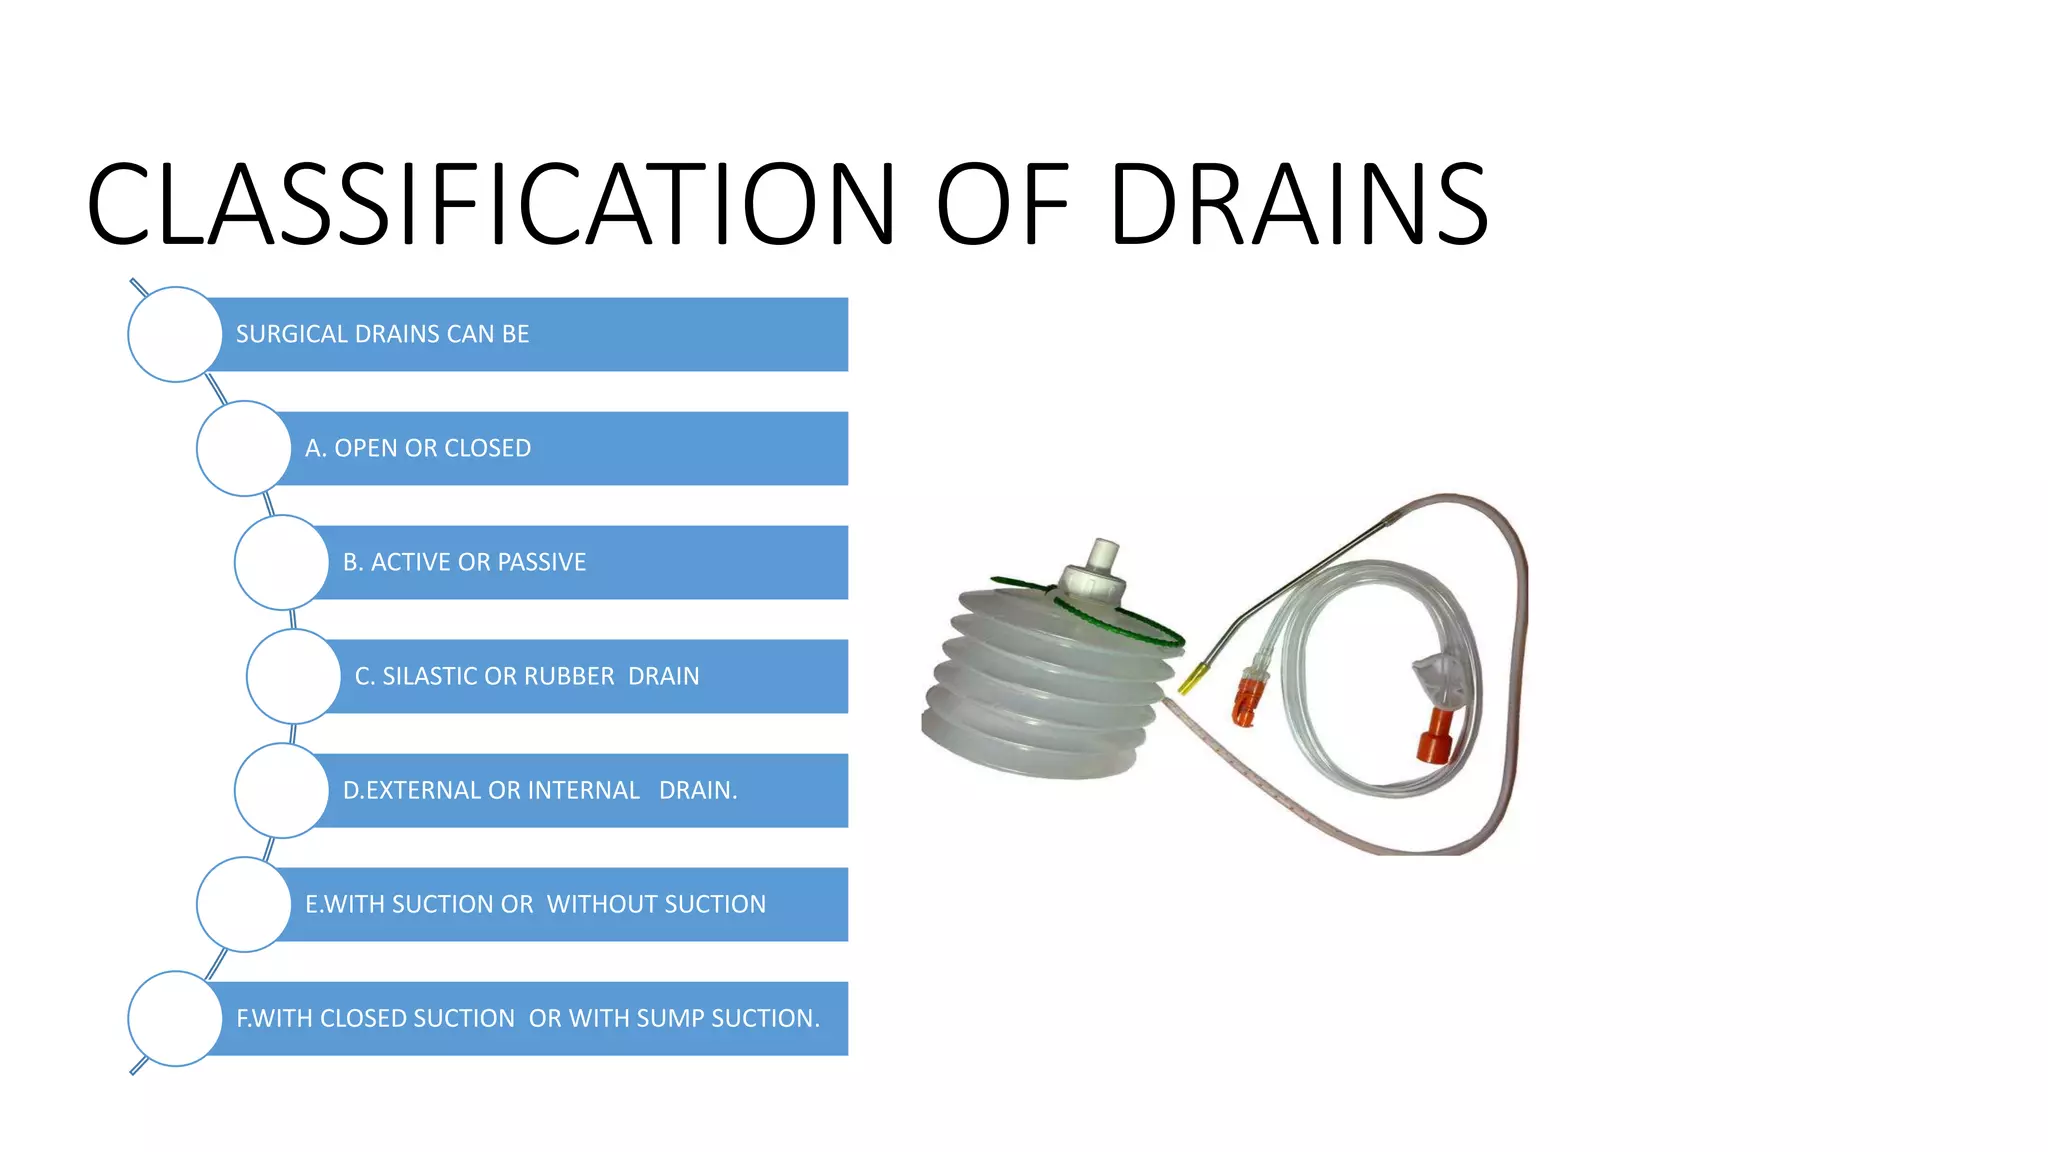
Surgical drains are tubes placed during operations to move fluid away from a surgical site so it does not pool and cause infection or wound breakdown. They range from simple passive tubes to closed systems with suction. The choice depends on what kind of fluid you expect, how much of it will accumulate, and where the surgery took place. I have worked with most of these in general surgery, trauma, and orthopedic cases. The categories break down into passive drains, active closed-suction drains, and specialized variant drains designed for specific anatomical concerns. Understanding the difference matters because picking the wrong one often leads to complications that take longer to resolve than the original surgery itself. Passive drains rely on gravity and capillary action. Jackson-Pratt drains and Penrose drains fall into this group. A Jackson-Pratt uses a closed bulb that creates negative pressure when compressed. The fluid moves through tubing into that reservoir. A Penrose is essentially an open rubber tube laid along the wound. It lets fluid drain onto a dressing. Penrose drains are cheap and simple but they carry a higher risk of retrograde contamination because they are not a closed system.
Closed-suction drains include the Hemovac and the more modern negative-pressure variants. These maintain continuous low suction. They are better for preventing seroma formation after breast surgery or abdominal wall procedures. The suction prevents fluid from collecting around the operative field. I once placed a Hemovac after a large abdominoplasty in a patient with significant adipose tissue. The drain kept pulling clear serous fluid for four days. We left it in longer than usual because the dead space was substantial. Removing it too early would have guaranteed a seroma that needed repeated aspiration. T-tubes are a different category altogether. They are used primarily in biliary surgery. The tube passes through the common bile duct and exits the body. It keeps the duct open while swelling goes down after choledochotomy. A cholangiogram can be done through it before removal. I learned the hard way that leaving a T-tube in beyond three weeks without imaging leads to encrustation and makes removal significantly more complicated. I had a case where the tube was crusted with bile salts and we had to involve interventional radiology for percutaneous exchange instead of a straightforward removal at the bedside. Wound VAC systems are a more recent addition. They apply controlled negative pressure directly to an open wound. This is not a traditional drain but it functions as one in many ways. The foam matrix collects exudate and the machine maintains consistent suction. These are commonly used in contaminated or revision cases where primary closure is not possible. The downside is cost and the inconvenience of managing the canister changes every two to three days. A standard open wound with a VAC typically requires dressing changes twice daily which adds nursing workload significantly.
Emergencies and trauma cases often call for chest tubes. These are larger bore drains placed in the pleural space to remove air or blood. A standard 28 French tube is common for hemothorax. A smaller 14 French pigtail catheter may suffice for a simple pneumothorax. The size matters because a chest tube that is too small gets occluded by blood clots. I had a trauma case where the initial tube kept clotting and the patient developed a trapped lung. Switching to a larger bore tube and administering intrapleural DNase helped break up the fibrin deposits. That combination is now standard practice in many centers for complicated effusions. Internal versus external drainage is another key distinction. Some drains stay entirely inside the body and are removed through a minor procedure. External drains exit through the skin and connect to a collection device. Internal stents like ureteral stents or biliary stents are self-draining in a sense but they are classified differently because they do not connect to an external bag. The decision process for selecting a drain type usually involves evaluating the expected volume and viscosity of drainage. Thick purulent fluid requires a larger bore drain than thin serous fluid. Location matters too. Drains near the diaphragm or in deep pelvic spaces behave differently than superficial ones. Gravity assists in some areas and works against you in others. I once placed a drain in a deep pelvic collection after a low anterior resection. The drain kept collapsing because the negative pressure was not sufficient to overcome the ambient tissue pressure. Switching to a larger diameter drain with active suction resolved the issue within hours.
Get the Full Details

Removal timing is where most mistakes happen. Leaving a drain in too long increases infection risk. Removing it too early invites fluid accumulation. The general rule is to monitor output volume and character. When output drops below 20 to 30 milliliters per day for a closed system, removal is usually safe. Penrose drains are removed earlier because they are passive and the tract begins closing almost immediately. I follow a protocol of removing JP drains when output is under 30 cc per day over two consecutive days. That threshold has worked consistently across thousands of cases in my experience. Complications from drains are surprisingly common when people underestimate them. Infection at the site is the most frequent issue. Skin breakdown around the tube happens especially in elderly patients with thin skin. Drain occlusion occurs when fibrin or tissue debris blocks the lumen. I once found that a drain that appeared to be functioning well on imaging was actually clogged because the exit site was leaking around the tube rather than through it. Flushing the drain with sterile saline through a closed system cleared the obstruction without needing to remove and replace it. Sometimes drains cause more harm than good. In clean orthopedic implant surgery, routine drain placement is controversial. Several studies show no benefit and a slightly higher infection rate when drains are used prophylactically. The current trend in joint replacement is to avoid drains altogether unless there is a clear indication such as significant soft tissue dissection or known coagulopathy.
Cost and resource utilization should not be ignored either. Closed suction systems are more expensive than passive drains. Insurance coverage varies. In resource-limited settings, a simple Penrose or even a closed glove fingertip drain serves the purpose adequately. I have used improvised closed drains made from sterile examination gloves with rubber bands securing the tubing. They work well in austere environments where commercial drain supplies are unavailable. The technique for placement matters as much as the type you choose. The drain should be inserted through a separate incision when possible rather than through the primary wound. This reduces the risk of the wound dehiscing along the drain track. The exit site should be secured with sutures to prevent accidental dislodgement. I always use a non-absorbable suture like 3-0 silk around the drain at the skin level and tape the tubing securely to the patient's skin with an additional anchor point further up the tubing to reduce tension on the insertion site. Maintenance involves regular assessment of the output color and volume. Clear yellow fluid is expected early on. Bloody output that persists beyond the first 24 hours warrants evaluation. Fecal or bilious drainage indicates a possible enteric or biliary leak and needs immediate attention. I check drain output every four hours during the first postoperative day and then every shift thereafter. Documenting the trajectory of output volume helps predict when the drain can be safely removed.
Newer drain materials and coatings are improving outcomes. Antimicrobial-impregnated drains are available and reduce colonization at the skin entry site. Silicone-coated tubes cause less tissue irritation than latex. Bioabsorbable stents are replacing some external drains in urologic and biliary procedures. These developments are incremental but meaningful over time. The most important thing to remember is that a drain is not a substitute for meticulous surgical technique. Good hemostasis and proper tissue handling matter far more than any drain you place afterward. Drains manage what your surgery could not prevent. They are a safety net, not a fix for sloppy operative technique. I have seen drains left in place for weeks in cases where a more thorough surgical approach would have eliminated the need entirely.