
Aerospace Physiology Training and Reference Guide
The fundamentals come down to understanding how the human body degrades under altitude, acceleration, and thermal extremes. You need to know the thresholds, the symptoms, and the countermeasures. Not the textbook definitions, but the ones that matter when you are 35,000 feet up and something goes wrong. Usaf Aerospace Physiology covers four main stress domains: hypoxia and decompression, G-forces, thermal environments, and spatial disorientation. Each one has its own timeline from symptom onset to performance failure. The hypoxia domain is the most unforgiving. At 25,000 feet, effective consciousness time without supplemental oxygen is roughly three to five minutes for a trained individual. That window shrinks dramatically if you have been holding your breath, exerting yourself, or breathing low-pressure nitrogen-rich gas before the event. I once had a pilot who passed out during a simulator run at 30,000 feet because he had spent the previous ten minutes doing a slow, controlled descent on cabin pressure instead of maintaining oxygen flow. He had convinced himself he was fine because he felt normal. The hypoxic threshold does not announce itself with panic. It arrives as a subtle clarity loss and mild euphoria before motor control drops off.
Essential Protocols for Usaf Aerospace Physiology
The core protocol revolves around the oxygen system and the pressure breathing apparatus. You wear the mask. You check the seal before pressurization. You do not rely on the ambient cabin feel as a valid indicator of oxygen adequacy. The mask must be on and functioning before you climb above 10,000 feet unless you are in a pressurized environment that maintains an equivalent airspeed of 8,000 feet or lower. Cabin altitude, not flight altitude, is the real variable. A pressurization failure at 40,000 feet can bring cabin altitude above 30,000 in under 30 seconds in certain aircraft types. That is faster than it takes to properly don and seal an oxygen mask if you are not practiced. G-force management requires anti-G straining maneuvers. The modern standard is the L-1 or H-1 maneuver depending on the suit and vest configuration. You flex your leg and abdominal muscles hard while holding your breath against a closed glottis. This raises your blood pressure artificially and keeps blood in the brain. The maneuver should be sustained continuously during positive G exposure, not done in pulses. The most common mistake I see is pilots releasing the strain between G-load spikes. That is when gray-out occurs. The visual field narrows from the periphery inward, and once you lose central vision, recovery is almost never possible without reducing G-load immediately. For the anti-G suit, you need to understand the inflation cycle. The suit inflates from approximately 1.5 to 3 seconds after G onset, peaking around 4 to 5 seconds. If you initiate the straining maneuver before the suit is fully inflated, you can overcompensate and actually reduce cerebral perfusion. The correct timing is to begin muscle tension at the moment of G-onset, then maintain it steadily as the suit inflates behind you. The suit handles the peripheral pooling; your muscles handle the central venous return. They work in tandem. One without the other is insufficient above 4 G.
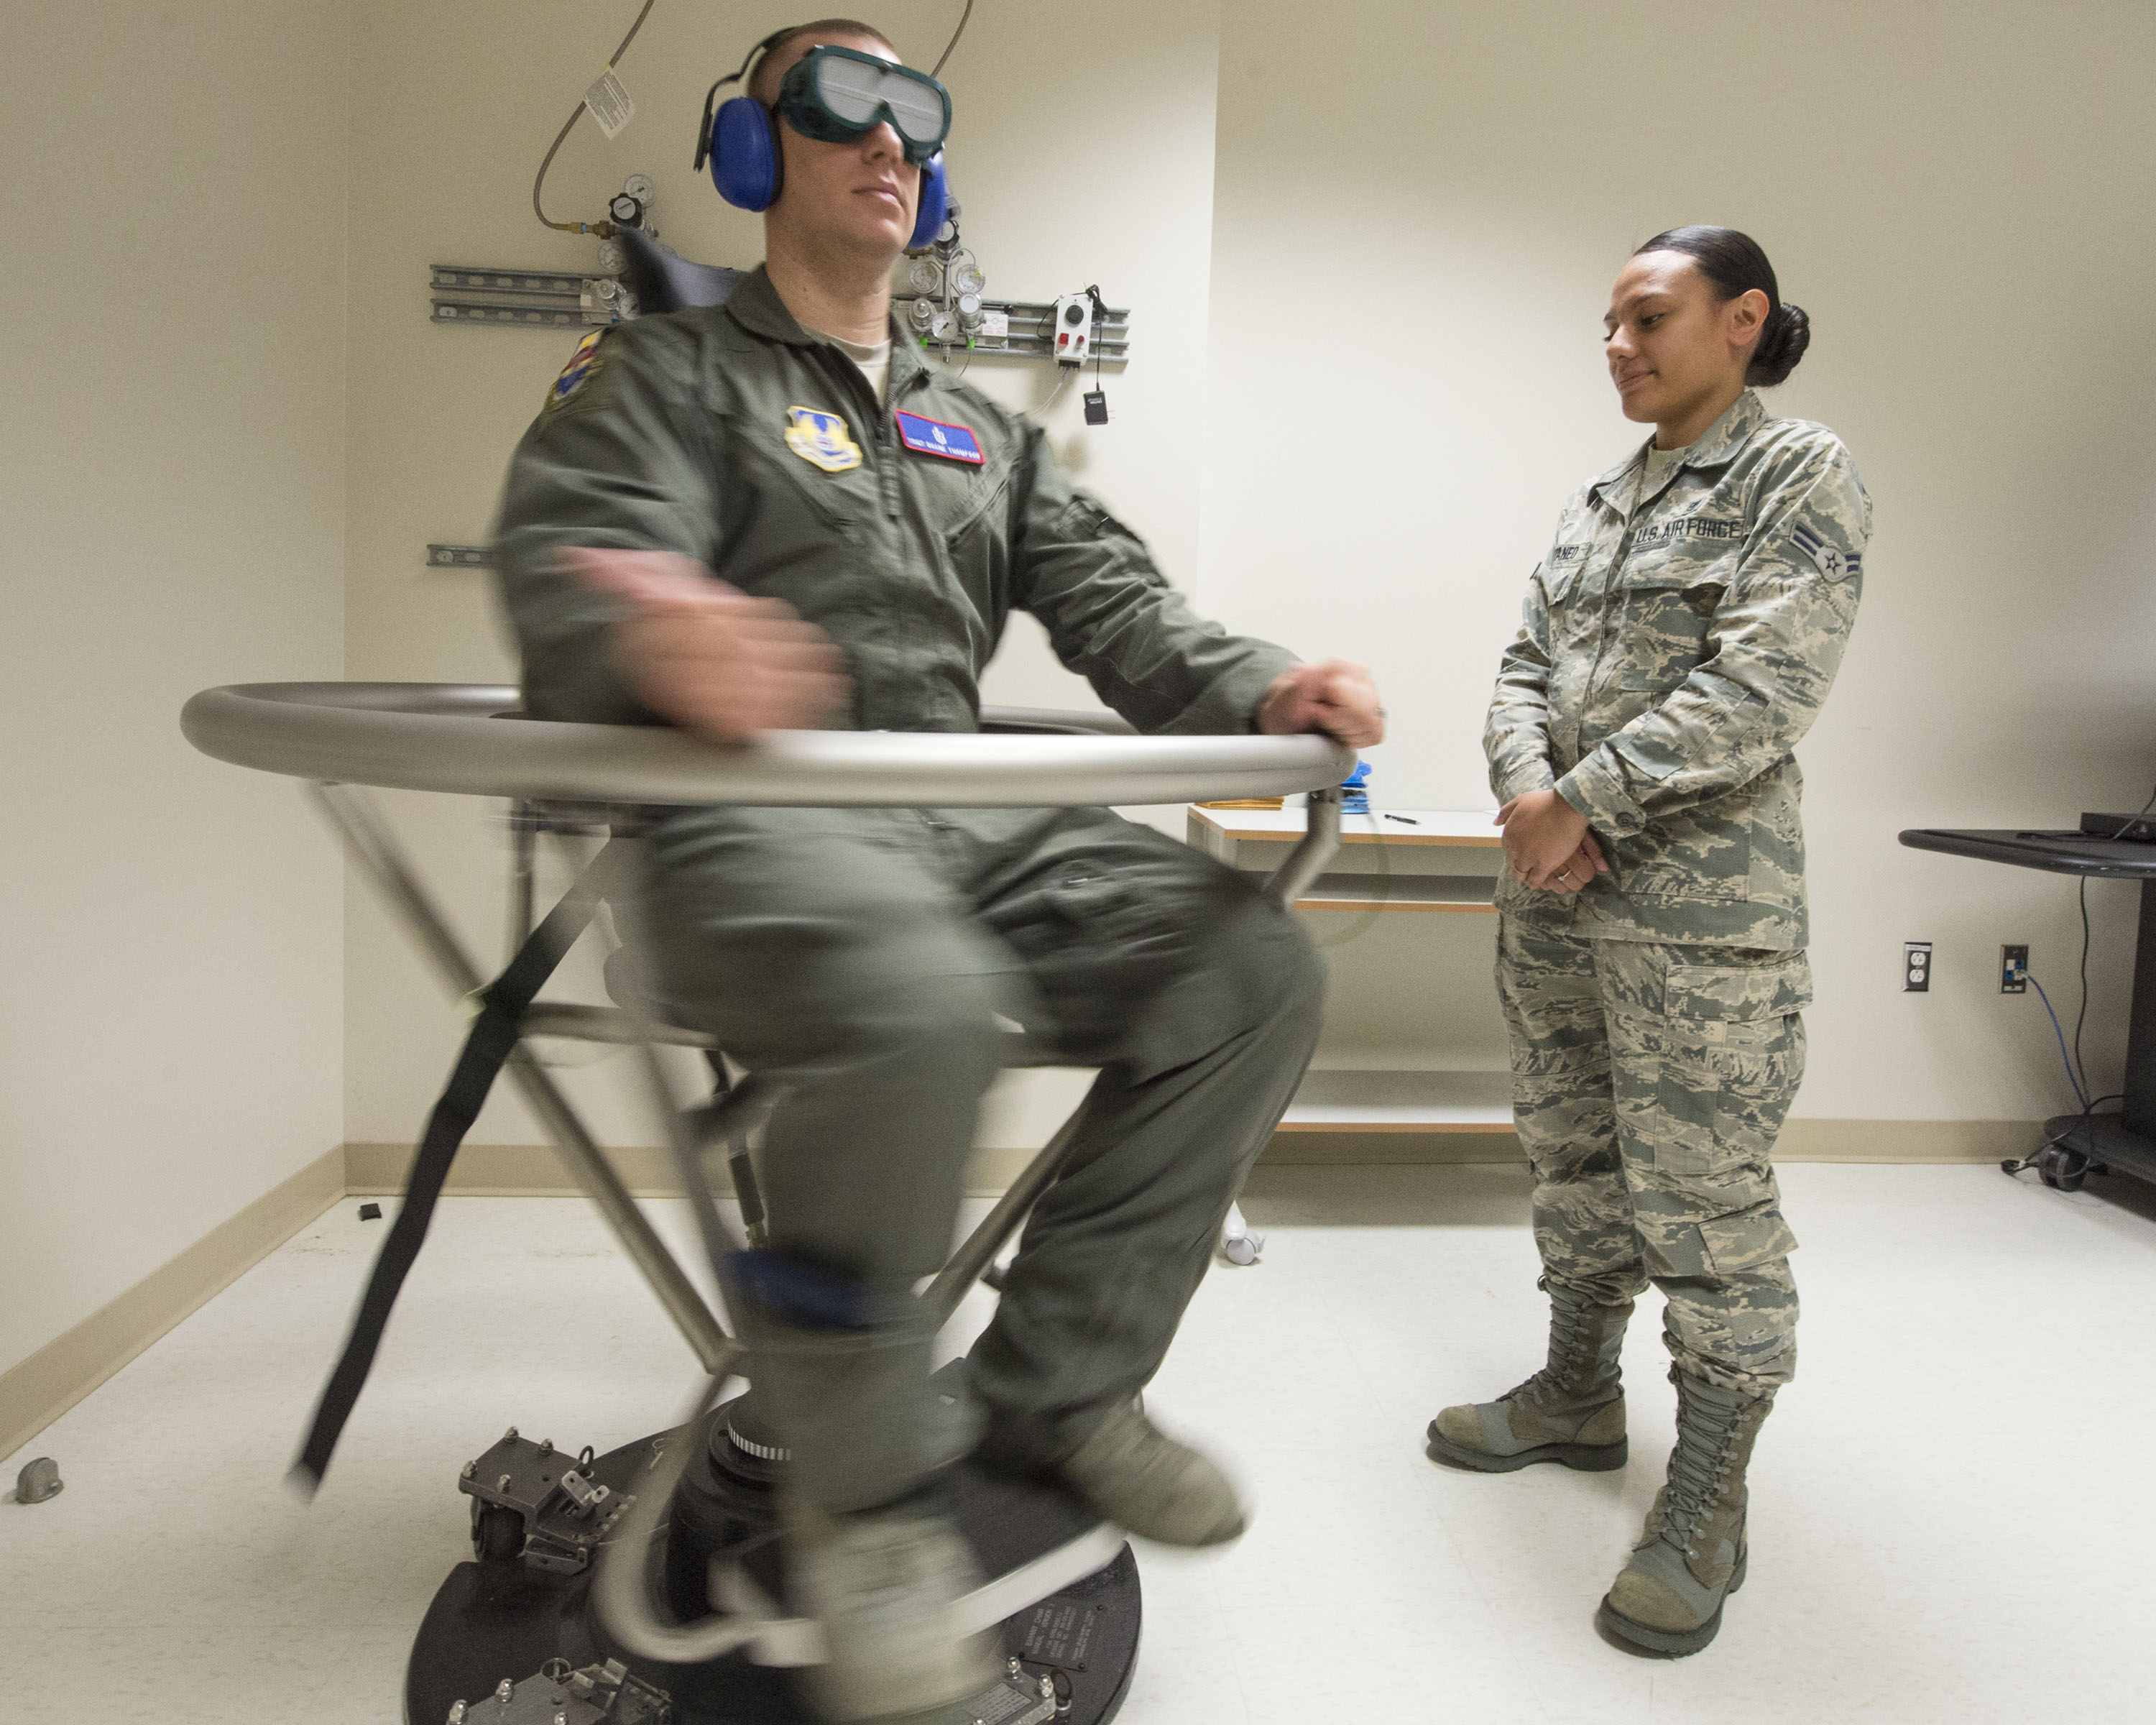
Thermal physiology in high-altitude environments involves both cold exposure and dehydration. Moisture inside the flight suit freezes rapidly once you are above 20,000 feet in an unpressurized environment. The cold stress response diverts blood flow to the core, which compounds the G-force problem. Dehydration reduces plasma volume by roughly 10 to 15 percent after a single high-altitude exposure, which directly impairs G-tolerance. The workaround I use is a strict pre-flight hydration protocol. Two liters of water in the six hours before flight, minus whatever you urinate out in that window. It is not comfortable, but it adds roughly 0.5 to 1.0 G of effective tolerance during exposure. Spatial disorientation falls into three categories: unrecognized, recognized, and induced. The most dangerous is unrecognized. Your vestibular system tells you you are climbing when you are actually in a shallow turn. Your eyes can be fooled. The instruments cannot. The only workaround is instrument cross-check discipline. Three seconds per instrument, rotating left to right, always returning to the primary attitude indicator. Do not chase a single instrument. The human eye needs approximately two seconds to focus on a different gauge. If you spend six seconds checking attitude, then heading, then altitude, your situational awareness is three seconds stale on the primary display. The edge case I encountered that nobody talks about is the interaction between positive G and the Valsalva maneuver during ear clearing. If you perform a forceful Valsalva while under 3 to 4 G of load, the increased intrathoracic pressure can temporarily reduce venous return just enough to trigger a black-out. I learned this the hard way during a routine formation checkout. I cleared my ears aggressively during a turn into the sun, lost vision for approximately two seconds, and came out of it disoriented about 15 degrees off heading. The fix was simple: stop clearing your ears actively during G exposure. Let the pressure equalize passively through the Eustachian tubes, or defer ear clearing until you are at a constant G level or below 1 G. It sounds trivial. It is not.
Get the Full Details
Supplemental Resources and References
The official technical manual for this subject is T.O. 00-20-1, the Aerospace Physiology Training Manual. It is publicly available through the Air Force Electronic Technical Library and can be downloaded at no cost. The current revision covers hyperbaric physiology, inert gas narcosis at altitude, and the updated G-tolerance standards for modern flight suits. Another essential document is AFMAN 11-202V3, which references physiology requirements within the broader flight operations manual. It is not as detailed on the physiological mechanisms, but it links the physiology knowledge directly to what is expected during flight certification and operational compliance checks. The FAA also maintains Advisory Circular 61-107, which covers high-altitude physiology for civil pilots operating above 25,000 feet. The material overlaps significantly with the USAF standards, and it is useful for understanding the common baseline. The military version goes further into pressure breathing oxygen systems and negative G tolerance, which the civil guidance does not address.
There is no shortcut around repetition. Understanding the numbers is one thing. Under stress, those numbers become irrelevant. The protocols need to be mechanical. Practice the anti-G maneuver seated and standing until you can execute it without thinking. Check your mask seal every single time, even when you have done it a hundred times before. The time it takes to properly seal a mask is about eight seconds. The time it takes to fail to seal it correctly on a bad day is two seconds. The difference between a controlled landing and an emergency is usually measured in that gap. The biggest limitation in aerospace physiology training is that most exercises are simulated. You will never truly experience 9 G in a classroom. You will never hypoxiate in a controlled setting without specialized equipment. The simulations get you close, but they compress the timeline and remove the environmental noise. Real exposure to high G for more than ten seconds produces a different cognitive state than anything a simulator can replicate. The simulation teaches you the procedure. The procedure keeps you alive. Whether it works under actual conditions depends on how much time you have spent doing it until it is automatic.




