What the Vanderbilt Assessment Scale Actually Is
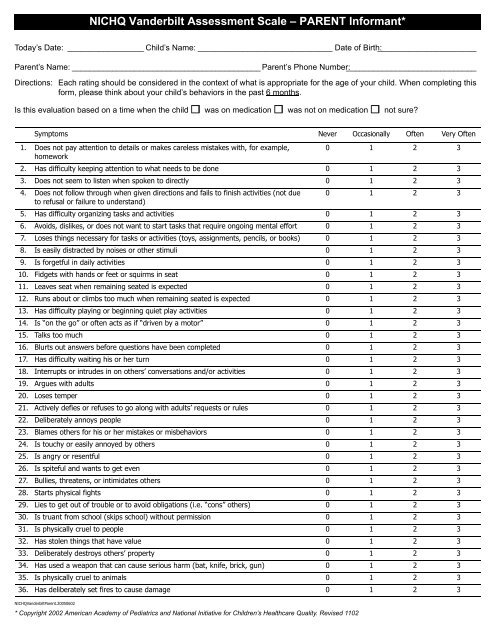
The Vanderbilt Assessment Scale is a behavioral screening tool primarily used to evaluate children for ADHD and related disorders. It is not a diagnostic instrument on its own, which is a distinction parents and even some clinicians blur. The parent version collects observations from home over a typical week or two, while the teacher version does the same for school. Both forms feed into a clinical assessment alongside a direct evaluation, medical history, and sometimes standardized testing. There are two main versions. Version 4 is the most commonly referenced. It includes symptom checklists mapped directly to DSM-IV criteria, plus separate assessments for oppositional defiant disorder, conduct disorder, anxiety, depression, and learning problems. Some clinics have moved toward Version 5, which aligns with DSM-5 criteria. The differences matter if you are filling these out for a school evaluation versus a psychiatric workup.
Vanderbilt Assessment Scale Parent
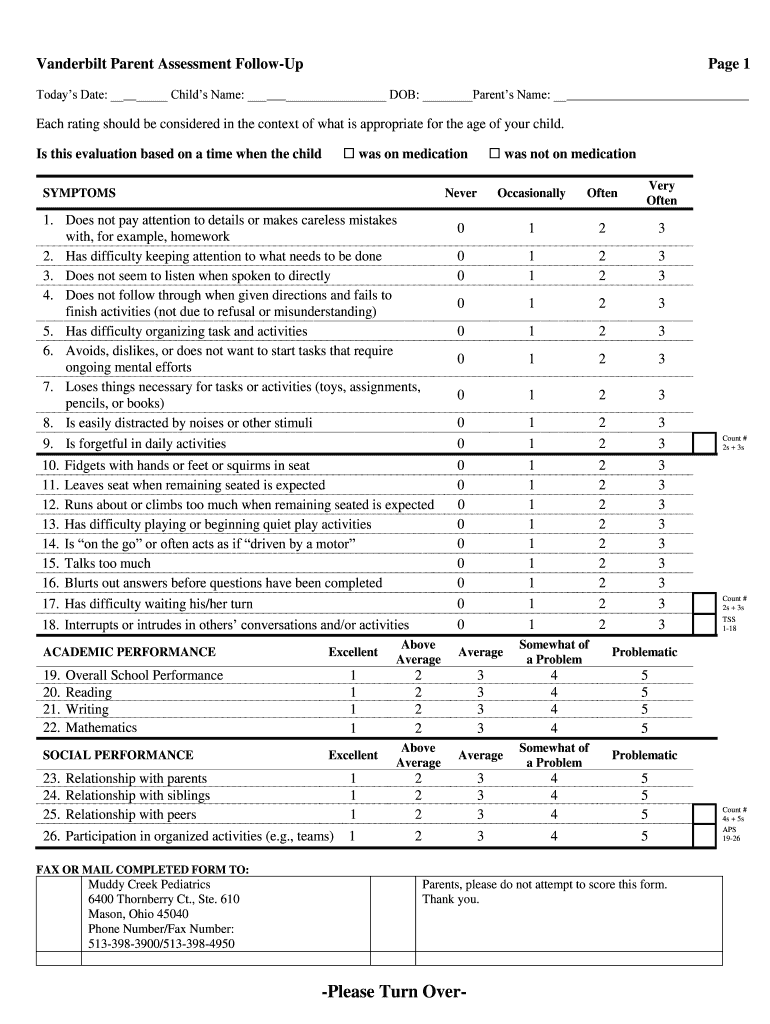
The parent form asks you to rate your child's behavior across roughly eighteen ADHD symptoms in two clusters: inattention and hyperactivity-impulsivity. Each symptom is scored as never, occasionally, or often. There are also functional impairment questions that ask whether the behavior causes problems at home, with siblings, or in social settings. A positive screen typically requires at least six symptoms rated as often in one cluster, plus evidence of functional impairment. The impairment section is where a lot of people get tripped up because it is weighted just as heavily as the symptom count. The original Vanderbilt forms are in the public domain. You can download them from the Vanderbilt University Medical Center website, which hosts both the parent and teacher versions. Several state Medicaid programs and school district portals also distribute them. Make sure you are downloading the version labeled with the correct year, because the DSM-5 updated version has different wording on a few items. Using an outdated form won't invalidate an evaluation, but it can create confusion when the clinician is cross-referencing current criteria. I have watched parents fill these out and realize too late that they scored based on their worst day rather than their typical week. The instructions say to rate behavior over the past thirty days, but that window is broad enough that a single rough week skews everything. I had a case where a child's teacher form came back almost completely clear while the parent form lit up red. The kid had just gone through a messy divorce situation at home that was inflating the scores. The parent hadn't realized how much the stress was coloring his perception. Once we separated the situational factors from the baseline behavior, the clinical picture changed entirely.
Another thing that goes wrong routinely: parents conflate the child's behavior with compliance issues. The scale measures core ADHD symptoms, not defiance. If your kid doesn't do homework because he refuses to do it, that belongs on a different part of the evaluation. If he doesn't do homework because he lost the assignment three times and forgot the instructions despite reminders, that is inattention and it belongs on the scale. Writing down specific examples next to each rating helps keep this straight. I usually tell parents to jot a one-line note for any symptom they score as often, so they can pull details if the clinician asks. The functional impairment section deserves more attention than it gets. It is not filler. A child can meet symptom thresholds but show zero impairment, and that changes the diagnosis completely. Conversely, a child with fewer symptoms but significant impairment across multiple settings often gets flagged for a full evaluation anyway. When I worked clinic sessions, I found that parents tend to underreport impairment because they normalize their kid's struggles. "Well everyone in my family is like this" is a common line. It is not inaccurate, but it does not help the clinical assessment. Put the impairment on the form honestly. The goal is to get the right support, not to make the child look worse than they are.
Get the Full Details

What the Scale Does and Does Not Do
It screens. It does not diagnose. A high score on the Vanderbilt means you should talk to a professional, not that your child has ADHD. There are conditions that mimic ADHD symptoms: sleep apnea, iron deficiency, thyroid issues, trauma, anxiety disorders, and even chronic boredom in gifted kids who are not being challenged. I once saw a twelve-year-old whose Vanderbilt scores suggested severe ADHD, and the workup revealed he was getting maybe six hours of sleep a night because of untreated insomnia. Fix the sleep, scores dropped by half. The teacher form is not just a copy-paste exercise. Teachers see the child in a different environment with different demands. Discrepancies between home and school ratings are actually informative. If symptoms show up only at home, the issue may be environmental or relational rather than neurodevelopmental. If symptoms show up everywhere, that points toward a more consistent underlying condition. Both forms together give a much clearer picture than either one alone.
Common Pitfalls
Rating everything as occasionally is the most common mistake. Parents worry about over-pathologizing, so they default to the middle option for everything. This flattens the data and makes the form useless. Pick the rating that matches what you actually observe. Another pitfall is skipping the impairment questions because they feel subjective. They are subjective by design, and that is the point. ADHD is diagnosed partly on how symptoms affect functioning, not just on raw symptom count. A third pitfall is filling out the form during a crisis. If your child is going through a breakup, a move, a family loss, or academic failure, the scores will be artificially inflated. Wait it out if you can, or note the circumstances on the form so the clinician can adjust. The scale was never meant to capture acute stress responses.
What Happens After You Submit It
The clinician reviews the scores, compares them to cutoff thresholds, and decides whether a full evaluation is warranted. A full evaluation usually includes a clinical interview, collateral information from multiple sources, cognitive or academic testing, and sometimes medical workup. The Vanderbilt is one data point in a larger process. Do not treat a passing score as a final answer, and do not treat a high score as a label. It is a starting place. If you are going through this process for your child, the most useful thing you can do is be specific and consistent. The form rewards honest observation, not advocacy or minimization. Fill it out once, then set it aside for a day and review it. You will catch errors and re-ratings you missed the first time.