Why you need this when you're pulling an all-nighter
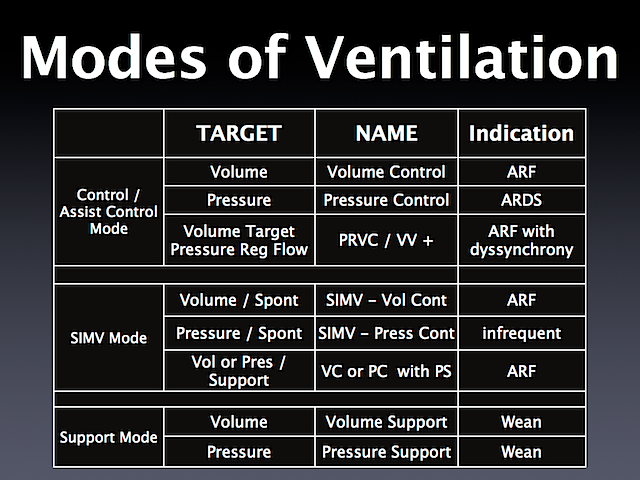
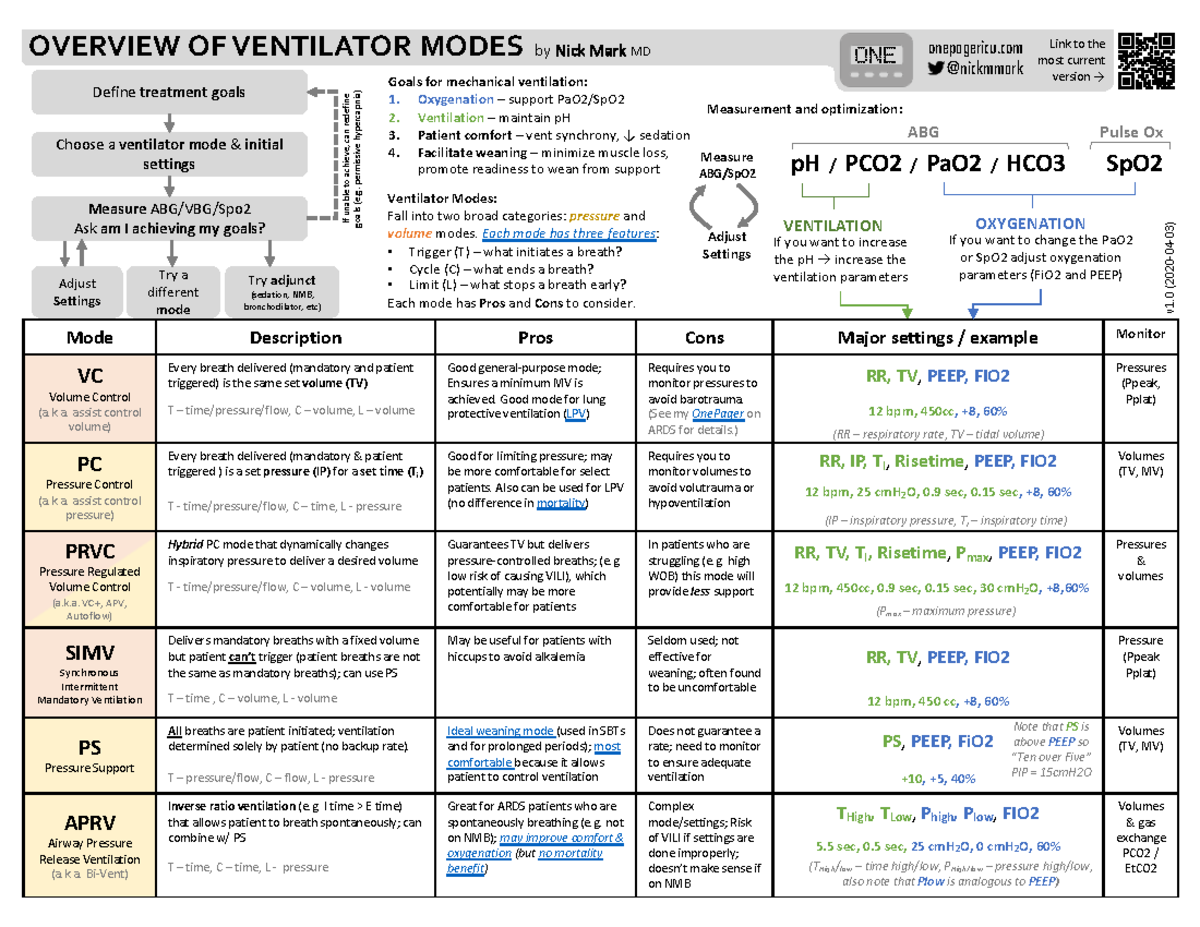
I keep a laminated card at the edge of my monitor. Not because I don't know my modes, but because during a coding event or a code blue at 3 AM, your brain doesn't do well with nuance. You need the numbers in front of you, not the textbook definitions you memorized three years ago. The Ventilator Modes Cheat Sheet I use covers the six modes we actually run on our floor, the settings that matter, and the one setting you should never ignore for each. It's not a replacement for understanding physiology. It's a pattern-matching aid. When you walk into a room and the vent is doing something unexpected, the cheat sheet helps you answer three questions fast: what mode is it in, what triggers are driving it, and what knobs can you turn right now without calling Respiratory Therapy. That's it. It won't tell you why the patient is fighting the vent, but it will tell you whether it's a trigger problem, a rate problem, or a compliance problem. Let me start with the one I wish people understood better, not the most common one. SIMV—Synchronized Intermittent Mandatory Ventilation—gets blamed for patient-vent asynchrony more than any other mode, and the reason is almost never what people think. It's not that SIMV is bad. It's that people set the mandatory rate too low and then wonder why the patient is triggering breaths that aren't being supported. The workaround I use: always check the patient's spontaneous respiratory rate first. If it's more than 1.5 times the set mandatory rate, you're already in trouble. Drop the mandatory rate to maybe 6-8, let the patient carry their own minute ventilation, and add pressure support on top. That turns SIMV into something actually usable instead of a tug-of-war.
Assist-Control (AC) for volume is the default for a reason. You set the tidal volume—usually 6 to 8 mL/kg of predicted body weight—and the vent delivers that every time, whether the patient triggers it or the machine does. The trap here is auto-PEEP in COPD patients. I had a case last year where a guy with severe emphysema was on AC-V with a set TV of 480 mL and a rate of 14. His inspiratory time was 0.9 seconds because we were trying to keep peak pressures down. He was breath stacking before I even walked in. The fix wasn't changing the mode. It was dropping the rate to 10, cutting the TV to 400, and accepting a higher PaCO2. Permissive hypercapnia saved his lungs more than any mode switch would have. Pressure Control is what I reach for when peak pressures are the problem, not plateau pressures. The difference matters. In PCV, the vent limits the pressure and lets the tidal volume vary. In VC, the vent guarantees the volume and the pressure soars if compliance drops. If your plateau is already above 30 and you're only seeing high peaks, stick with volume control and add a sedative. If both are climbing, switch to pressure control and watch the minute volume. It will drop. You'll need to adjust the pressure level until the EtCO2 stabilizes, which usually takes two or three attempts over 20 minutes.
Settings that matter and settings that don't
Here's the part most cheat sheets skip. FiO2 and PEEP are not independent levers. They're coupled. When you increase PEEP in a patient with ARDS, you're recruiting alveoli, which improves compliance, which means you might actually be able to lower the FiO2. The old school PEEP/FiO2 tables from the late 90s are useful as a starting point but they don't account for driving pressure. I use a different heuristic now: target a driving pressure below 15 cmH2O. Driving pressure is plateau minus PEEP. If it's above 15, you're likely overdistending some alveoli while recruiting others. That's the real problem, not the FiO2 number. A quick Ventilator Modes Cheat Sheet will list FiO2 ranges but it won't tell you that driving pressure is a stronger predictor of mortality than either FiO2 or PEEP alone. RATE is the hidden driver of auto-PEEP. Every time you add a set breath per minute, you're stealing from expiratory time. In obstructive disease, the expiratory time is already short. Add 16 breaths per minute and you'll see the intrinsic PEEP creep up even if the set PEEP hasn't changed. I check the expiratory flow waveform first. If it doesn't return to baseline before the next breath fires, you have auto-PEEP. The fix is almost always to lower the rate before you reach for a neuromuscular blocker.
Get the Full Details
When the cheat sheet fails you
I'll be straight about this. The Ventilator Modes Cheat Sheet doesn't help when the patient has a complex arrhythmia causing trigger desynchronization, or when the ventilator circuit has a hidden leak that's mimicking a demand-flow mismatch. I encountered the latter in a trauma patient two years ago—the vent kept cycling to inspiration, the flow trigger seemed fine on paper, but the minute ventilation was 20% lower than set. Turns out there was a crack in the Y-connector that only appeared under pressure. No cheat sheet would catch that. You need to listen to the circuit and watch the exhaled volume number. If exhaled minus inspired is more than 100 mL on a modern vent, check the circuit before you check the mode. Another failure mode: neuromuscular blockade. If you paralyze the patient, the "synchronized" part of SIMV disappears. The vent will deliver mandatory breaths on schedule regardless of the patient's own drive. That's sometimes exactly what you want after major abdominal surgery. It's also what makes you miss a spontaneous breath initiative if you're not watching the waveform. The workaround is simple—every 4 hours or after a med change, run a sedation vacation if the patient is stable enough, or at minimum watch the trigger sensitivity for a while.
My actual laminated card contents
Volume Control: TV 6-8 mL/kg PBW, rate 12-16, I:E 1:2, plateau < 30, driving
15. Pressure Control: PC 12-20, rate 12-16, I:E 1:2, TV 400-500, plateau
30. AC-V: same as volume control but every breath is patient-triggered if possible, support level set to meet target MV.
AC-P: same as pressure control but every breath gets full pressure support, watch for hyperventilation if patient is anxious. SIMV: mandatory rate 6-10, pressure support 10-15 on top, check spontaneous rate stays below 1.5x mandatory. PSV: pressure support 8-12, trigger 2 L/min, rate limit off, RR target 10-20, wean when patient can sustain it for 2 hours without fatigue signs.

HFOV and APRV don't make the card. They're not bedside mode changes. Those are Intensivist-level decisions with a CT scan and a pulmonologist on the phone. The card is for the things you can adjust before you page someone.
A note on PBW calculations
Almost every wrong setting starts with a wrong predicted body weight. I've seen nurses and residents calculate PBW from actual body weight in obese patients, which means they're delivering 8 mL/kg of total weight instead of lean mass. The correction is brutal but necessary. For men: 50 + 0.91 × (height in cm - 152.4). For women: 45.5 + 0.91 × (height in cm - 152.4). If the patient is obese and you use actual weight, you're essentially volutraumatizing them on purpose. I had a 120 kg male who was on 700 mL tidal volumes because someone used his actual weight. Plateau was 38. Switched to PBW-based 480 mL and the plateau dropped to 24 in 15 minutes. Same patient, same lungs, completely different math. The Ventilator Modes Cheat Sheet lives on my screen because the numbers change faster than my memory does under stress. But the real skill isn't memorizing the modes. It's knowing which number to look at first when something goes wrong. Drive pressure. Then minute volume. Then trigger sensitivity. Everything else is downstream.