Where the Numbers Actually Come From
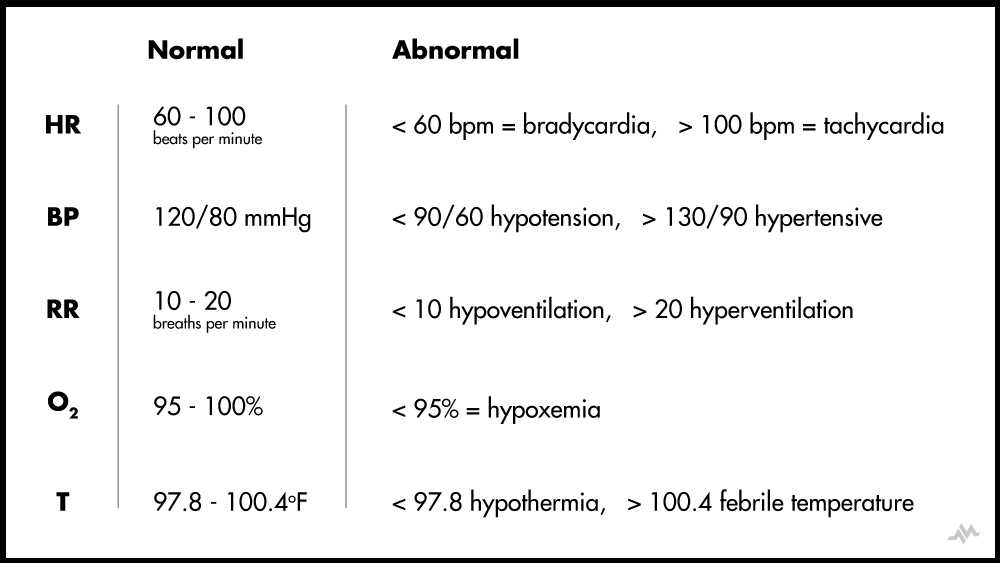
Vital Signs Normal Ranges are not the hard boundaries most people think. The standard reference intervals most textbooks list were pulled from healthy volunteer studies in the 1970s and 80s, mostly white, middle-class adults coming in for routine exams. That means the "normal" band is wide by design, not because human physiology varies that much, but because they wanted coverage for 95% of a selected population. I have seen younger clinicians treat the edges of those ranges as absolute lines. That causes problems fast. Take resting heart rate. Textbook says 60 to 100 beats per minute. That covers a well-trained marathoner at 42 bpm and a deconditioned office worker tapping 98 after climbing two flights of stairs. Both are physiologically plausible. The number itself does not carry enough signal to be meaningful without context.
Understanding Vital Signs Normal Ranges in Practice
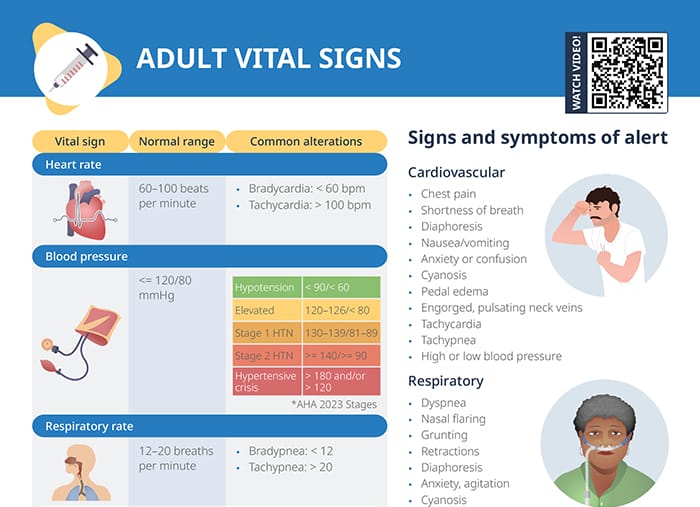
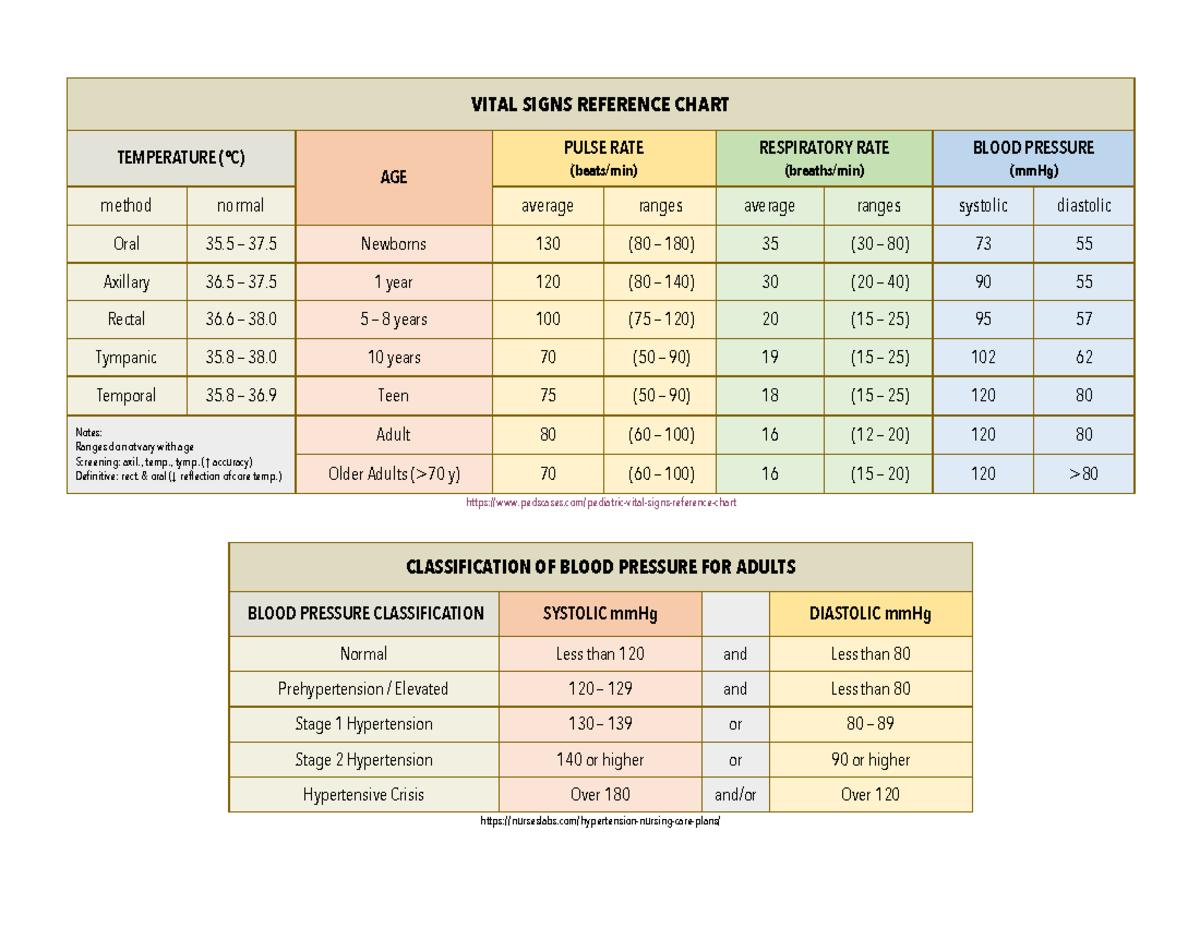
Here is how I actually use these numbers at the bedside instead of treating them as gospel. Temperature sits around 36.5 to 37.5 degrees Celsius for most adults measured orally. That range shifts if you switch sites. Rectal readings run roughly 0.3 to 0.6 degrees higher. Axillary readings run lower and are more variable depending on how tightly the probe is held. I stopped arguing with residents about borderline fevers until someone started recording the measurement site on every nursing note. It cut the confusion dramatically. Heart rate between 60 and 100 is the headline number. What matters more is the trend and the clinical picture. A patient with atrial fibrillation sitting at 88 who looks and feels fine does not need intervention. A patient in sinus rhythm at 72 who is diaphoretic and hypotensive absolutely does. The number alone will mislead you in that scenario.
Respiratory rate is 12 to 20 breaths per minute in resting adults. This is also the most underused vital sign and the one I see most often charted incorrectly. Nurses count for fifteen seconds and multiply by four. That introduces rounding error. I recommend counting for a full sixty seconds, especially when the rhythm looks irregular. The difference matters when you are tracking early sepsis or a deteriorating respiratory rate in a patient who does not yet look critically ill. Blood pressure is where the noise is loudest. "Normal" is generally below 120 over 80 for a single reading in a calm setting. But a single reading tells you almost nothing. White coat hypertension affects roughly 15 to 30 percent of newly labeled hypertensives. Masked hypertension affects another chunk in the opposite direction. Ambulatory monitoring is the actual standard for diagnosis, not the cuff in the exam room. Oxygen saturation reads 95 to 100 percent on room air at sea level. Below 95 raises eyebrows. Below 90 is an actionable threshold in most protocols. But remember that pulse oximetry is less accurate in patients with poor peripheral perfusion, dark skin pigmentation, nail polish, and motion artifact. I had a patient who was clearly hypoxic with a saturation stuck at 97 percent while his work of breathing was unmistakable. The device was lying. Capnography and arterial blood gas told the truth. This happens more than it should.
Get the Full Details

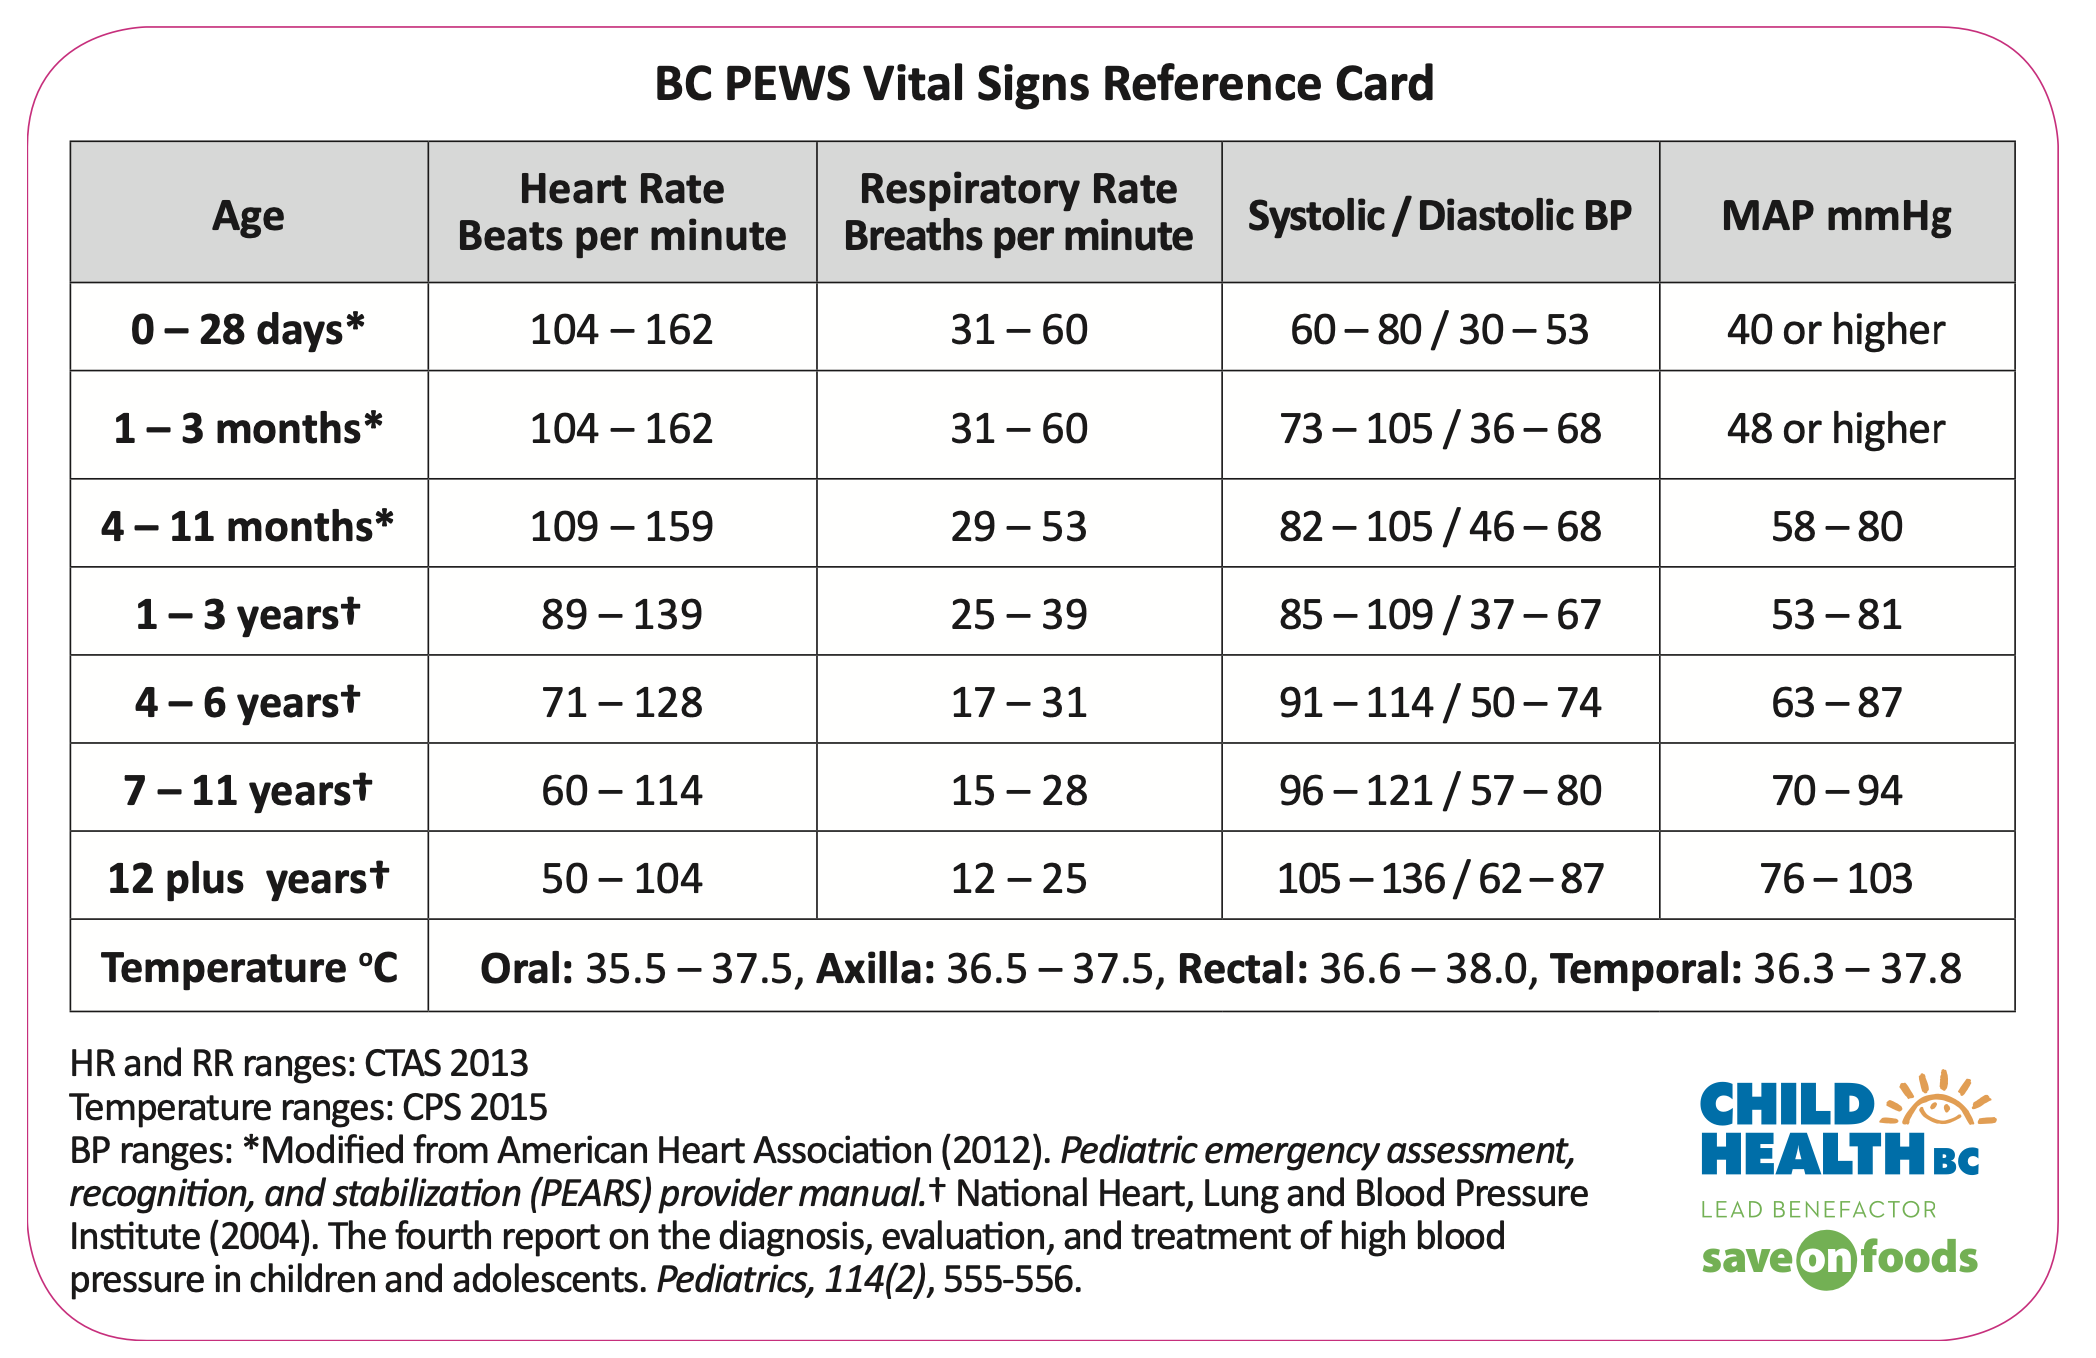
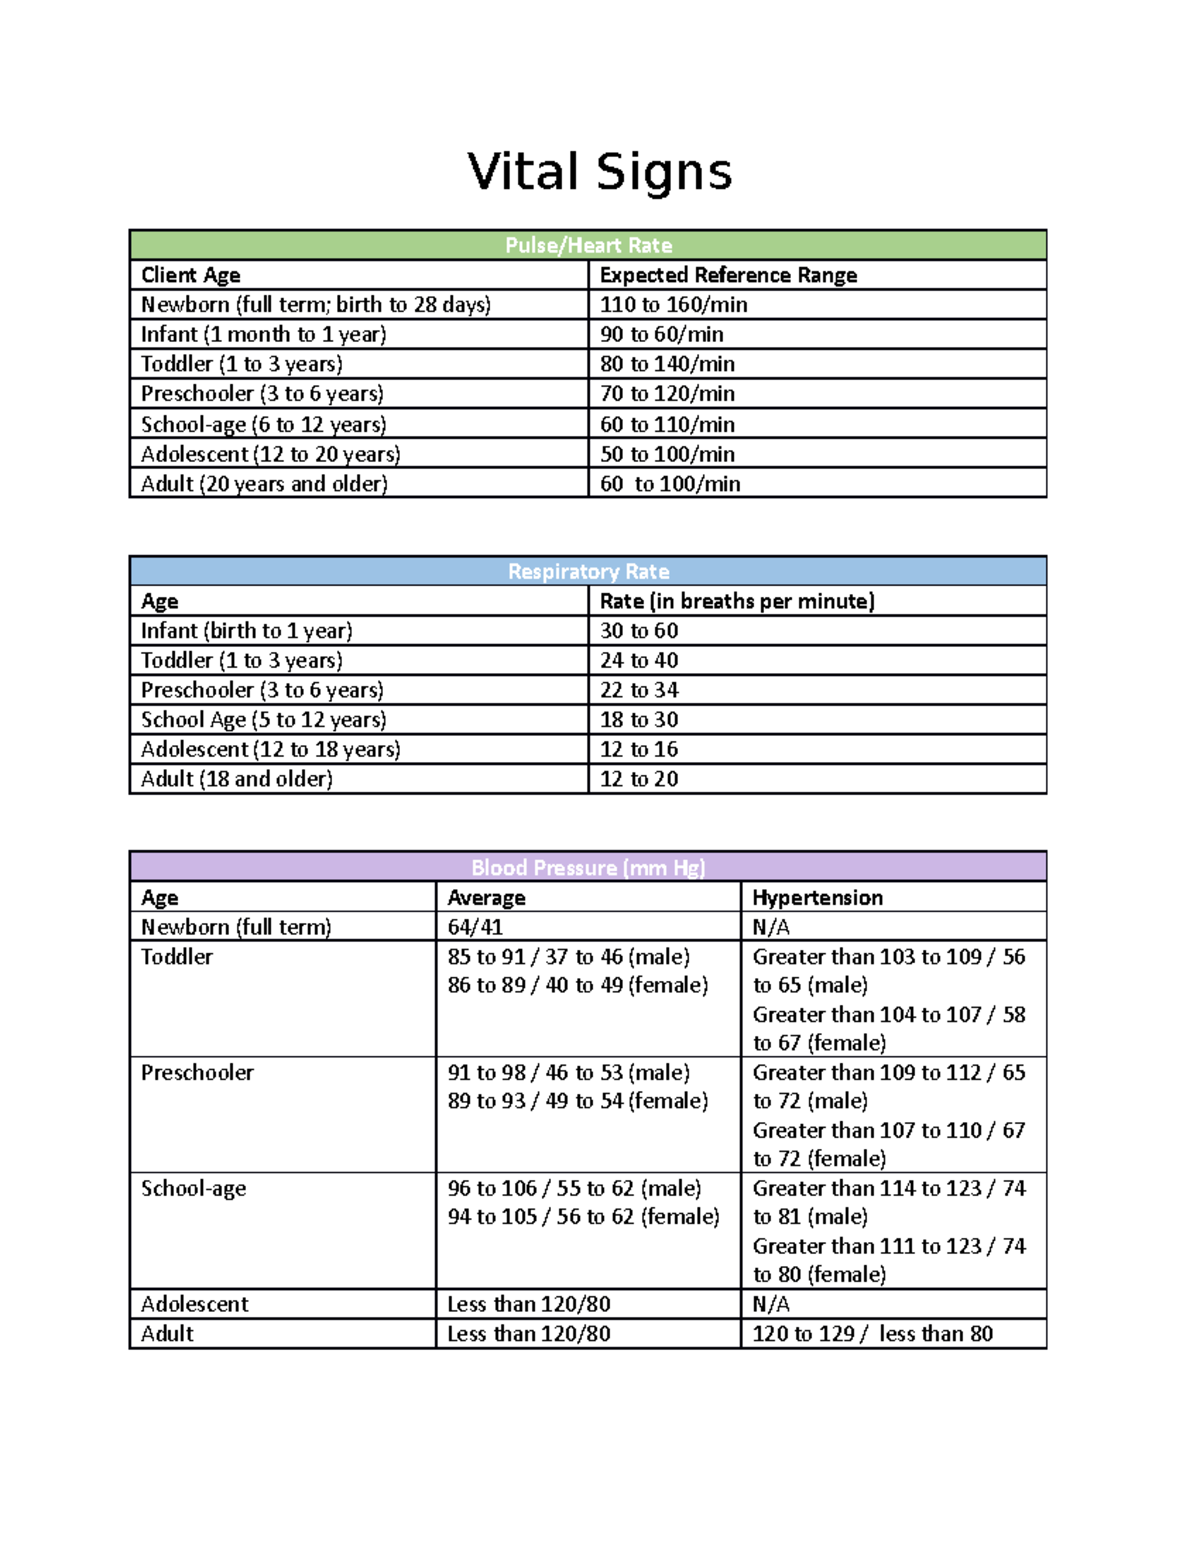
There are also age-related adjustments most people skip. Pediatric respiratory rates are meaningfully higher. Neonates breathe 30 to 60 times per minute normally. Toddlers sit around 24 to 40. The adult range of 12 to 20 does not apply until late adolescence. I keep a quick pocket card with pediatric norms. It saves time and prevents overreacting to normal adolescent or child numbers.
The Edge Case I Still Think About
A few years back I was covering a medical floor and saw a post-op abdominal surgery patient flagged for a "fever" of 38.1 degrees Celsius. The initial workup ran through. Cultures drawn, chest imaging ordered, antibiotics considered. Then someone rechecked the temperature axillary with a fresh probe and got 37.2. The original reading had been pulled from a chart entry where the nurse had logged the temperature earlier that shift after the patient had just received a warm IV fluid bag and was wrapped in thermal blankets. The patient was afebrile. The workup was unnecessary. The cost was mostly time and patient anxiety, but it could have been worse if we had escalated care based on a bad number. The workaround I put in place was simple. Require the measurement site, the device type, and the patient position on the vitals flow sheet. Anything missing gets flagged back for recheck before it enters the problem list. It takes forty seconds per entry and prevents about half the avoidable workups I was seeing.
Where These Ranges Fail You
Here is what nobody puts on the laminated poster in the break room. Normal ranges assume a steady state. Acute illness breaks that assumption constantly. A patient can be inside the textbook bands and still be critically ill. Early shock frequently presents with a compensatory tachycardia and preserved blood pressure until it does not. By the time the numbers move outside range, you have already lost the early window. Chronic conditions shift baselines. A patient with long-standing hypertension may run symptomatic at 130 over 85 because their autoregulation curve has shifted right. The number is "normal" by standard tables but pathologic for that individual. Conversely, a young athlete with naturally low blood pressure may feel fine at 90 over 60. Same number, different meaning.
Pregnancy changes everything. Blood pressure drops in the first and second trimesters, respiration rate climbs slightly, and heart rate increases by about ten to twenty beats per minute. Using non-pregnant reference ranges here leads to missed preeclampsia diagnoses and unnecessary panic about benign physiologic changes. The other honest limitation is that most commercial monitors are calibrated for adults and fail gracefully in extreme populations. Pediatric and bariatric patients often get poor SpO2 readings because the algorithm assumes a standard pulse waveform. I have seen saturations drop to 80 percent in morbidly obese patients when the signal quality indicator was flashing red. Ignoring that flag costs lives. If you want tighter guidance, look at population-specific references. The Pediatric Advanced Life Support guidelines have age-stratified vital sign norms that are actually useful. For blood pressure in children, use percentiles by height and sex instead of fixed numbers. The American Heart Association published updated pediatric BP tables for a reason. Fixed thresholds do not work there.
A Few Practical Notes That Actually Help
Rest the patient for five minutes before taking a blood pressure. Legs uncrossed. Back supported. Arm at heart level. Cuff size matters more than people admit. A too-small cuff inflates the reading by ten to forty millimeters of mercury. I see wrong-cuff hypertension more often than I would like to confess publicly. Standardize the timing. Vitals taken immediately after transport, after pain medication, or during a noisy conversation are less useful. I schedule routine vitals thirty minutes after morning meds and before physical therapy when possible. The variability drops noticeably. Track trends, not snapshots. Three readings over twelve hours tell you more than one reading pulled from a different context. Paper flow sheets are better than dropdown menus that let you backdate and edit after the fact. Audit trails catch charting errors that otherwise slide through.
The takeaway is not that normal ranges are useless. They are a starting frame, not a diagnosis. The skill is knowing when a number is an outlier worth chasing, when it is a normal variant, and when it is an artifact. That judgment comes from seeing enough patients to recognize the patterns, not from memorizing a table. The table is there so you do not miss the obvious. It is not there so you stop thinking when you hit it.