The Chart Isn't the Whole Story
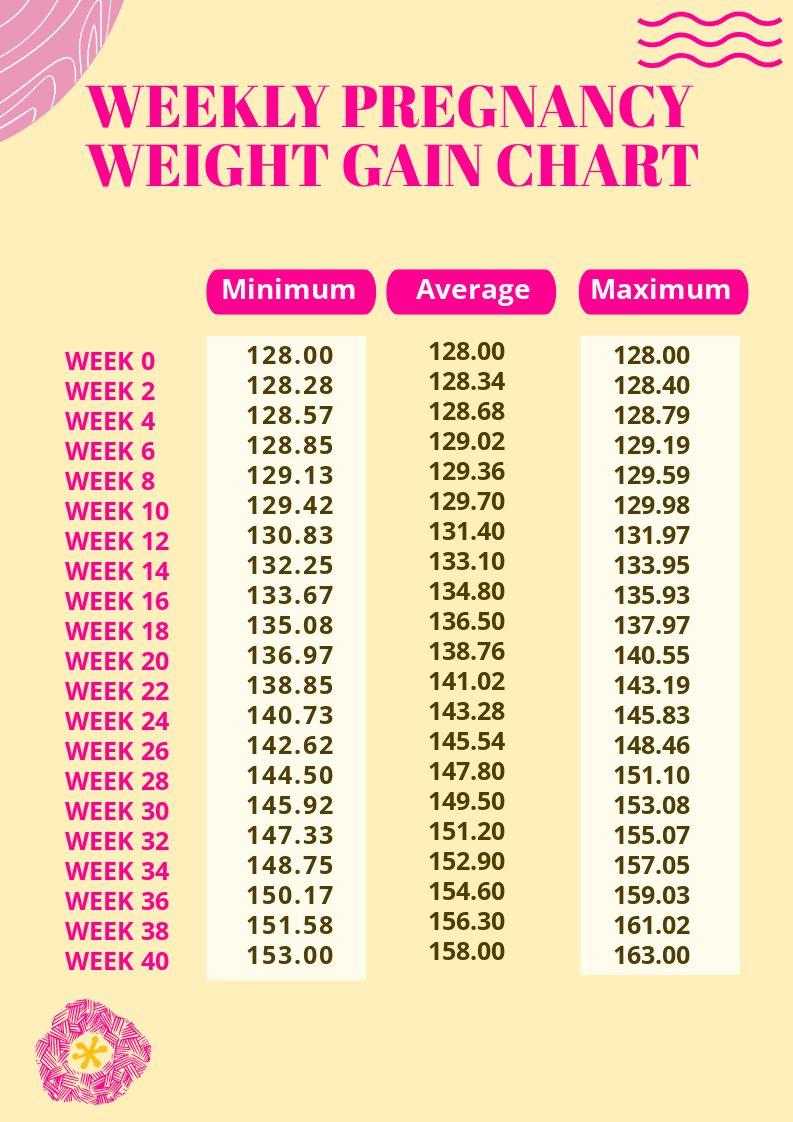
Pregnancy weight gain charts sound straightforward, but most people don't realize they're built on a single number from months ago and a statistical average that might not apply to their body at all. I have spent years reviewing prenatal records, and the charts get used as gospel even when they clearly don't fit the person holding them. The Institute of Medicine published the current guidelines in 2009, and they remain the primary reference point across the US. Your pre-pregnancy BMI determines which category you fall into, and that category then gives you a total weight range for the entire pregnancy. Simple enough on paper. Here is what actually happens in a clinic. A patient comes in at her first visit, the nurse weighs her, calculates the BMI, and checks off a box. That box becomes the track she is expected to follow for the next thirty-something weeks. But the chart does not account for hyperemesis gravidarum, fluid retention conditions, or a patient who genuinely was underweight before pregnancy and gained nothing in the first trimester because she could not keep food down. I had a case where a woman with a normal pre-pregnancy BMI lost four pounds in her first twelve weeks due to severe morning sickness. The chart said she was behind. Her provider said she was off-track. She was not. She caught up by week twenty-two and delivered a healthy baby at the lower end of her range. The chart was wrong for her situation, not the other way around.
How to Read the Weight Gain Chart While Pregnant
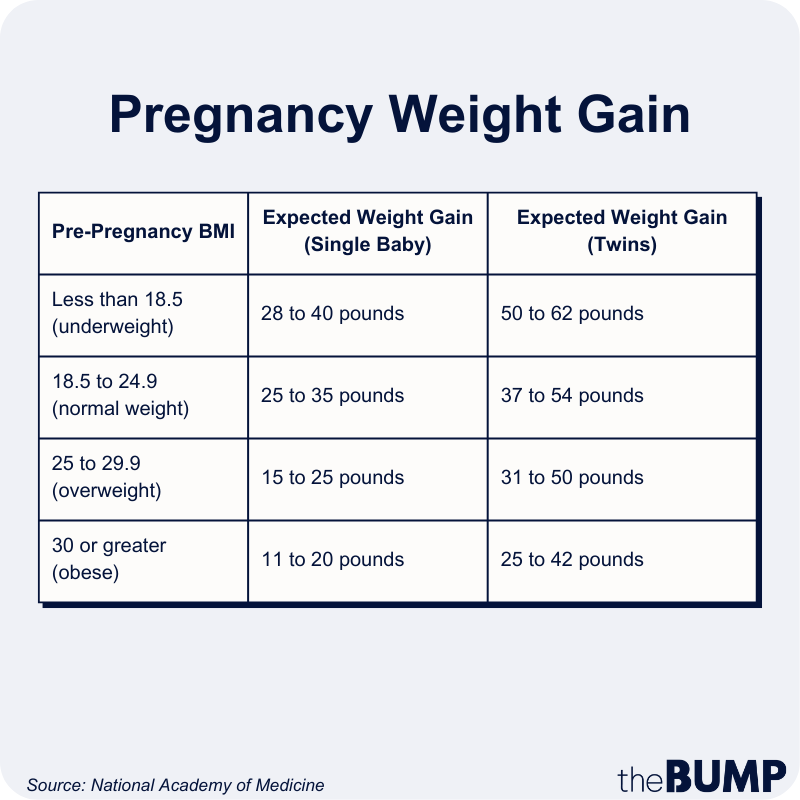
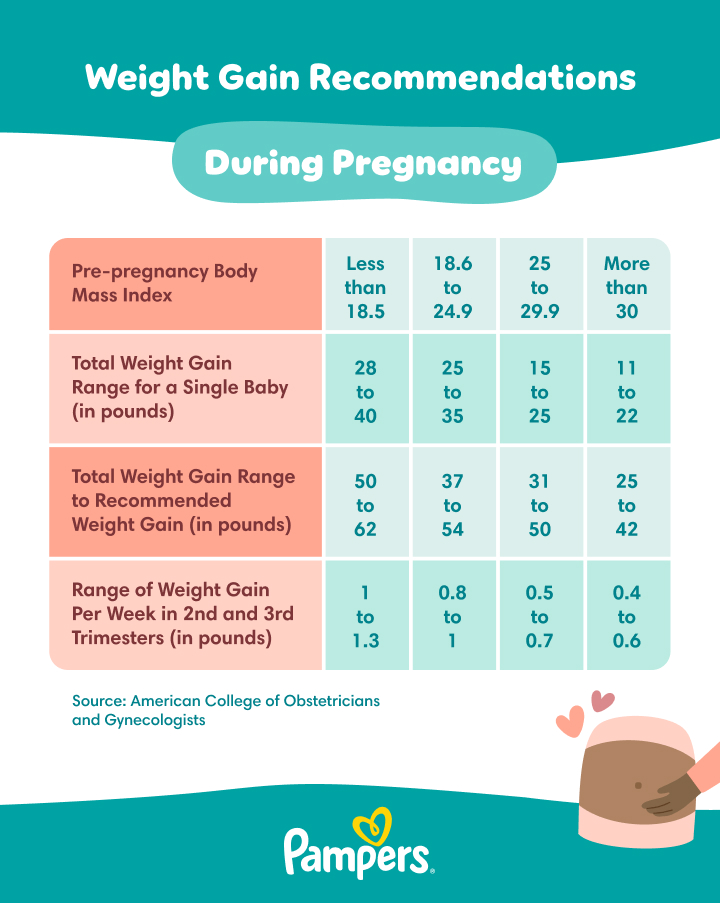
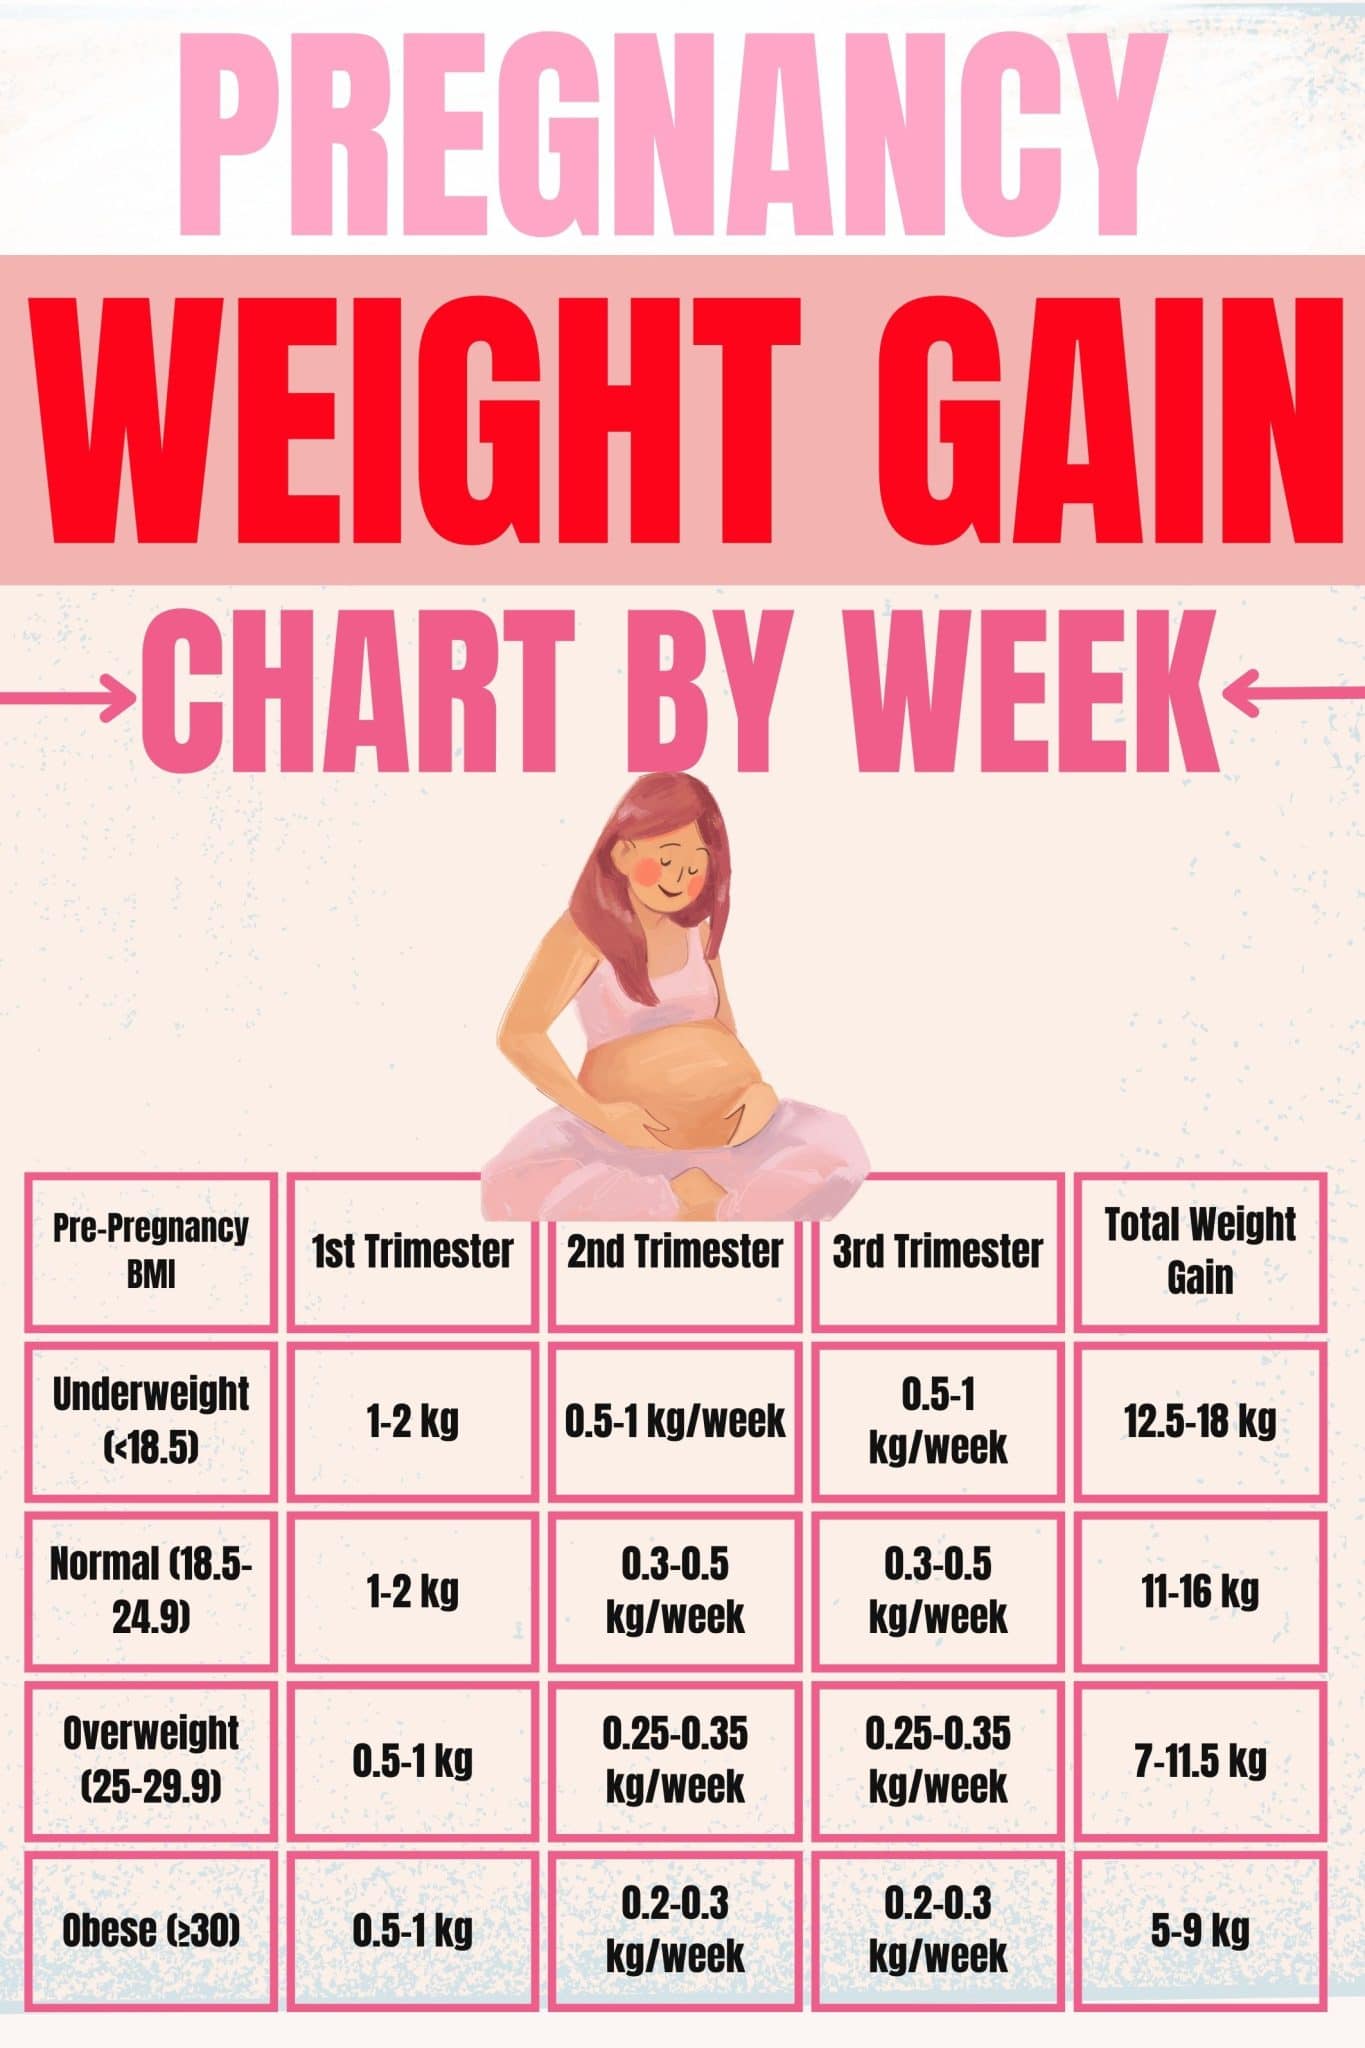
Underweight (BMI under 18.5): The recommended total gain is 28 to 40 pounds over the full pregnancy. That breaks down to roughly one pound per week starting in the second trimester. Normal weight (BMI 18.5 to 24.9): The target range sits between 25 and 35 pounds total. About 0.8 to 1 pound per week in the second and third trimesters is the standard expectation. Overweight (BMI 25 to 29.9): Recommendations drop to 15 to 25 pounds total. You are looking at roughly 0.5 to 0.7 pounds per week once the second trimester starts.
Obese (BMI 30 or higher): The suggested range is 11 to 20 pounds. This translates to about 0.4 to 0.6 pounds per week in the later stages. These numbers assume a singleton pregnancy. They do not account for multiples. Twins sit in a different bracket entirely, usually at the 37 to 54 pound range depending on the source you trust. The IOM revised its guidelines for twins in a 2018 update, and the ranges shifted noticeably. Most people asking about this chart are carrying one baby, but if your scan shows more than one, the standard table is not the right tool.
Get the Full Details
The Mechanism Behind the Numbers
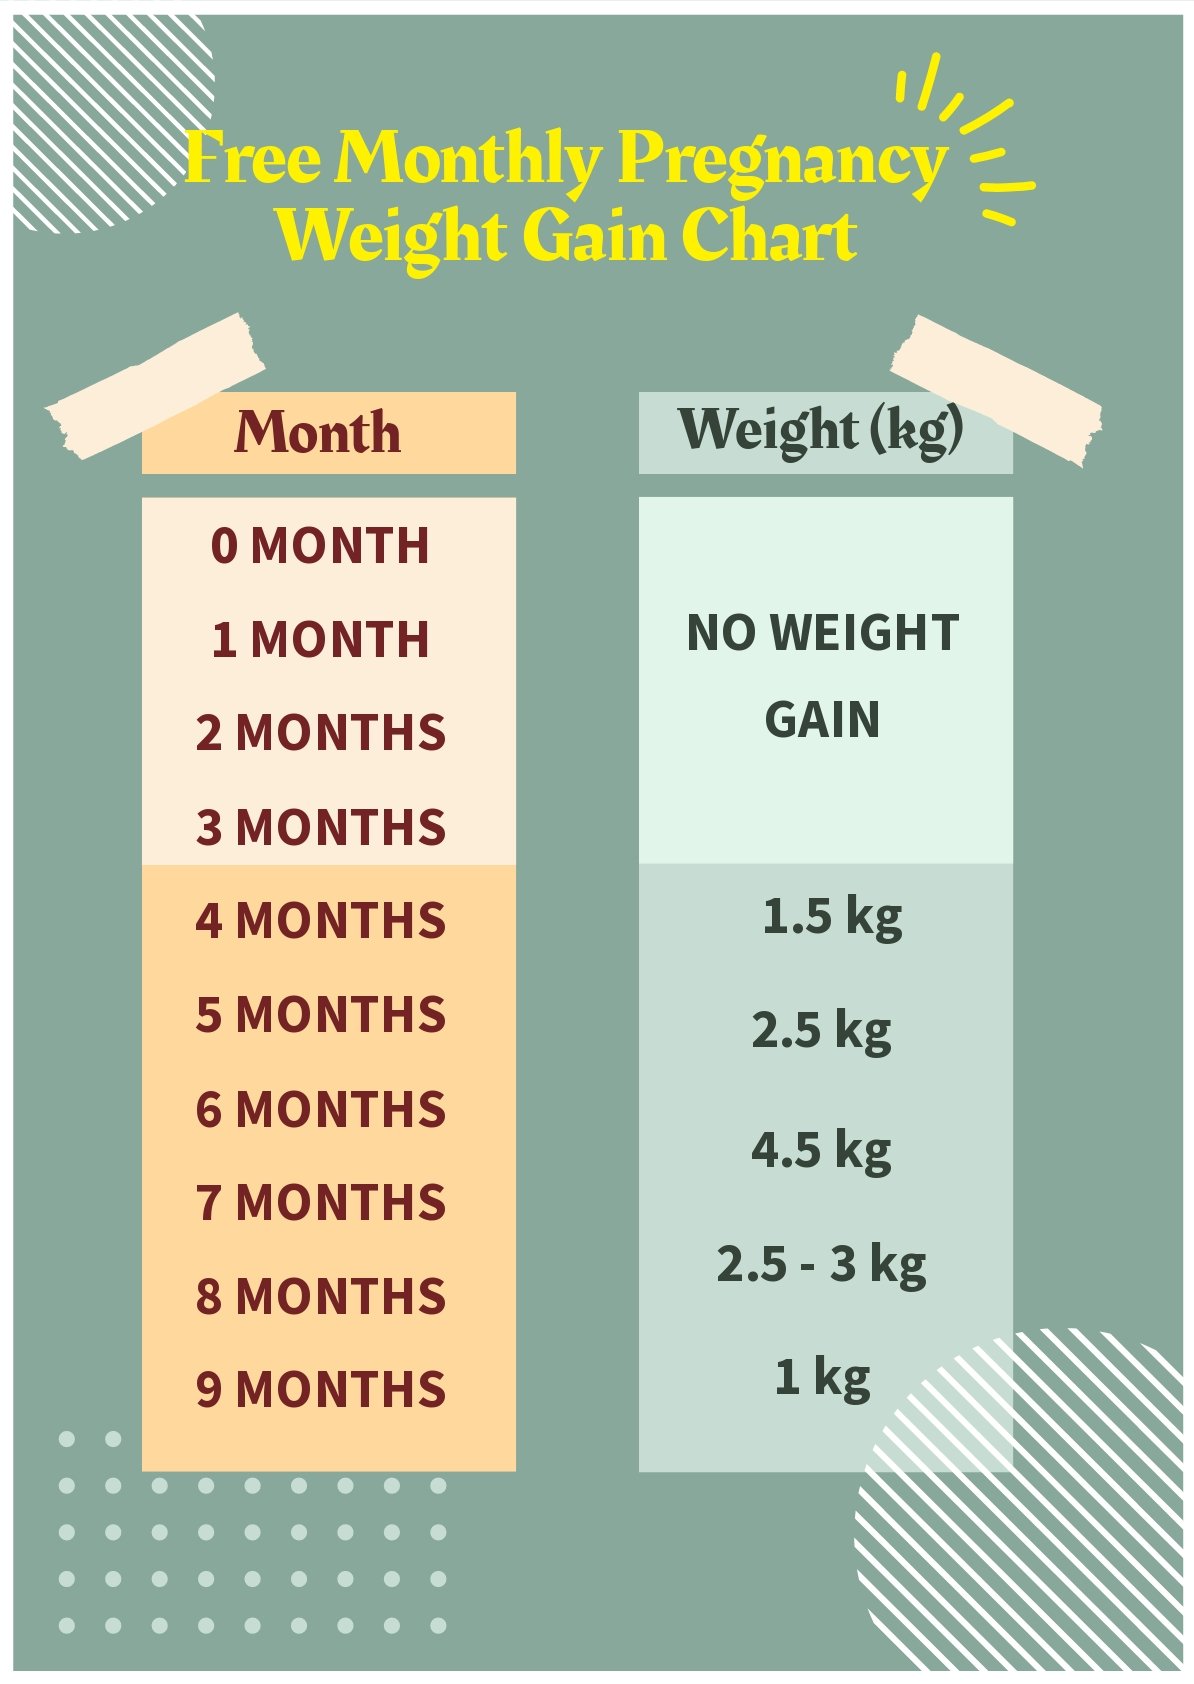
Weight gain during pregnancy is not just baby weight. A full-term singleton pregnancy distributes weight across tissue and fluid in a way that most people do not consider. The baby itself averages about seven to eight pounds. The placenta adds another one to two pounds. Amniotic fluid contributes roughly two pounds. The uterus grows by about two pounds, and breast tissue increases by about one and a half pounds. Blood volume expands by approximately four pounds, and extracellular fluid adds another two. Then there is the maternal fat and protein stores, which account for six to eight pounds of the total. When you add those components together, the 25-to-35-pound range for a normal-BMI pregnancy stops looking arbitrary. It is actually a rough sum of everything the body needs to support gestation and prepare for lactation. The distribution shifts across trimesters. In the first trimester, total gain is usually minimal, often between zero and four pounds for most people. This is the period where individual variation is highest because nausea, food aversions, and hormonal changes make steady gain unrealistic for many. By the second trimester, the rate picks up. The third trimester is where the bulk of the weight accumulates, and this is also where complications become visible in the data. Sudden spikes in weekly gain often signal fluid retention rather than healthy tissue growth, which is why providers watch the slope of the curve more closely than the absolute number.
Where the Chart Breaks Down
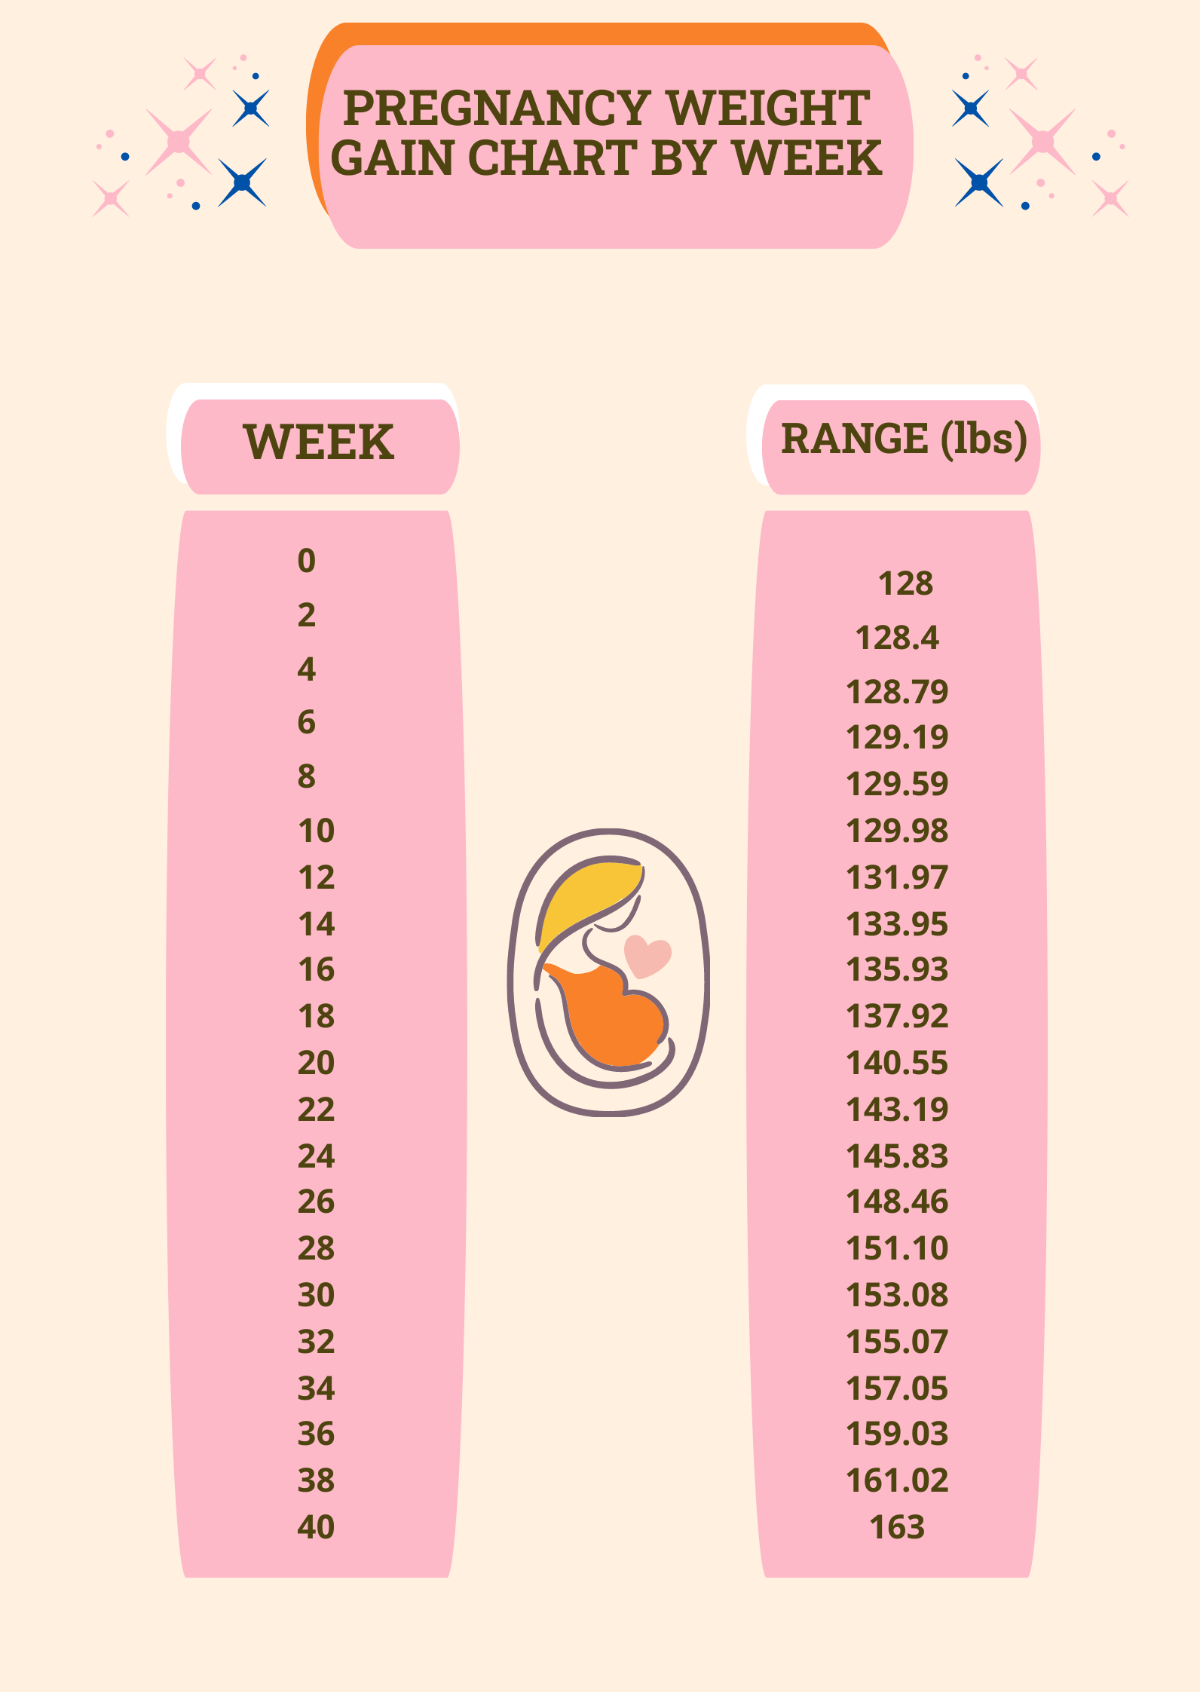
The biggest issue with using a Weight Gain Chart While Pregnant is that it treats every pregnancy as a linear progression, and pregnancy is not linear. I worked through a scenario last year involving a patient whose provider flagged her for excessive gain at week thirty-two because she had put on three pounds in a single week. The chart made it look alarming. In reality, she had attended a wedding the weekend before, the event included a lot of standing and social walking, and she had noticed her rings were tight and her ankles looked swollen. She was retaining fluid, not gaining fat. The chart could not distinguish between the two. What actually helped was switching to a weekly trend view instead of fixating on any single data point, and adding a simple log of swelling and blood pressure readings so the provider could see the pattern over time rather than reacting to one outlier measurement. Another edge case that catches people off guard involves gestational diabetes management. When blood sugar is being tightly controlled, some patients actually gain less weight than the chart recommends, sometimes because dietary changes are aggressive or because insulin therapy alters metabolism in ways the standard table does not predict. I have seen patients with well-managed gestational diabetes who sat at the very bottom of their recommended range and delivered perfectly healthy babies. The chart would have labeled that insufficient gain if you looked at it in isolation. The workaround is to pair the weight data with fetal growth ultrasounds, which give you a much clearer picture of whether the pregnancy is progressing appropriately than the chart alone ever could.
Counter-Intuitive Things Most People Miss
The first thing most people do not realize is that early weight gain matters less than late weight gain. A patient who gains nothing in the first trimester but follows the curve perfectly from week fourteen onward typically has a better outcome than someone who hits every target early and then stalls out completely in the third trimester. The fetus does most of its growth in the last twenty weeks, so the later trajectory carries more predictive weight for birth outcomes than the early numbers. The second thing is that the chart assumes a certain pattern of muscle and fat storage that does not apply to everyone. Athletic women or those who lift heavy regularly may carry more lean mass, which shows up differently on the scale than the same amount of fat. The chart cannot see body composition. It only sees total mass. If you are an active person who has maintained muscle through pregnancy, you might be on the higher end of your range without having excess fat, and the chart will misread that as a problem. Monitoring waist circumference trends alongside weight can give you a better signal than the scale alone, though even that metric has limits in pregnancy because the expanding uterus makes waist measurement somewhat meaningless past the first trimester.
Practical Use of the Chart
To actually use this effectively, start with your pre-pregnancy weight. If you do not have a recent number, use the weight you had at your earliest available checkup and treat that as your baseline. Calculate your BMI by dividing your weight in kilograms by your height in meters squared, or use any standard BMI calculator if imperial units are more familiar to you. Match your BMI to the IOM categories above, and write down your target range. Then track your weight weekly at the same time of day, preferably in the morning before eating, wearing similar clothing each time. Consistency matters more than precision. A difference of two pounds between morning and evening weigh-ins is normal and has nothing to do with actual tissue gain. Inputting your data into a spreadsheet lets you plot the trend line and compare it against the recommended weekly rate, which makes deviations visually obvious within a couple of weeks rather than requiring you to remember every number by heart. I prefer this approach because clinic visits often happen every four weeks in the second trimester, and that is a long gap where small issues can accumulate before anyone notices them on paper.
Limitations You Should Accept Up Front
The chart is a population-level tool, and populations are messy. It was derived from observational data spanning several decades and represents statistical averages, not individualized targets. It does not account for racial and ethnic differences in body composition, it does not adjust for pre-existing metabolic conditions, and it does not adapt to pregnancies complicated by chronic hypertension or kidney disease. In those scenarios, your provider will likely give you different guidance anyway, and the standard chart becomes decorative at best and misleading at worst. The chart also cannot tell you whether the weight you are gaining is appropriate for your specific situation. It gives you a range, not a diagnosis. If you are gaining significantly below or above your range, the chart will flag it, but it will not explain why. That requires a clinical evaluation that looks at blood pressure, urine protein, fetal growth measurements, and dietary intake. Relying on the chart as a substitute for those assessments is a mistake I see regularly in prenatal records, and it is the kind of mistake that can delay intervention when intervention is actually needed. If the chart feels like it is not working for you, the most practical alternative is to shift the conversation with your provider toward functional metrics rather than absolute numbers. Fetal growth ultrasounds, fundal height measurements, and symptom tracking tend to give you more actionable information than a single weight figure compared to a static table. The chart is a starting point, not a verdict.