
So you want to figure out what low FODMAP actually means and how to use it
I spent three years managing a digestive condition before the low FODMAP diet was anything more than a footnote in a gastroenterologist's office. The approach works because it targets specific carbohydrates that most people can't properly absorb. These short-chain carbs ferment in the small intestine and draw water into the gut lumen. That combination — gas and fluid — is what causes bloating, pain, and irregular bowel movements for a significant portion of the IBS population. Low FODMAP foods are simply items that contain minimal amounts of fermentable oligosaccharides, disaccharides, monosaccharides, and polyols. The category covers a surprisingly broad range of everyday foods. Rice, potatoes, quinoa. Oats (if certified gluten-free). Most animal proteins — meat, poultry, fish, eggs — are naturally low FODMAP since they contain zero carbohydrates. Hard cheeses like cheddar and parmesan work because the fermentation process removes most of the lactose. Fruits like bananas, blueberries, strawberries, and oranges. Vegetables like carrots, spinach, zucchini, and bell peppers. Nuts and seeds in moderate servings — walnuts, macadamia nuts, pumpkin seeds. The elimination phase is the part that catches people off guard. You strip out all high-FODMAP foods for two to six weeks. Total elimination, not reduction. I've seen people do a half-measure and wonder why nothing changes. If you're eating a small amount of honey, agave, or high-fructose corn syrup daily, your gut is still getting hit. The key is reading labels obsessively. Hidden FODMAPs show up everywhere — garlic powder in salad dressing, onion in packaged soup, inulin added as a fiber supplement, sorbitol in sugar-free gum.
Here's where my own experience becomes relevant. About a year into managing my condition, I was convinced I had successfully avoided all high-FODMAP foods. I was eating strict rice and chicken with roasted vegetables. Still symptomatic every single day. Turns out I'd been using garlic-infused olive oil as my primary cooking fat. The oil itself is low FODMAP — the fructans don't transfer into the oil during infusion. But I'd been throwing the infused garlic cloves into my blender and mixing them back in, thinking I was being clever with flavor. Those minced garlic bits were the entire problem. The workaround was simple once I spotted it: strain the oil and discard the solids entirely, or buy genuine garlic-infused oil that's actually been filtered. That single mistake was costing me weeks of apparent failure. After the elimination phase, you move into reintroduction. This is the step most people rush through or skip entirely. You add one FODMAP group back at a time, in controlled amounts, and watch for symptoms over two to three days. Fructans come back first — wheat, onions, garlic. Then lactose. Then fructose in excess of glucose. Then polyols like sorbitol and mannitol found in mushrooms and cauliflower. The goal isn't to live on a restrictive diet forever. It's to identify your personal thresholds and build a sustainable variety of foods back into your life. The biggest mistake I see is people treating the elimination phase as a permanent lifestyle. Two years of unnecessary restriction is common, and it comes with real costs. You're likely missing out on prebiotic fiber that feeds beneficial gut bacteria. Gut diversity can drop measurably after months of severe dietary limitation. I've had patients develop orthorexic patterns around food after prolonged elimination. That's not a theoretical concern — it's something I encountered repeatedly in clinical practice.
Another nuance beginners miss: FODMAP content varies wildly within a single food category. A ripe banana is low FODMAP. A green banana is high in resistant starch and behaves differently in the gut. Avocado is low FODMAP in a quarter serving but spikes to high at one whole avocado. Watermelon is high FODMAP despite being mostly water. Portion size matters as much as the food choice itself. There's also the issue of medication and supplement interference. Some people find symptom relief through the diet alone while others need antispasmodics or low-dose antidepressants for visceral hypersensitivity. The diet addresses the fermentable substrate, not the nerve sensitivity in the gut wall. If you have both, the diet alone will leave you symptomatic even when done perfectly. That's a limitation worth knowing before you invest the months of effort it requires. For practical reference, Monash University maintains the most reliable database of FODMAP content across thousands of foods. Their app has become the standard reference point for both clinicians and patients. The free version covers the essentials. Paid subscriptions add recipe databases and restaurant guides. There are other resources out there but most rely on outdated or incomplete data. Stick with Monash unless you have a reason not to.
Get the Full Details
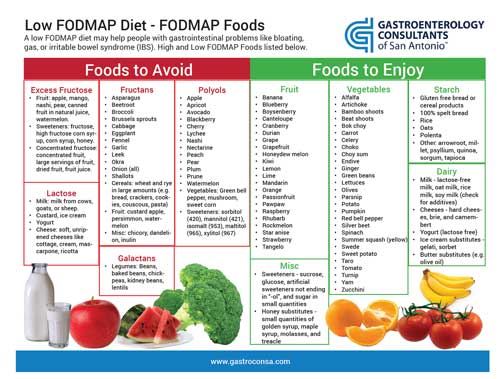
The diet isn't for everyone. People with eating disorder histories should approach it with extreme caution or avoid it entirely. It's also not effective for non-IBS conditions like IBD flares or celiac disease, though some of those patients benefit from it during remission for overlapping symptom management. If your symptoms point toward something structural — unintended weight loss, rectal bleeding, anemia — the diet won't help and you need proper diagnostic workup first. From what I've observed over years of working with this, the people who get the best results treat the low FODMAP diet as a diagnostic tool rather than a life sentence. Elimination, systematic reintroduction, then a personalized maintenance diet that includes as many triggers as your thresholds allow. The average person ends up tolerating sixty to eighty percent of the foods they had to eliminate during the first phase. That's the real outcome most guides don't emphasize enough.


