Kidney Function Basics
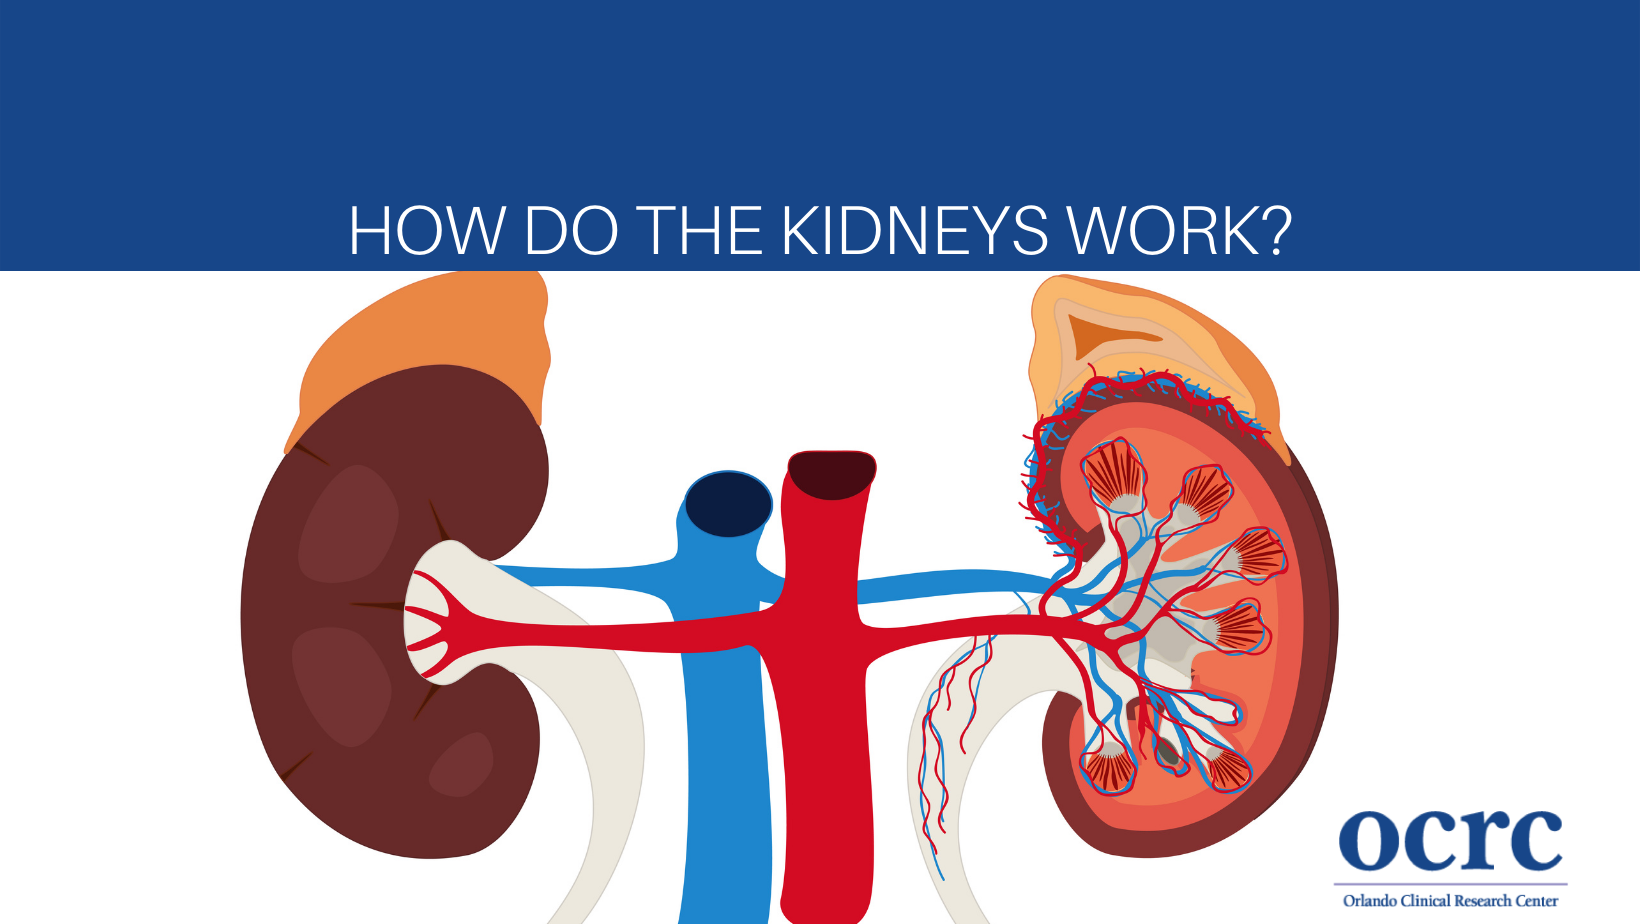
The kidneys filter about 180 liters of blood daily, removing waste products and excess fluid while maintaining electrolyte balance. They produce roughly 1-2 liters of urine per day through a combination of glomerular filtration, tubular reabsorption, and tubular secretion. Most people have two kidneys located on either side of the spine below the rib cage, each weighing around 150 grams. When I first started working in nephrology, I underestimated how much clinical information you can extract from basic kidney function tests. A patient's creatinine level alone tells you very little without considering age, muscle mass, and race. I learned this the hard way when I dismissed elevated creatinine in an elderly woman because her baseline was always borderline high due to low muscle mass. By the time we investigated properly, she had already progressed to stage 4 chronic kidney disease.
What Does The Kidney Do Beyond Filtering
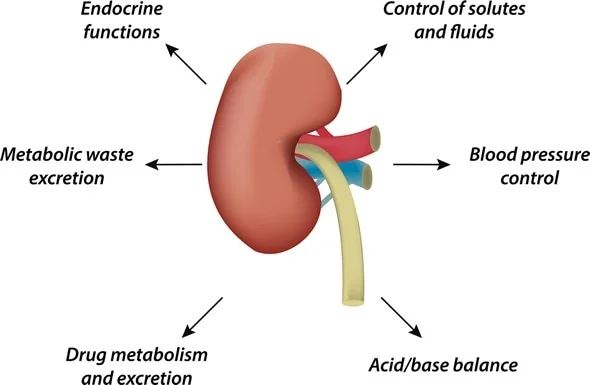
Beyond waste removal, kidneys regulate blood pressure through the renin-angiotensin-aldosterone system. They activate vitamin D for calcium absorption and produce erythropoietin for red blood cell production. When kidney function declines, patients often develop anemia and bone disease before experiencing obvious swelling or fatigue. This delayed presentation is why routine blood work matters more than symptom monitoring. The nephron, the kidney's functional unit, contains approximately one million structures per kidney. Each nephron has a glomerulus for filtration and a tubule for reabsorption. The proximal tubule reclaims about 65% of filtered sodium and water, while the loop of Henle creates a concentration gradient in the medulla. Distal tubules and collecting ducts fine-tune electrolyte balance under hormonal control from aldosterone and antidiuretic hormone.
Common Misunderstandings About Kidney Health
Many people believe drinking excessive water protects kidney function. This assumption ignores the kidney's ability to concentrate urine up to 1200 mOsm/L. Overhydration actually dilutes electrolytes and provides no additional protection against kidney damage. I've seen patients develop hyponatremia from water fasting attempts, thinking they were "detoxifying" their kidneys. Another frequent misconception involves NSAID use and kidney damage. Ibuprofen and naproxen reduce prostaglandin synthesis, which can decrease renal blood flow by 30-40% in susceptible individuals. Patients with existing kidney disease, heart failure, or dehydration face the highest risk. The FDA requires warning labels on these medications, yet many physicians fail to discuss this risk during prescriptions. Contrary to popular belief, creatinine supplements do not harm healthy kidneys in standard doses. However, bodybuilders consuming 5-10 grams daily may see artificial elevations in creatinine without actual kidney damage. This happens because creatine converts to creatinine non-enzymatically. Distinguish between supplementation effects and pathological elevation by monitoring cystatin C alongside creatinine.
Get the Full Details

When to Actually Worry About Kidney Function
Stages 1-3 chronic kidney disease often progress without symptoms for years. A glomerular filtration rate below 60 mL/min for three months defines chronic kidney disease regardless of other findings. Patients with diabetes or hypertension should undergo annual screening with urine albumin-to-creatinine ratio and serum creatinine. Early detection through routine testing identifies disease before irreversible damage occurs. I encountered a particularly difficult case involving contrast-induced nephropathy during a cardiac catheterization. The patient's baseline creatinine was 1.4 mg/dL, suggesting stage 2 kidney disease. We proceeded with hydration protocols but still experienced a 45% increase in creatinine post-procedure. The workaround involved using iso-osmolar contrast media and delaying the procedure for optimal hydration status. This incident changed our institutional protocol for patients with eGFR below 45. Acute kidney injury often results from hemodynamic changes rather than direct toxin exposure. Prerenal causes account for approximately 70% of hospital-acquired kidney injuries. Dehydration, heart failure, and sepsis reduce renal perfusion, triggering functional changes before structural damage occurs. The key is recognizing reversible causes early and correcting volume status within 6 hours of presentation.
Practical Kidney Protection Strategies
Maintaining blood pressure below 130/80 mmHg slows kidney disease progression by 35% compared to standard targets. ACE inhibitors and ARBs provide additional protection beyond blood pressure control by reducing intraglomerular pressure. Patients with proteinuria above 300 mg/day benefit most from this approach. Monitor creatinine and potassium within 2 weeks of initiating therapy. Diabetic patients should target HbA1c levels between 7-8% rather than strict normalization. Intensive glucose control below 6.5% increases hypoglycemia risk without additional kidney protection in type 2 diabetes. SGLT2 inhibitors like empagliflozin reduce kidney disease progression by 35% independent of glucose lowering. These medications show benefit even in non-diabetic kidney disease with proteinuria above 500 mg/day. Avoid nephrotoxic combinations like NSAIDs plus ACE inhibitors in dehydrated patients. This triple threat increases acute kidney injury risk by 4-fold compared to either medication alone. Patients taking diuretics face additional vulnerability due to volume depletion. The workaround involves monitoring renal function weekly during concurrent therapy and maintaining adequate hydration status.
Advanced Kidney Function Testing
GFR estimation equations vary in accuracy across different populations. The CKD-EPI equation outperforms MDRD in patients above 60 years old and those with GFR above 60 mL/min. Cystatin C-based equations provide better accuracy in patients with unusual muscle mass, such as amputees or vegetarians. Combine both markers when precise dosing decisions depend on accurate GFR estimation. Urine albumin-to-creatinine ratio categorizes kidney disease risk more accurately than dipstick testing alone. Categories range from A1 (normal to mildly increased) to A3 (severely increased above 300 mg/g). Patients with A2 or A3 proteinuria face 2-4 fold increased cardiovascular risk independent of GFR. This association explains why kidney disease predicts heart attacks as strongly as diabetes. Kidney biopsy indications have expanded beyond unexplained kidney failure. Patients with rapid creatinine rise above 0.3 mg/dL within 48 hours warrant investigation for crescentic glomerulonephritis. Early diagnosis through biopsy guides immunosuppressive therapy within 2 weeks of presentation. Delayed biopsy beyond 4 weeks reduces treatment effectiveness for acute inflammatory conditions.

Limits of Current Kidney Disease Management
Kidney transplantation remains the optimal treatment for end-stage kidney disease, yet donor organ availability limits access. Approximately 100,000 patients wait for transplantation in the United States alone. Live donor programs improve outcomes by 15-20% compared to deceased donor transplants. Desensitization protocols enable transplantation in highly sensitized patients with panel reactive antibodies above 80%. Dialysis life expectancy varies significantly based on residual kidney function. Patients maintaining urine output above 500 mL/day survive 25% longer on hemodialysis than anuric patients. This association explains why kidney transplant candidates prioritize preserved renal function over dialysis vintage. Peritoneal dialysis offers additional benefits for patients with cardiovascular instability, reducing hemodynamic fluctuations during treatment. Kidney disease progression rates differ substantially between diabetic and non-diabetic etiologies. Diabetic nephropathy progresses over 10-20 years in most patients, while autoimmune conditions like IgA nephropathy may accelerate to end-stage disease within 5 years. The workaround involves distinguishing etiologies through clinical features and biopsy findings before initiating disease-modifying therapy. Late differentiation reduces treatment effectiveness for rapidly progressive conditions.