So You Need To Understand Hypotonic Solutions
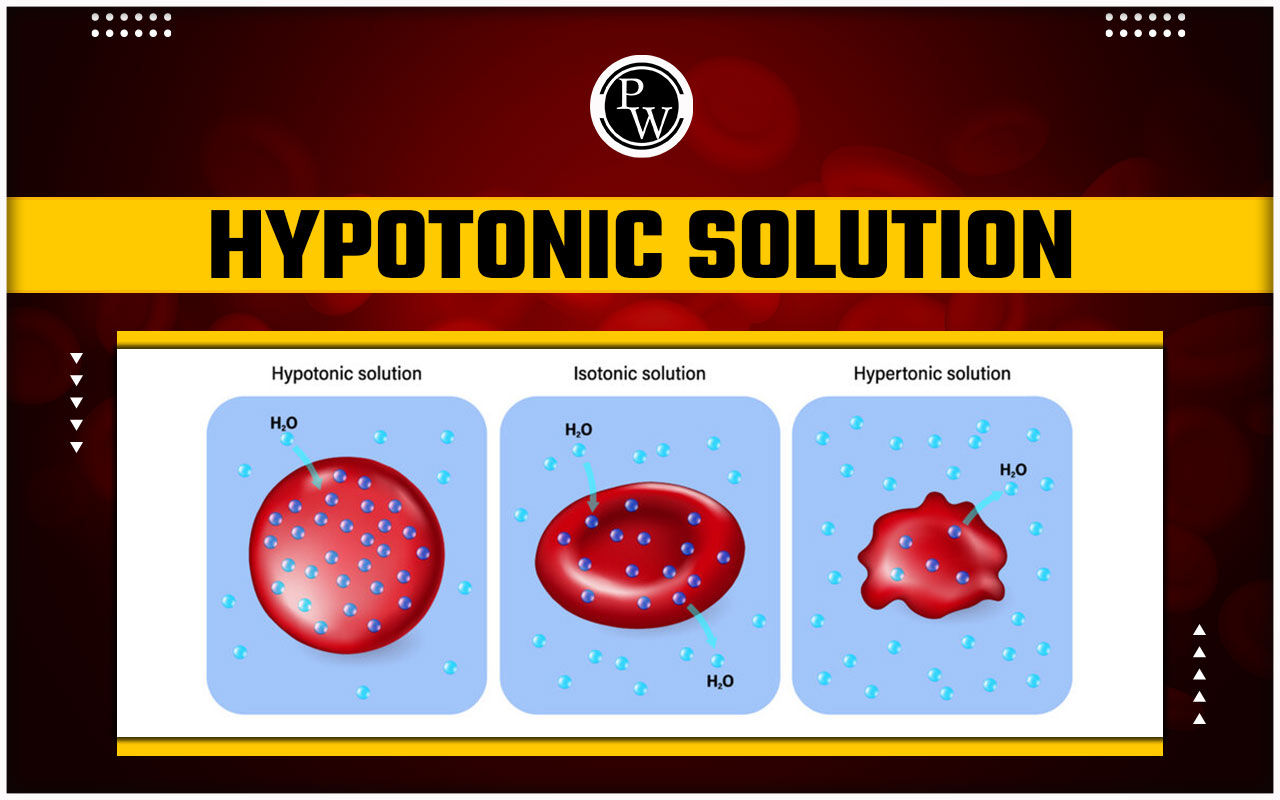
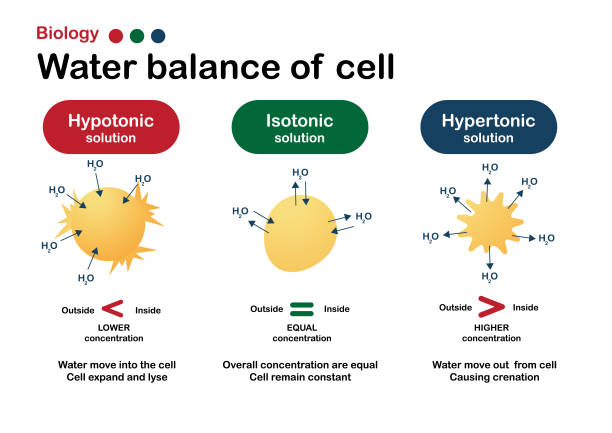
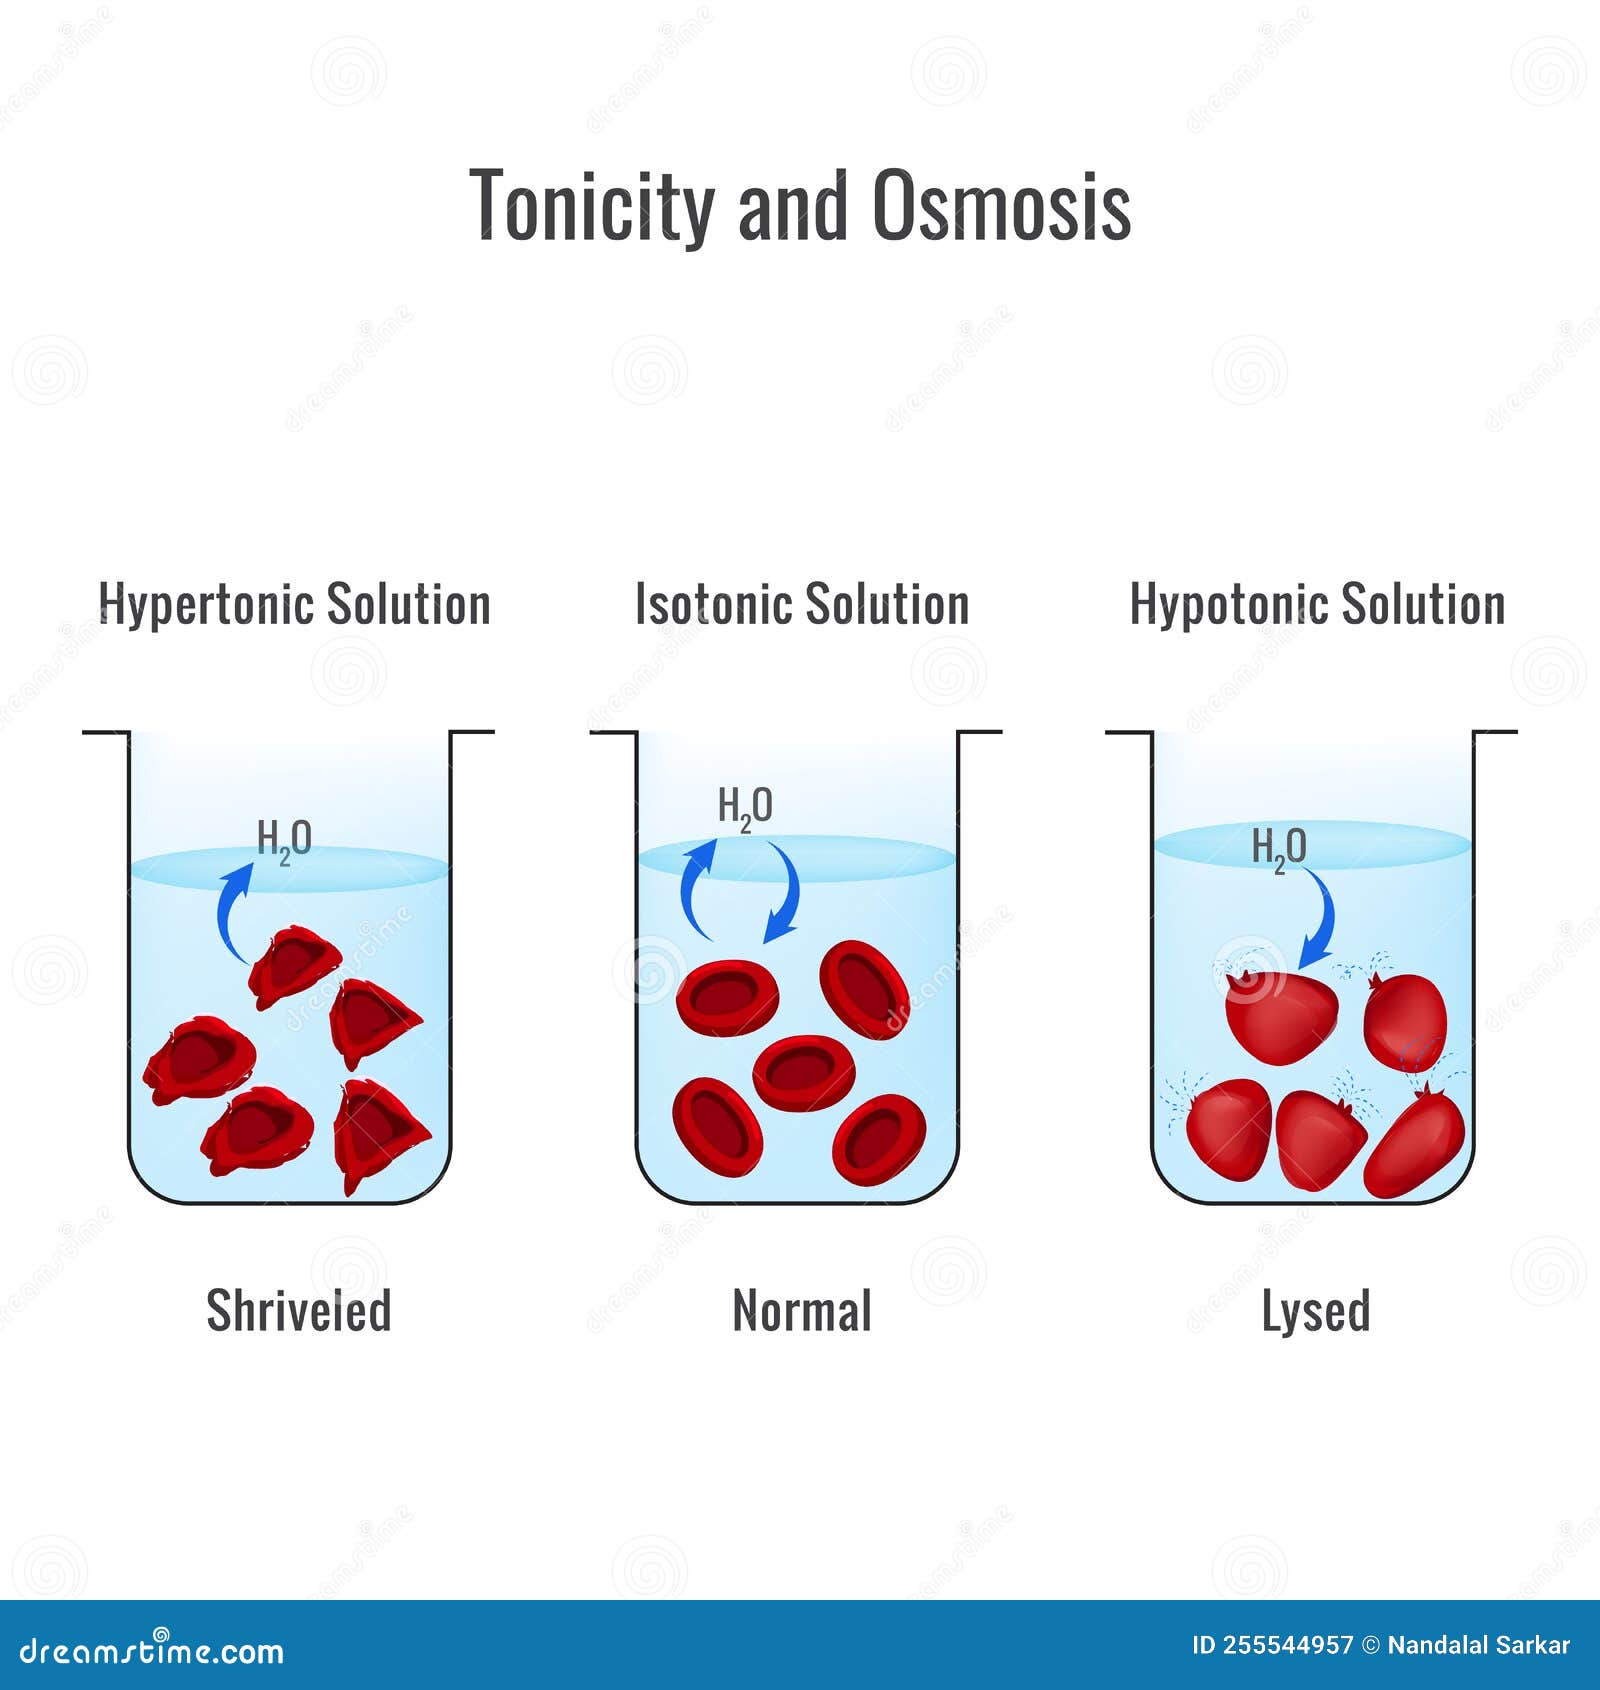
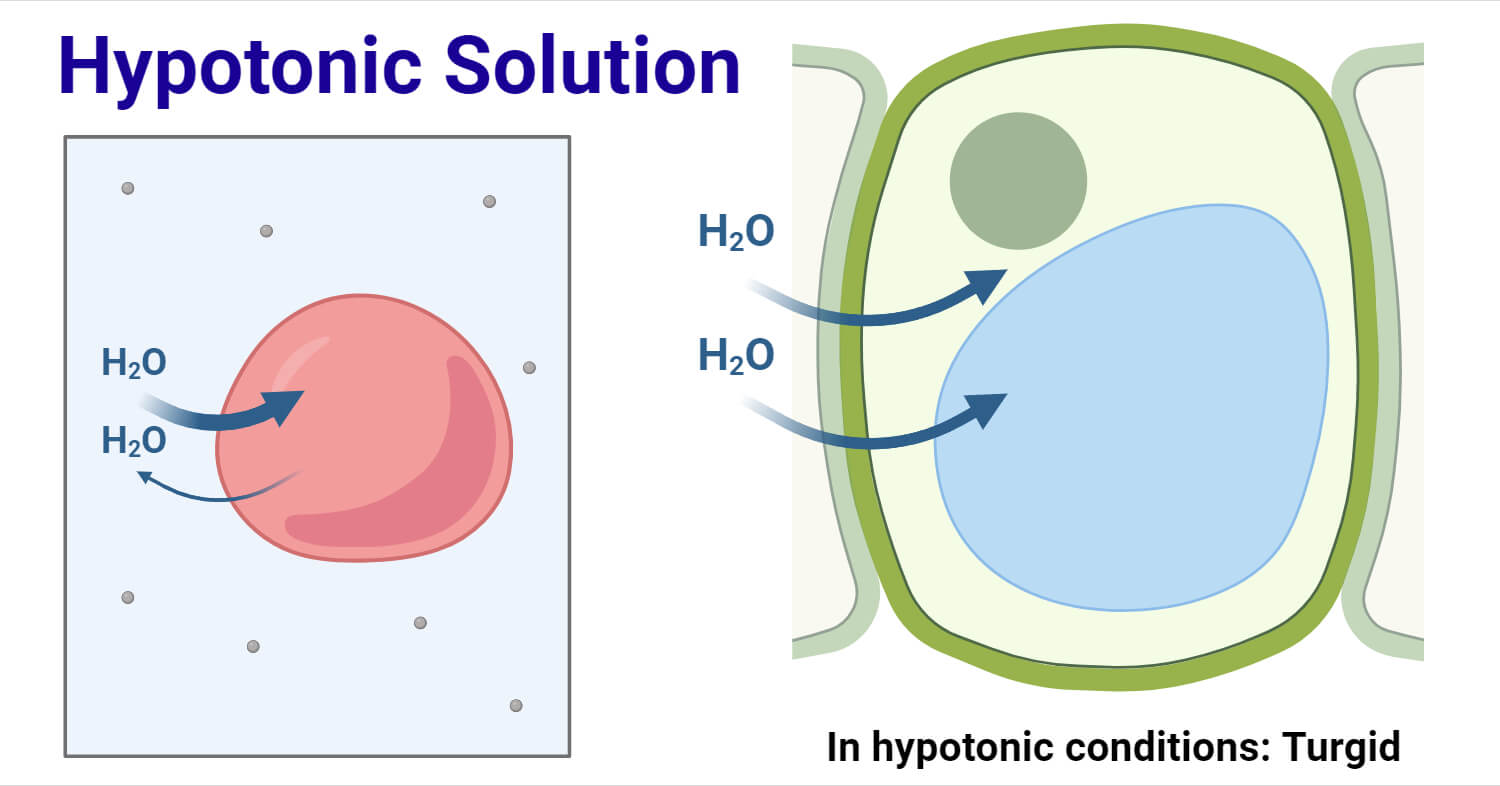
I keep seeing people post questions about this in various study groups and it always comes back to the same confusion: tonicity is not the same as osmolarity, and mixing those up will get you in trouble fast. A hypotonic solution is simply one where the concentration of solutes outside a cell is lower than the concentration inside the cell. Water moves across the membrane toward the higher solute side. That is the whole mechanism. Everything else is just applying it to different contexts. The textbook definition says a hypotonic solution has a lower osmotic pressure than the fluid inside a cell. In practice that means if you put a red blood cell into a 0.3% saline solution, it will swell and eventually lyse. Normal saline for intravenous use is 0.9% NaCl, which is isotonic to blood. Go below that and you are entering hypotonic territory, and the consequences become immediate. I worked in a clinical lab for years and one thing that always caught new techs off guard was the difference between true hypotonicity and what happens when cells are exposed to solutions containing permeant solutes like urea. Urea crosses the cell membrane freely. If you put a cell in a urea solution that is technically hypotonic by osmolarity calculations, the urea enters the cell, osmolarity equalizes, and the cell does not swell the way it would in a NaCl hypotonic solution. The cell actually shrinks initially then swells back as equilibrium is reached. This is why tonicity depends on whether the solute can cross the membrane, not just on the raw concentration numbers.
Another thing nobody warns you about: temperature matters more than most people realize. Osmotic pressure is temperature-dependent. A solution you prepared and labeled as hypotonic at room temperature may shift slightly at body temperature. In most lab work this is negligible, but in precise experiments involving cell viability over extended periods, the drift adds up. I once had a batch of cells showing unexpected lysis rates in what I thought was a standard hypotonic lysis buffer. Turned out the lab HVAC had been down and the solutions were sitting at 22°C instead of the intended 37°C. The osmotic gradient was slightly off. Took me three hours to figure it out.
How It Actually Works In Practice
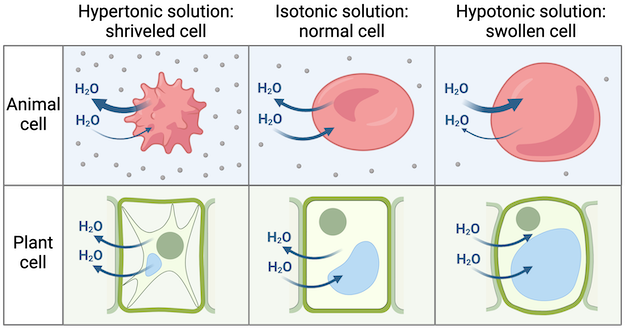
The mechanics are straightforward but easy to screw up if you are not paying attention to detail. Start with the basic principle. Water moves from low solute concentration to high solute concentration through a semi-permeable membrane. In a hypotonic environment the outside has fewer dissolved particles than the inside of the cell. Water rushes in. Animal cells lack a cell wall so they can burst. Plant cells have a rigid wall and just become turgid, which is actually desirable for their structural integrity. When preparing a hypotonic solution for any application, you need to calculate the exact concentration you want relative to your target. For red blood cell hemolysis assays, a common starting point is 0.32% NaCl. But you do not just dump salt into water and call it done. You need to account for the fact that NaCl dissociates into two ions. The effective particle concentration, or osmolarity, is roughly double the molar concentration. That is why 0.9% NaCl is about 308 mOsm/L, which matches blood plasma closely. If you are doing this in a research setting, here is the method that actually works without wasting reagents. First, make a concentrated stock solution. Then dilute it stepwise using calibrated pipettes and volumetric flasks. Never try to make a large volume of dilute hypotonic solution directly from solid salt. The error margins are too large at low concentrations. I usually prepare a 1X working solution from a 10X stock, and then verify the osmolarity with a freezing point osmometer before using it on cells. Takes about five minutes per sample and saves you from repeating experiments because the numbers were wrong.
Get the Full Details
Where People Go Wrong
The biggest mistake I see is assuming that any dilute solution is automatically hypotonic. It is not. If you dilute a solution that already contains permeant solutes, the tonicity behavior changes in ways that are not obvious from the label. Another common error is ignoring the Donnan effect when dealing with charged solutes near a membrane. Proteins inside cells are negatively charged and cannot cross the membrane. This creates a slight imbalance in ion distribution that shifts the actual osmotic pressure by a few percent. In most routine work this does not matter, but if you are working with high-precision cell sizing or microfluidic applications, it can throw off your results. A third pitfall is using the wrong reference point. Tonicity is always relative. A solution can be hypotonic relative to one cell type and isotonic or even hypertonic relative to another. Human erythrocytes and rat hepatocytes do not have the same internal osmolarity. What works as a hypotonic lysis buffer for one may do nothing to the other. Always check the baseline osmolarity of your specific cell type before assuming a standard protocol will apply. The main limitation of hypotonic solutions in clinical settings is that they cannot be used indiscriminately. Intravenous administration of even slightly hypotonic fluids can cause hemolysis if the rate is too fast or the volume is large. I have seen cases where well-intentioned protocols using half-normal saline led to complications in pediatric patients because the fluid shifts were not monitored closely enough. The workaround is to use isotonic or near-isotonic formulations for IV therapy and reserve true hypotonic solutions for specific diagnostic or laboratory procedures where the risk is manageable and the benefit is clear.
Bottom Line
A hypotonic solution drives water into cells. That is the core idea. The details around solute permeability, dissociation, temperature, and cell type determine whether that water movement causes harmless turgor pressure or actual cell rupture. Get the concentration right, verify it with proper instrumentation, and do not skip the step of checking your cell type's baseline osmolarity. Everything else is just cleanup after a preventable mistake.