The Actual Method Matters More Than the Target
I used to tell patients to aim for 120 over 80, but the obsession with that single number caused more anxiety than it prevented. The real question is how you measure, when you measure, and what context surrounds that reading. A perfectly performed measurement will always beat a perfect target number.
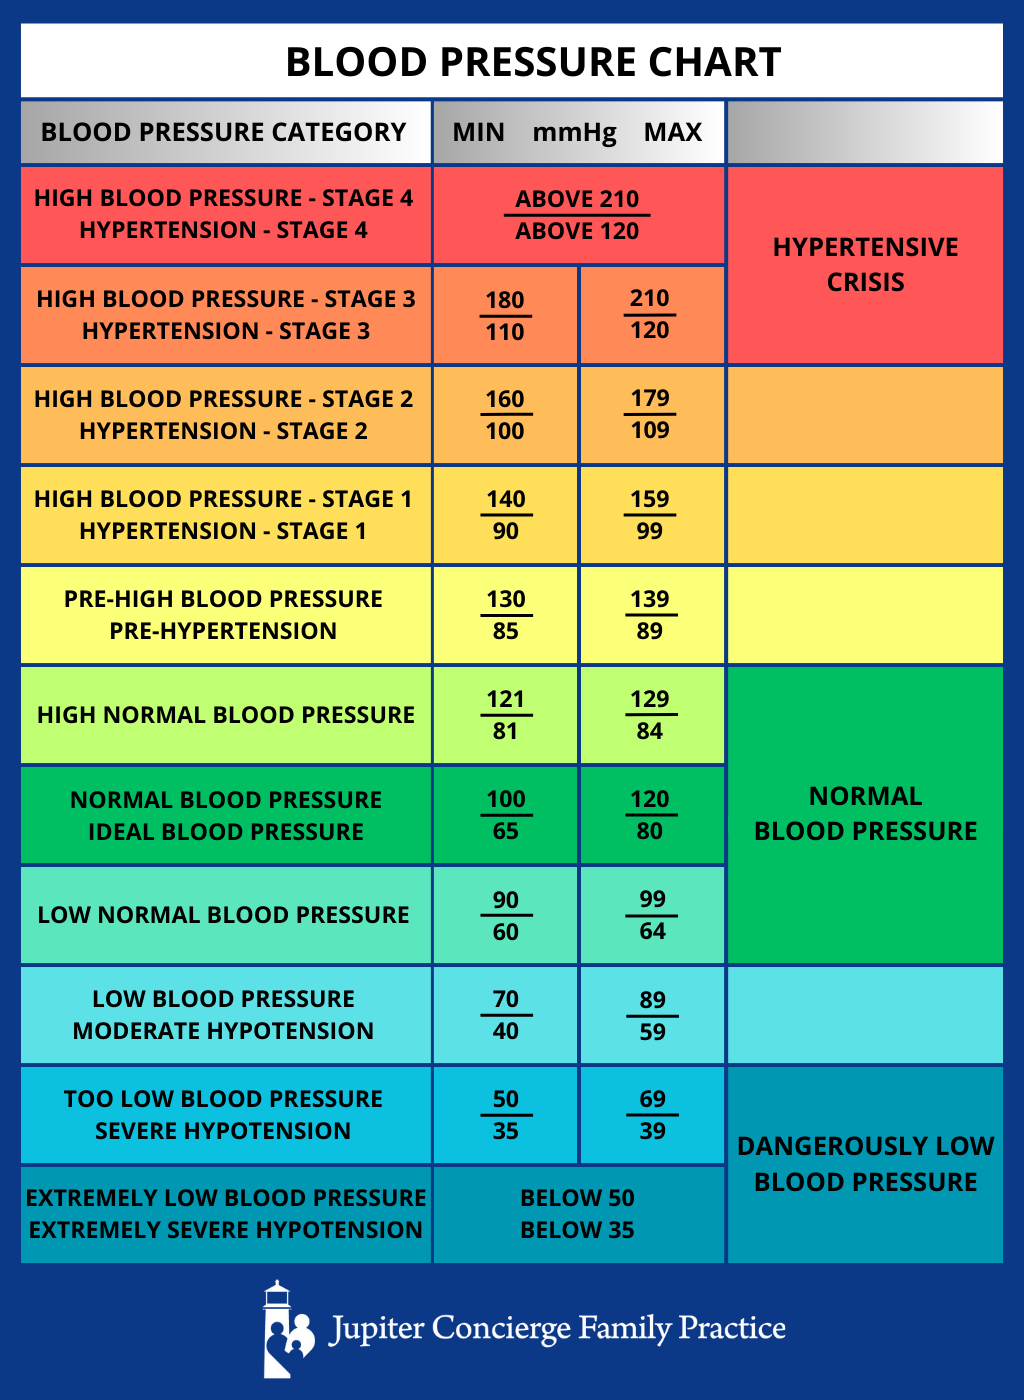
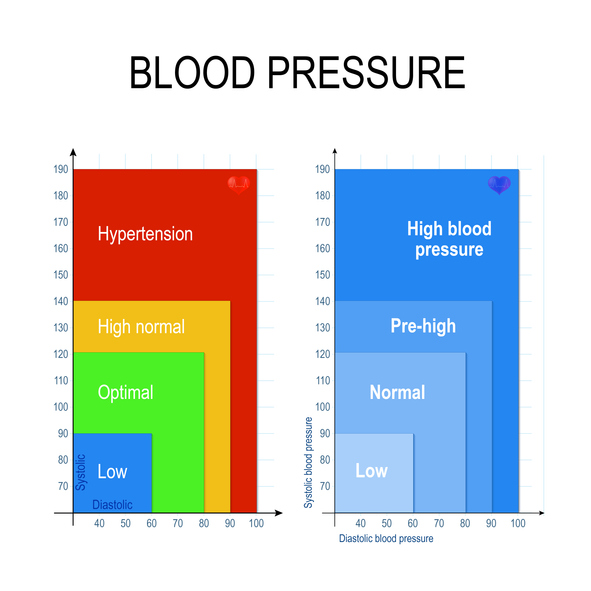
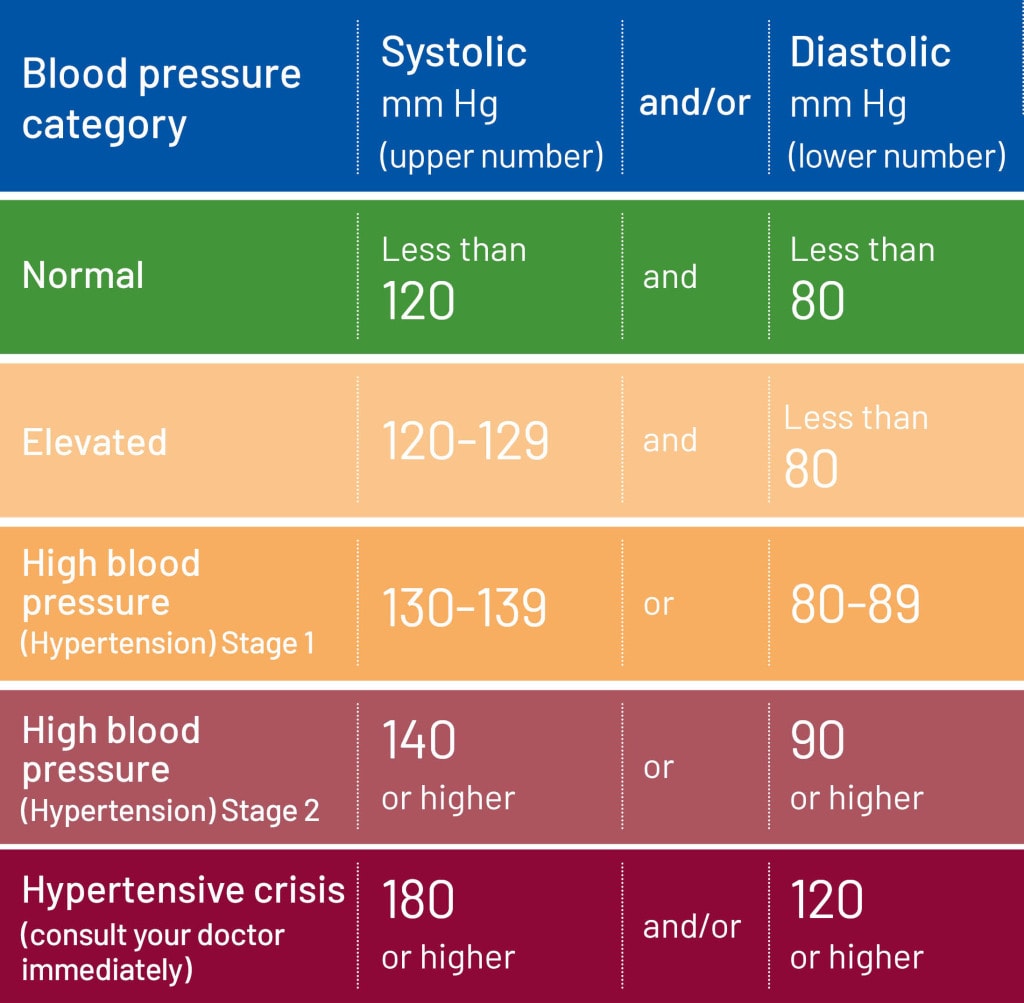
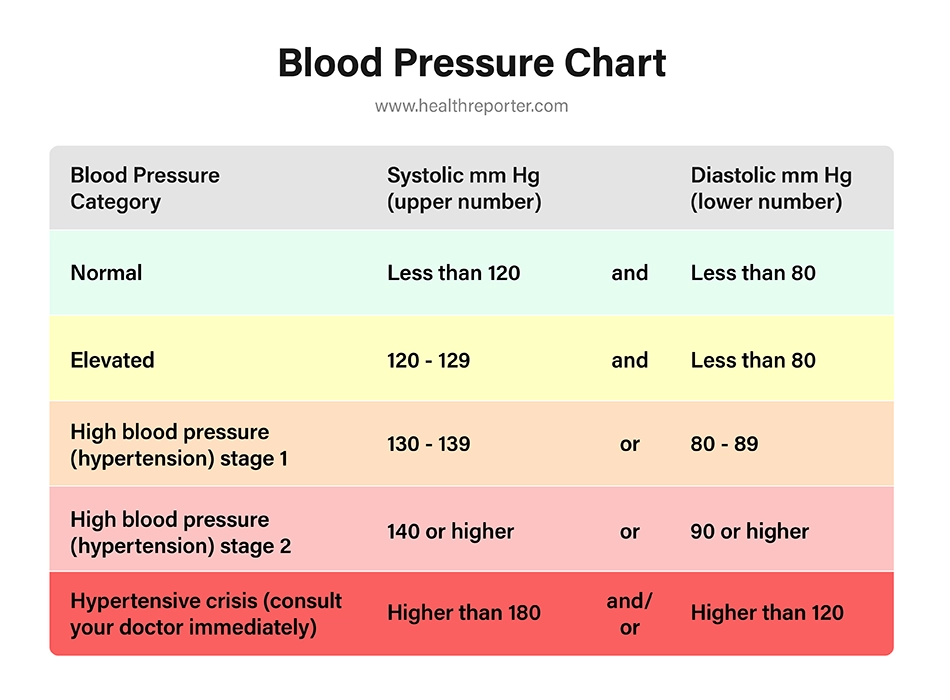
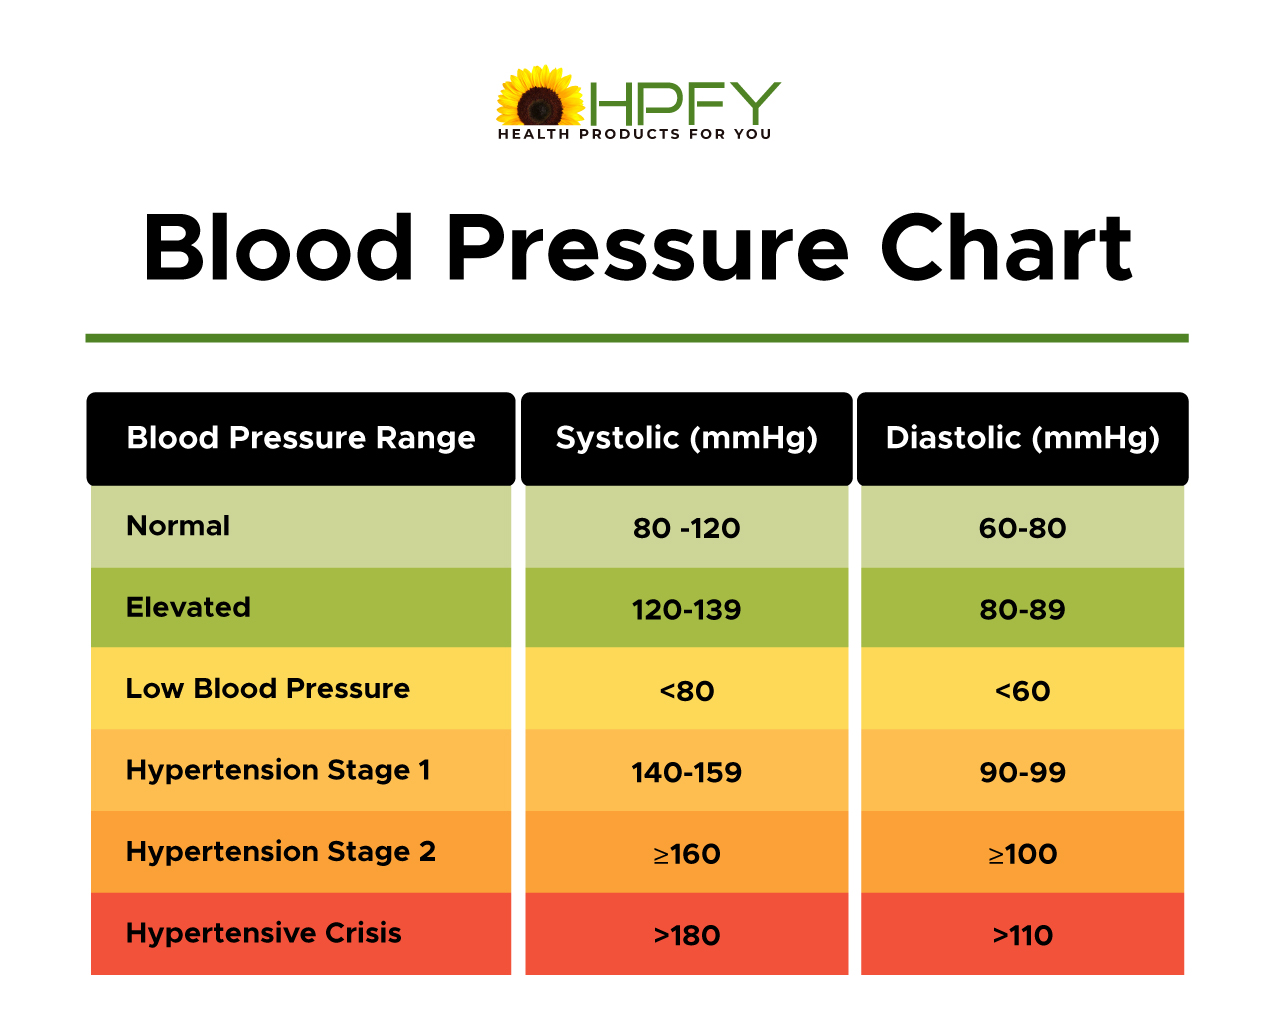
Here is how I have a patient actually get a reliable number. Stop caffeine for thirty minutes before. Sit in a chair with back support for five minutes without talking. Place your arm on a table so the cuff is level with your heart, not dangling. Use a validated upper-arm cuff, not a wrist device. Take two readings one minute apart and average them. Take three readings morning and evening for a week. This whole routine takes about twelve minutes and it transforms what is otherwise a deeply noisy data point into something actually useful. The standard reference is straightforward. Anything below 120 over 80 millimeters of mercury qualifies as normal. Below 120 and below 80 separately is the ideal range. Elevated sits at 120 to 129 with a diastolic under 80. Stage one hypertension is 130 to 139 systolic or 80 to 89 diastolic. Stage two starts at 140 or higher, or a diastolic of 90 or higher. That framework comes from the 2017 ACC/AHA guidelines and it is the baseline most clinicians use in the United States. But here is the part that does not make it into patient handouts. A single reading of 118 over 76 is not inherently better than a single reading of 119 over 77. The difference is clinically meaningless noise. What matters is the pattern across multiple days, multiple times of day, and under normal conditions. The number that comes from a rushed measurement after climbing stairs is almost always wrong for diagnostic purposes, even if it reads lower than your resting number from the morning.
The Edge Case That Breaks the Rule
I dealt with a patient last year whose home readings were consistently 115 over 72 but whose office readings hovered around 155 over 95. White coat hypertension. On paper, his perfect number was excellent. In reality, he had sustained hypertension that was being masked by the very environment where it should be caught. I had him wear a 24-hour ambulatory monitor, which revealed an average daytime reading of 148 over 91. He needed treatment. A single perfect number would have missed it entirely. This happens more often than you think. Masked hypertension, where office readings are normal but out-of-office readings are high, affects roughly 15 to 20 percent of people who present with normal clinic numbers. If you rely only on what you see in a single visit, you are working with an incomplete picture. Ambulatory monitoring or confirmed home averages are the only way to catch this.
Counter-Intuitive Things Most People Miss
Lower is not always better. There is a J-shaped curve relationship between blood pressure and cardiac events, particularly in older adults. Pushing systolic below 110 in someone over 75 with existing coronary disease can actually reduce perfusion to the heart muscle and increase risk. The perfect number for a healthy 35-year-old is different from the perfect number for a 78-year-old with a history of stroke. Treatment targets are individualized for a reason, not because the guidelines are vague. Another thing people overlook is isolated systolic hypertension. This is when the top number is high but the bottom number is normal, common in older adults due to arterial stiffening. A reading of 160 over 78 looks worse than it actually is on the surface, but the pulse pressure of 82 tells a different story. Wide pulse pressure is an independent risk factor for cardiovascular events, and it is easy to fixate on the diastolic alone and miss the real concern.
Get the Full Details
When the Method Fails Completely
Home monitors lose calibration over time. I had a patient whose device read 20 millimeters of mercury high for six months because the cuff had stretched. The numbers looked fine. The reality was stage two hypertension. You should bring your home monitor to your next appointment and compare it against the office device. If they differ by more than 5 millimeters systolic, replace the monitor or switch brands. It costs about twenty dollars and saves you from false reassurance. Atrial fibrillation and frequent ectopic beats also throw off automated cuff readings. The oscillometric method these devices use cannot reliably average irregular rhythms. If your pulse is irregular, your home monitor may give you a number that looks precise but is actually unreliable. In those cases, manual sphygmomanometry with a stethoscope is the gold standard, and home monitoring should supplement rather than replace clinical measurement. Cuff size is another common failure point. Using a standard adult cuff on a larger arm overestimates blood pressure by 5 to 10 millimeters of mercury. Using a large adult or extra-large cuff on a smaller arm can underestimate it. Measure your arm circumference at the midpoint between the shoulder and elbow. If it is above 33 centimeters, you likely need a large adult cuff. If it is above 42 centimeters, you need an extra-large thigh cuff. This is a trivial check that most people skip, and it is responsible for a significant portion of misdiagnosed hypertension in primary care.
The numbers themselves are only as good as the process that produced them. A reading of 120 over 80 taken correctly, on average, over a week, in the right context is far more valuable than a reading of 110 over 70 taken after rushing into a room. Focus on the method first, then the numbers.