The Practical Reality of Maintaining a Sterile Field
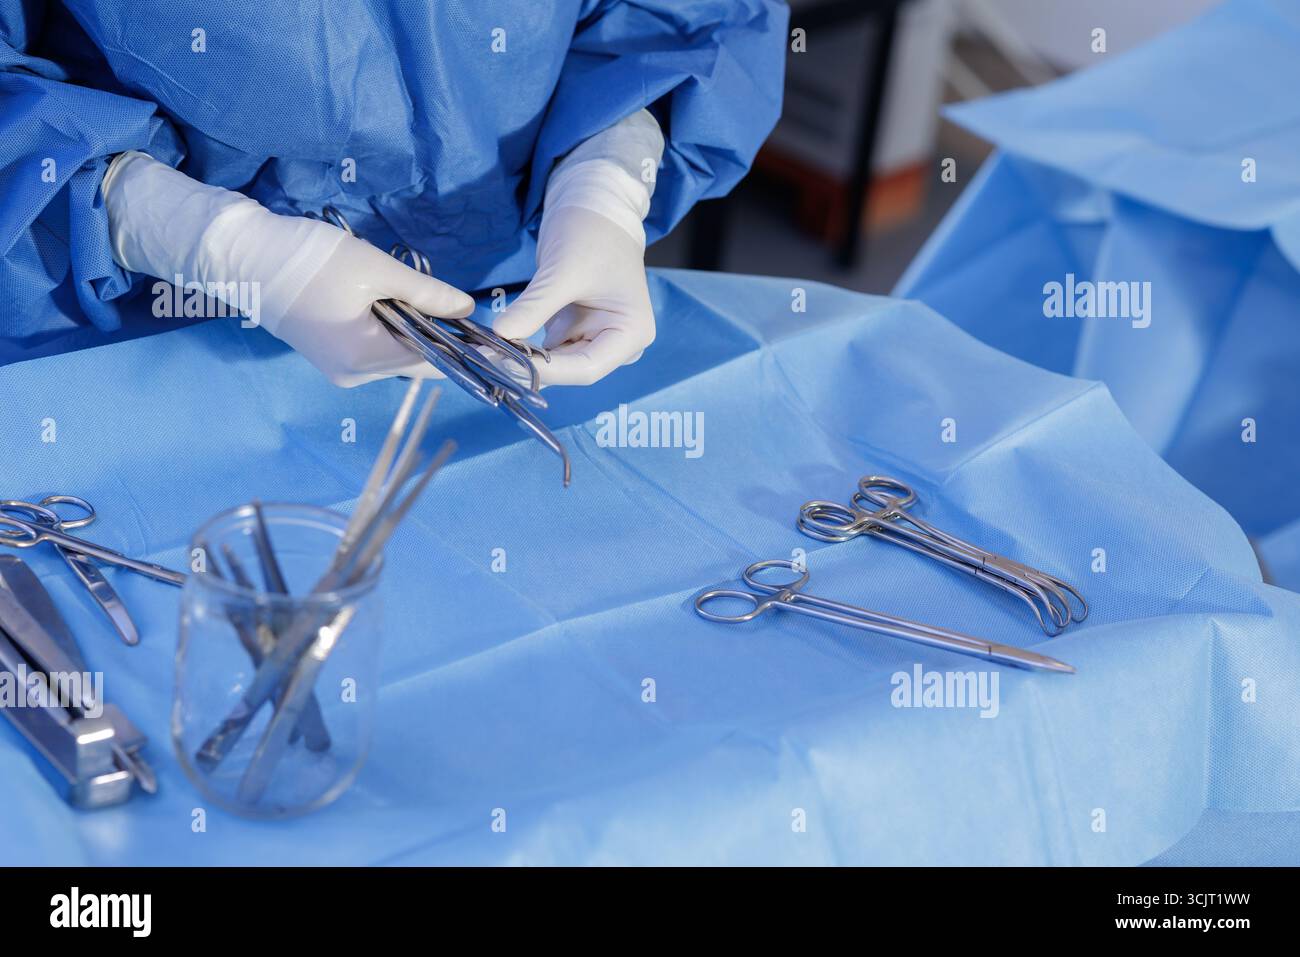
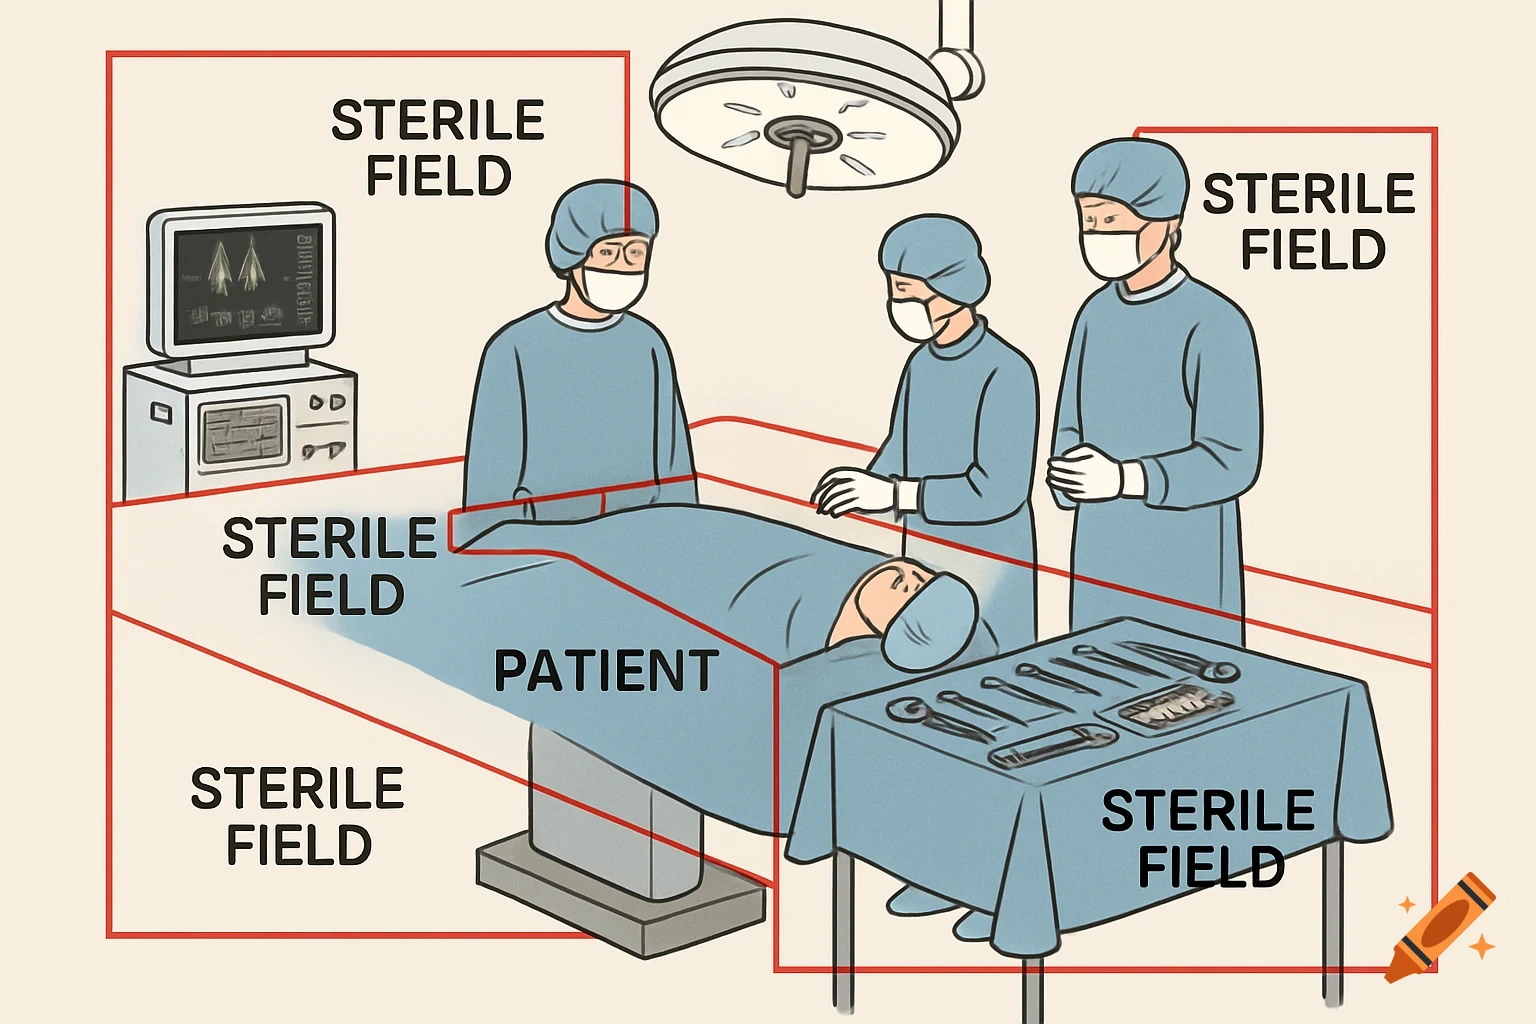
A sterile field is an area or surface that has been treated to eliminate all living microorganisms, including bacterial spores. In surgical settings, this means draped instruments, the patient's prepared skin site, and the zone immediately surrounding them. Anyone who has worked in an operating room knows that establishing one takes minutes, but maintaining it requires constant vigilance. The moment someone Breaches protocol, the field is contaminated and the procedure may need to restart. The definition seems straightforward, but the execution is where people get tripped up. A sterile field exists wherever sterile items are placed within line of sight and reach of the scrub team. This includes draped tables, opened instrument packs, gowned and gloved personnel, and any prep solution applied to the patient. The field extends roughly one inch beyond the edge of every sterile drape — anything past that is considered unsterile. You can't cross that boundary with a gloved hand without compromising everything inside it. I've watched surgeons lose count of how many times a tray got repositioned too close to the edge of a drape and had to restart the entire setup. The rule is simple: if it's not clearly on the sterile surface, it doesn't belong there. But in practice, trays slide. Drapes shift when patients move. Someone sets a suction canister down a fraction too far and now you're deciding whether it actually broke the field.
Here's something most training programs don't emphasize enough. The top layer of a peeling sterile wrap becomes sterile when opened correctly, but the underside does not. I once had a nurse pull open a instrument pack and lay it on the table only to realize five minutes later that she'd been using the contaminated underside as her working surface. She caught it because she was watching her own hands the whole time. Had she been distracted, that contamination would have traveled to every instrument that touched it. The peel-back method matters more than people give it credit for.
How It Works in Practice
Setting up a sterile field follows a predictable sequence, though every hospital has slight variations. The scrub person opens the outer wrap first, then the inner wrap, laying it flat without touching the interior surface. Instruments go on top in a specific arrangement — sharps separate from general tray items. The surgeon gowns and gloves before touching anything on the field. Sponges, needles, and sutures follow. The circulating nurse pours solutions directly onto the field without crossing the glove boundary with non-sterile hands. The real work starts after setup. Every pass across the unsterile perimeter counts. A gloved hand reaching for a door handle mid-procedure means a full glove change and potential field reassessment. This typically adds eight to twelve minutes to an already tight schedule. When a sterile field gets questioned, the circulating nurse documents it. If the breach is significant, the entire setup has to come down and restart, which in a busy OR can mean thirty to forty-five minutes of lost time while additional supplies are gathered and a new field is assembled. One counter-intuitive detail about moisture. Liquid spreads contamination. When prep solution or irrigation fluid wicks under a drape from the inside out, it carries microorganisms with it. A drape that appears dry on the surface may have microscopic wicking happening underneath. I've seen this cause false confidence in the field's integrity during longer procedures. The workaround is straightforward — use absorbent impervious drapes on high-fluid cases and check the perimeter at regular intervals rather than assuming the barrier holds.
Get the Full Details

Where It Breaks Down
Sterile fields aren't foolproof and they fail in ways that aren't always obvious. Porous drapes let pathogens through even without visible tears. Airflow from overhead vents or open doors can carry contaminants onto exposed surfaces, which is why minimizing movement in the OR during critical phases isn't just etiquette. The 30-centimeter rule around the field is supposed to prevent this, but in cramped surgical suites with multiple team members moving in and out, maintaining that zone is often aspirational. Another problem area is the intersection between sterile and non-sterile zones. Tape used to secure drapes to the patient has adhesive on one side and paper on the other, and the paper side is not sterile. Passing it across the field without touching the sterile surface requires deliberate technique. I've seen shortcuts where tape gets tossed onto the field with the sticky side down, and nobody catches it until after closure is underway. The limitations are worth acknowledging honestly. Sterile fields reduce risk significantly but don't eliminate infection. Surgical site infections still occur at rates between one and three percent even in properly maintained fields. The field is one layer of defense, not the entire system. Proper antibiotic prophylaxis timing, skin preparation with appropriate agents, and temperature management all matter just as much, sometimes more. If you treat the sterile field as the sole guarantee against infection, you're ignoring half the equation.
For cases where a traditional draped field isn't feasible — prolonged trauma resuscitations, field surgeries in non-OR environments, or situations where prepping the patient is impossible — there are alternative approaches. Antimicrobial-impregnated drapes and adhesive incise drapes with built-in iodine layers can provide a degree of contamination control when standard setups won't work. They're not equivalent to a full sterile field, but they're the next best thing when you have no other option.