Understanding Suffixes in Medical Language
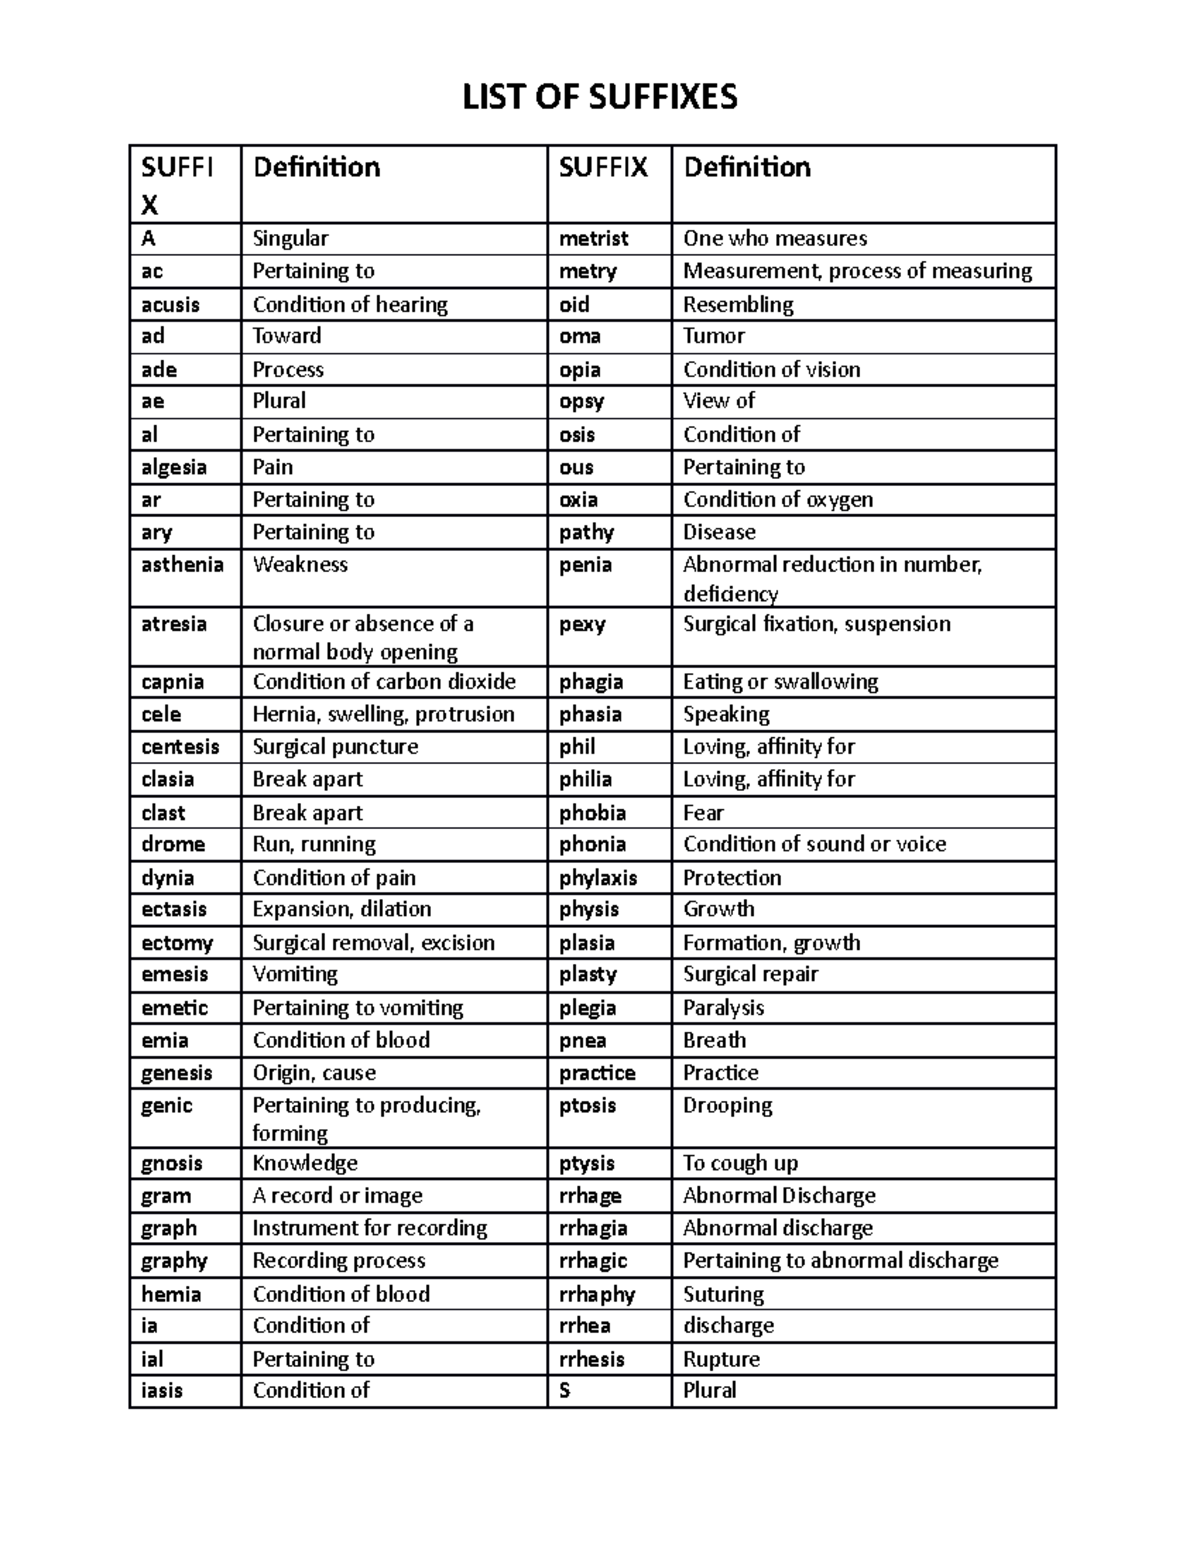
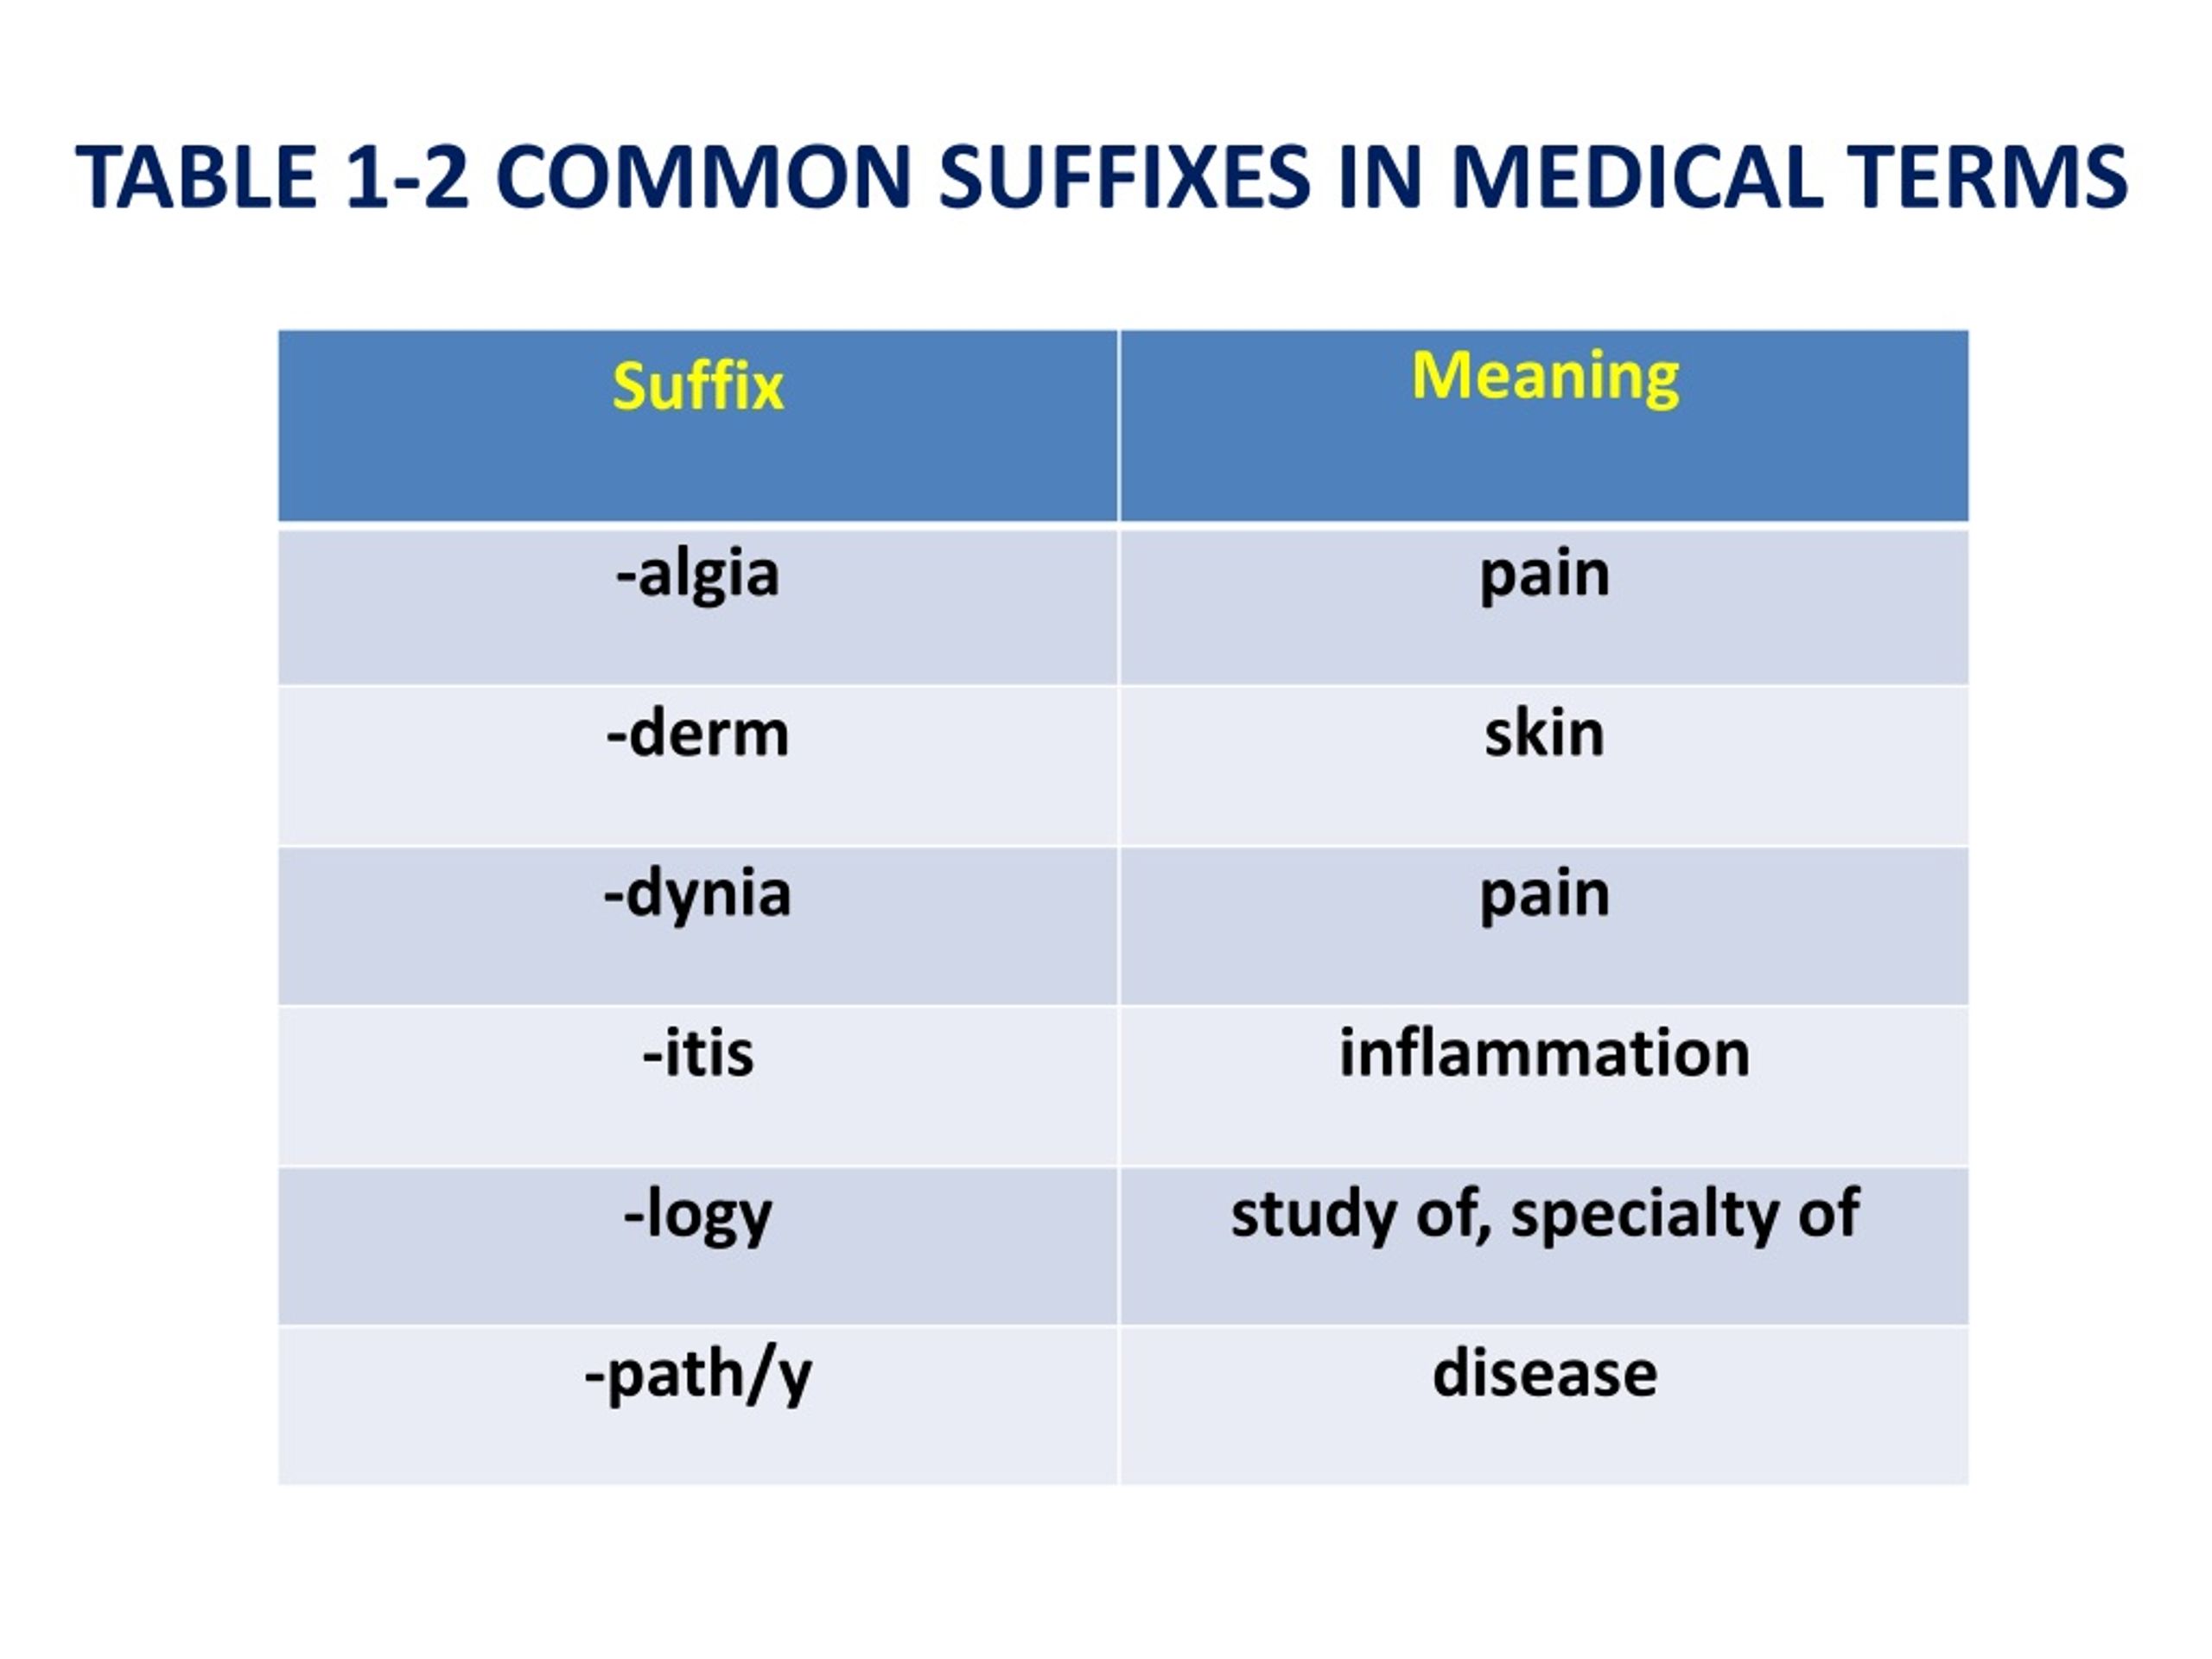
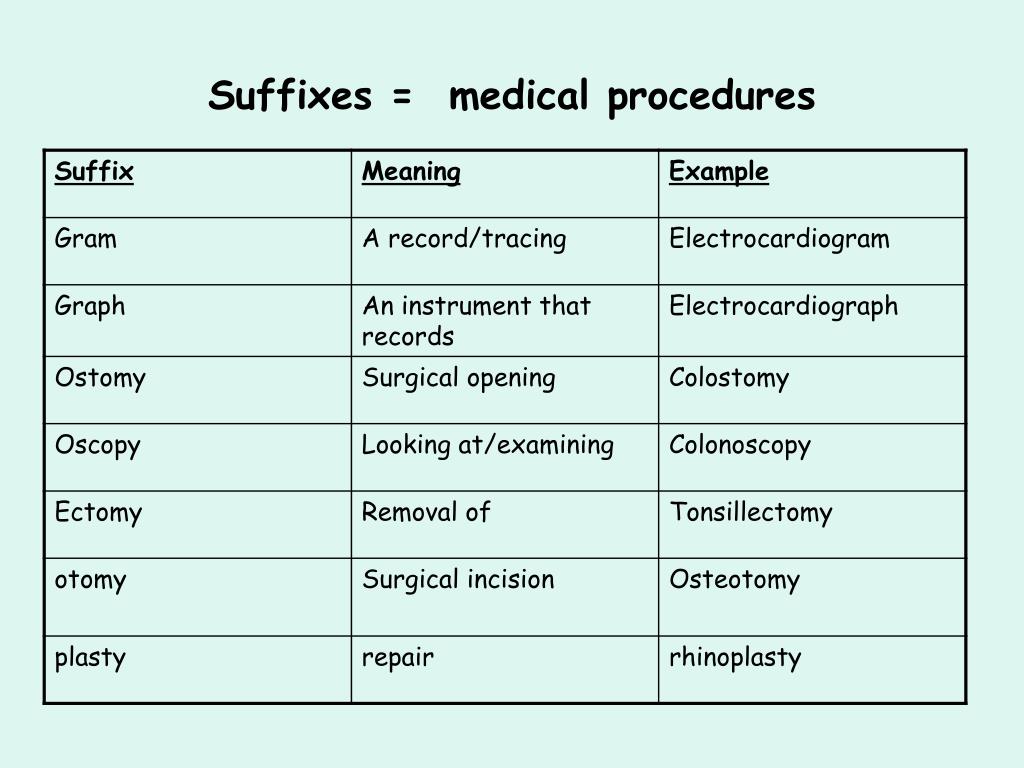
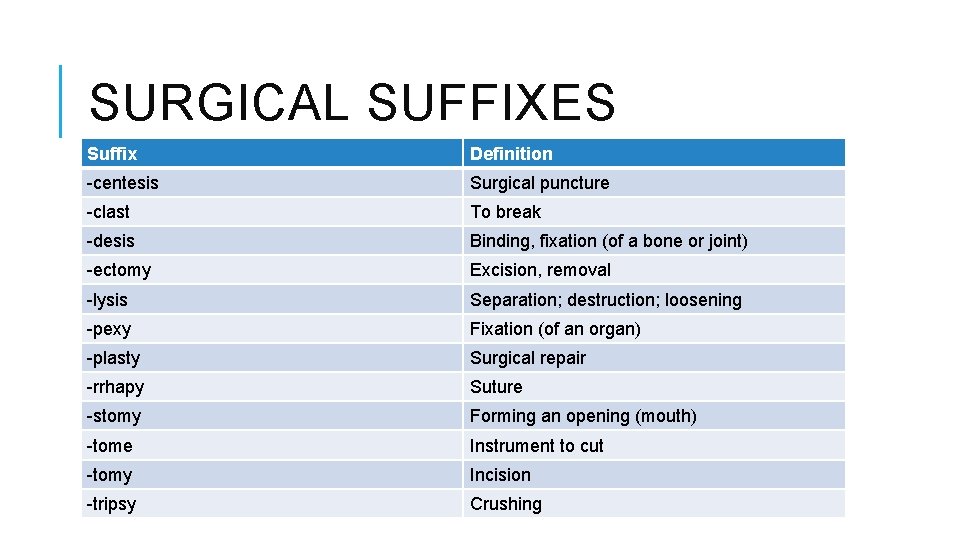
When you strip away the prefix and root of a medical term, what's left is usually a suffix. It's the ending piece that modifies meaning, and it's often where confusion creeps in. I spent years translating lab reports and surgical notes, and I can tell you that misreading a single suffix can flip a diagnosis completely. Take -itis versus -osis. One means inflammation, the other means a condition or disease state. Hepatitis is liver inflammation. Hepatosclerosis is hardening of the liver. Get them mixed up and your clinical picture shifts entirely. A medical suffix is a word element attached to the end of a root or combining form to modify its meaning. Most often it indicates a procedure, a condition, a specialty, or a diagnostic test. The core suffixes you will encounter repeatedly include -ectomy (surgical removal), -otomy (incision into), -scopy (visual examination), -plasty (surgical repair), -gram (record or image), and -logy (study of). Each one carries weight and specificity that changes the entire term when swapped with another. Here is the practical reality: suffixes rarely appear alone. They attach to roots, sometimes through a combining vowel, sometimes directly. Gastr/o plus -itis becomes gastritis. But cardi/o plus -logy becomes cardiology because the combining vowel -o- bridges them. The vowel is not part of the suffix itself, and beginners frequently misattribute it. That mistake compounds when you start parsing compound terms.
I ran into a specific edge case years ago involving the terms -emia and -ism. A junior colleague and I were reviewing lab documentation for a patient labeled with a condition described as "hyperparathyroidism." The chart had been flagged for endocrine workup, but the actual issue was hyperparathyroidism causing secondary hypercalcemia. The suffix -emia (blood condition) was being read through the lens of -ism (condition of), and the clinical chain was missed. We had to trace the suffixes back through the root each time. Now I always break the term down phonetically: hyper-para-thyroid-ism, then re-read what -emia would have meant if it were present instead. It took about three seconds per term once the habit stuck. One counter-intuitive thing about medical suffixes: some look identical but function differently depending on context. -pathy can mean disease (neuropathy) or simply a branch of medicine (homeopathy). -stomy means surgical opening (colostomy), but -scopy is purely visual. Beginners assume -stomy and -scopy are interchangeable because they share the -stom- root, but they are not. One creates an opening, the other examines through an instrument. Mixing them up during transcription has real consequences. Another nuance that gets glossed over: suffixes can change meaning when paired with different roots. -gen means producing or causing. carcinogen produces cancer. But -genic means originating from. hepatogenic means originating from the liver. The root -gen versus -genic distinction matters in oncology documentation where source and causation are clinically separate.
The main limitation of relying purely on suffix memorization is that medical terminology evolves. New procedures get new suffix combinations that don't fit clean patterns. -ectomy follows rules. -plasty follows rules. But terms like -ablation or newer interventional radiology suffixes don't always map neatly onto classical Greek or Latin roots. When you hit one of those, suffix decoding breaks down and you have to fall back on context and reference material. I recommend keeping a specialized glossary for interventional and procedural terms rather than assuming every ending follows the standard set.
Get the Full Details
How to Decode Any Medical Suffix
Start by isolating the ending. Look at the last three to five letters of the term and check against a reliable suffix reference. If it matches, remove it and examine what remains. The remainder should be a recognizable root or combining form. If it does not match any known suffix, the term might be using a non-standard or newer ending, and you should verify it directly. The breakdown process works like this: arthro + -scopy = arthroscopy, visual examination of a joint. Nephro + -logy = nephrology, study of the kidneys. Derma + -logy = dermatology, study of the skin. Notice how the root sometimes drops a letter or adjusts slightly when the suffix attaches. Cardi/o becomes cardi- before -logy. This morphological adjustment is normal and expected, not an error in the term itself. For quick reference, here are the most clinically significant suffixes organized by function type:
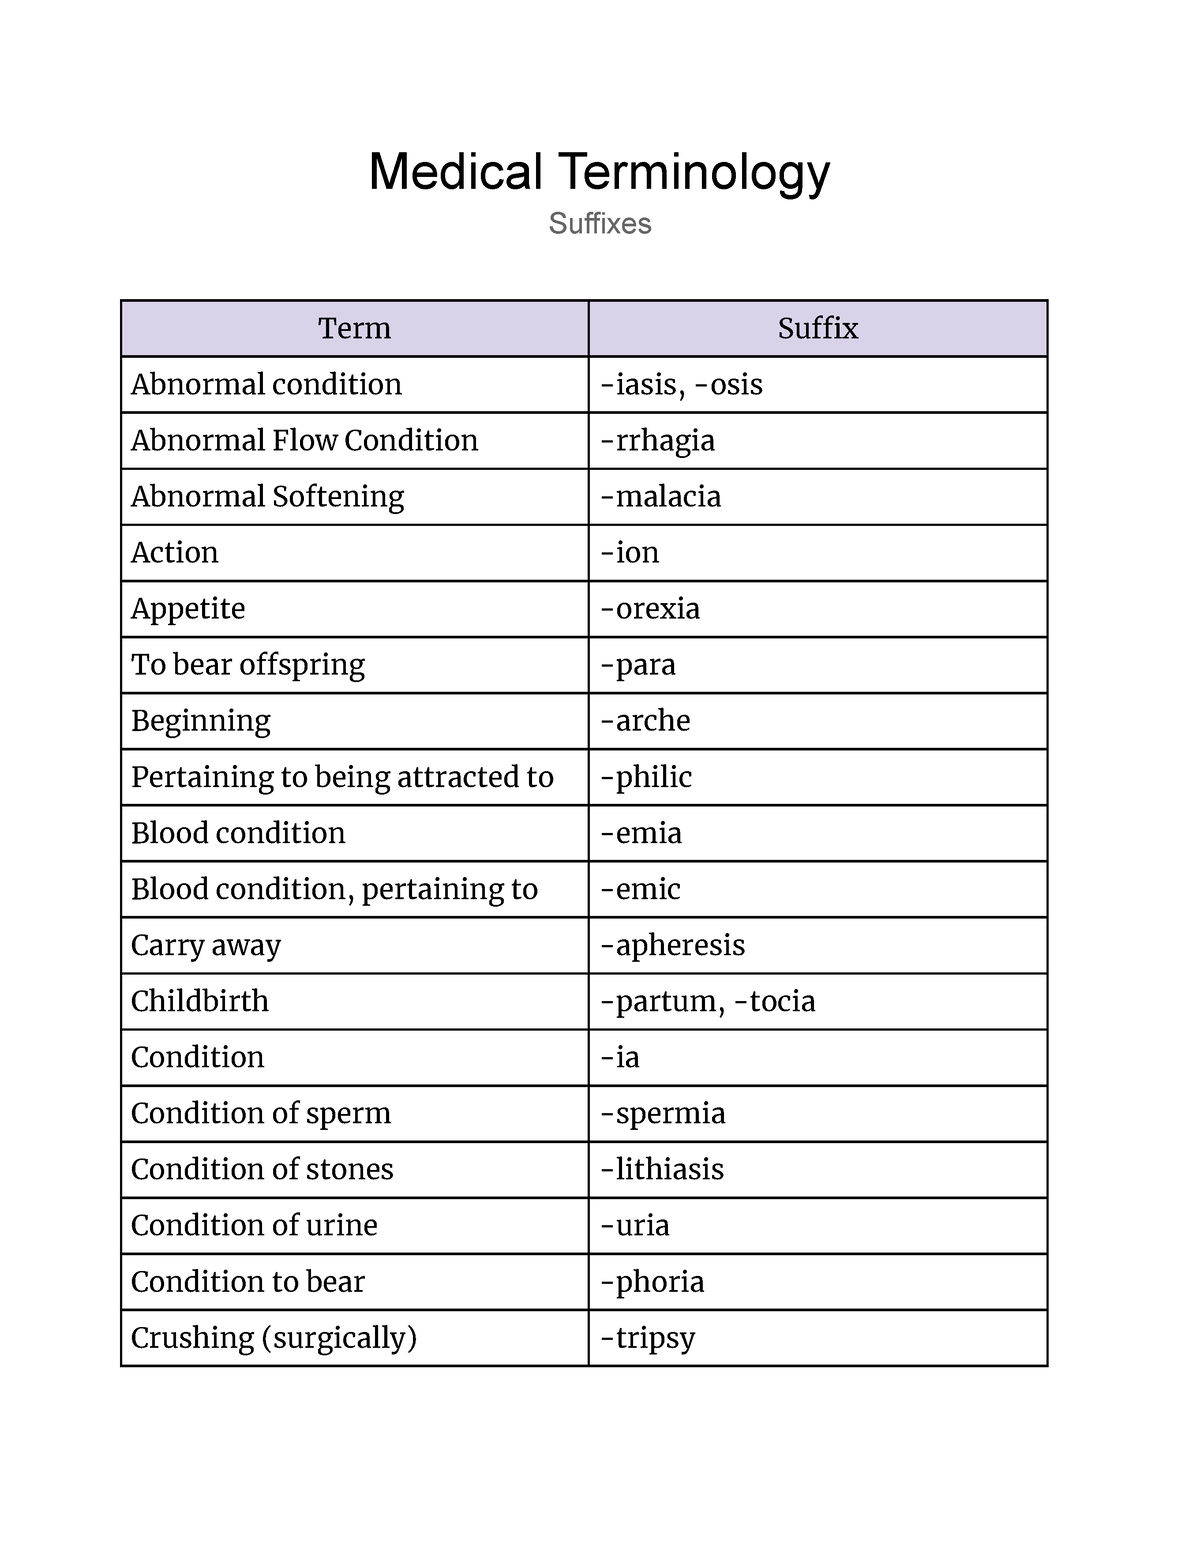
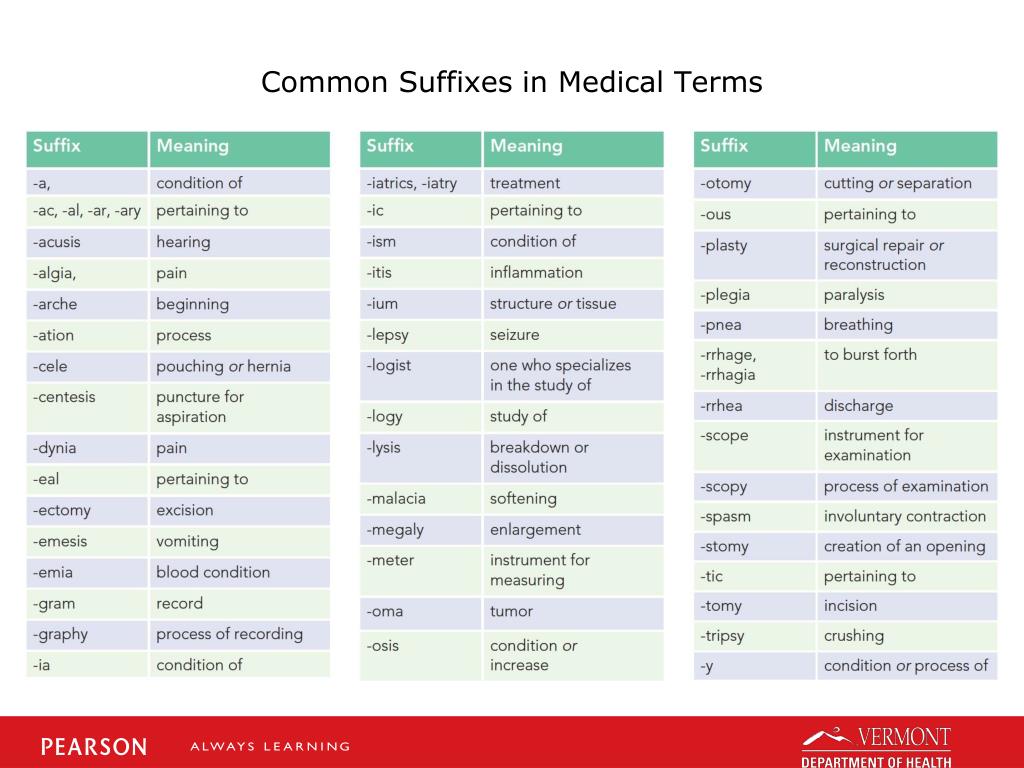
Diagnostic suffixes: -gram (record), -graphy (process of recording), -scopy (visual examination), -metry (measurement). Procedural suffixes: -ectomy (excision), -otomy (incision), -stomy (creation of opening), -puncture (penetration with needle), -plasty (surgical repair). Condition suffixes: -itis (inflammation), -osis (abnormal condition), -algia (pain), -dynia (pain), -penia (deficiency), -philia (attraction or affinity for).
Specialty suffixes: -logy (study of), -ist (specialist), -ian (specialist), -ics (study or field of). A workflow tip that actually saves time: when parsing unfamiliar terms, read the suffix first, not the prefix. Most people start at the beginning of the word and work forward, but suffixes carry more consistent meaning than prefixes. -itis always means inflammation regardless of what root it attaches to. -emia always relates to blood. Starting from the end gives you a stable anchor point before you try to decode the root. The biggest bottleneck I see in practice is that suffix tables alone are insufficient. You need the root vocabulary to match them against. Learning -ectomy means nothing if you do not know that hepat- means liver and gast- means stomach. The two lists must be studied together, and the most efficient approach is to learn them in thematic clusters rather than alphabetically. Group suffixes by procedure type and pair each with five to ten common roots. This reduces recall time during actual chart review to roughly two seconds per term.
There is no single download or resource that covers every modern suffix comprehensively because new terminology gets added continuously. The closest thing to a reliable standard reference is the AMA Manual of Style and the terminology sections in standard medical dictionaries. For clinical transcription work, I maintained a personal spreadsheet mapping every suffix I encountered in my daily workload, cross-referenced with the root and the full term definition. It took about four hours to set up initially and saved maybe twenty minutes per day going forward. That is the practical equivalent of a download link, and it adapts as the language evolves.