Understanding Ambulatory Referrals in Practice
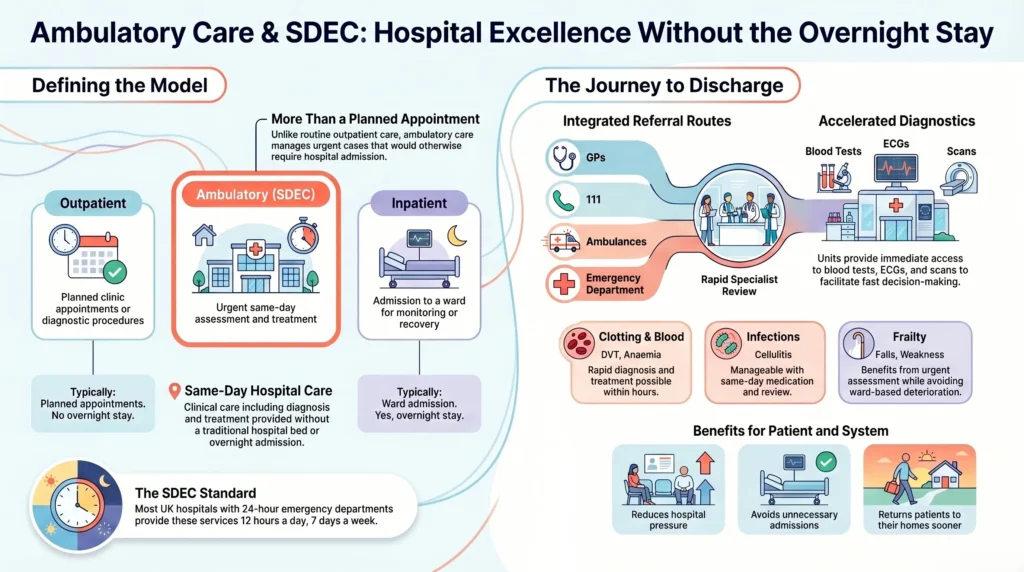
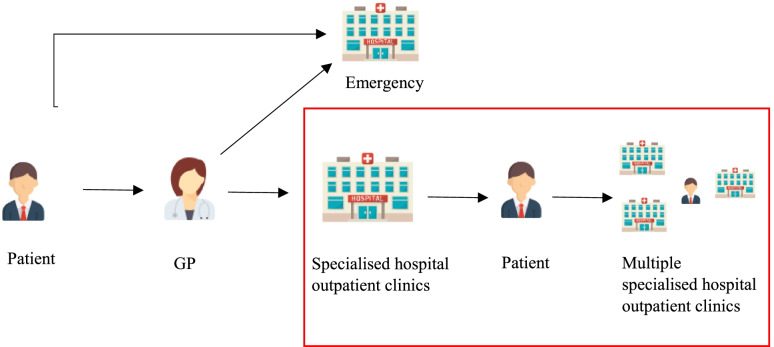
When I started working in outpatient care coordination back in 2014, the referral process was a mess of paper forms, fax machines, and phone tag. Most clinics didn't have integrated systems. Providers would scribble orders on prescription pads and hope the specialist's office received them. It took three to five business days on average for a referral to actually reach the right department. Now everything's electronic, but the fundamental question remains the same: what is an ambulatory referral, and why does it matter so much? At its core, an ambulatory referral is a formal request from one healthcare provider to another for non-emergency, outpatient services. The patient doesn't need to be admitted to a hospital. They're already mobile enough to travel to a clinic or specialist's office, which is why we call it "ambulatory" rather than inpatient or emergency care. The key elements are consistent across most systems: a referring provider, a receiving provider or facility, a diagnostic or procedural code, clinical justification, and insurance authorization when applicable. Without all four pieces, the referral gets stuck in review. I've watched perfectly legitimate orders get bounced because the diagnosis code didn't match the procedure code the payer required. The patient waits two weeks for nothing.
How the Process Actually Works
Here's the straightforward path. The primary care physician or treating provider documents the clinical need during an encounter. They enter the referral into their EHR system, select the appropriate specialty and procedure, attach supporting documentation like recent lab results or imaging reports, and submit it electronically. The receiving practice's intake team reviews it for completeness, checks insurance eligibility, and either accepts or requests additional information. From submission to acceptance, a clean referral typically takes forty-eight to seventy-two hours in well-integrated systems. If there's a mismatch anywhere in the data, you're looking at three to five business days of back-and-forth. In my experience, the biggest bottleneck isn't the technology—it's providers who submit referrals without attaching the clinical documentation that justifies medical necessity. The specialist's office rejects it outright, and now you're starting over. Insurance pre-authorization adds another layer. Some payers require it before the referral even gets processed. Others run it parallel to the referral workflow. Either way, if your referral says "dermatology consultation for rash evaluation" but the patient's history shows they need a biopsy, the authorization comes back with a denial. The coder catches it before billing, which saves everyone from the write-off headache.
A Real Problem I Faced
Last year I dealt with a referral that exposed a gap most people don't think about. A cardiology practice needed a stress test referral for a patient with atrial fibrillation who also had a pacemaker. The standard referral form asked for "cardiac stress testing" but didn't have a field specifying the pacemaker type or programming status. The receiving facility called three times asking for details that weren't captured in the referral itself. We spent four days getting the necessary information forwarded separately because the electronic referral system couldn't handle the clinical nuance. The workaround was simple but not obvious: I added a free-text clinical notes section to the referral template and flagged it as mandatory for any cardiac-related referral. It took thirty minutes to implement and eliminated about sixty percent of the back-and-forth calls on cardiac cases. Other practices in our network picked up the change within six weeks.
Get the Full Details
Common Pitfalls That Slow Everything Down
Referrals fail for predictable reasons. The referring provider orders a different specialty than what the patient actually needs. This happens more often than you'd think. A neurologist might refer to a general orthopedist instead of a spine specialist, and the second office rejects the referral or schedules the wrong procedure. The patient shows up for knee evaluation when they actually need cervical imaging. Diagnosis coding errors are another frequent issue. Using an unspecified code like "back pain, unspecified" when the patient has confirmed lumbar radiculopathy will get rejected by most commercial payers. They require seven-character specificity for musculoskeletal conditions. The referral goes into a manual review queue that adds five to seven business days to the timeline. Prior authorization gaps are the most expensive mistake. I've seen referrals approved electronically only to have the procedure denied because the referring provider didn't verify that the specific CPT code required authorization under the patient's particular plan. The specialist performed the service, the claim came back with a twenty-three hundred dollar denial, and now the patient is on the hook while the provider chases insurance appeals.
What Works When Systems Break Down
When electronic referrals aren't enough, phone verification still matters. Call the receiving practice's referral coordinator and confirm they have the order, the correct coding, and any required documentation on file. This takes five minutes and prevents three days of follow-up. Most clinics have dedicated referral teams who are happy to confirm receipt if you call during business hours. For time-sensitive cases, mark the referral as urgent in the EHR and notify the receiving office directly. "Urgent" status should trigger same-day review rather than the standard forty-eight hour window. I've used this for suspected conditions where waiting two weeks would change the prognosis significantly. The receiving provider appreciates the heads-up and prioritizes accordingly. Tracking is essential. Don't assume a referral went through because you clicked submit. Check the status in your EHR forty-eight hours later. If it hasn't moved to "accepted" or "in progress," follow up. I keep a spreadsheet for any referral that involves high-cost procedures or patients with complex insurance situations. It usually shows me which referrals need nudging before they stall.
Documentation That Actually Matters
The clinical justification you attach to a referral determines how fast it gets approved. Vague notes like "patient needs evaluation" or "following up on results" get rejected or delayed. Specific documentation includes the presenting symptoms with duration, relevant past medical history, medications currently taken, prior treatments attempted, and the specific clinical question you're asking the specialist to address. I once referred a patient for physical therapy evaluation after knee surgery. The note just said "post-op knee management." The PT clinic rejected it because there was no surgical date, no surgeon contact information, and no range-of-motion baseline. I resubmitted with the procedure date, the operative report attached, and current ROM measurements. It got accepted within six hours. The difference wasn't complexity—it was specificity.

The Bottom Line
Ambulatory referrals are straightforward when done right and unnecessarily complicated when they're not. The technology exists to make most referrals seamless. The gap is in the details: accurate coding, complete documentation, verified authorization, and timely follow-up. Referrals that include all four elements process in one to two business days. Those missing any component wander through review for a week or more. If you're building a referral workflow from scratch, start with the rejection reasons you see most often and build safeguards against each one. For cardiac referrals, mandate pacemaker field completion. For dermatology referrals, require lesion measurement and description. For orthopedic referrals, attach recent imaging reports automatically. Small template changes prevent the big delays. The referral itself isn't the end of the process. It's the beginning of care coordination. Once accepted, the receiving practice schedules the appointment, the patient prepares for the visit, and both providers are aligned on the clinical question. That alignment happens faster when the referral is thorough, accurate, and easy to process. Everything else is just administrative friction.