Measuring the apical pulse properly matters more than most people realize
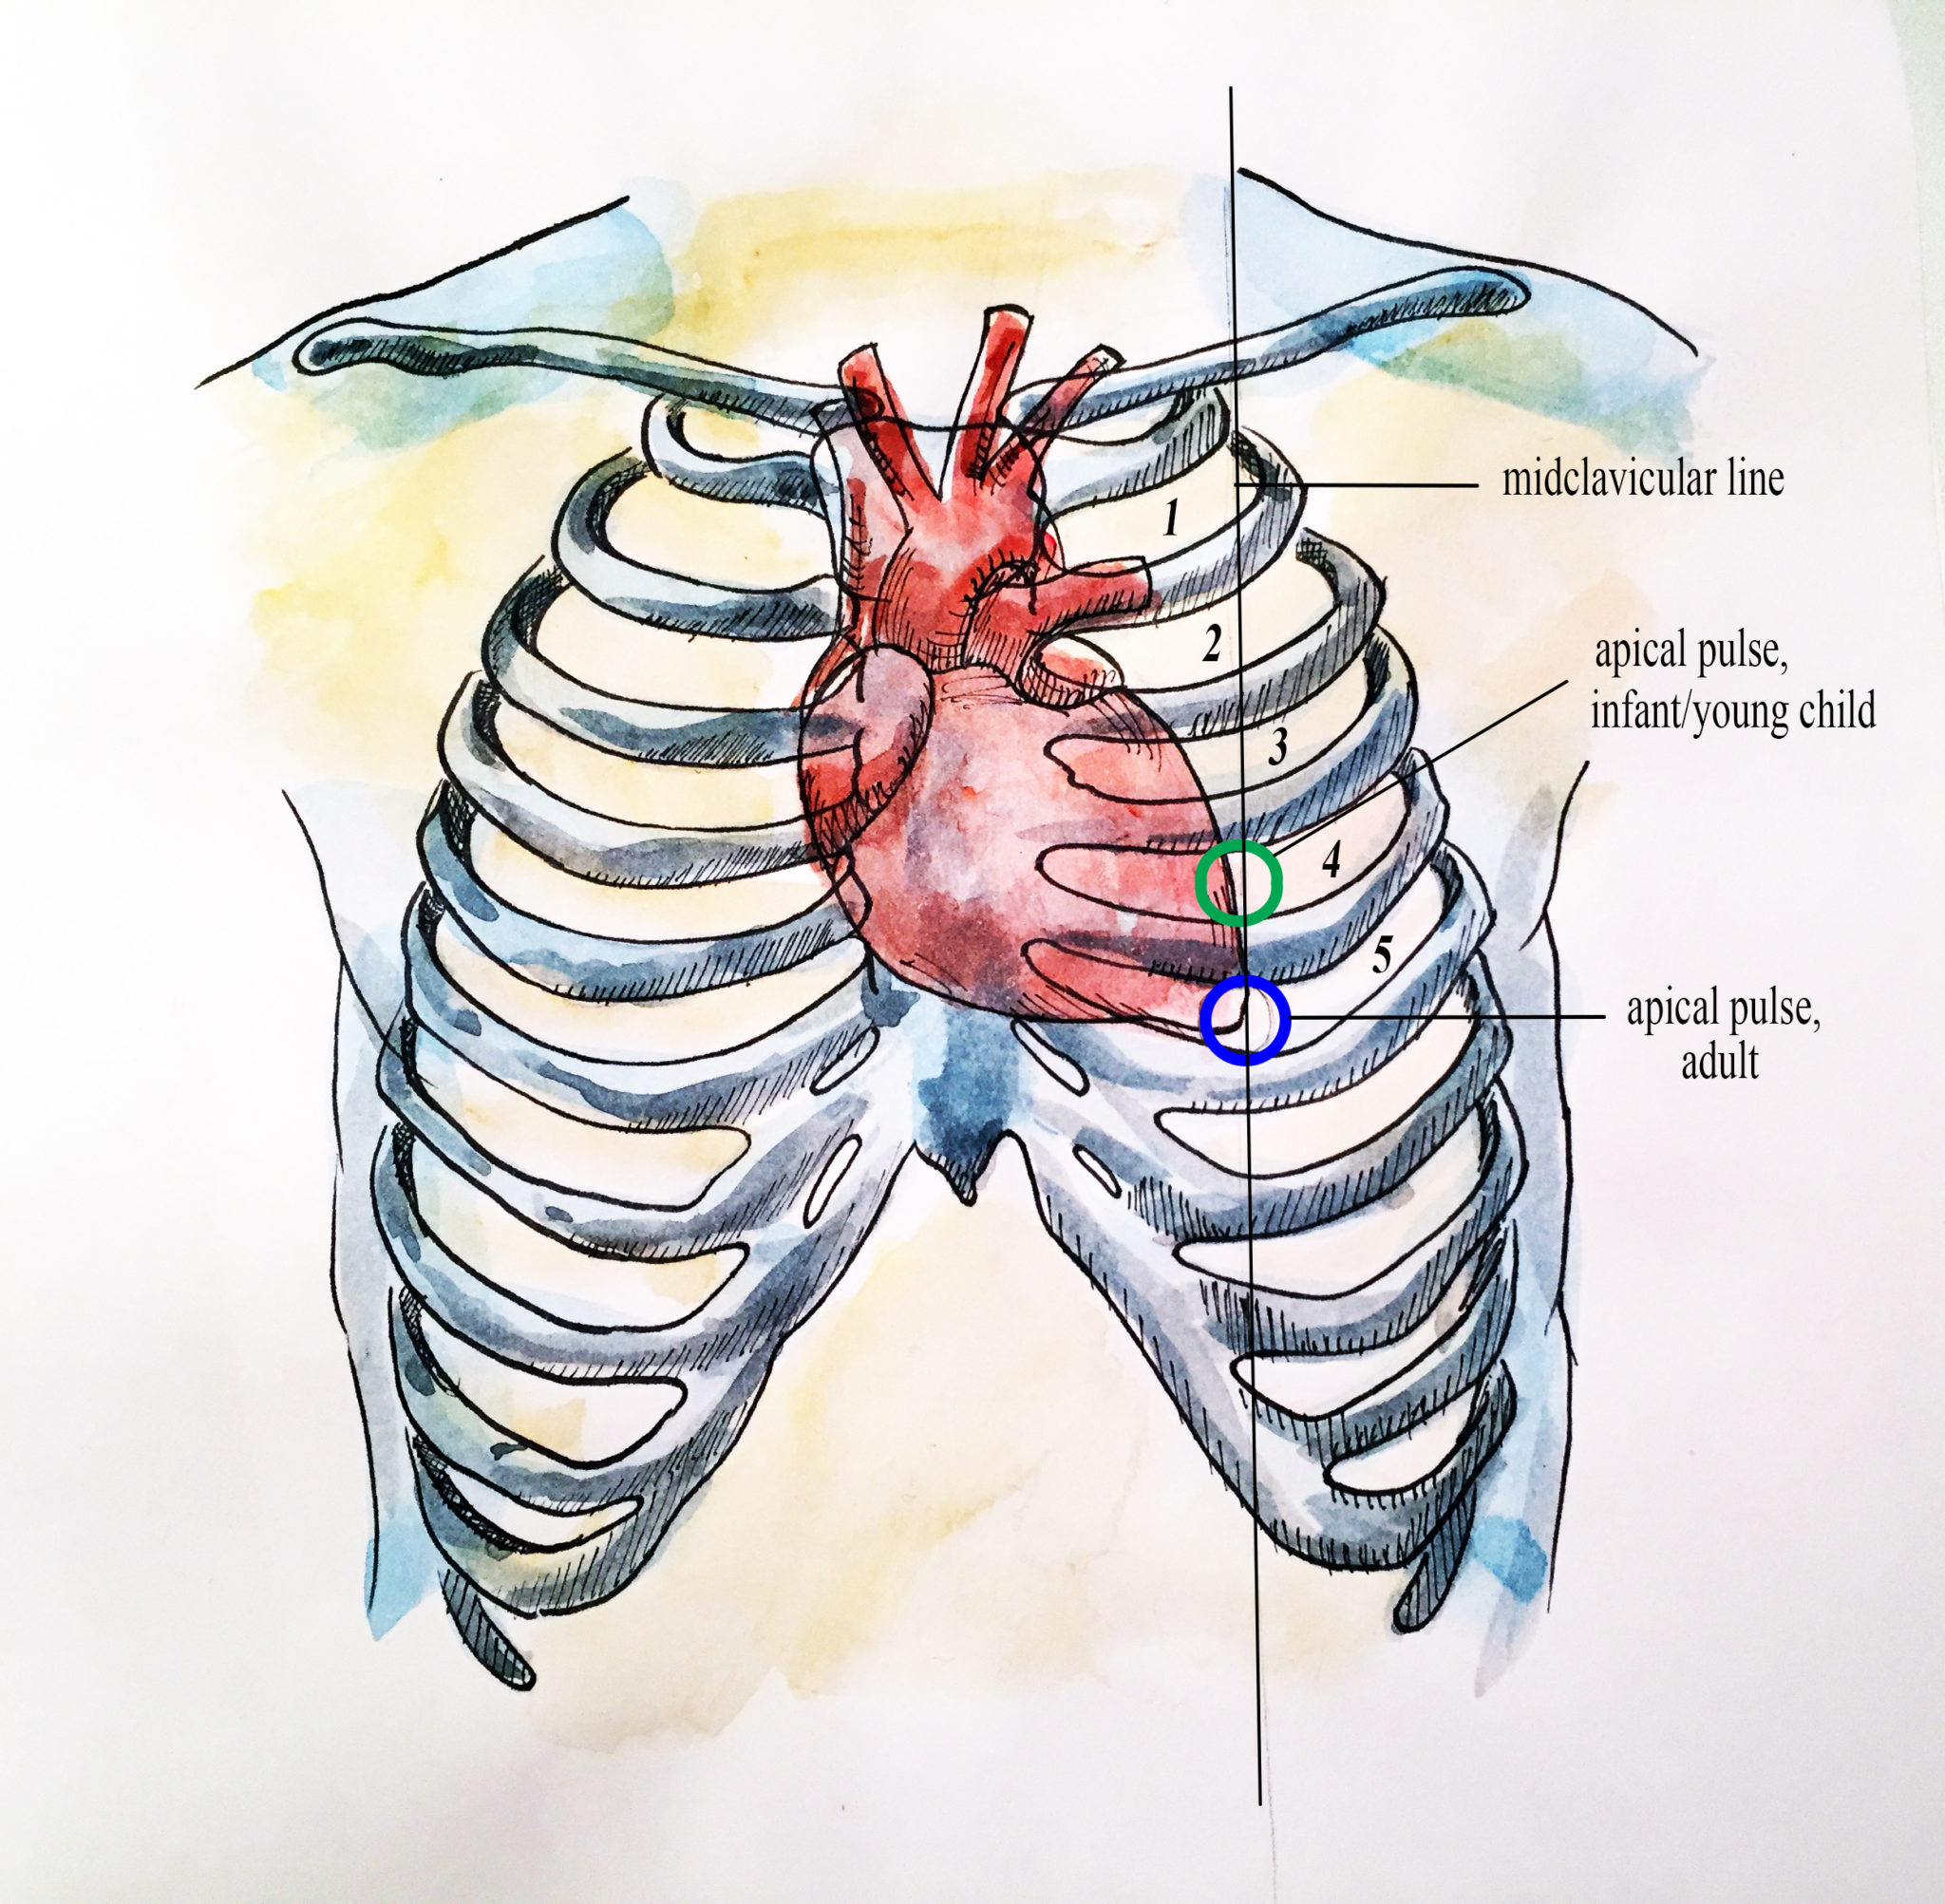
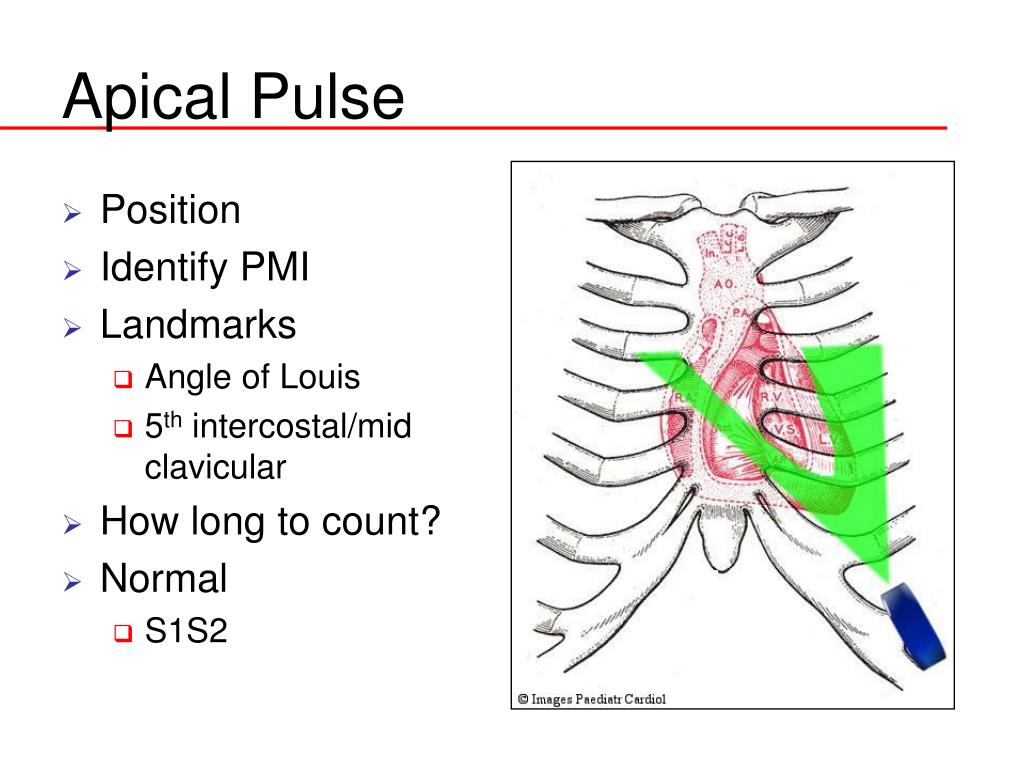
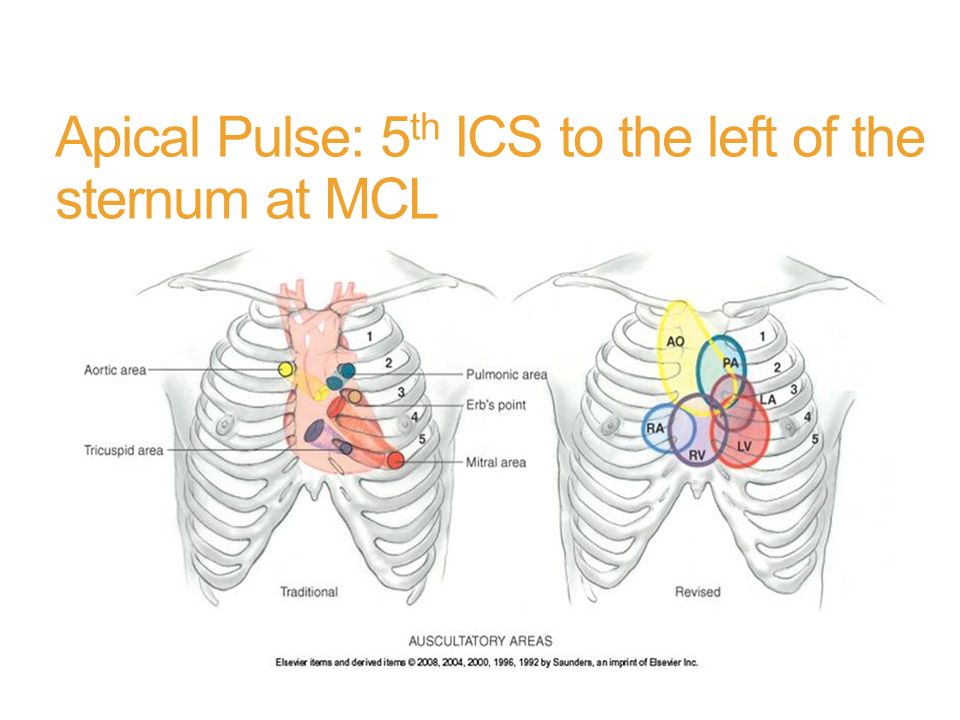
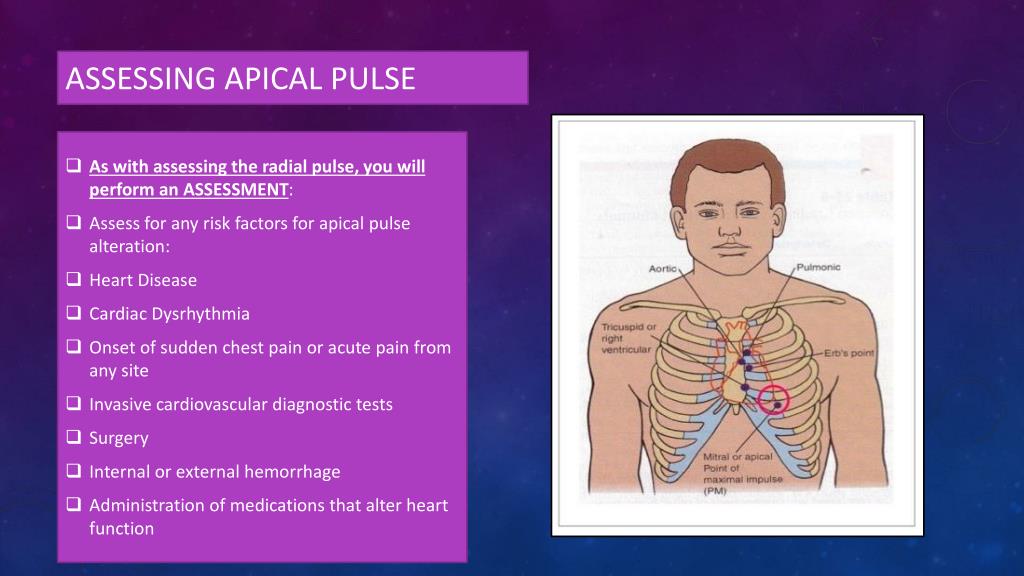
The apical pulse is the heartbeat you hear or feel at the point of maximal impulse on the chest wall. It is located at the fifth intercostal space, just medial to the left midclavicular line. This is where the heart's apex presses most directly against the rib cage. In clinical practice, it is the standard site for auscultating heart rate when accuracy matters. I spent years doing vitals on a telemetry unit, and the apical pulse was where I learned the difference between "close enough" and actually correct. Electronic monitors give you a number, but they also give you artifacts during patient movement, shivering, or poor electrode contact. When the monitor read 110 and the patient looked calm sitting in a chair, I knew something was wrong with the reading, not the patient. You go to the chest. You count for a full minute. That is the habit that saves you later.
What Is Apical Pulse and why it differs from radial checks
The radial pulse is a peripheral pulse. It is easier to access but susceptible to arrhythmias, low perfusion states, and vasoconstriction. The apical pulse reflects actual ventricular contraction. The gap between the two is called a pulse deficit, and it is clinically significant. Atrial fibrillation is the classic example. In afib, some ventricular contractions are so weak they do not generate a palpable peripheral pulse. If you only check the radial site, you will underestimate the true heart rate. The apical reading is the one you document when perfusion is questionable or when an accurate baseline is required. There is a specific technique that most people get slightly wrong. You do not just press the diaphragm of the stethoscope against the chest and hope for the best. The skin needs to be exposed properly, the room needs to be quiet enough to hear S1 and S2 without background interference, and you need to identify the correct landmark before you place the diaphragm. In my experience, the biggest source of error is placing the stethoscope too high or too lateral. That lands you over the aortic or pulmonic areas instead of the mitral area, and you are counting valve sounds rather than the apical impulse itself. The difference matters when you are tracking heart rate trends over time. Here is the practical method I used daily. Position the patient supine or semi-Fowler's. Expose the chest. Locate the left midclavicular line. Count down to the fifth intercostal space. That is where the point of maximal impulse typically sits in an adult with normal anatomy. Place the diaphragm there. Count for a full sixty seconds. Note the rhythm regularity. Document the rate and the character. That is it. It takes about ninety seconds total if you know where you are going, and about three minutes if you are hunting for the landmark on a patient with a larger chest wall or increased breast tissue.
There are situations where the apical pulse is harder to pick up than you would expect. I worked a patient once who had a BMI over 40 and emphysema. The lung hyperinflation pushed the heart downward and rotated it, shifting the PMI laterally and inferiorly from the textbook location. The apical impulse was nowhere near the fifth intercostal space at the midclavicular line. I had to sweep the stethoscope along the lower left anterior chest while listening for the loudest S1. The rate was audible around the sixth or seventh intercostal space, closer to the anterior axillary line. You do not always find it where the diagrams show it. The diagram is for a standard anatomy reference, not for every patient you will see. Another edge case I encountered involved patients on digoxin with atrial fibrillation and frequent ectopic beats. The heart rate was around 95 apically but the radial pulse was barely 60. The pulse deficit was nearly 35 beats per minute. That is a massive discrepancy, and it is exactly the kind of thing that gets missed if you are rushing through vitals and only grabbing the radial. The monitor in that room was also giving inconsistent readings because the patient's irregular rhythm confused the pulse oximeter's algorithm. The apical count was the only reliable number available. Writing it down was the only thing that prevented the next clinician from missing the severity of the low cardiac output state. There are limitations to this method that are worth stating plainly. It is operator dependent. Two different clinicians can count the same apical pulse and get different numbers if one counts for thirty seconds and doubles it while the other counts for a full minute. The three-second or fifteen-second extrapolation method introduces error, especially with any degree of irregularity. If the rhythm is irregular, you must count for a full minute. There is no acceptable shortcut. Additionally, obese patients, patients with copious chest hair, and patients with loud surrounding noise all make auscultation more difficult. In those cases, you may need to use the bell, apply more pressure with the diaphragm, or ask the patient to hold their breath briefly to reduce respiratory noise. You cannot always get a clean reading, and you should document when you could not obtain one rather than guessing.
Get the Full Details
Pediatric apical pulses follow the same anatomical principle but the landmark shifts slightly with age. Infants and small children often have the PMI at the fourth intercostal space rather than the fifth. The heart sits more horizontally in the chest until the child grows into a more upright posture. Using the adult landmark on a toddler will often put you below the actual impulse. This is a common mistake for anyone transitioning from adult to pediatric work. The fix is straightforward: find the sternum, locate the nipple line as a rough guide, and move medially from there. If you are uncertain, start at the fourth intercostal space and work downward until you find the loudest point. The equipment required is minimal. A standard acoustic stethoscope is sufficient. Electronic stethoscopes exist and can amplify heart sounds, but they are not necessary for routine vital assessment and they add cost without adding reliability in most general ward settings. A timer or a watch with a second hand is all you need for timing the count. Some units use a dedicated apical pulse timer app, but I never trusted phone vibrations or screen-based timers during a busy shift. A mechanical watch or the wall clock was more dependable. If you need a written reference or a quick checklist for training purposes, the methodology is standardized across most nursing and medical programs. Look for the guidelines published by the American Heart Association or your hospital's nursing policy manual. Those documents spell out the landmark identification, timing requirements, and documentation standards. There is no single downloadable resource that covers this better than the actual practice of doing it repeatedly until the landmarks become second nature.
The bottom line is that the apical pulse remains the most accurate bedside method for determining true heart rate and rhythm character. Electronic monitors are useful for continuous surveillance but they are not substitutes for direct auscultation when precision is required. The technique is simple in theory and tedious in practice when you have twenty patients to cover. The accuracy gain is real, though, particularly for patients with arrhythmias, compromised perfusion, or those on medications that affect cardiac output. I have seen too many documentation errors traced back to someone checking the radial instead of the apical. It is a small step that prevents larger mistakes downstream.