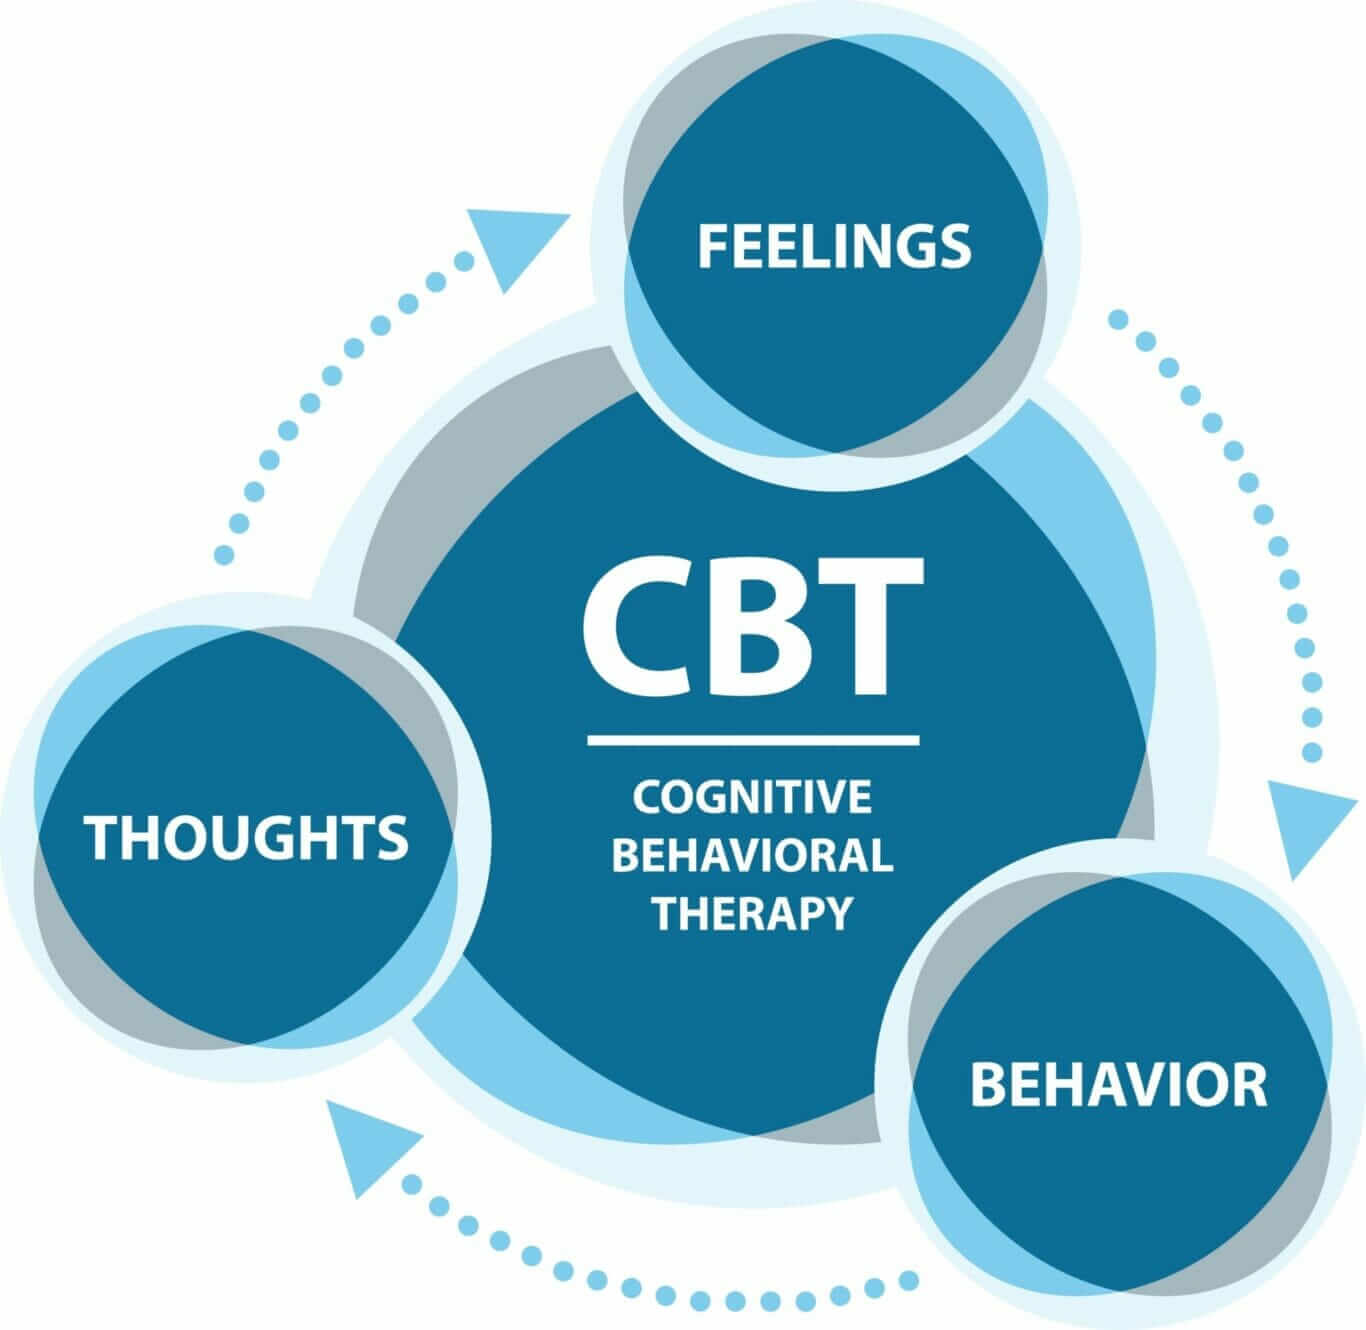
Understanding Cbt Therapy For Anxiety
I have spent more years than I want to admit working with anxiety disorders, mostly in clinical settings but also dealing with my own stress along the way. People come to me asking What Is Cbt Therapy For Anxiety and I usually start by telling them it is not what they expect. It is not a magic reframe that makes panic attacks disappear after one session. It is behavioral training with a cognitive component, and the results depend heavily on how rigorously you do the homework between sessions. The core mechanism is exposure combined with cognitive restructuring. You identify the thought patterns that feed the anxiety, challenge them against evidence, and then systematically expose yourself to the avoided situations until the nervous system habituates. That sounds straightforward until you are sitting in a grocery store with a racing heart because you made eye contact with someone and suddenly your brain decided this was a threat. That is where the theory meets reality.
What Is Cbt Therapy For Anxiety
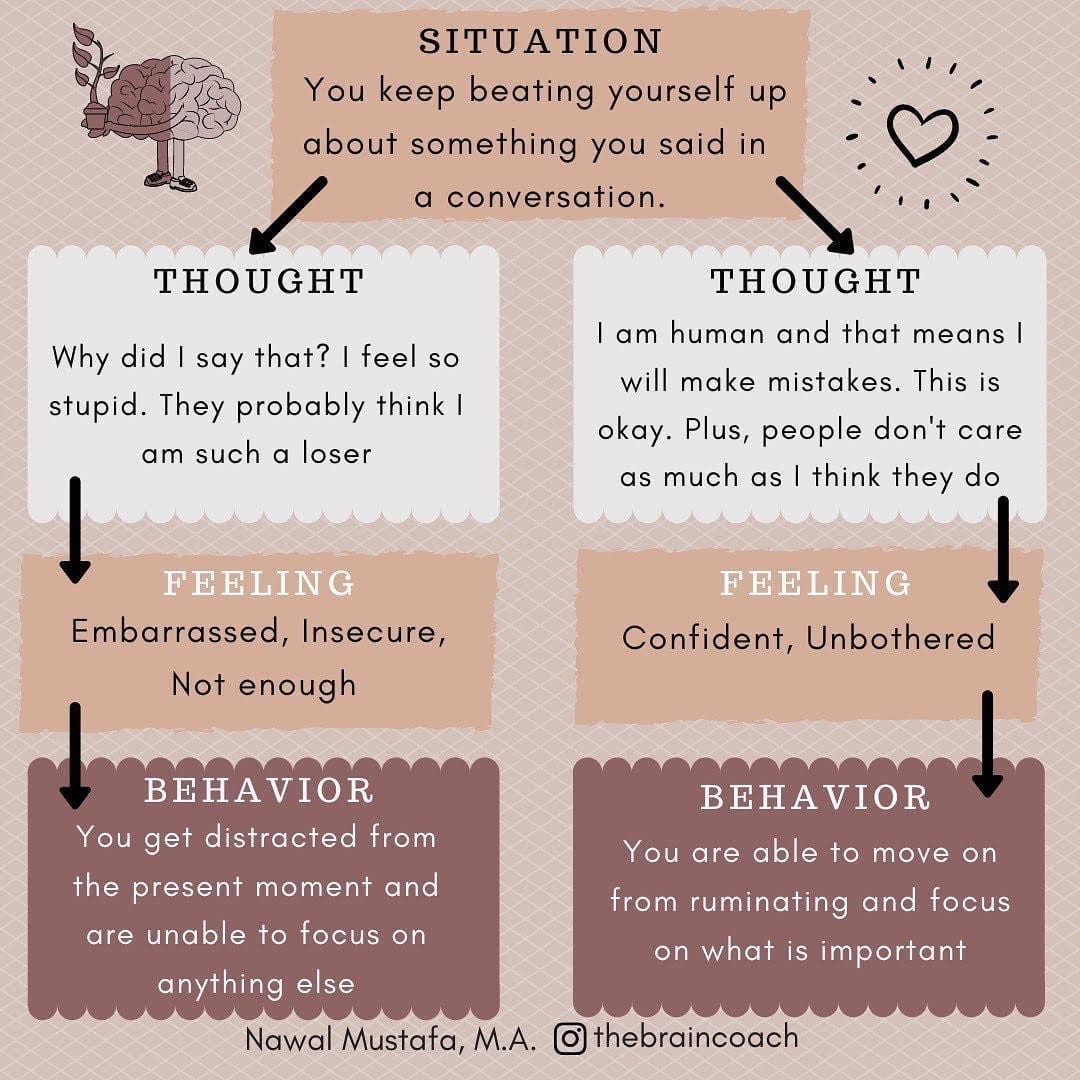
At its simplest, CBT for anxiety teaches you to catch the automatic thoughts that spiral into catastrophic predictions and run them through a reality test. When you think everyone is judging you, CBT asks you to write down what evidence actually supports that versus what evidence contradicts it. Most people find the evidence for the fear collapses under basic scrutiny. But the thought catching is only half of it. The exposure part is where the actual rewiring happens, and that is the part most clients skip because it feels terrible in the moment. I had a client once who had severe social anxiety and could not order food at a restaurant without going into a full panic. We built a hierarchy starting with ordering through a drive-thru window, then moving up to ordering from a cashier, then adding complications like asking for a substitution. She did her homework every week. By session eight she could handle most casual interactions. But then we hit a wall. She could order food fine, but if the waiter spoke fast or seemed impatient, she would freeze and apologize excessively. The original hierarchy did not account for unpredictable social tempo. The workaround was to introduce a new variable into the exposure: rushing. I had her practice ordering while I deliberately spoke faster and interjected questions mid-sentence. She had to learn to tolerate the discomfort of not having perfect control over the interaction. That specific edge-case taught me that anxiety hierarchies need a flexibility component. Standard templates assume a predictable fear ladder, but real life throws variability at you constantly. Without that component, clients relapse when something unexpected happens.
One thing beginners miss is that cognitive restructuring alone rarely produces lasting change. A 2019 meta-analysis in the Journal of Consulting and Clinical Psychology showed that exposure components account for significantly more variance in outcomes than cognitive techniques alone. You can reframe every catastrophic thought in the world, but if you still avoid the situation, your amygdala learns nothing new. The body keeps the score, not the prefrontal cortex. Another common pitfall is safety behaviors. Clients will go to the exposure but do it while clutching a water bottle, scrolling their phone, or rehearsing what they will say. These behaviors reduce anxiety in the moment but prevent full habituation. It is like practicing a piano piece while only using one finger. You get better at using one finger, not at playing the song. I tell clients to drop the crutches even if it feels unbearable for the first few minutes. The discomfort usually peaks around minute three and drops sharply after that. The typical course runs twelve to twenty sessions, with weekly visits and daily homework. Most people start noticing a measurable shift around session six if they actually do the exercises. Some improve faster, some slower. Age, comorbid conditions, and the severity of avoidance all factor in. There is no universal timeline.
Get the Full Details
CBT is not the right approach for everyone. If you have active psychosis, severe OCD without a separate exposure protocol, or substance dependence that is currently unmanaged, CBT alone will not cut it. In those cases you need a different starting point, usually medical stabilization first. Even for standard anxiety, CBT has a relapse rate of roughly twenty to thirty percent within the first year after treatment ends, particularly if the client stops practicing the skills. Alternatives exist. Acceptance and Commitment Therapy shares the same theoretical roots but emphasizes psychological flexibility over cognitive restructuring. It tends to work better for people who find the thought-challenging aspect too intellectual or argumentative. Mindfulness-based cognitive therapy combines elements of both and shows decent results for recurrent anxiety, though the evidence base is slightly smaller. Exposure and Response Prevention is the gold standard for OCD specifically and should not be conflated with general anxiety CBT. If you are considering CBT, look for a licensed clinician who specializes in anxiety disorders and who actually assigns homework. The therapist who just talks about your feelings without giving you structured exercises between sessions is not doing CBT, regardless of what they call it. The treatment is in the practice, not in the conversation. A good therapist will spend maybe forty percent of session time on review and twenty percent on teaching new concepts, leaving the rest for in-session exercises and planning. If your sessions feel like casual therapy with anxiety labeled onto them, it is probably time to find someone else.
The homework itself usually takes between thirty and sixty minutes per week for mild to moderate cases. Severe cases with high avoidance can require two hours or more. This is not a minor commitment. People who treat it as optional tend to see minimal improvement. The data is pretty consistent across studies. One practical tip that most guides skip: record your exposure sessions. Your brain will convince you that the anxiety was manageable during the exercise, but the memory fades within hours. A three-minute phone recording of you describing the fear before the exposure and after gives you concrete evidence for the next session. It also helps you track patterns over time that you would otherwise miss. Another detail worth noting is that CBT for anxiety works best when you target the specific maintaining factors, not just the surface symptoms. Sleep disruption, caffeine intake, and lack of physical activity can mimic or amplify anxiety symptoms to the point where therapy stalls. I routinely ask clients about their sleep and stimulant use before diving deep into exposure work. Fixing those basics alone sometimes reduces anxiety severity by a third without any formal intervention.
The bottom line is that CBT for anxiety is effective when delivered properly and practiced consistently. It is not a quick fix, it does not work for every presentation, and the exposure component is genuinely uncomfortable for most people. But the alternative, which is avoiding life until anxiety shrinks it to an unbearable size, is worse. Most clients who push through the initial resistance see significant improvement within three months. If you want to find a provider, the Association for Behavioral and Cognitive Therapies website has a directory, and the Anxiety and Depression Association of America maintains another. Both let you filter by specialty and location. Insurance coverage varies, so call your provider before booking and ask specifically about CBT for anxiety disorders, not just general therapy. Some plans distinguish between them.




