
How Neurovascular Assessment Actually Works in Practice
The neurovascular assessment is the routine check clinicians perform to make sure blood flow and nerve function remain intact after an injury, surgery, or immobilization. It sounds simple on paper, but the details matter because missing early signs of compromised circulation can mean the difference between a quick fix and a permanent problem. I am going to walk through how this is done step by step, where people routinely go wrong, and what to do when the standard protocol does not give you a clear answer. At its core, a neurovascular assessment evaluates perfusion and neurological status in a specific region, most often a limb. Clinicians check motor function, sensation, capillary refill, pulse distal to the injury or surgical site, skin color, and temperature. The framework most people learn is the Six P method: Pain, Pallor, Pulselessness, Paresthesia, Paralysis, and Poikilothermia. The order of priority matters though. Pain and paresthesia are usually the earliest indicators that something is wrong, while pulselessness and pallor often appear later when the situation has already escalated significantly. I have seen this exact sequence play out badly in a post-op orthopedic patient. The team was focused on checking pulses and documenting everything as present and normal. But the patient kept reporting a deep, unrelenting ache in the affected leg that did not respond to the prescribed analgesics. The pulses were still palpable. What we eventually identified was compartment syndrome, and the delayed recognition cost us valuable time. That episode changed how I approach these assessments going forward. Pain that is disproportionate to the injury or surgery, especially pain that worsens with passive stretching of the muscles, should raise a red flag even when everything else looks fine on paper.
The Step-by-Step Process
Start with inspection. Look at the affected limb and compare it to the opposite side. Note any swelling, discoloration, or visible deformity. Skin that is unusually pale, blue, or mottled is an immediate signal to investigate further and document the findings precisely. Check skin temperature by gently touching the area with the back of your hand. Cool skin distal to the injury suggests reduced perfusion. Warm or hot skin can indicate inflammation or infection, which also affects outcomes. Next assess capillary refill. Press firmly on a nail bed or the palmar surface of the fingers until the area blanches, then release. Normal refill takes two seconds or less. Slower refill times point toward circulation problems. Do this on both limbs for comparison. If the patient has darkly pigmented skin, nail beds are unreliable, so press on the palm or the anterior aspect of the tibia instead. This is a detail that gets skipped too often in clinical settings. Palpate pulses distal to the affected area. For an upper extremity injury, check the radial and ulnar pulses. For a lower extremity issue, assess the dorsalis pedis and posterior tibial pulses. Record the strength on a standard scale, typically zero through three, with three being a normal strong pulse. Absent pulses are a late finding. Doppler ultrasound should be used if you cannot locate a pulse by palpation. Most emergency departments and inpatient units have handheld Doppler devices available, and learning to use one properly saves a lot of guesswork.
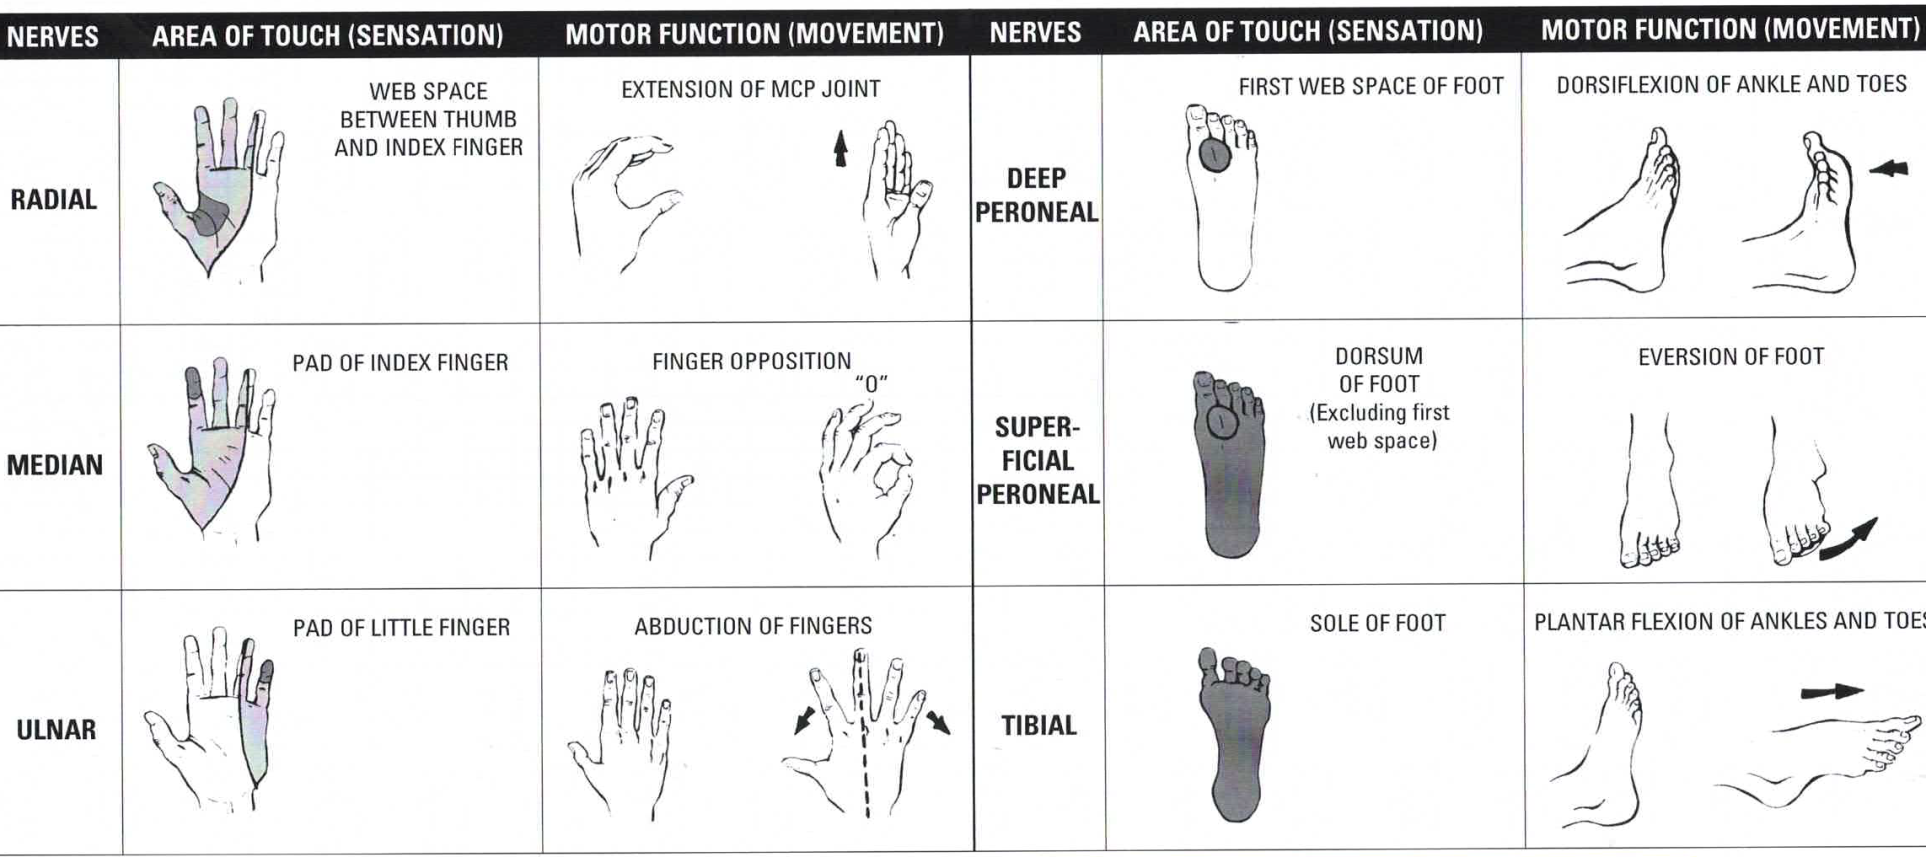
Motor function comes next. Ask the patient to move their fingers or toes through their full range of motion. In an unconscious or sedated patient, observe spontaneous movement or apply gentle pressure to elicit a response. Inability to move a limb may indicate nerve damage or severe ischemia. Document the specific movements the patient can and cannot perform rather than a vague good or poor label. Sensation assessment requires the patient to report whether they feel touch and pressure. Use a light touch with a cotton wisp or your fingers and compare both sides. Also test for sensation using a sharp object like a safety pin, but only if appropriate for the clinical context. Numbness or tingling, which patients describe as paresthesia, is an early warning sign of nerve compromise. Loss of sensation indicates that the problem has progressed further. Pain assessment is often the most subjective element, but it is also frequently the most informative. Ask the patient to rate their pain on a standard scale and note whether it is constant or intermittent. Pain that increases when you passively stretch the affected muscles is a particularly important finding. Document the exact location, character, and intensity. If the pain pattern changes over time, repeat the full assessment and note the progression. These assessments should be documented at regular intervals, typically every fifteen to thirty minutes in acute settings and at least every four hours on general wards, depending on institutional policy.
Get the Full Details

Common Mistakes and Shortcuts to Avoid
The biggest mistake I see is relying solely on pulse checks. A palpable pulse does not guarantee adequate tissue perfusion. You can have intact pulses and still have compromised capillary-level circulation. Always combine pulse assessment with capillary refill, temperature checks, and sensory evaluation. Relying on one component alone gives a false sense of security. Another frequent error is comparing the affected limb to nothing at all. Without a baseline on the contralateral side, your assessment lacks context. A slightly cool foot might look normal until you realize the other foot is noticeably warmer. Take a moment to check both sides before drawing conclusions. Documentation quality is another area where standards slip. Writing that neurovascular status is intact without recording the actual findings is not documentation. Future clinicians need to see the specific pulse strengths, capillary refill times, and sensory responses. Vague notes are useless when the patient condition changes and someone needs to track the timeline.
There is also a persistent tendency to dismiss reports of increasing pain as simply part of the expected post-injury or post-surgical course. Dismissing pain without a thorough reassessment has led to delayed diagnoses of compartment syndrome and other serious complications in my experience. When a patient reports worsening pain, especially pain that is out of proportion to what you would expect, take it seriously and reassess immediately rather than assuming it will resolve on its own.
When Standard Assessment Falls Short
Neurovascular assessment has real limitations that beginners rarely encounter because they have not been in the room enough. In obese patients, distal pulses are difficult to palpate regardless of circulatory status. In patients with peripheral arterial disease, capillary refill and pulse strength may be chronically altered and do not necessarily reflect acute changes. Elderly patients often have baseline sensory deficits from conditions like diabetic neuropathy, making sensation assessments less reliable for detecting new problems. When clinical assessment is inconclusive, compartment pressure measurement is the next step. This involves inserting a needle connected to a pressure monitor into the affected compartment. Pressures above thirty millimeters of mercury are generally considered indicative of compartment syndrome and may require fasciotomy. Some institutions use the delta pressure method, subtracting the compartment pressure from the diastolic blood pressure, with a delta below thirty considered concerning. Bioimpedance spectroscopy and near-infrared spectroscopy are emerging tools that can provide additional data on tissue perfusion when clinical assessment is ambiguous, though these are not yet universally available in all care settings. When in doubt, and the clinical picture does not fully align with your assessment findings, consult a specialist rather than waiting for multiple parameters to deteriorate simultaneously.
Quick Reference: Assessment Interval Guidelines
Acute trauma or post-operative orthopedic patients: every fifteen to thirty minutes for the first two hours, then every hour for four hours, then every four hours once stable. Post-cast or post-splint application: assess within thirty minutes of application and then every hour for the first four hours. Medical patients on anticoagulation with suspected limb ischemia: every one to two hours depending on severity. These are general guidelines and institutional protocols may vary, so always follow your facility's specific policies. The neurovascular assessment is not a checkbox exercise. It is a systematic evaluation that requires attention to detail, comparison to baselines, and a willingness to act when findings do not match the expected clinical picture. The techniques are straightforward, but the consequences of performing them poorly are significant. Pay attention to the early signs, document accurately, and escalate when something feels off even if you cannot immediately pinpoint why.


