Oral Language Development, Explained Without the Textbook Stuff
Oral language development is the process by which a person builds the ability to understand and produce spoken language over time. It starts at birth and continues shaping well into adolescence, sometimes even adulthood when people are learning new dialects or second languages. The core components are listening, speaking, vocabulary growth, grammar internalization, and pragmatic competence — knowing how to use language appropriately in different social situations. When parents and educators ask what is oral language development, they are usually looking for a practical answer they can apply. Here is the honest version: it is the accumulation of auditory input paired with active verbal output, reinforced through repetition and social feedback. A child hears a word, associates it with meaning, attempts to say it, and gets corrected or confirmed by a caregiver. That loop builds the neural pathways required for fluent speech. The tricky part is that timing is not symmetrical across all learners. Some children hit major milestones like combining two words by eighteen months. Others do not speak in full sentences until they are three or four. Neither outcome is automatically a red flag, but prolonged delays without any compensatory communication — pointing, gesturing, vocalizing — warrant evaluation. This is where people often misinterpret the landscape.
I worked with a five-year-old who had been labeled late-talking because he only used single words past his third birthday. His parents assumed he was behind. He was not. He had a severe auditory processing gap tied to chronic ear infections throughout infancy. Once we addressed the medical issue and introduced structured listening therapy, his vocabulary exploded within six months. The takeaway: always rule out sensory or medical barriers before labeling a child underdeveloped in oral language.
How Oral Language Actually Develops in Practice
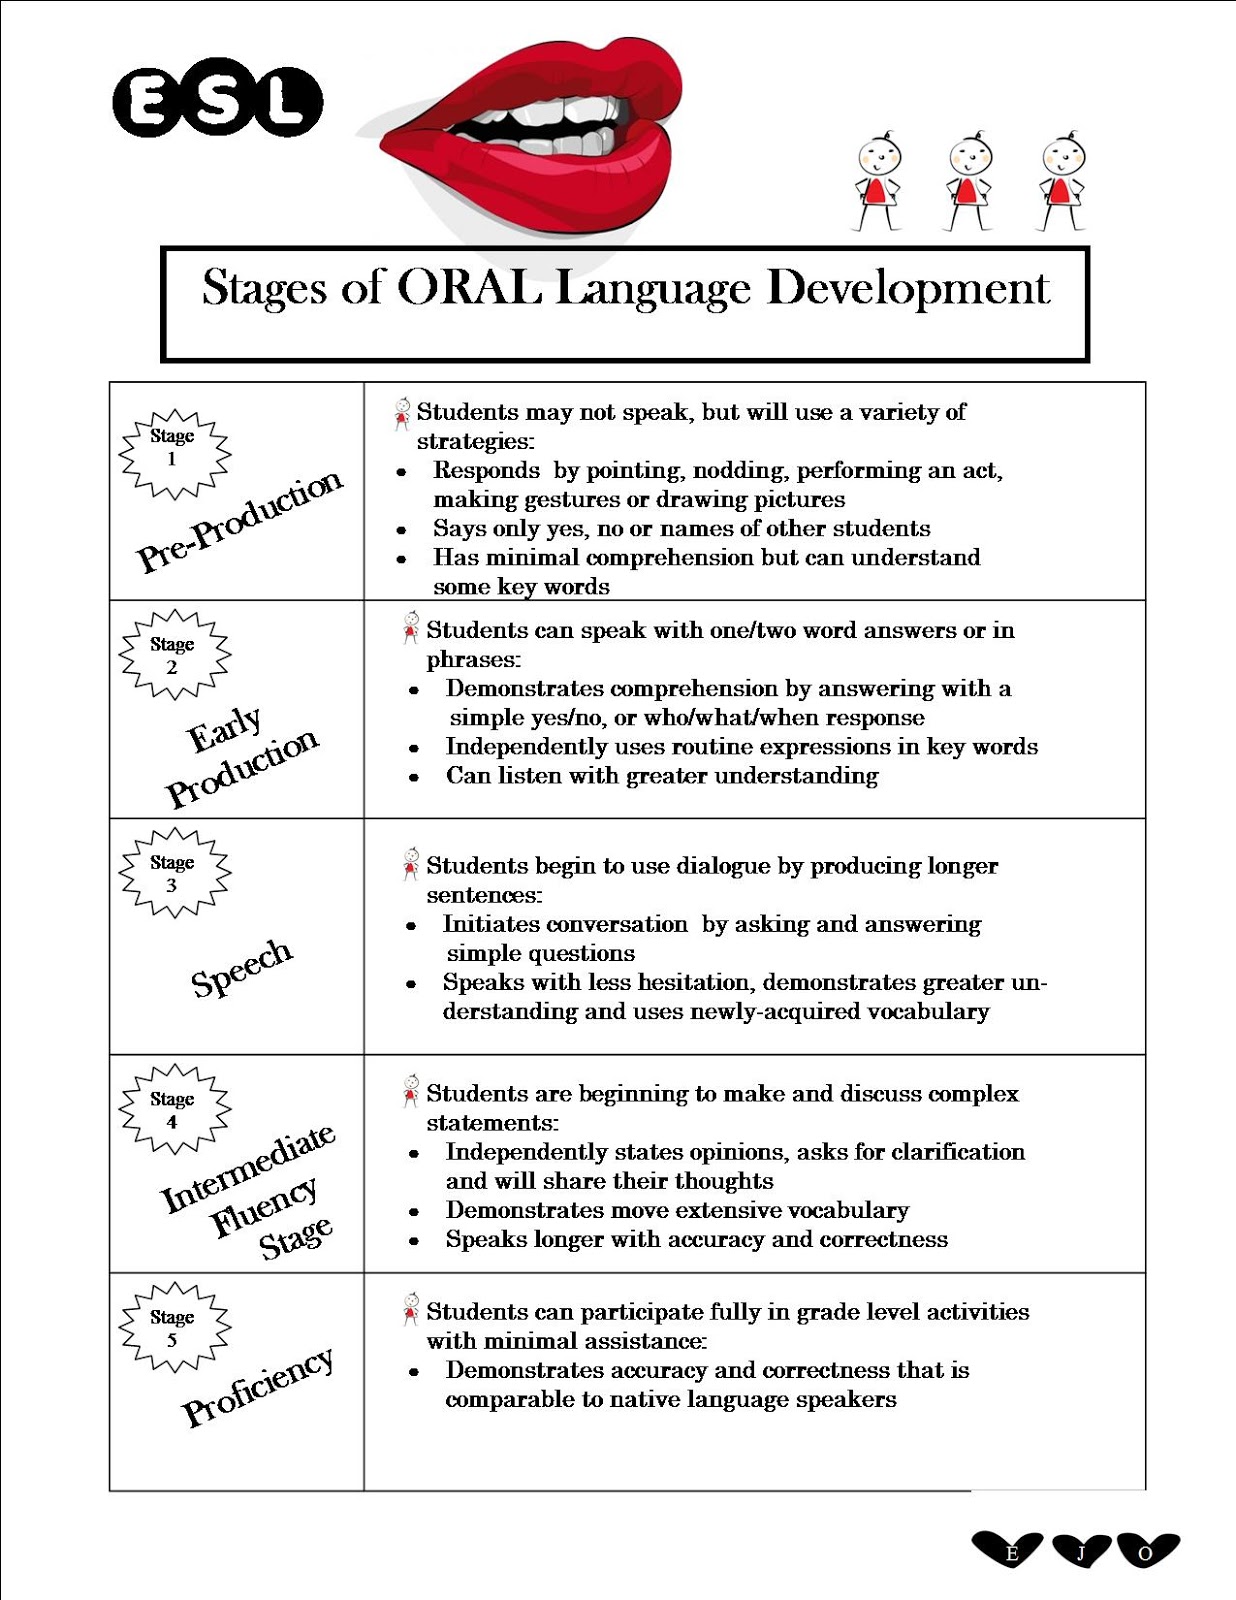
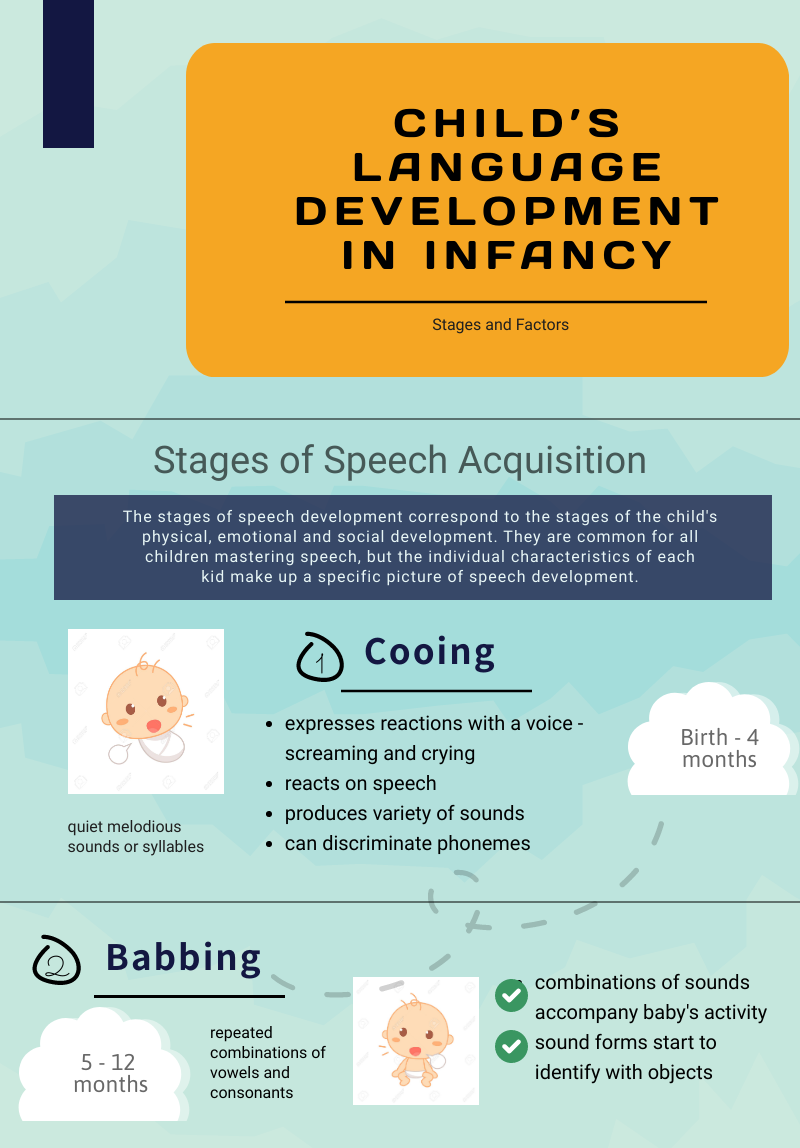
Development moves through stages, but the stages are messy. Children do not march neatly from babbling to words to sentences. They oscillate. A toddler might use a three-word sentence one day and regress to two-word phrases the next after a disruption like a move, a new sibling, or illness. Regression is normal and should not be mistaken for permanent loss of progress. Receptive language — what a person understands — always precedes expressive language — what they produce. You will see this pattern repeatedly. A child comprehends far more than they can say. If you ask them to point to a "dog" in a picture book, they will find it correctly. But if you ask them to name the animal, they might say "woof" instead. That gap between comprehension and production is the training ground where oral language development happens. Vocabulary growth is exponential during the preschool years. Research from the Hart and Risley study estimated that children from language-rich homes hear roughly forty-five million more words by age three than children from language-poor environments. The difference is not just quantity — it is the diversity of sentence structures, the range of topics, and the frequency of back-and-forth dialogue. One-way exposure like television does not produce the same results. The brain needs interaction to wire the connections properly.
Get the Full Details

Common Pitfalls That Sabotage Oral Language Progress
The biggest mistake parents and even some educators make is focusing exclusively on speech output while neglecting the listening side. Oral language is not just talking. It is hearing, processing, storing, and retrieving. If you only push a child to repeat words or recite phrases, you are training performance, not development. Another pitfall is correcting every error in real time. When a child says "I runned to the park," stopping them to say "No, it is ran, not runned" interrupts the communicative flow and can make them hesitant to speak. The research supports a strategy called recasting. You simply model the correct form naturally in your response: "Oh, you ran to the park? That is exciting." The child hears the correct grammar embedded in meaningful conversation without feeling policed. Screentime is also a factor, but not in the way most people think. Background television does not contribute to oral language development and can actively reduce parent-child conversation. The screen does not respond to the child. It does not adjust its vocabulary to the child's level. Interactive media designed for language learning exists, but even those cannot replace human dialogue. Two hours of screen time per day is generally considered the upper limit for children under five by most pediatric guidelines.
Assessment and Intervention Approaches
If you are working with someone who has a gap in oral language, the first step is formal assessment. Speech-language pathologists use standardized tools like the Clinical Evaluation of Language Fundamentals (CELF) or the Preschool Language Scales (PLS) to measure receptive and expressive abilities against age norms. These tests give you a baseline. Without a baseline, you are guessing. Intervention varies by age and severity. For young children, the most effective approach is language stimulation — increasing the quantity and quality of linguistic input through reading, conversation, and play-based activities. For older children and adults with more entrenched difficulties, direct therapy targeting specific deficits like morphological awareness or narrative structure is necessary. I encountered a case involving a seventh grader who could read at a ninth-grade level but spoke with a fifth-grade vocabulary and struggled to construct coherent paragraphs orally. His receptive vocabulary was strong, but his expressive oral skills lagged significantly. This is a classic dissociation that standardized tests sometimes miss because they focus on single domains. The workaround was structured oral narration exercises — having him describe events, retell stories, and explain processes out loud while recording and reviewing his own speech. Within four months, his expressive vocabulary expanded noticeably and his oral coherence improved.
What Is Oral Language Development in Non-Traditional Learners?
Children with autism, hearing impairments, or intellectual disabilities follow different trajectories. The fundamental mechanism — input leading to output through feedback — remains the same, but the pathways to get there are different. For autistic children, oral language development may require visual supports, augmentative and alternative communication (AAC) devices, and explicit teaching of pragmatic language rules that neurotypical children absorb intuitively. For deaf or hard-of-hearing children, signed language counts as oral language development only if you are using a strict definition of oral as spoken. More accurately, signed language is a complete linguistic system that engages the same cognitive mechanisms. Many deaf children benefit from bilingual-bicultural approaches that include both sign and spoken language, depending on residual hearing and family preference. Children raised in bilingual households develop oral language in two languages simultaneously. This is not a delay. Bilingual children may have smaller vocabularies in each individual language compared to monolingual peers, but their combined conceptual vocabulary is typically equal or greater. The important factor is consistent exposure to both languages. Code-switching — alternating between languages mid-sentence — is normal and indicates flexibility, not confusion.

Tools and Resources That Actually Help
Reading aloud daily is the single most evidence-backed activity for oral language development. It exposes children to complex sentence structures, low-frequency vocabulary, and narrative patterns that everyday conversation does not provide. Even fifteen minutes per day makes a measurable difference over a school year. Conversation expansion is another simple technique. When a child says "look dog," you respond with "Yes, look at the big brown dog running." You are not correcting. You are expanding. This models more complex syntax without breaking the flow of interaction. For families seeking structured programs, resources like Head Start materials, Reach Out and Read initiatives, and apps such as Endless Words or Speakaboos can supplement home interaction. Therapeutic programs like Language Express or Expressive One-Word Picture Vocabulary Test based curricula are available through speech-language pathology practices.
No app or program replaces consistent human interaction. The human voice provides prosody, emotional context, and contingent responsiveness that technology cannot fully replicate. If you want to support oral language development, talk to the child, listen to what they say, and respond in ways that stretch their language just beyond their current level.