The Numbers You See On The Cuff Don't Tell The Whole Story
I spent years in primary care and cardiology before moving into clinical research, and I can tell you that most people treat blood pressure readings like they're gospel from the start of time. They aren't. The question of what is perfect blood pressure has generated more confusion in my inbox than just about anything else I've encountered, mostly because the targets have shifted multiple times over the past decade and the average person reading these guidelines online has no context for why. Here's how it actually works in practice. You sit down. You've been sitting for five minutes. Your back is supported, your feet are flat on the floor, your arm is at heart level, and you haven't talked during that entire wait. You get a reading. Then you get another one ten minutes later. Then a third. The first number is almost always higher than the others because your nervous system hasn't settled yet. I used to see people who would panic because their first reading was 150 over 95 and then walk out of the clinic thinking they had hypertension, when their average of the subsequent readings was perfectly fine. That white coat effect is real and measurable, and it accounts for a significant chunk of overdiagnosis.
What Is Perfect Blood Pressure
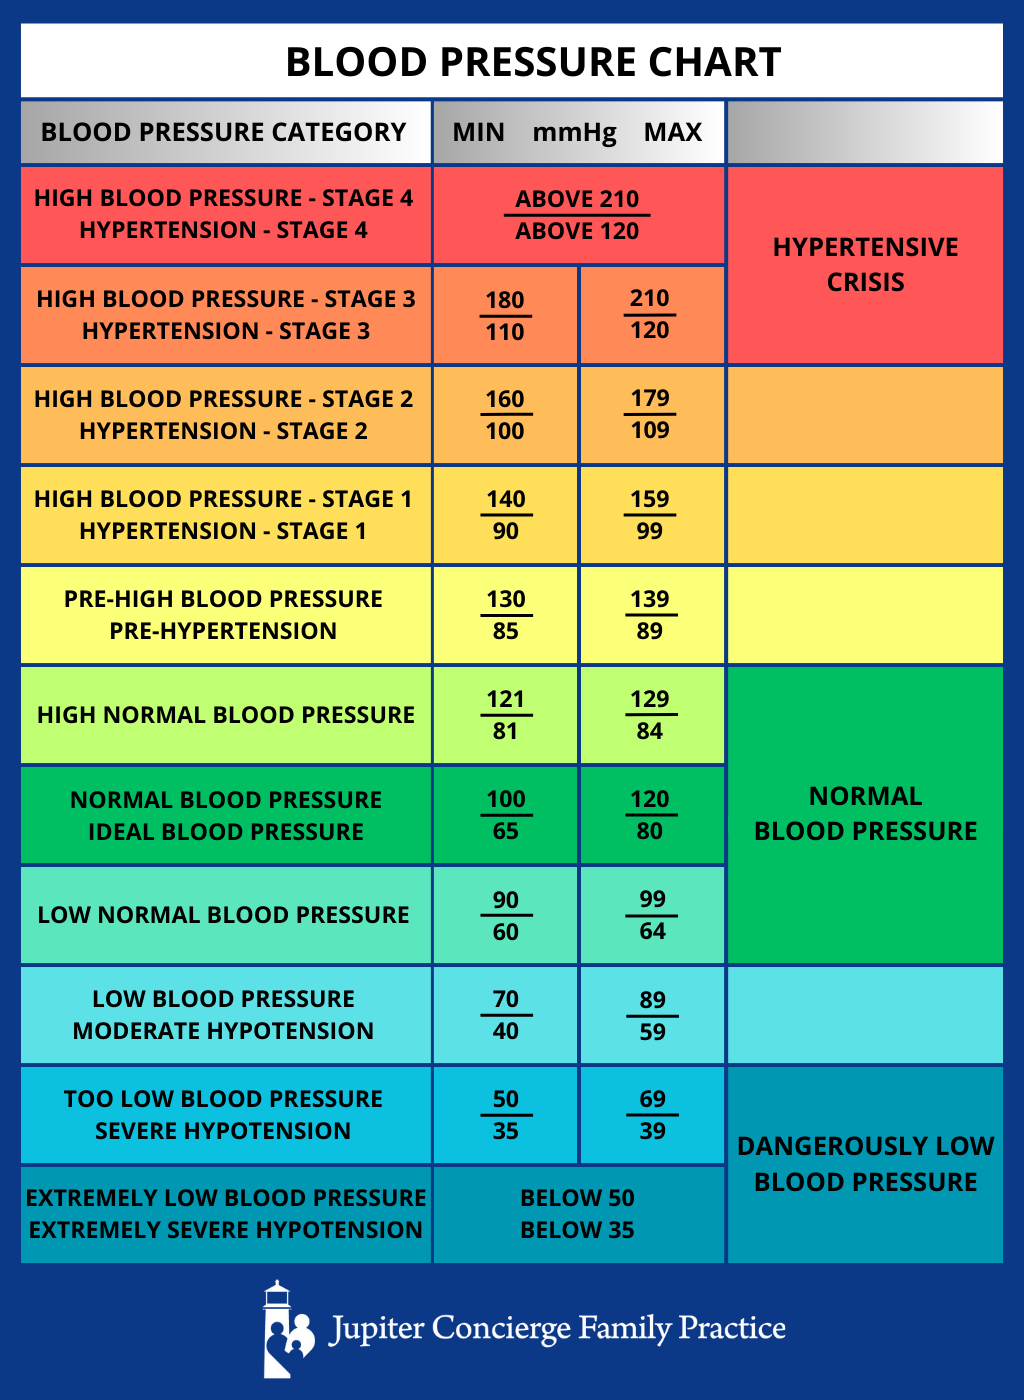
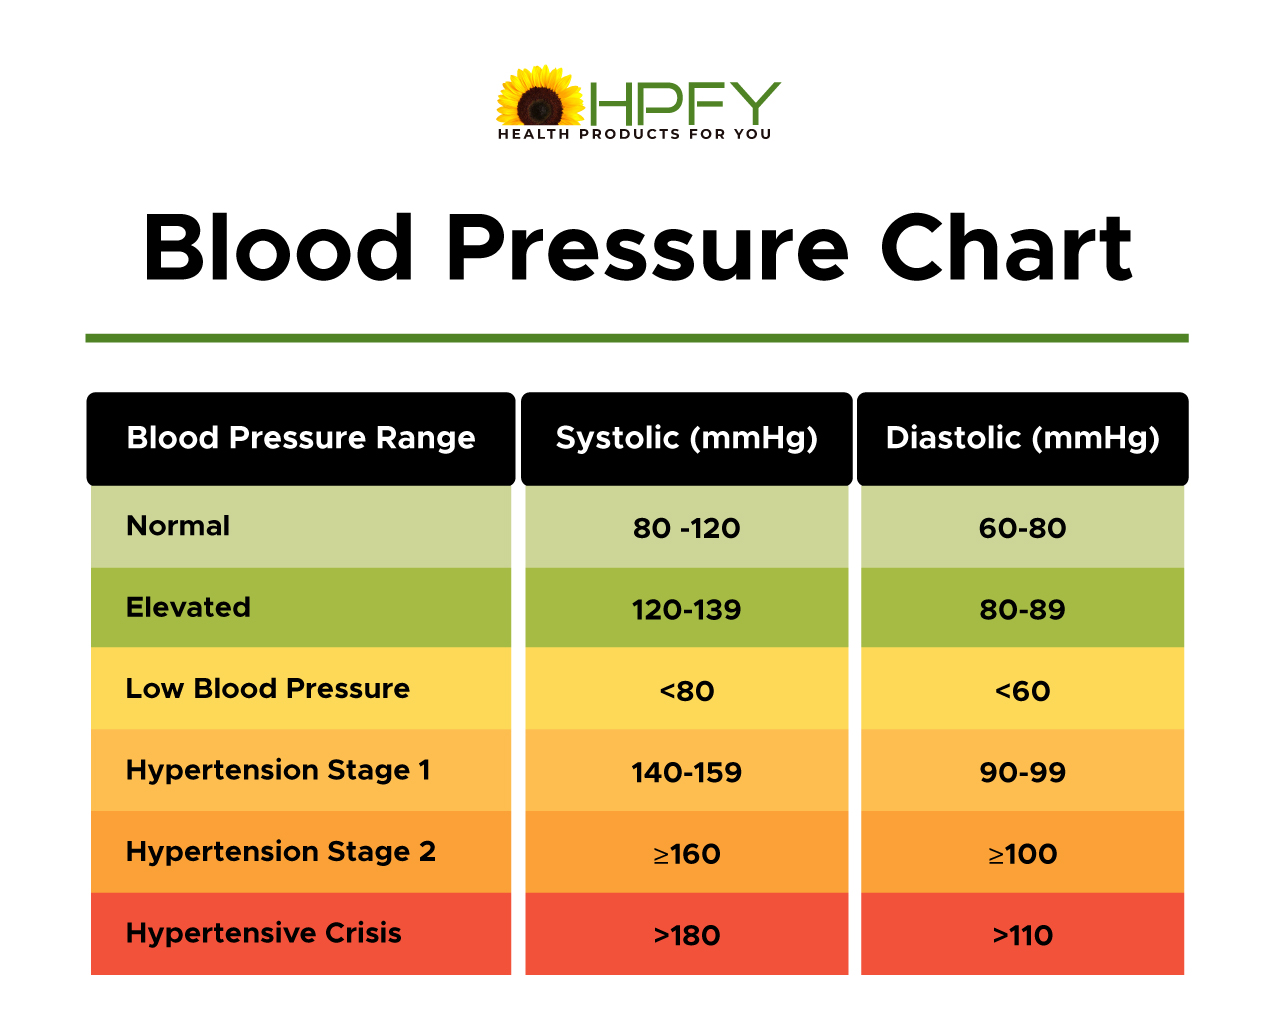
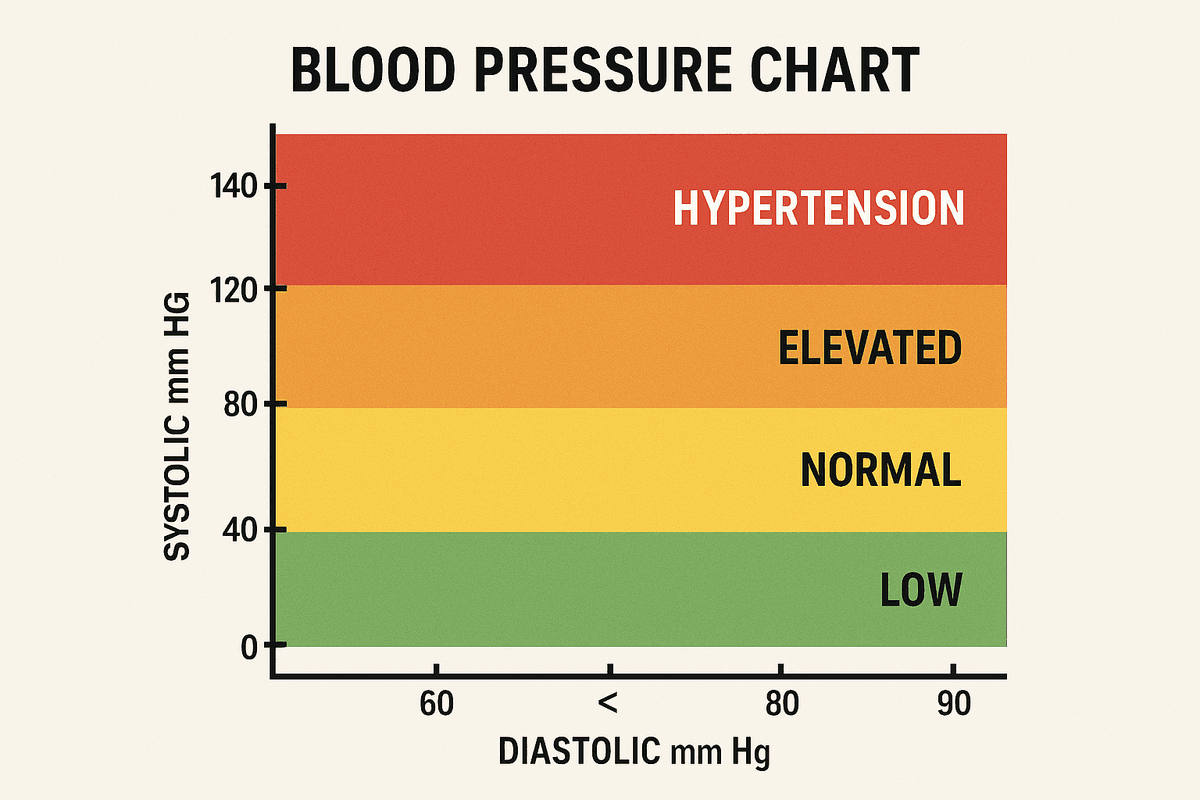
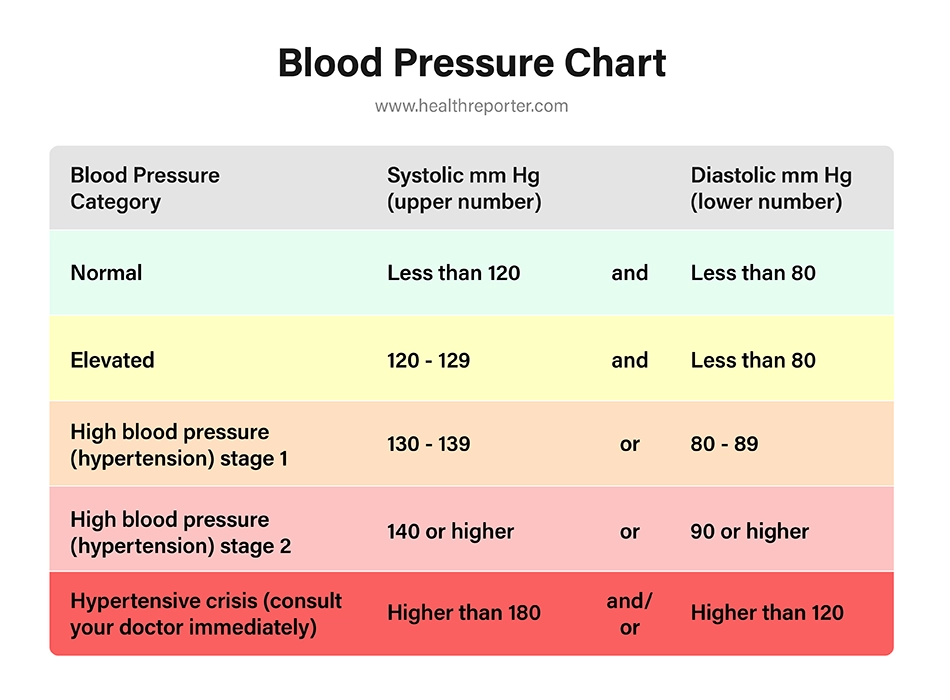
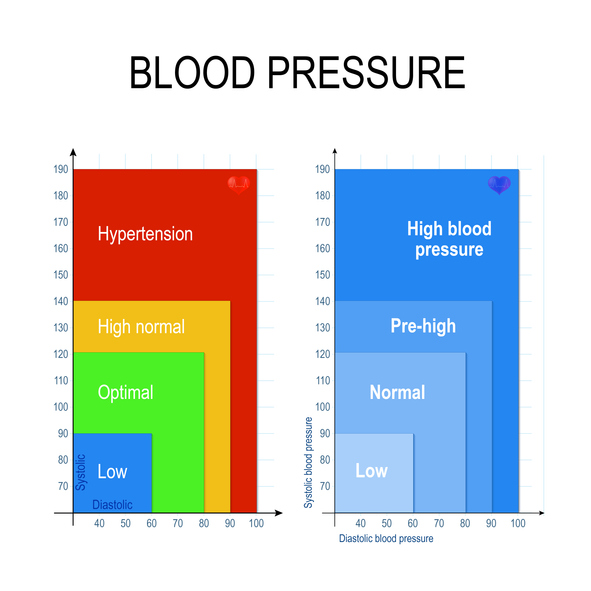
The short answer is below 120 over 80 millimeters of mercury, consistently. But that's the textbook definition that gets people in trouble because "consistently" means something very specific. It doesn't mean one good reading at the doctor's office. It means multiple readings taken under proper conditions across different days, or ideally ambulatory monitoring over a twenty-four hour period. The American College of Cardiology and the American Heart Association landed on this threshold around 2017 after the SPRINT trial showed that pushing systolic pressure down to around 120 in high-risk patients reduced cardiovascular events significantly compared to the old target of 140. Previous guidelines had set the bar much higher, which is why you still see references to 140 over 90 in older literature and in some international guidelines. The nuance that most people miss is that optimal isn't the same as lowest. Going too low can be dangerous, especially in older adults. In the SPRINT trial, the intensive treatment group did have a higher rate of hypotension, syncope, and acute kidney injury. So while 120 over 80 is the target for most non-elderly patients without comorbidities, aiming for 100 over 60 in a seventy-five-year-old with diabetes is generally not the right move. The J-curve phenomenon in blood pressure management is still debated but worth noting: below a certain threshold, organ perfusion suffers and outcomes actually worsen. For most people that floor sits somewhere around 100 systolic. I ran into a specific problem a few years back with a patient who had been diagnosed with resistant hypertension based on office readings in the 160s. We started him on three medications including a diuretic and an alpha-blocker, and his numbers barely moved. His pharmacy claimed he wasn't adhering, but he swore he was taking everything. The breakthrough came when we finally got him to do twenty-four hour ambulatory monitoring, and his average daytime reading was 128 over 76. His nighttime average was even lower. He didn't have hypertension at all. What he had was severe white coat syndrome, and he was essentially being treated for a condition he didn't possess. This happens more often than you'd expect. Roughly thirty percent of people labeled as hypertensive based on office measurements alone turn out to have normal blood pressure once you account for the clinical setting. That's not a small number.
Another edge case I want to flag is masked hypertension, which is the opposite problem. Someone walks into the clinic and their reading is 122 over 78, looks completely fine, and the physician clears them. But their average out-of-office reading is 145 over 90. This patient is getting no treatment for uncontrolled hypertension because the office measurement is misleadingly low. Masked hypertension carries roughly the same cardiovascular risk as sustained hypertension, so missing it is just as bad as the white coat misdiagnosis. If you're checking your blood pressure at home and it's consistently above 135 over 85, that's equivalent to a clinic reading of 140 over 90, regardless of what the doctor sees in person. Home monitoring is mandatory for accurate assessment in a lot of cases.
Get the Full Details
How To Actually Measure It Correctly
Most home monitors are reasonably accurate, but the process of using them incorrectly introduces more error than the devices themselves. I had a patient who brought in his home monitor for calibration and it was within three millimeters of mercury of our clinical standard. The device was fine. His technique was the problem. He was measuring while sitting on the couch with his arm dangling, talking on the phone, and doing it right after coming home from work without waiting. Every one of those factors inflates the reading. Sitting with your arm unsupported adds roughly five to ten millimeters of mercury. Talking during measurement adds another five to eight. Not waiting the full five minutes after activity adds variable amounts depending on how intense that activity was. Here's the practical protocol that actually works. Buy an upper-arm monitor with a validated cuff size. Wrist monitors are convenient but significantly less reliable unless you hold them at exact heart level, which most people can't do consistently. Sit in a chair with back support for five minutes before measuring. Place your arm on a table so the cuff is at heart level. Take two readings one minute apart. Do this morning and evening for a week. Record everything. Bring the log to your physician. The average of those readings is what matters, not any single number. If your average stays below 130 over 80 at home, you're in a good range. If it's consistently above 135 over 85, you need to talk to a doctor about next steps. There's a practical limitation here that worth being honest about. Home monitoring works well for motivated people who follow the protocol. It fails for people who measure sporadically, who get anxious about each reading and skew their own data, or who use cheaper monitors that drift out of calibration. I've seen monitors that read fifteen millimeters high after two years of normal use. Manufacturers recommend calibrating or replacing your monitor every one to two years, but most people never do this. If your home readings and office readings disagree substantially, get the monitor checked at a pharmacy or clinic.
What The Numbers Mean Beyond The Diagnosis
Systolic pressure, the top number, reflects the force against your arterial walls when your heart contracts. Diastolic, the bottom number, is the pressure when your heart rests between beats. Both matter, but their importance shifts with age. In younger patients under fifty, diastolic hypertension is more common and clinically significant. Above sixty, isolated systolic hypertension dominates because arterial stiffness increases with age and the aorta loses elasticity. This is why you'll see older adults with readings like 170 over 75. The pulse pressure of ninety-five is a marker of vascular aging and cardiovascular risk independent of the systolic number itself. A wide pulse pressure is its own warning sign. The relationship between blood pressure and outcomes isn't linear either. The risk of stroke and coronary events rises continuously from around 115 over 75 upward. There's no natural cutoff where risk suddenly appears, which is why the old category of "prehypertension" kept getting refined and redefined. The 2017 guidelines reclassified things by lowering the threshold for stage one hypertension to 130 over 80, largely because the evidence showed meaningful risk escalation starting at those levels. Some international bodies, particularly in Europe and parts of Asia, still use 140 over 90 as their diagnostic threshold, partly because they weigh the treatment harms more heavily at lower thresholds and partly because of differences in population risk profiles. One counter-intuitive point that people rarely consider is that blood pressure variability itself may be an independent risk factor. Two patients can have the same average blood pressure, but one has consistent readings while the other swings wildly between 110 and 160 systolic throughout the day. The volatile patient likely has worse outcomes. Ambulatory monitoring captures this kind of variability; single office readings don't. If you're trying to assess true cardiovascular risk, looking at variability matters more than any single number will ever tell you.
I also want to address the question of whether perfect blood pressure changes as you age. The idea that a reading of 140 over 90 is acceptable for an elderly person is widespread but not well-supported by the data. Age-adjusted targets exist in some guidelines for frail patients, but for healthy older adults, tighter control still reduces stroke and heart failure risk. The SPRINT trial included participants averaging around seventy-two years old and found clear benefit from intensive control. Frailty, not chronological age, should be the deciding factor in whether to push targets lower. The honest limitation of all of this is that blood pressure is only one piece of cardiovascular risk assessment. A patient with a resting pressure of 118 over 76 who smokes, has elevated LDL, and is diabetic is at higher risk than someone with a pressure of 128 over 82 who has normal lipids, doesn't smoke, and exercises regularly. Risk calculators like the ASCVD Pooled Cohort Equation incorporate blood pressure along with age, cholesterol, smoking status, and diabetes to give a ten-year risk estimate, and that estimate is far more useful clinically than the blood pressure number alone. Focusing exclusively on hitting a perfect target without looking at the broader risk picture is a narrow approach that misses important context.