Understanding Somatic Pain Beyond the Textbook Definition
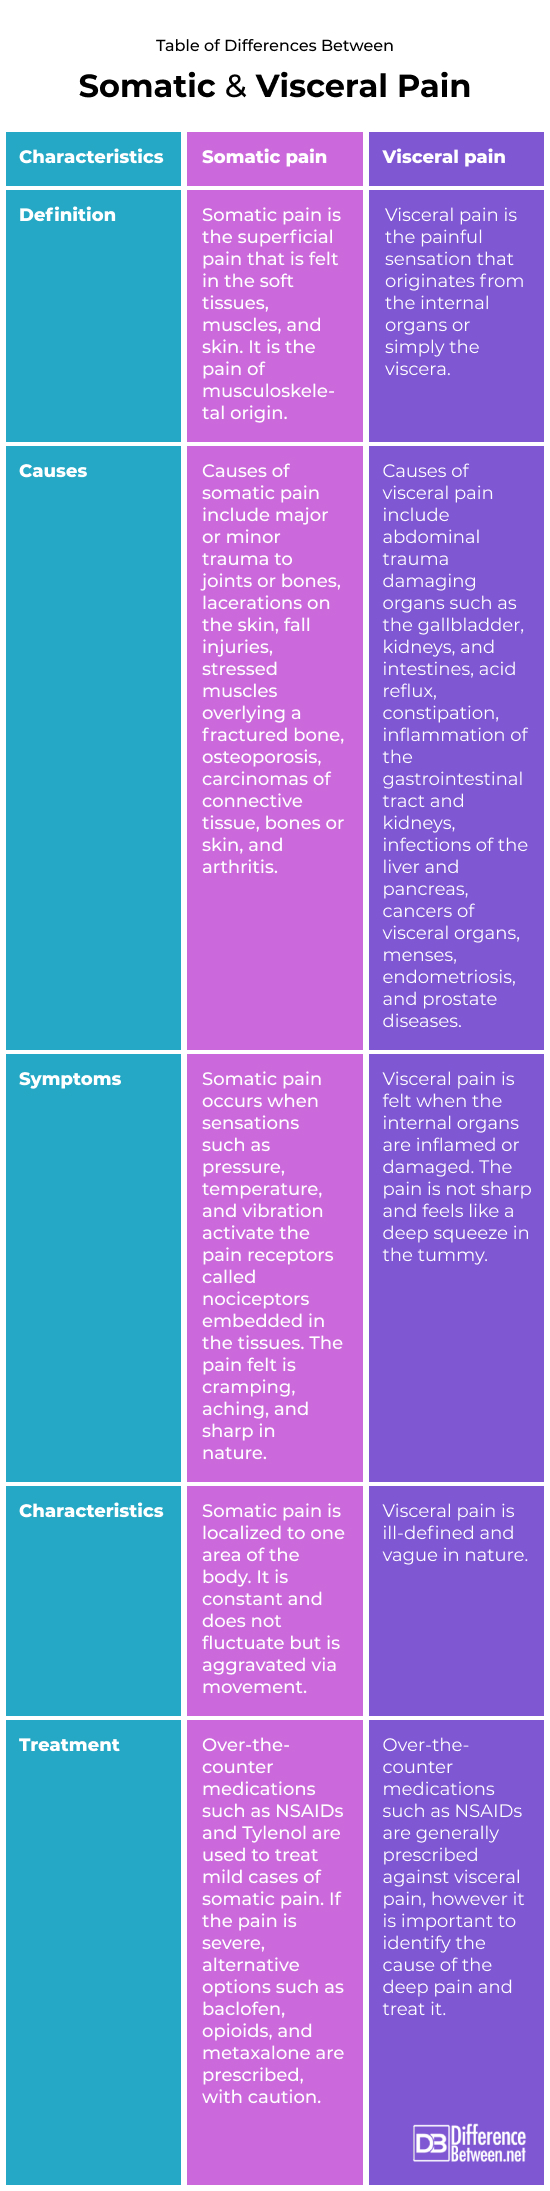
Somatic pain is pain that originates from the body's tissues rather than from internal organs or nerves misfiring. It comes from skin, muscles, bones, joints, and connective tissue. You feel it clearly localized to a specific area. A sprained ankle throbs with somatic pain. A muscle strain in your lower back does too. The distinction matters because treatment approaches differ significantly depending on whether the source is somatic, visceral, or neuropathic. I spent several years working with chronic pain patients and one thing kept coming up consistently: people confuse somatic and neuropathic pain all the time. A patient will come in describing what they're certain is somatic pain, but the presentation doesn't match. The pain crosses midline boundaries in ways somatic sources don't typically cross, or it has a burning quality that points toward nerve involvement rather than tissue damage. Getting this distinction right early on saves weeks of ineffective treatment.
What Is Somatic Pain and How Does It Actually Present?
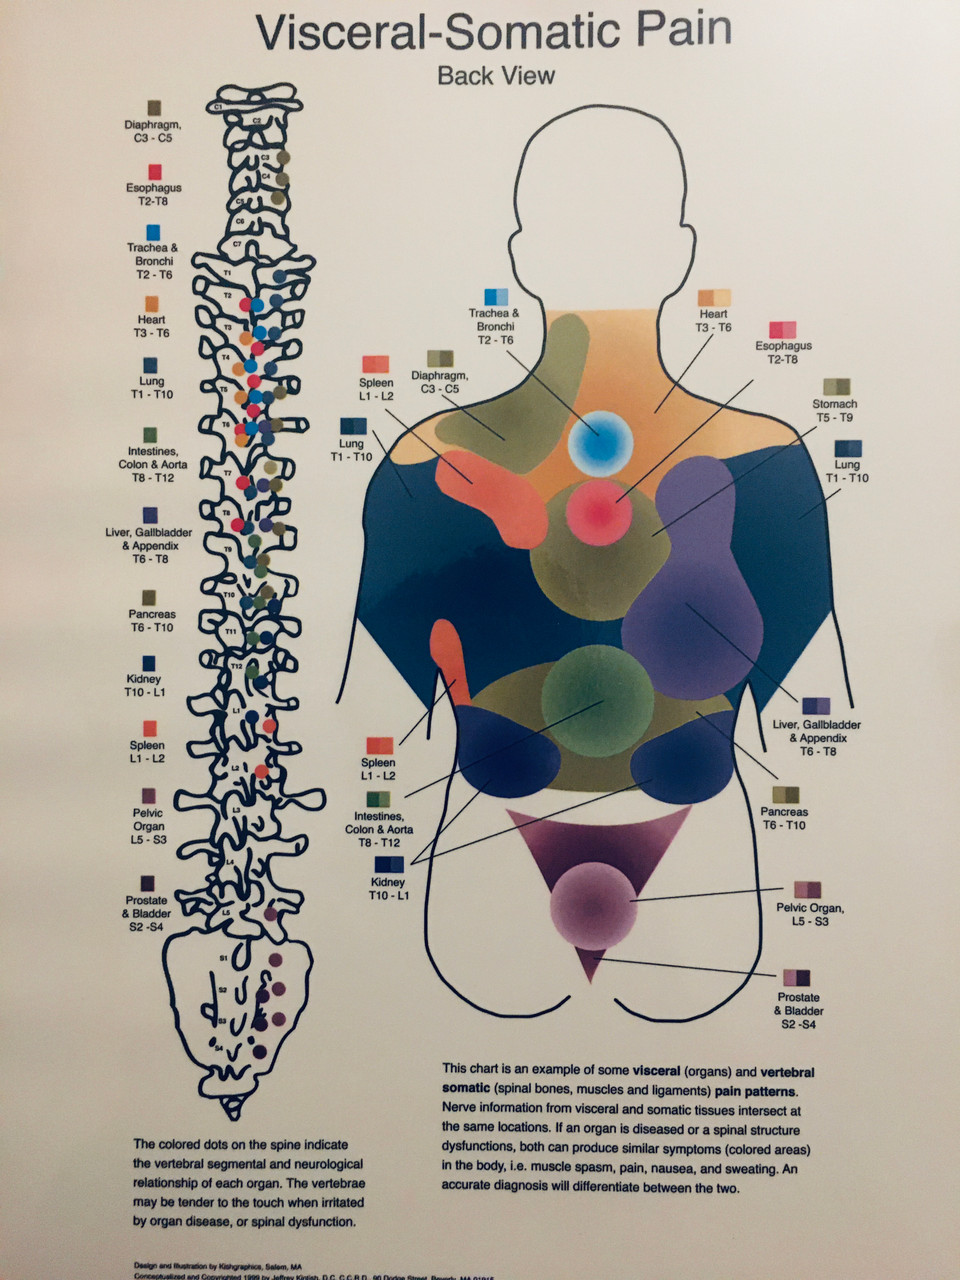
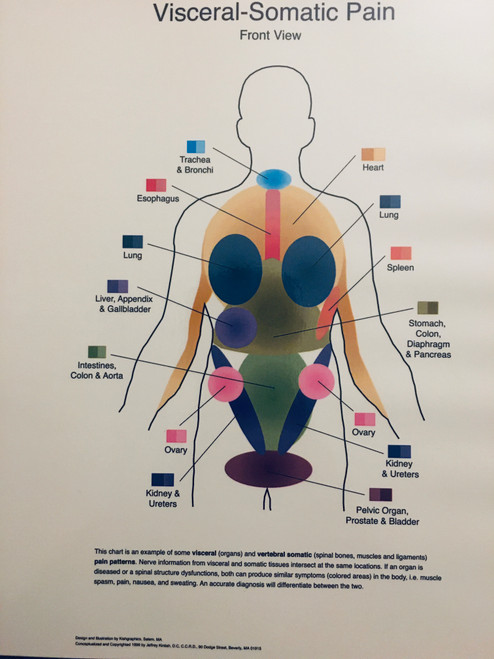
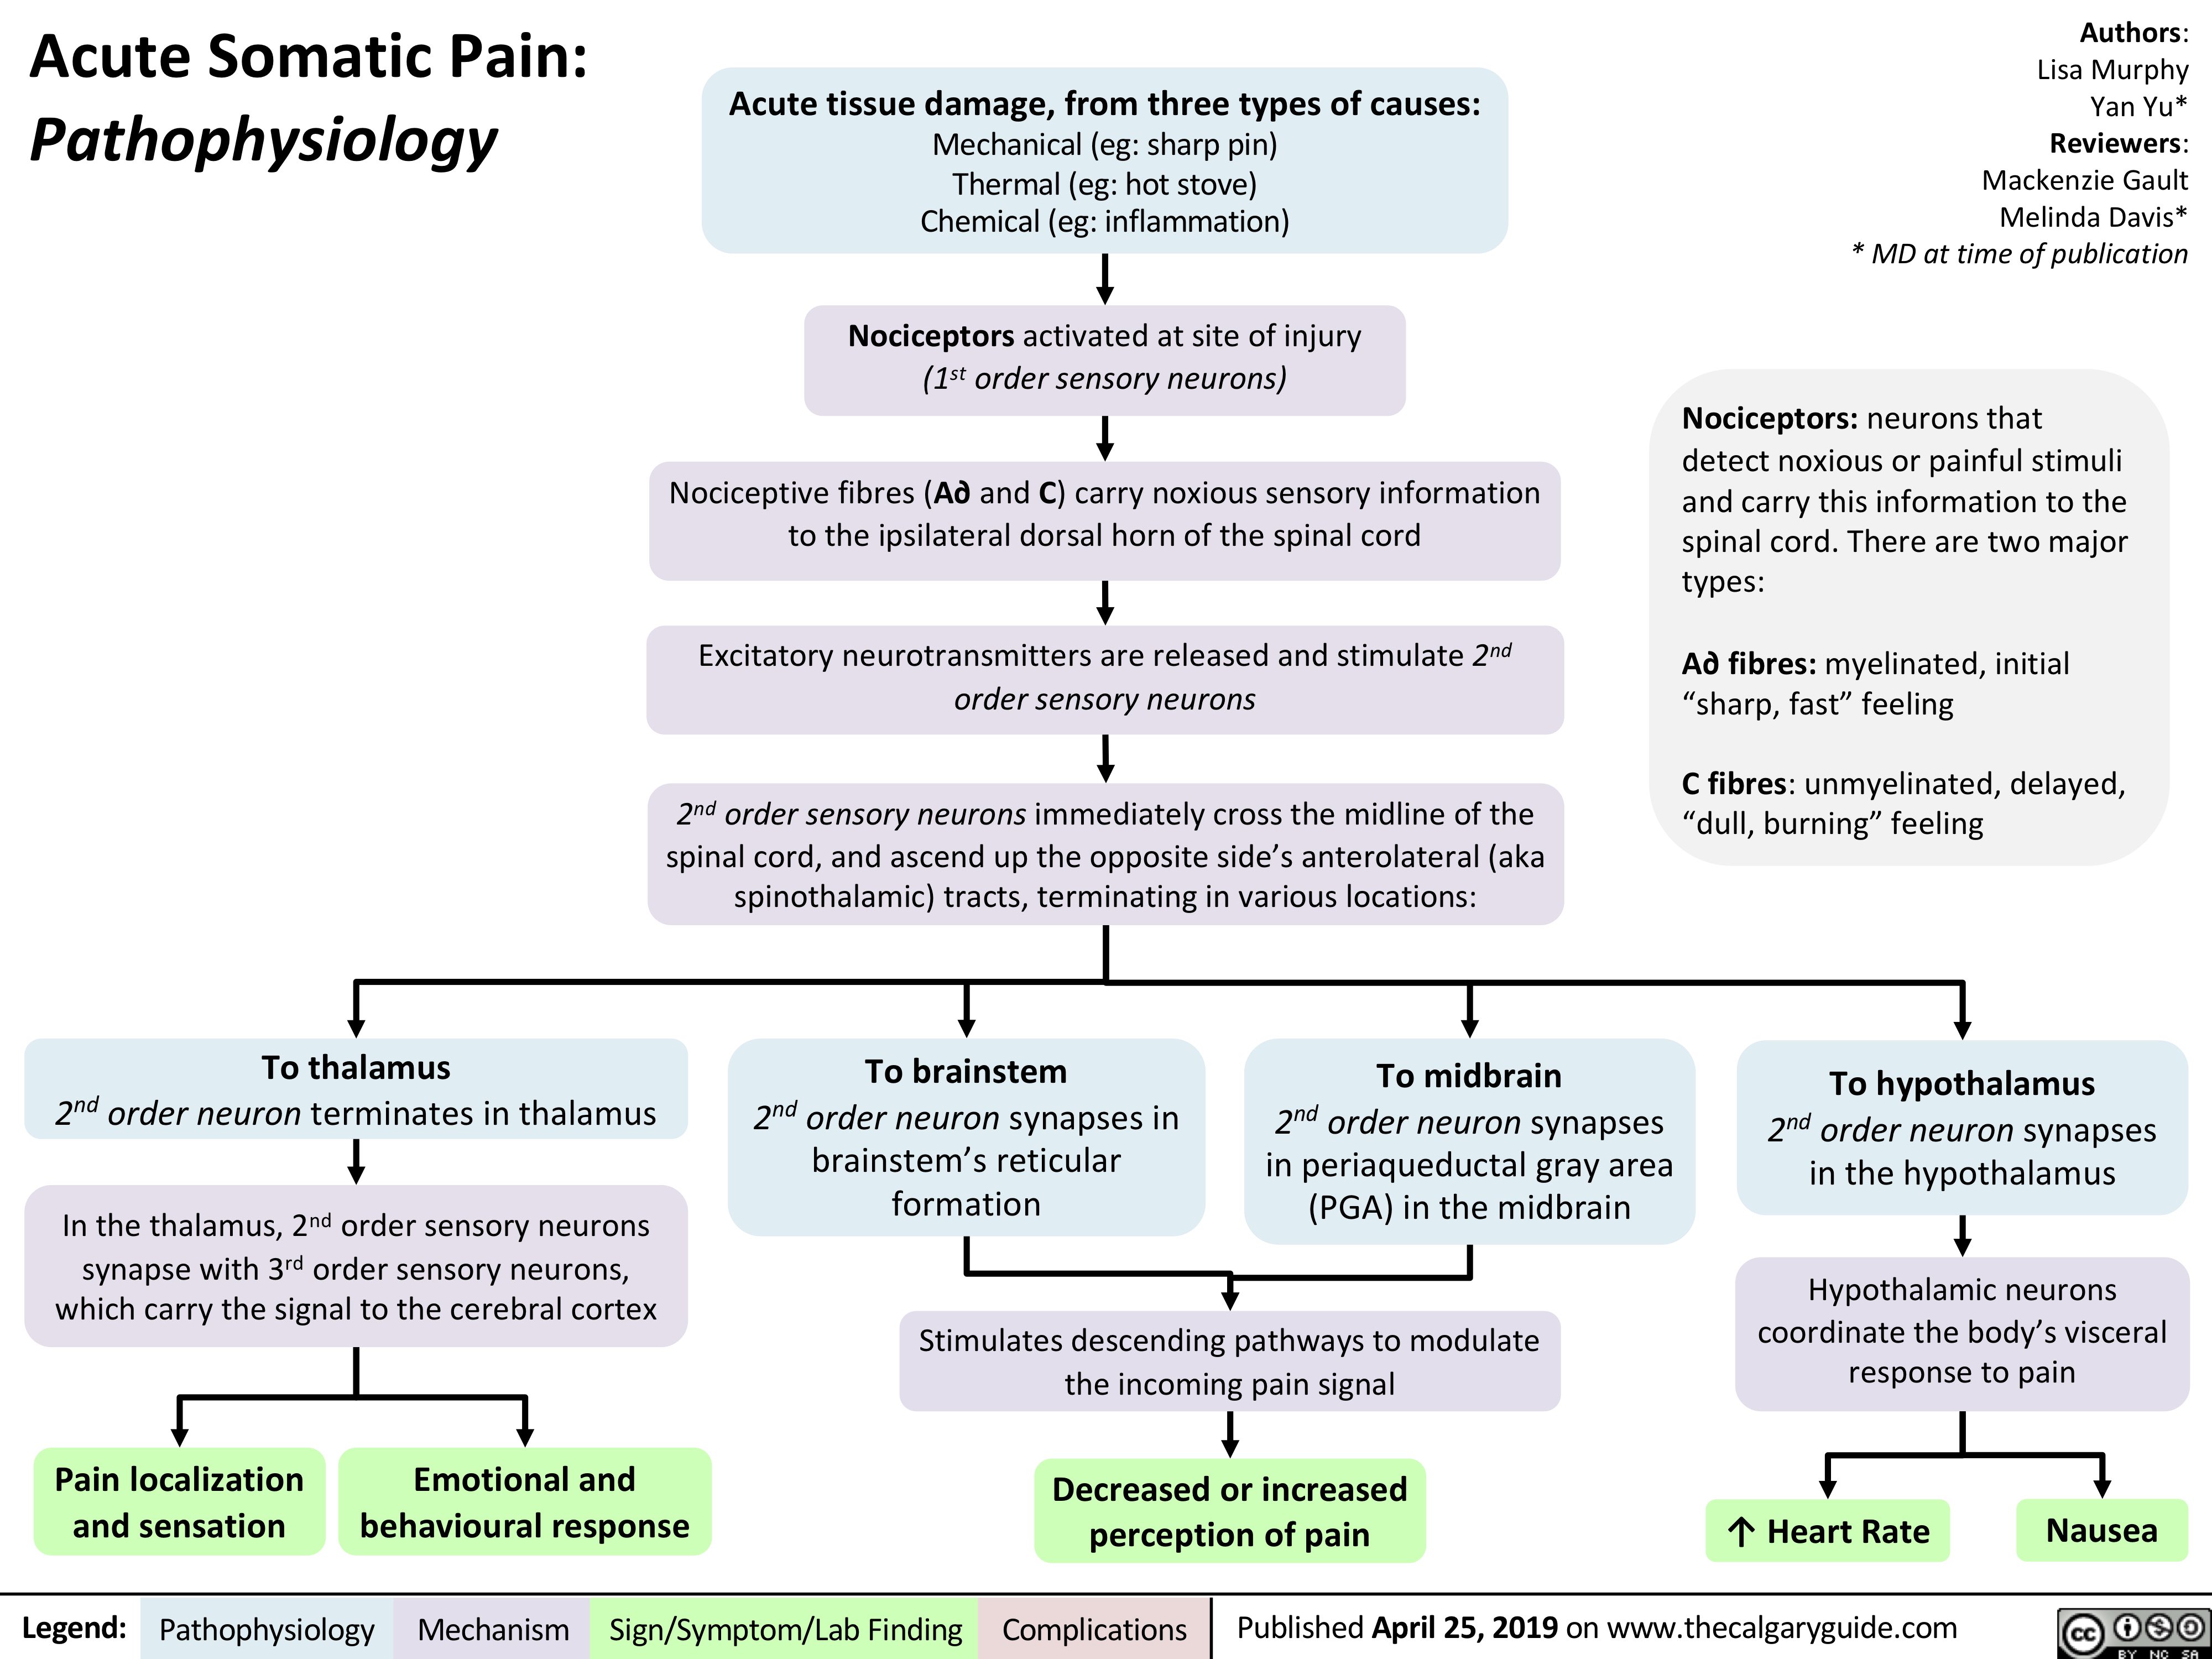
Somatic pain divides into two subtypes: superficial and deep. Superficial somatic pain arises from the skin and subcutaneous tissue. Think a cut, a burn, or a bruise. Deep somatic pain comes from muscles, ligaments, tendons, fascia, and bone. That's your rotator cuff tendinopathy, your facet joint pain from the spine, your stress fracture. Both types are nociceptive, meaning they result from actual tissue damage triggering pain receptors, but the quality and depth of the sensation differs noticeably. One counter-intuitive thing most beginners miss about somatic pain is that the intensity doesn't always correlate with tissue damage severity. I had a client with a minor grade 1 hamstring strain who was essentially non-functional from pain, while another client with a significant lumbar facet arthropathy on imaging could barely complain about the discomfort. The nervous system's pain amplification threshold varies enormously between individuals. Imaging findings are notoriously poor predictors of somatic pain intensity. This is important because a lot of treatment decisions get anchored to scan results when they should be anchored to the pain presentation itself. Another nuance that doesn't get enough attention: somatic pain can refer. A trigger point in your serratus anterior can produce pain around your shoulder blade that mimics a rotator cuff problem. Trigger points in the trapezius can create headaches that feel nothing like typical tension headaches. When you're trying to identify whether pain is truly somatic or if it's referred from another somatic structure, you need to map the pain pattern against known referral patterns rather than assuming the most obvious location is the source. This is where myofascial trigger point assessment becomes essential, and honestly, it's something a lot of general practitioners and even some physical therapists underutilize.
The practical management of somatic pain depends on identifying which subtype and which structures are involved. For superficial somatic pain, the approach is usually straightforward: protect the area, manage inflammation if acute, and allow tissue healing. Topical NSAIDs, proper wound care, and avoiding re-injury during the healing window cover most cases. For deep somatic pain, the picture gets more complicated because musculoskeletal structures often have overlapping innervation and the pain can become sensitized if left untreated. I encountered a particularly stubborn case involving a client with persistent lateral elbow pain diagnosed as lateral epicondylalgia. Standard eccentric loading protocols, rest, and a counterforce brace produced minimal improvement over six weeks. The breakthrough came when I noticed her pain patterns shifted with neck position. A significant portion of her symptoms was actually referring from C6-C7 myofascial trigger points in her upper trapezius and levator scapulae rather than originating from the tendons at the elbow itself. We shifted the focus to cervicoscapular rehabilitation, incorporated cervicogenic assessment into every session, and the elbow pain dropped by roughly sixty percent within three weeks after the initial plateau. The takeaway here is that somatic pain referral patterns can mimic primary tissue pathology, and ignoring proximal sources is a common reason somatic pain treatments stall. There are limitations to everything in this space. Somatic pain assessment relies heavily on clinical examination and patient history, which introduces subjectivity. Imaging rarely shows the actual pain generator for most soft tissue somatic pain. MRIs and X-rays are useful for ruling out structural pathology but poor at confirming what's actually causing the pain in day-to-day function. Treatment also varies widely in effectiveness depending on the chronicity of the issue. Acute somatic pain from recent injury responds much faster to standard conservative care than chronic somatic pain that has undergone central sensitization, where the nervous system itself becomes the pain problem rather than the original tissue source.
Get the Full Details

When somatic pain persists beyond the expected healing timeframe for the diagnosed tissue injury, or when it presents with atypical features like widespread distribution, associated neurological symptoms, or disproportionate intensity relative to findings, shifting the differential to include centralized pain conditions or neuropathic components is warranted. Continuing to treat chronic widespread somatic-type pain as purely local tissue pathology often leads to iatrogenic harm through unnecessary procedures and interventions that don't address the underlying mechanisms.