The Behavioral Component of CBT Explained Without the Fluff
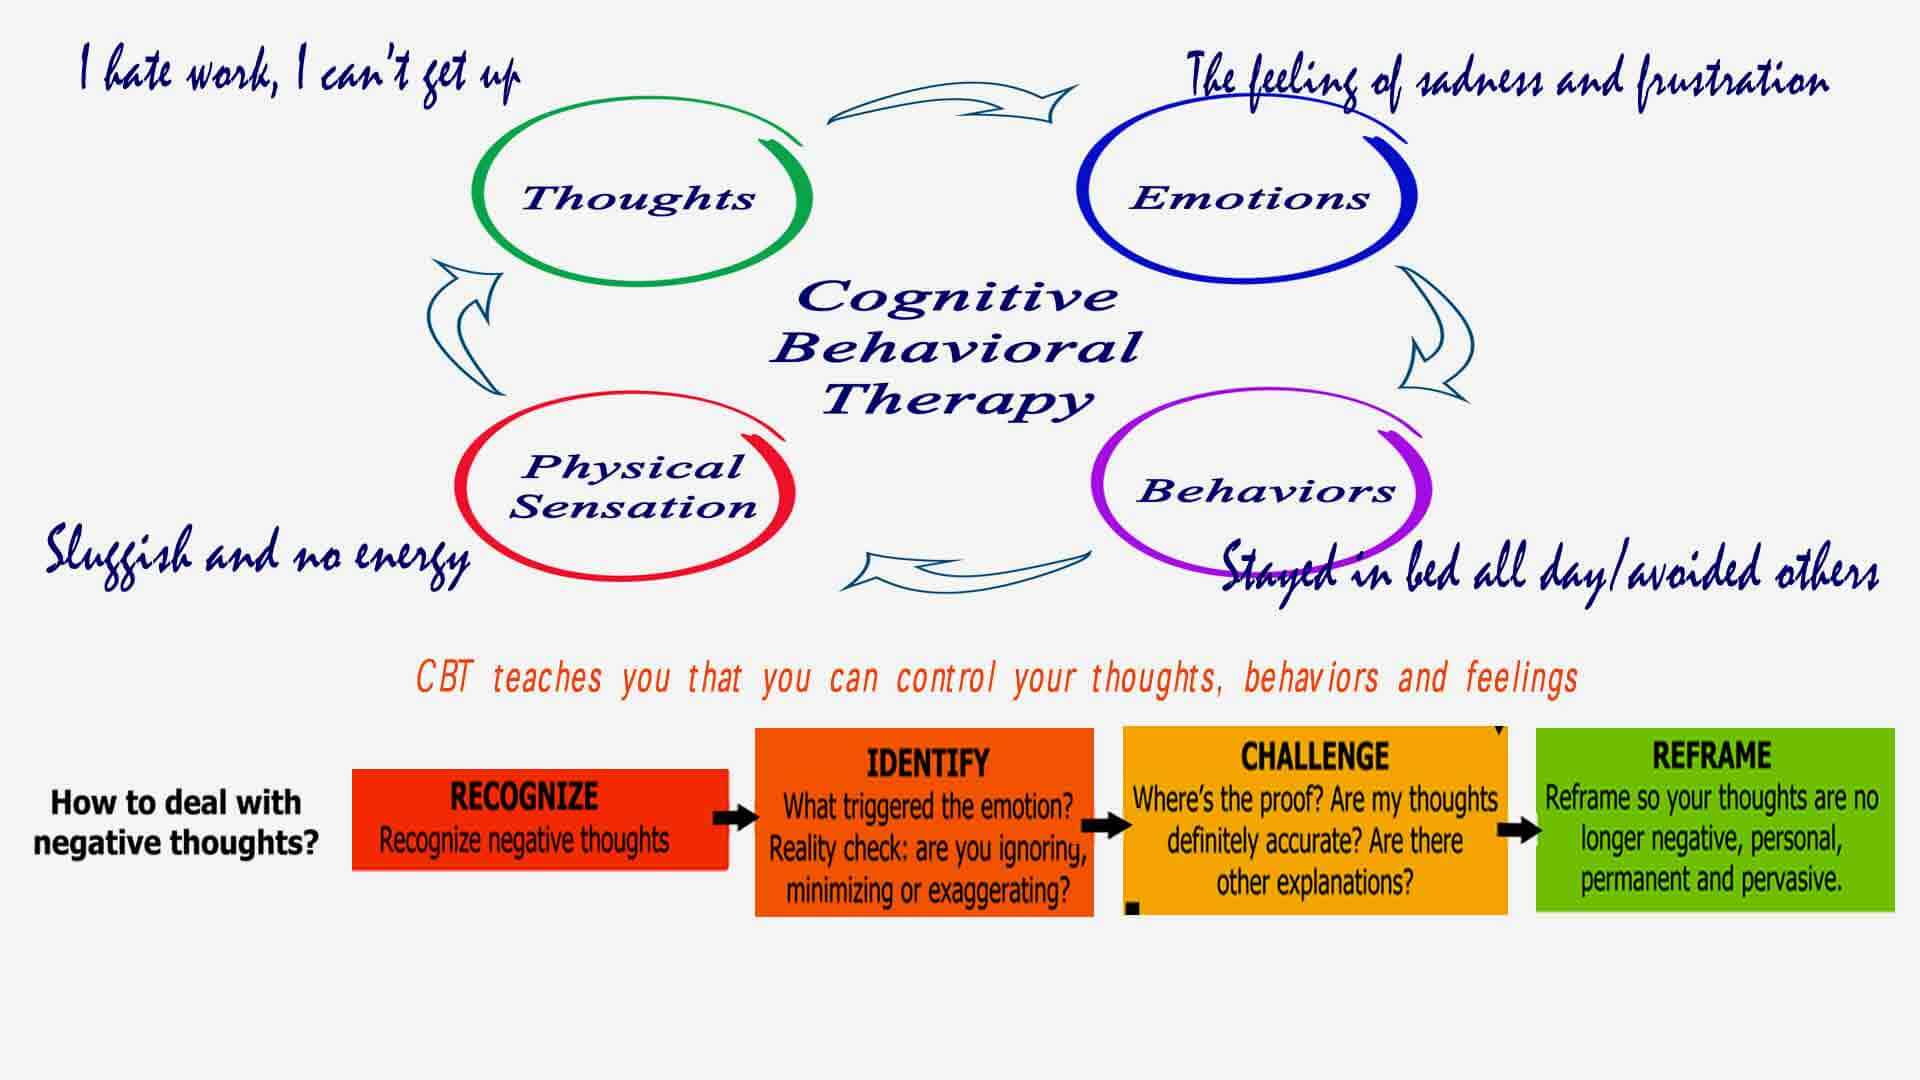
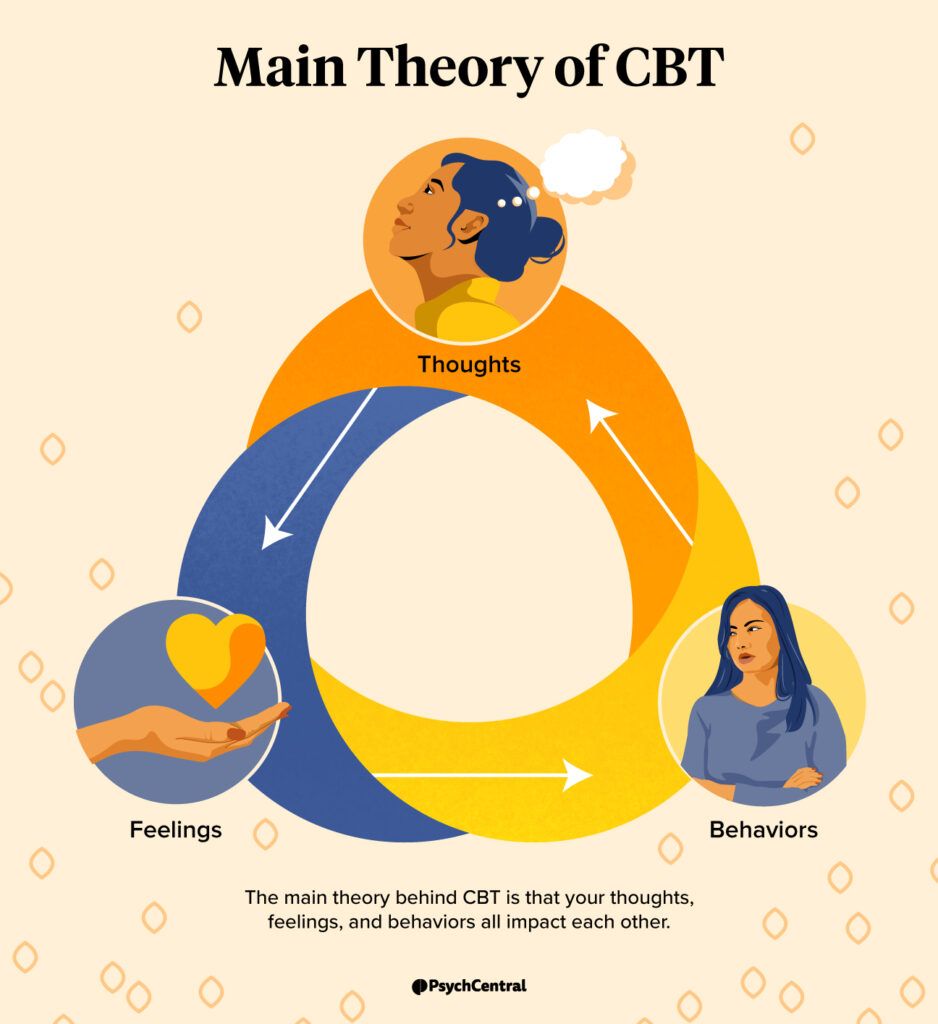
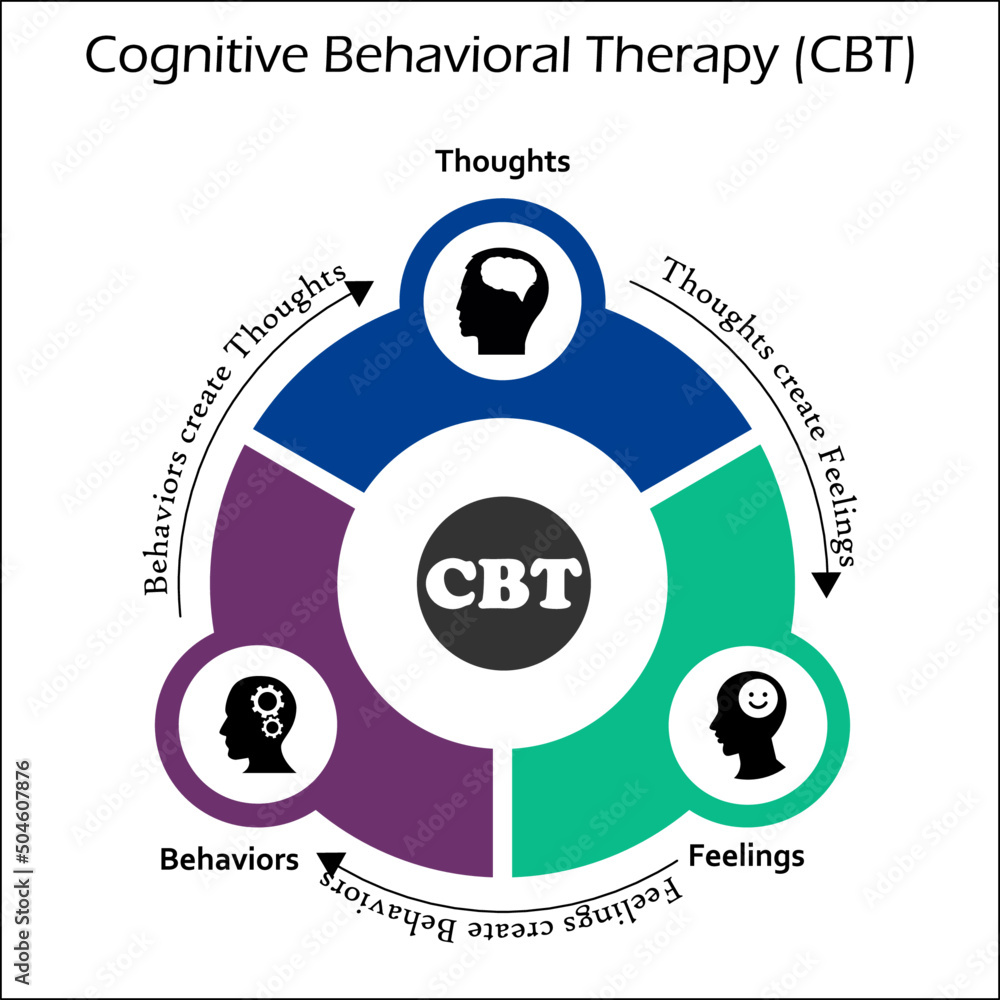
CBT is split into two halves that most people lump together without thinking about it. The cognitive side deals with thoughts and beliefs. The behavioral side deals with what you actually do. They influence each other, sure, but they are not the same thing. If you are only looking at one half, you are missing half the mechanism. The behavioral part is where exposure happens. It is where behavioral activation gets its meaning. It is where homework moves from a suggestion to a measurable action. Most therapists learn the cognitive piece first because it feels more like conversation. The behavioral piece requires someone to sit down and map out what a person will physically do between sessions, then track whether they did it. That tracking is where things usually go sideways.
What Is The Behavioral Part Of Cbt
At its core, the behavioral component means changing how a person acts in order to change how they feel and think. It is built on the principle that behavior both results from and reinforces emotional states and cognitive patterns. You do not wait for motivation to show up. You schedule the behavior, execute it, and observe what happens afterward. The feedback loop matters more than the action itself. Behavioral activation is the most common framework used. It works by scheduling activities that a person has been avoiding, starting with low-effort items. The logic is that depression and anxiety create a withdrawal loop. You avoid things. Avoidance reduces short-term distress. Avoidance then reinforces the belief that you cannot handle those things. Scheduling breaks that cycle. Exposure therapy is another major branch. Here the behavioral work involves systematically confronting feared stimuli until the anxiety response habituates. You do not talk someone out of a fear. You have them walk through it repeatedly. The fear decreases because the nervous system learns the predicted threat does not occur. This is well documented in OCD, phobias, and PTSD treatment.
Behavioral experiments come up a lot in practice. A client believes that speaking up in meetings will result in social ruin. Instead of arguing with that belief, you design a small experiment where they say one thing in a meeting and record what actually happens. Often the outcome is boring. That outcome is useful. I ran into a case last year involving a client with severe social anxiety who kept failing behavioral activation assignments. She would schedule going to a coffee shop, sit in her car for twenty minutes, and drive home. The standard approach would be to call it avoidance and press harder. That did not work here. The issue was that her anxiety had spiked past her window of tolerance before she even arrived. I switched tactics and had her sit outside the shop for five minutes with no requirement to enter. Next session she stayed ten minutes. We chunked the approach into micro steps she could actually tolerate, not what looked good on paper. It took six weeks instead of three, but she actually moved forward instead of just logging failures. There are pitfalls that almost everyone misses when they first work with the behavioral side. One is confusing compliance with progress. A client completes every homework assignment because they want to please the therapist, but the assignments are too easy to generate any meaningful change. The other pitfall is underestimating the effort required for consistent tracking. Paper worksheets get lost. Mental tracking is unreliable after a certain number of days. Digital tools help, but they introduce their own friction for people who are already struggling with executive function.
Get the Full Details

Another counter-intuitive point is that sometimes behavioral work should come before cognitive restructuring, not after. When someone is in acute distress with severe avoidance, trying to examine thoughts before changing behavior can feel abstract and unhelpful. Changing what they do first creates evidence that their catastrophic predictions were wrong. The cognitive work then has something concrete to build on. This order is not universal, but it is more common than most training programs admit. The behavioral component has real limitations. It does not address underlying trauma narratives that require deeper processing. It struggles with conditions where executive dysfunction is the primary barrier rather than avoidance. It also depends heavily on the client having the basic capacity to plan and follow through. When that capacity is impaired by substance use, acute psychosis, or severe neurological issues, behavioral interventions alone fall apart and need to be part of a broader treatment plan. If you want resources to dig deeper, the behavioral activation section in the original work by Martell, Fairburn, and Beck is the standard reference. For exposure-based protocols, Foa and Kozak laid the groundwork decades ago and the principles still hold. The Association for Behavioral and Cognitive Therapies website maintains a publicly accessible directory of trained clinicians and published treatment manuals. Those are more reliable than generic self-help books that conflate cognitive reframing with actual behavioral change.
The practical takeaway is straightforward. Identify the behavior maintaining the problem. Design an intervention that changes that behavior. Measure whether it actually changed. Adjust based on the data. That cycle repeated with precision is what separates actual CBT from vague talk therapy that happens to include some worksheets.