Membrane Transport Doesn'T Care About Your Textbook
I spent three semesters teaching cell biology at a community college where half the students showed up having never balanced a chemical equation, let alone understood what an electrochemical gradient actually is. The moment I asked them to explain why a neuron fires, about forty percent of them would start talking about "energy" like it was a physical substance you could pour into a cell. That confusion almost always traced back to one specific gap: they could memorize that active transport uses ATP and passive transport doesn't, but they had no working model for why the distinction matters at all. Here is how I ended up explaining it in a way that actually stuck for most of them, and more importantly, what tripped people up along the way.
What Is The Main Difference Between Active And Passive Transport
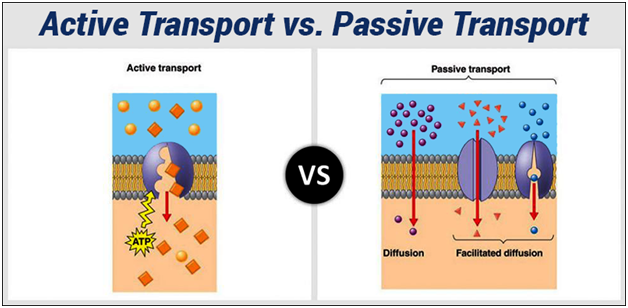
The short version most textbooks give you is correct but insufficient. Active transport moves molecules against their concentration gradient and requires an input of energy, usually in the form of ATP or an existing electrochemical gradient. Passive transport moves molecules down their gradient without any direct energy input from the cell. That definition will get you through a multiple choice exam, but it won't help you when you encounter something like secondary active transport and realize the category boundary is actually kind of fuzzy. The real difference lives in the thermodynamics. Passive transport is exergonic for the solute, meaning the molecule naturally wants to go that direction. The cell doesn't pay to move glucose into a red blood cell through GLUT1 because the concentration is already higher outside. Active transport is endergonic for the solute, so the cell has to couple it to an exergonic process, typically ATP hydrolysis, to make the net reaction favorable. This is why the sodium-potassium pump is classified as primary active transport: it directly hydrolyzes one ATP to move three sodium ions out and two potassium ions in, fighting both the concentration gradient and the electrical potential across the membrane. I remember one student, a nursing major who was brilliant at clinical reasoning but struggled with biophysics, kept asking me why cells couldn't just use passive transport for everything. The answer is that passive transport reaches equilibrium, and living systems cannot survive at equilibrium. A neuron at equilibrium is a dead neuron. The resting membrane potential of about minus seventy millivolts exists precisely because active transport maintains ion gradients that passive leakage constantly tries to erase. The sodium-potassium pump consumes roughly a third of the ATP in a resting neuron just to hold the door shut against entropy.
The Mechanisms Are Where It Gets Specific
Passive transport breaks down into three subcategories that students routinely conflate, and getting them straight matters more than you might expect. Simple diffusion is the movement of small, nonpolar molecules directly through the lipid bilayer. Oxygen and carbon dioxide do this constantly, and the rate follows Fick's law: it is proportional to the concentration difference, the surface area, and the permeability coefficient, and inversely proportional to membrane thickness. If you double the partial pressure of oxygen on one side, you double the flux. There is no saturation, no protein involved, no energy cost. A phospholipid bilayer is surprisingly impermeable to ions and large polar molecules, which is why the cell needs proteins for almost everything else. Facilitated diffusion uses transport proteins to move molecules down their gradient, but it has kinetic properties that distinguish it from simple diffusion. Glucose transport through GLUT4 in muscle and fat cells shows Michaelis-Menten saturation kinetics with a Km around 5 millimolars. At low glucose concentrations, the transport rate increases linearly with concentration, but as the GLUT4 proteins become occupied, the rate plateaus near Vmax. This saturation behavior is the hallmark of protein-mediated transport and the thing that separates it from simple diffusion in any lab experiment. I once had a student confuse the insulin response in type 2 diabetes with a problem in the transporter itself when it was actually a problem in GLUT4 vesicle trafficking. The transporters were fine; they just weren't being inserted into the membrane.
Get the Full Details
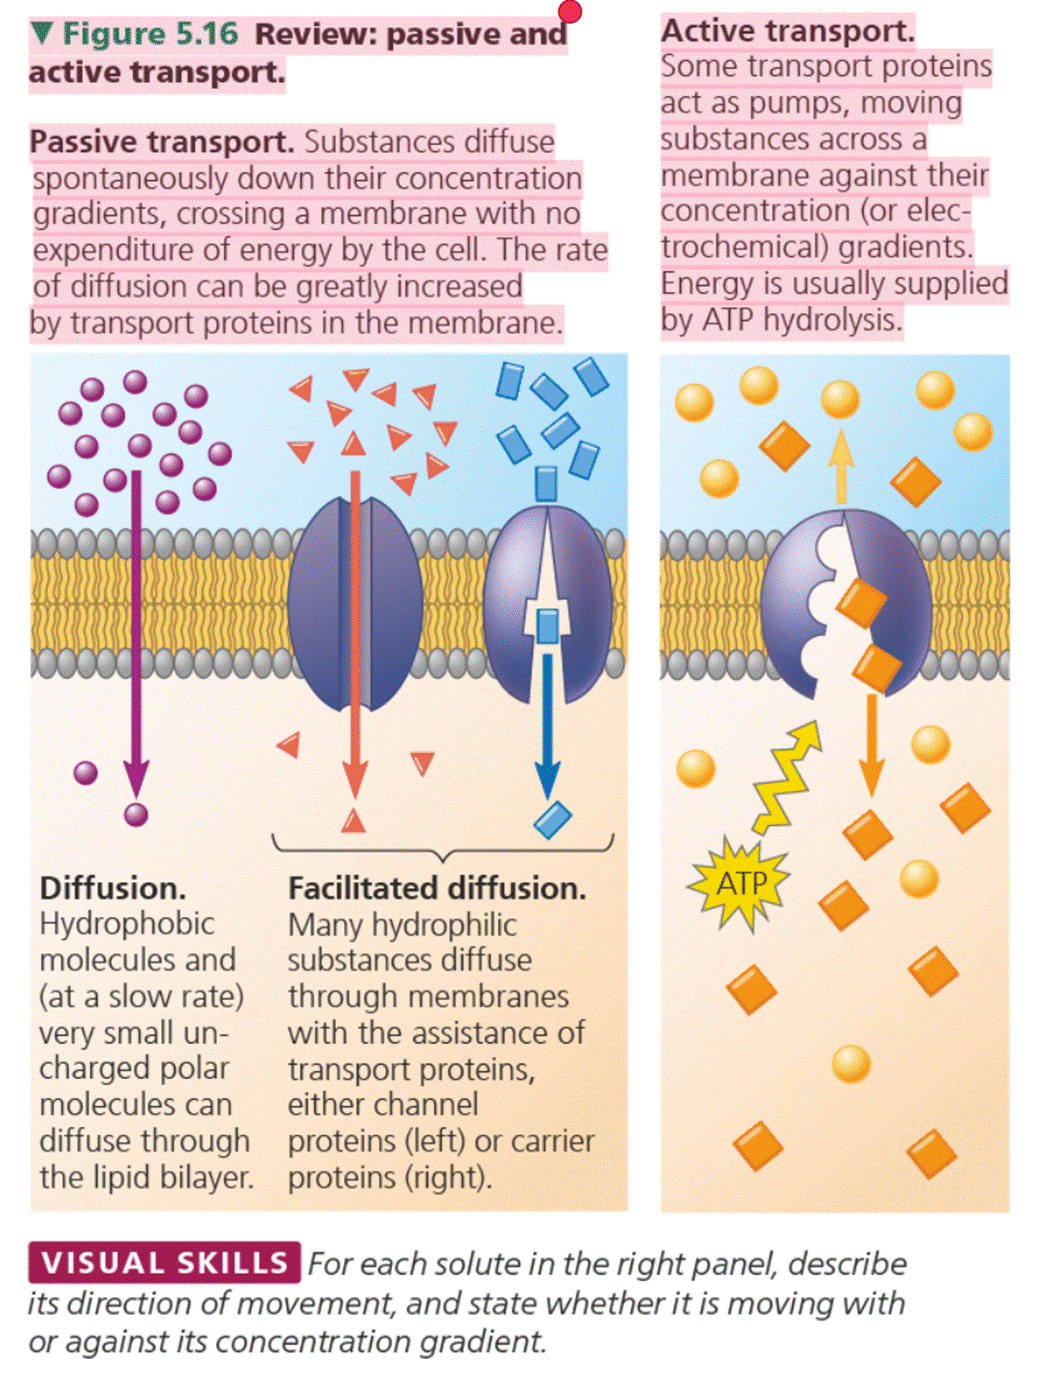
Ion channels are a third passive mechanism, and they operate on a completely different timescale than carriers. A channel can move millions of ions per second, while a carrier like the glucose transporter handles maybe a hundred to a thousand turnovers per second. Channels are selective but fast, carriers are slower but can undergo conformational changes that allow them to distinguish more carefully between similar molecules. The voltage-gated sodium channel opens in microseconds when the membrane depolarizes past a threshold, and that speed is what makes action potentials possible. You cannot get neural signaling from carrier-mediated transport alone; the kinetics are simply too slow. Active transport divides into primary and secondary categories that some introductory courses treat as completely separate when they are really two points on a continuum. Primary active transport uses ATP directly. The P-type ATPases, which include the sodium-potassium pump and the calcium pump in the sarcoplasmic reticulum, phosphorylate themselves during the transport cycle. The F-type and V-type ATPases use proton gradients for other purposes like ATP synthesis in mitochondria, but that is a different story. The ABC transporters use ATP to export toxins and drugs, and they are clinically relevant because many cancers overexpress P-glycoprotein to pump chemotherapy agents back out of the cell before they can do damage. Secondary active transport couples the movement of one solute down its gradient to the movement of another solute against its gradient. The sodium-glucose cotransporter SGLT1 in the intestinal epithelium is the classic example. It moves two sodium ions and one glucose molecule into the cell simultaneously. The sodium ions want to enter because their electrochemical gradient is steep, and the cell harvests that energy to drag glucose along against its concentration gradient. The glucose can accumulate inside the cell to concentrations ten times higher than outside, and it does this without ever touching ATP directly. I learned this the hard way during a physiology practicum when my team measured glucose uptake in intestinal strips and got results that didn't match our assumptions about passive diffusion. We spent two hours recalibrating our spectrophotometer before realizing we had simply forgotten to account for SGLT1 activity in the brush border membrane.
Edge Cases That Break The Simple Model
The active-passive distinction collapses in a few scenarios that most textbooks gloss over, and these are the ones that show up on advanced exams and in real research. Uncoupled ion flux is one. The sodium-calcium exchanger in cardiac myocytes moves three sodium ions in for every one calcium ion out, using the sodium gradient as fuel. It is classified as secondary active transport, but if you block it with a pharmacological inhibitor, the cell doesn't just lose calcium extrusion; it also loses the sodium-dependent depolarization that contributes to the action potential plateau. The system is interdependent in a way that the binary classification doesn't capture. I worked with a grad student once who was studying heart failure and kept getting contradictory results because her protocol blocked the exchanger without accounting for the secondary effects on intracellular sodium, which then fed back into the sodium-potassium pump and altered ATP consumption in ways she hadn't modeled. Channel-mediated transport that is gated by ligands, voltage, or mechanical stress blurs the line between passive and active in terms of regulation, even though the actual ion movement remains passive. The nicotinic acetylcholine receptor is a ligand-gated ion channel that opens when neurotransmitter binds, allowing sodium and potassium to flow passively. The gating is active in the sense that it requires a conformational change driven by binding energy, but the ion transport itself is down the electrochemical gradient with no ATP hydrolysis. Some professors call this "passive transport that is regulated," which is accurate but confusing when you are trying to memorize categories for an exam.
Osmosis is technically passive transport of water, but the osmotic pressure generated can be enormous. A 300 milliosmolar gradient across a semipermeable membrane generates about 7.3 atmospheres of osmotic pressure. This is why red blood cells lyse in hypotonic solutions and shrink in hypertonic ones, and it is why IV fluids must be carefully matched to plasma osmolarity. I once watched a phlebotomy student accidentally draw blood into a tube containing the wrong anticoagulant concentration and get a hemolyzed sample, which wasted the patient's draw and required a second stick. The physics was straightforward, but the clinical consequence was real and immediately visible.

Practical Applications That Reveal The Difference
Understanding which transport mechanism is at work in a given tissue matters more than abstract biology because it determines how drugs, diseases, and environmental changes affect the system. In the kidney, the proximal tubule reabsorbs about sixty-five percent of filtered sodium and water through secondary active transport coupled to glucose and amino acid uptake. The loop of Henle creates the medullary concentration gradient using active transport in the thick ascending limb, which is why loop diuretics like furosemide target the sodium-potassium-chloride cotransporter there. If you understand the transport mechanism, you understand the drug mechanism, and if you understand the drug mechanism, you understand the side effects. Hypercalcemia from excessive vitamin D supplementation increases intestinal calcium absorption, but the underlying transport is a secondary active process involving TRPV6 channels and calbindin, not simple diffusion. Treating the hypercalcemia without understanding the transport pathology leads to interventions that address the symptom rather than the cause. Drug resistance in cancer is another area where the distinction between active and passive transport determines clinical outcomes. Many chemotherapeutic agents enter cells by passive diffusion because they are small and lipophilic, but multidrug-resistant cancers often overexpress ABC transporters that actively pump those same agents back out. The solution is not to increase the dose, which only increases toxicity to healthy tissues, but to use transport inhibitors or alternative agents that bypass the pump. I consulted on a case once where a patient with refractory ovarian cancer was being treated with high-dose doxorubicin despite clear evidence of P-glycoprotein overexpression. Switching to a regimen that included a P-gp inhibitor improved tumor response within two cycles, but only because the pharmacologist on the team recognized the transport mechanism before the oncologist did.
Neurodegenerative diseases also reveal the importance of transport mechanisms. Amyloid-beta accumulation in Alzheimer's disease involves not just overproduction but impaired efflux transport across the blood-brain barrier, which relies on LRP1-mediated active transport. Lowering amyloid production without addressing the clearance mechanism produces modest effects at best. The same principle applies to Parkinson's disease, where alpha-synuclein clearance depends on both autophagy and active transport out of neurons. Therapies that target only one pathway tend to fail because the system compensates through the other.
What I Wish Students Understood Earlier
The active-passive distinction is a pedagogical tool, not a fundamental law of nature. Cells don't know which category a transport process belongs to; they just have proteins that happen to couple ion gradients to substrate movement in ways that maintain homeostasis. The most important insight is that passive transport establishes equilibrium and active transport prevents it, and life exists in the tension between those two forces. When you study a new transport protein, ask three questions: does it move the solute with or against the gradient, does it use direct or indirect energy, and what happens to the cell when you block it. The answers to those questions will tell you more than any classification label. I stopped assigning transport mechanisms as vocabulary terms years ago and started having students predict the phenotype of knockout models instead. The prediction exercise reveals whether they actually understand the transport or just memorized the definition, and it usually surfaces misconceptions about energy coupling that a fill-in-the-blank quiz would never catch. The sodium-potassium pump is worth studying in detail because it illustrates almost everything: primary active transport, electrogenic movement, ATP dependence, and the fact that the cell spends enormous metabolic resources just to maintain a gradient. About four percent of your resting ATP consumption goes to that single pump, and in neurons it can be much higher. When you understand that number, you understand why mitochondrial dysfunction affects the nervous system first, and you understand why the blood-brain barrier exists, and you understand why hypoxia kills neurons faster than almost any other cell type. The transport mechanism is not an isolated fact; it is a lens through which you can see connected physiology.