Why Everything Breaks Without A System
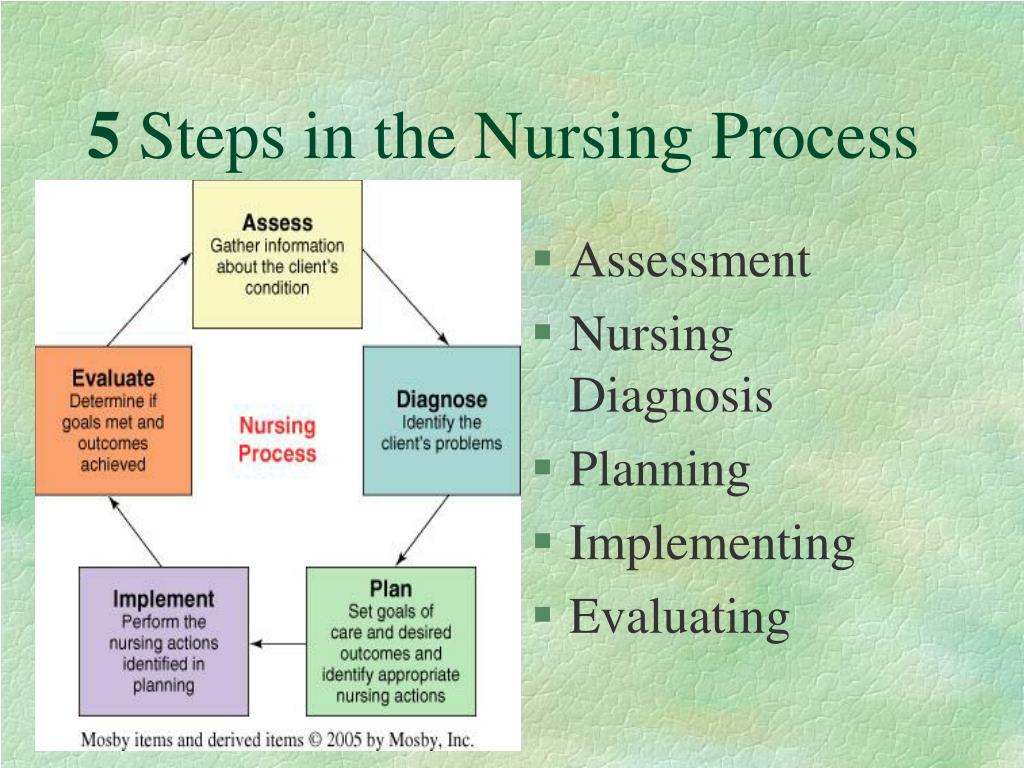
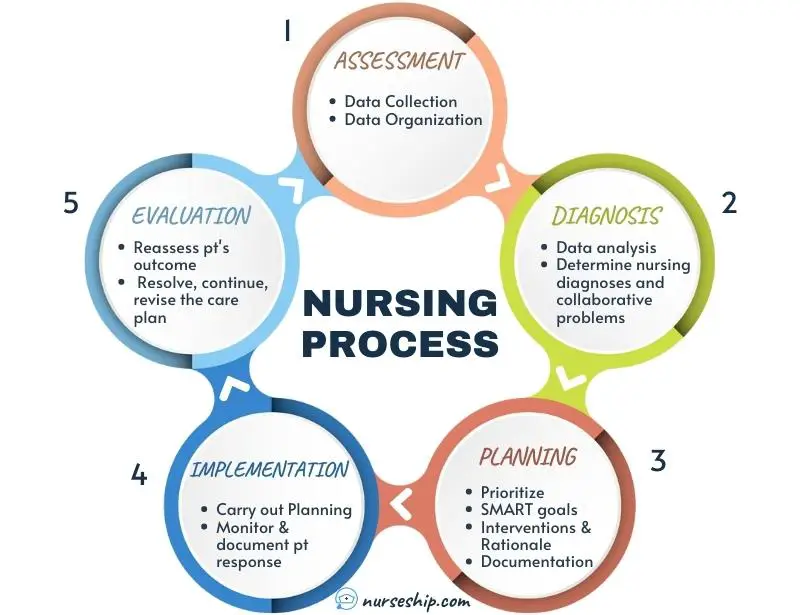
I worked a surgical floor for about eight years before moving into case management, and the thing that separated nurses who burned out from those who didn't was almost never clinical skill. It was whether they had a repeatable method for handling patients who presented with problems you couldn't just look up in a protocol. The nursing process is that method. It's five steps that have been part of nursing education since the 1960s, basically unchanged except for the documentation platforms we use now. The nursing process is a systematic, cyclic framework that guides clinical decision-making. It consists of assessment, diagnosis, planning, implementation, and evaluation. It's not a linear checklist where you check off step one and move to step two. In practice, you're cycling through all five repeatedly throughout a single shift. Assessment means collecting data. This is both subjective and objective. Subjective is what the patient tells you, their history, their complaints, the way they describe their pain. Objective is what you can measure, vitals, lab values, wound appearance, skin integrity. You're not just gathering information because a textbook says so. You're building a picture of the patient's baseline and current status.
Nursing diagnosis comes next. This is distinct from a medical diagnosis, which is important because people confuse them constantly. A medical diagnosis identifies a disease, like congestive heart failure. A nursing diagnosis identifies how that disease is affecting the patient's functional status, like excess fluid volume related to compromised regulatory mechanisms as evidenced by edema and dyspnea. NANDA-I maintains the taxonomy for these, and learning the format matters for documentation and for communication with other nurses. Planning is where you set outcomes and choose interventions. The outcomes need to be specific and measurable. A goal like improve breathing is too vague to evaluate. A goal like respiratory rate decreases from 28 to under 20 within four hours of positioning and oxygen therapy is something you can actually assess. Interventions flow from the diagnosis and the outcome you're targeting. Implementation is executing the plan. This includes independent nursing actions, collaborative actions with other providers, and patient education. Documentation happens here in real time. I can't stress this enough because most nurses I trained did it at the end of the shift, which meant either they forgot or they wrote it in a rushed state that made the notes nearly useless for the next person.
Evaluation determines whether the patient met the outcomes you set. If yes, you continue or discharge the plan. If no, you go back to assessment and restart the cycle. The cyclical nature is what makes this actually useful rather than just paperwork. Most people treat evaluation like an ending, which defeats the whole purpose. I had a patient once, post-op day two from a bowel resection, who wasn't showing the classic signs of a developing ileus. No vomiting, normal bowel sounds on paper, but her abdominal distension was inching up each shift and her output via NG tube was becoming more bilious than it had been. The nursing diagnosis I'd written earlier for acute pain was still technically active because nobody had formally reassessed it. I went back through the process with a fresh assessment and caught that the ileus was progressing before it became an emergency. That's the framework doing its job, even though I was tired and half the team thought I was being paranoid for flagging it.
Get the Full Details

The Details That Actually Matter
Here's what the textbooks don't always emphasize. The nursing process isn't just useful for bedside nurses. Case managers use it, public health nurses use it, nurse practitioners use variations of it. The structure is universal because human clinical judgment works the same way regardless of setting. One thing that catches people off guard is how much assessment overlaps with implementation. When you're reassessing a wound dressing, you're also implementing wound care. When you're repositioning a patient to prevent pressure injury, you're both assessing skin integrity and implementing preventive measures. You're not always moving cleanly from one step to the next. Good nurses learn to blend these rather than treating them as separate boxes to check. Another counter-intuitive point is that nursing diagnoses should ideally be patient-specific and derived from your own assessment, not copied from a template. I've seen care plans generated by software that pulled NANDA labels based on a few input fields and produced something mechanically correct but clinically hollow. The diagnosis might say risk for fall, which is technically accurate for an elderly post-op patient, but it doesn't capture that the real fall risk for that specific person is their unsteadiness combined with their refusal to use the call light because they're embarrassed to bother staff. That nuance changes the intervention entirely.
The process has limitations that aren't discussed enough. It assumes a level of nursing autonomy and time that doesn't exist in many current healthcare environments. When a nurse is assigned eight to ten patients and expected to complete four-hour documentation windows between medication passes, the nursing process becomes a compliance exercise rather than a thinking tool. That's not a flaw in the framework. It's a structural problem in how healthcare is organized. You still use the process under those conditions, but you're adapting it to survive, not flourishing. If you're learning this for a class or certification, focus on the language of NANDA-I diagnoses and make sure you understand how to link your assessment data to your chosen diagnosis to your planned outcome. That linkage is what evaluators and clinical instructors look for. It's also what separates a nursing student who's memorizing steps from one who's actually thinking through a patient's care. The five steps are Assessment, Diagnosis, Planning, Implementation, Evaluation. They're simple to state and easy to misapply. The value isn't in reciting them, it's in using them when you're tired and your patient list is full and something isn't adding up the way it should.