
The Framework That Actually Guides Your Day
You learn it in school as a chapter in your nursing theory textbook, then you forget it for six months until you're on a 12-hour shift and something goes sideways. Nursing philosophy isn't some academic exercise. It's the actual decision-making structure you fall back on when you don't have time to consult a policy manual. Most new grads never realize they're using one. I worked med-surg for about eight years before moving into case management, and honestly, the difference between nurses who were effective under pressure and the ones who burned out or made careless errors came down to this. The ones who knew their philosophy could articulate why they were doing what they were doing even when the unit was short-staffed and chaotic. The others just reacted to whatever demanded attention first.
What Is The Philosophy Of Nursing
At its core, nursing philosophy is a set of principles that defines the profession's purpose, scope, and values. It addresses what nursing is fundamentally about, how nurses should relate to patients, and what outcomes they're accountable for. The major frameworks that circulate in practice include Watson's Theory of Human Caring, which puts authentic presence and the nurse-patient relationship at the center of everything. Roy's Adaptation Model views the patient as a biopsychosocial system constantly adapting to stimuli, and nursing's role is to promote adaptive responses. Orem's Self-Care Deficit Theory focuses on what patients can do for themselves and where nursing support becomes necessary. Then there's Leininger's Culture Care Theory, which insists you cannot provide effective care without understanding the patient's cultural context, and Neuman's Systems Model, which looks at stressors and lines of defense around the patient. None of these are mutually exclusive. Most experienced nurses blend elements from two or three depending on the situation. That's not sloppy thinking. That's how actual practice works. A common mistake people make is treating philosophy as something separate from clinical skill. It's not. When you decide to sit with a patient who's anxious about discharge instead of rushing through paperwork, you're exercising a philosophical position. When you advocate for a pain management adjustment against a provider's dismissive attitude, same thing. Your philosophy shows up in micro-decisions throughout every shift.
How It Works In Practice
The thing nobody tells you about nursing philosophy is that it gets tested most brutally during resource shortages. I had a situation once where I was assigned six patients, two of them on continuous IV vasopressors, and one was end-of-life with a DNR who kept asking questions about hospice that I wasn't prepared to answer on the spot. My philosophy at that point was a blend of Watson and Roy, roughly. I held that nursing's primary obligation is to the individual person in front of me, but that I also had to manage the system around them to prevent harm. So I prioritized my time differently than the chart would suggest. I spent twenty minutes with the dying patient listening because she needed that more than the vasopressor titrations that were already on schedule. I delegated the question about hospice to social work rather than fumbling through it myself. I kept the other two monitored but stable. It wasn't textbook. It was judgment, and judgment is philosophy in action. The opposite approach, which I've seen lead to serious problems, is treating all patients as equal in time and attention regardless of clinical need and personal circumstance. That sounds compassionate on paper. On a real unit it means everyone gets mediocre care and the ones who needed more suffer in silence. Another nuance that trips people up is the relationship between nursing philosophy and medical philosophy. Medicine is oriented toward diagnosis and treatment of disease. Nursing is oriented toward response to illness and the human experience of it. They overlap constantly and sometimes conflict. A physician might say a patient is clinically stable and ready for discharge. The nurse might know the patient has no one to care for them at home and absolutely cannot go yet. That tension is philosophical, not just procedural.
Get the Full Details
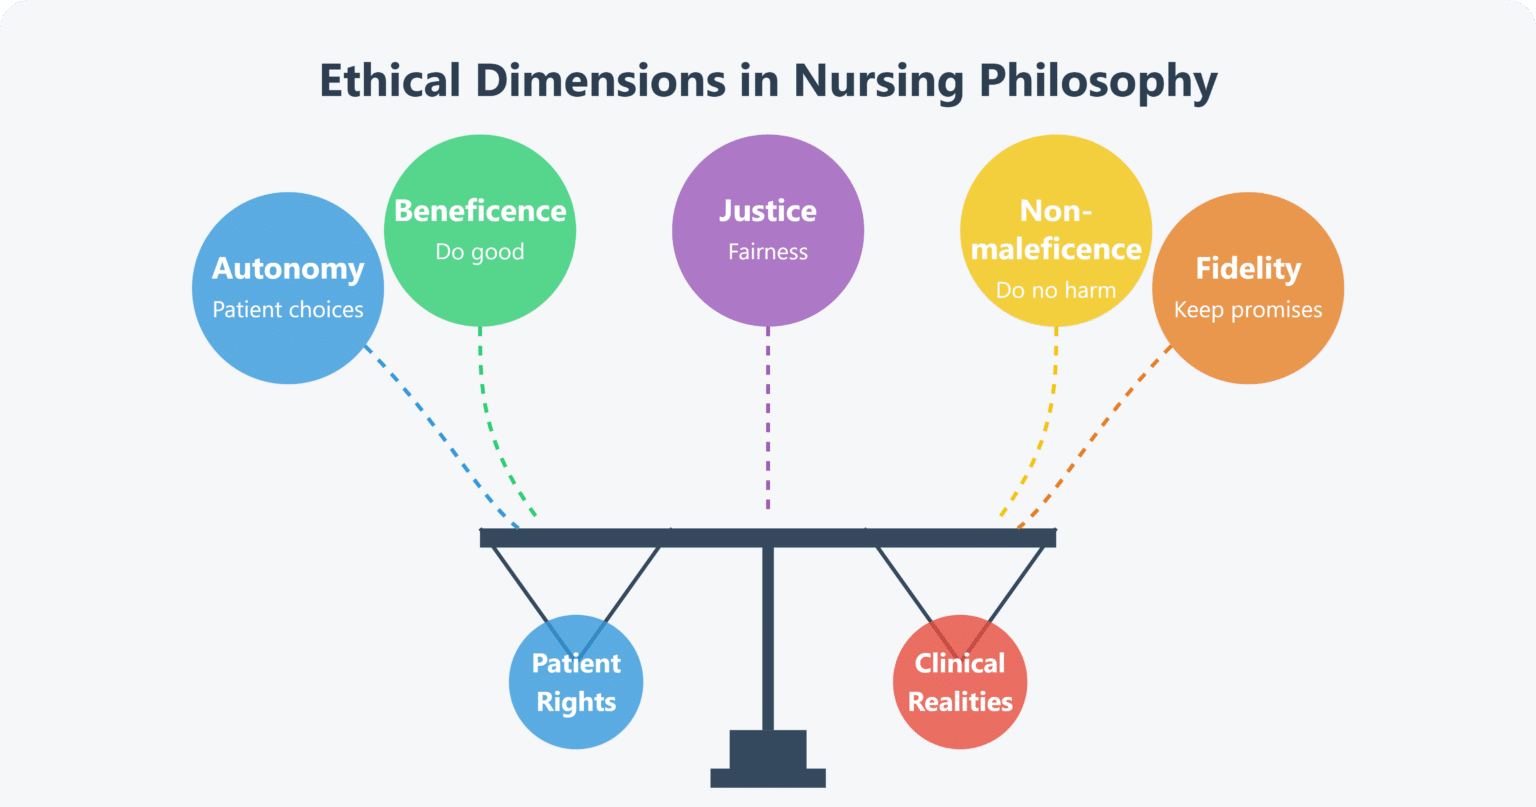
Building Your Own
If you're early in your career and you don't have a formed philosophy yet, that's normal. Most people develop theirs through experience rather than reflection. But you can speed that up. Start by identifying which moments on shift feel right to you and which feel wrong. The feeling of satisfaction after spending extra time with a frightened patient versus the irritation you feel when you're pulled away from someone mid-conversation. Those emotions are data points. They reveal your underlying values. Read the major theorists, but don't get stuck in academia. Watson's five cardinal carings are a practical starting point. Ask yourself whether you naturally align more with caring, with adaptation, with self-care promotion, or with cultural competence. Most nurses lean toward one or two. The ones who try to adopt all of them at once end up with no coherent framework at all. Write it down. A paragraph is enough. Something like: I believe nursing is fundamentally about supporting individuals through illness while preserving their dignity and autonomy, and that this takes precedence over efficiency metrics when the two conflict. That's a philosophy. It's testable, it's actionable, and it will guide you when protocols run out.
Where It Falls Short
I should be clear about the limitations here. A personal nursing philosophy does not protect you from institutional constraints. No amount of philosophical grounding will let you stay with a terminally ill patient for an hour if the nurse manager is tracking length-of-stay and threatening write-ups. Philosophy guides individual practice, but it does not override systemic priorities. I've watched competent, philosophically grounded nurses get disciplined for practices that were ethically sound but administratively inconvenient. That happens. You need to know where the line is between what your philosophy allows you to do and what the institution will actually tolerate. There's also a risk of philosophical rigidity. Some nurses lock into one framework and stop adapting. If you believe entirely in Orem's self-care model, for example, you might underestimate how much support a post-op patient actually needs on day one. Conversely, if you're purely Watson-oriented, you might neglect the physiological monitoring that keeps patients safe. The best practitioners keep their philosophy flexible enough to incorporate competing demands without abandoning their core values. And finally, nursing philosophy is not a substitute for evidence-based practice. Believing deeply in the importance of patient education doesn't help if you're recommending interventions that have no clinical support. Philosophy and evidence are complementary, not interchangeable. One tells you why you're doing something. The other tells you whether what you're doing actually works.




