Setting the Goals in Lipid Management
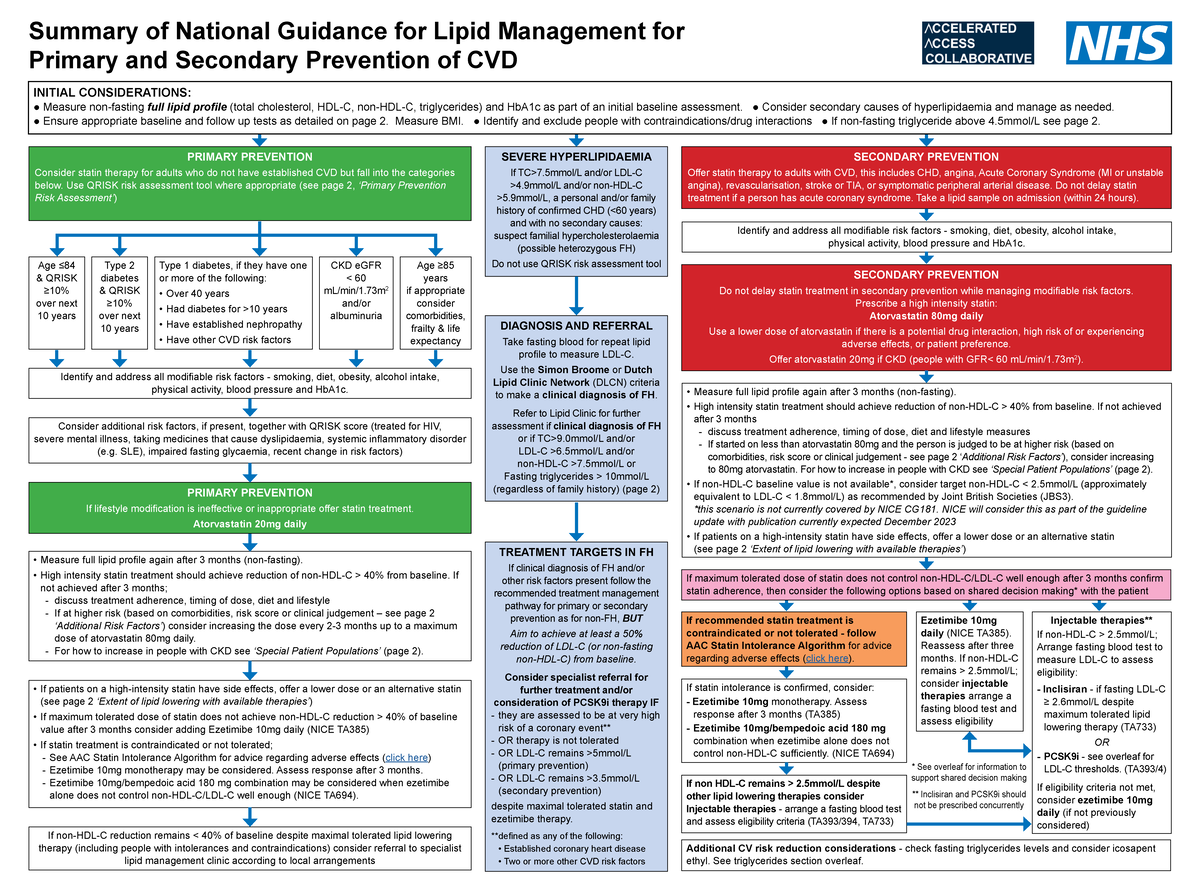
Lipid management sounds complicated because the literature is enormous, but the core question is straightforward: what are you actually trying to move the needle on when you prescribe a statin or add ezetimibe? The primary target is low-density lipoprotein cholesterol, abbreviated LDL-C. That is it. Everything else—triglycerides, non-HDL, apoB—is secondary. You lower LDL-C first, you hit your number, and then you decide if anything else needs attention. I see people get tripped up because guidelines keep introducing new numbers and risk calculators, and suddenly the conversation feels broader than it needs to be. It is not. LDL-C remains the primary target of treatment in lipid management. Non-HDL cholesterol is the alternative when triglycerides are elevated, and apoB is emerging as the more precise risk marker, but neither replaces LDL-C as the initial therapeutic focus in standard practice. The way I approach this in clinic is by starting with the risk category. A patient with established atherosclerotic cardiovascular disease, that is clinical ASCVD, falls into the very high-risk group. Their LDL-C goal is under 55 mg/dL according to the most recent ESC/EAS guidelines, or at least a 50 percent reduction from baseline if you are following the ACC/AHA framework. For someone with diabetes and additional risk factors, the threshold is usually 70 mg/dL. Primary prevention patients without those risk factors often have a goal below 100 mg/dL. These numbers are not arbitrary. They come from outcome trials, and they matter because every 38 mg/dL (1 mmol/L) reduction in LDL-C cuts major vascular events by roughly a quarter, independent of the drug you use.
Here is a practical complication that does not get enough attention. When a patient has severe hypertriglyceridemia, above 400 mg/dL, the calculated LDL-C using the Friedewald equation becomes unreliable. I ran into this with a patient whose triglycerides were around 600. The lab reported an LDL-C of 45, which looked fantastic on paper, but that number was wrong. The Friedewald formula simply breaks down at high triglyceride levels. I ordered a direct LDL measurement instead, which came back closer to 90 mg/dL. The patient needed treatment adjustment, and the original number would have given a false sense of security. If triglycerides are over 400, always request a direct LDL or use the Martin-Hopkins calculation if your lab supports it. This is one of those things that will quietly mislead you unless you catch it. Another nuance that beginners miss: LDL-C is not the same thing as the number of LDL particles. You can have a normal LDL-C but a high apoB count, meaning there are lots of small, dense particles circulating. This is common in metabolic syndrome and type 2 diabetes. The particle count matters for risk, but the treatment target stays LDL-C. You do not switch targets because apoB is elevated. You treat the LDL-C to guideline goals and then assess residual risk separately. ApoB is a refinement tool, not a replacement target in current standard of care. The practical workflow I use is simple. Get a fasting or non-fasting lipid panel. If non-fasting, triglycerides will be slightly higher but LDL-C is still usable. Calculate the 10-year ASCVD risk score if you are in a primary prevention context. Start with a high-intensity statin for very high-risk patients, moderate-to-high intensity for secondary prevention, and moderate intensity for primary prevention depending on risk. Recheck lipids in four to twelve weeks after starting or changing therapy. If the patient is not at goal, add ezetimibe before considering a third agent. PCSK9 inhibitors come after that, and bempedoic acid is an option for statin-intolerant patients who still need additional lowering.
Statins remain first-line because the evidence base is unmatched. Rosuvastatin and atorvastatin in their higher doses produce the largest LDL-C reductions, typically forty to fifty-five percent. But intensity does not automatically mean higher dose. Some patients tolerate moderate-intensity statins better and achieve acceptable control when combined with ezetimibe, which adds another eleven to nineteen percent reduction on top of whatever the statin is doing. The combination is often better tolerated than pushing a statin to its max dose, and it gets you to the same place. There is a real-world bottleneck worth noting. Patients do not always adhere to statin therapy, and muscle-related side effects are the most common reason they stop. I have seen it frequently. The evidence for true statin-induced myopathy is thinner than the public believes, but the nocebo effect is powerful. When a patient complains of myalgias, the first step is not to blame the statin immediately. Check CK if symptoms are significant, rule out other causes like hypothyroidism or vitamin D deficiency, and then consider a statin pause and rechallenge with a different agent or a lower dose. About half of patients who report intolerance on a initial statin will tolerate a different statin or a lower-intensity regimen on rechallenge. This is not a theoretical point. It is the pattern I see consistently. For patients with familial hypercholesterolemia, the targets shift again. Heterozygous FH patients often need combination therapy from the start because monotherapy rarely gets LDL-C below 70 mg/dL. Homozygous FH is even more challenging and may require lomitapide or evolocumab in specialized centers. This is where lipid management moves from standard primary care territory into genetic and specialist-driven care.
Get the Full Details

The takeaway is not complicated. LDL-C is the primary target. Know your risk-based thresholds. Use the right calculation method when triglycerides are high. Start with statins, add ezetimibe early, and only escalate to injectables or newer agents when necessary. The guidelines change periodically, but the center of gravity stays the same.