The Mechanics of Fat Breakdown
Lipid digestion is a multi-stage process that spans from the mouth all the way through the small intestine. Most people assume it happens mostly in the stomach, but the stomach's role is actually quite minor when it comes to breaking down fats. The real work happens downstream, and understanding where the action takes place requires looking at the whole GI tract, not just one organ. I used to think emulsification was just a fancy word for "mixing it up." Then I spent a semester in a biochemistry lab trying to demonstrate bile salt function with a simple oil-and-water separation experiment. What happened next made me reconsider how little most textbooks actually convey about the mechanics involved.
Where Does Lipid Digestion Take Place
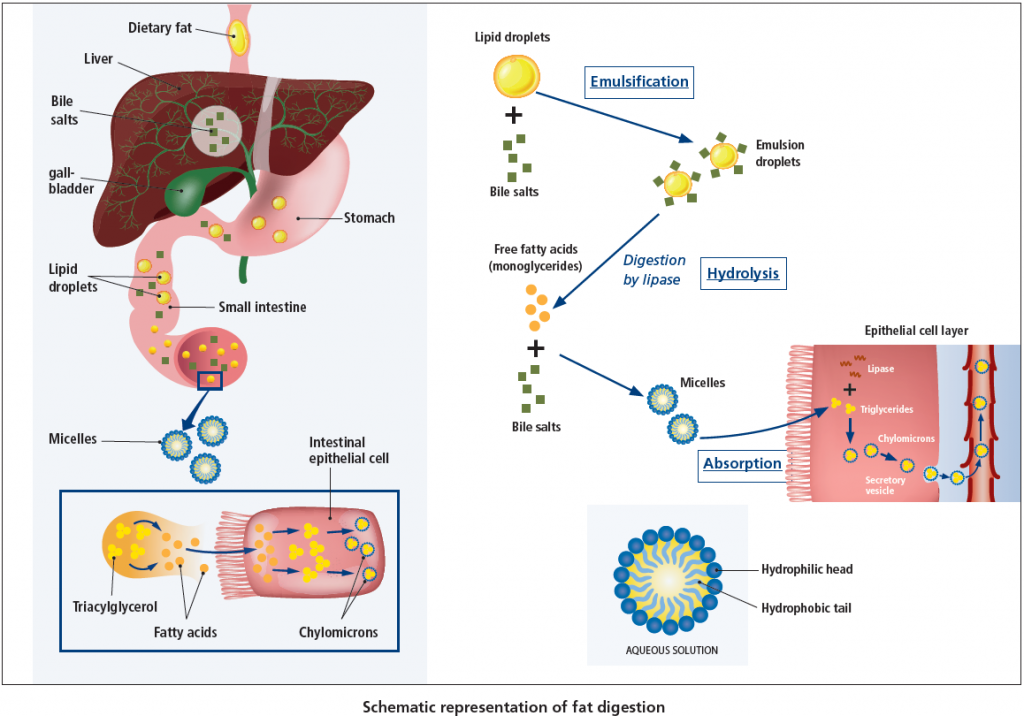
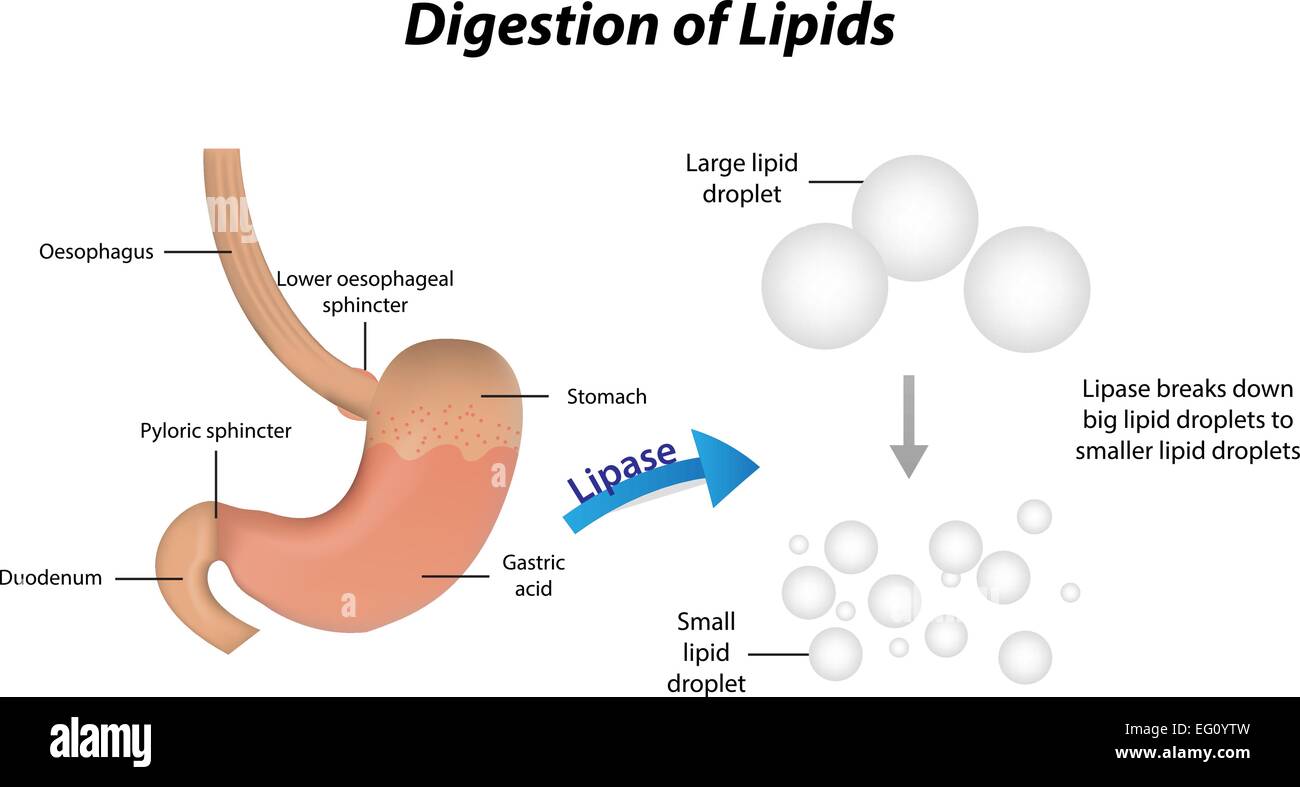
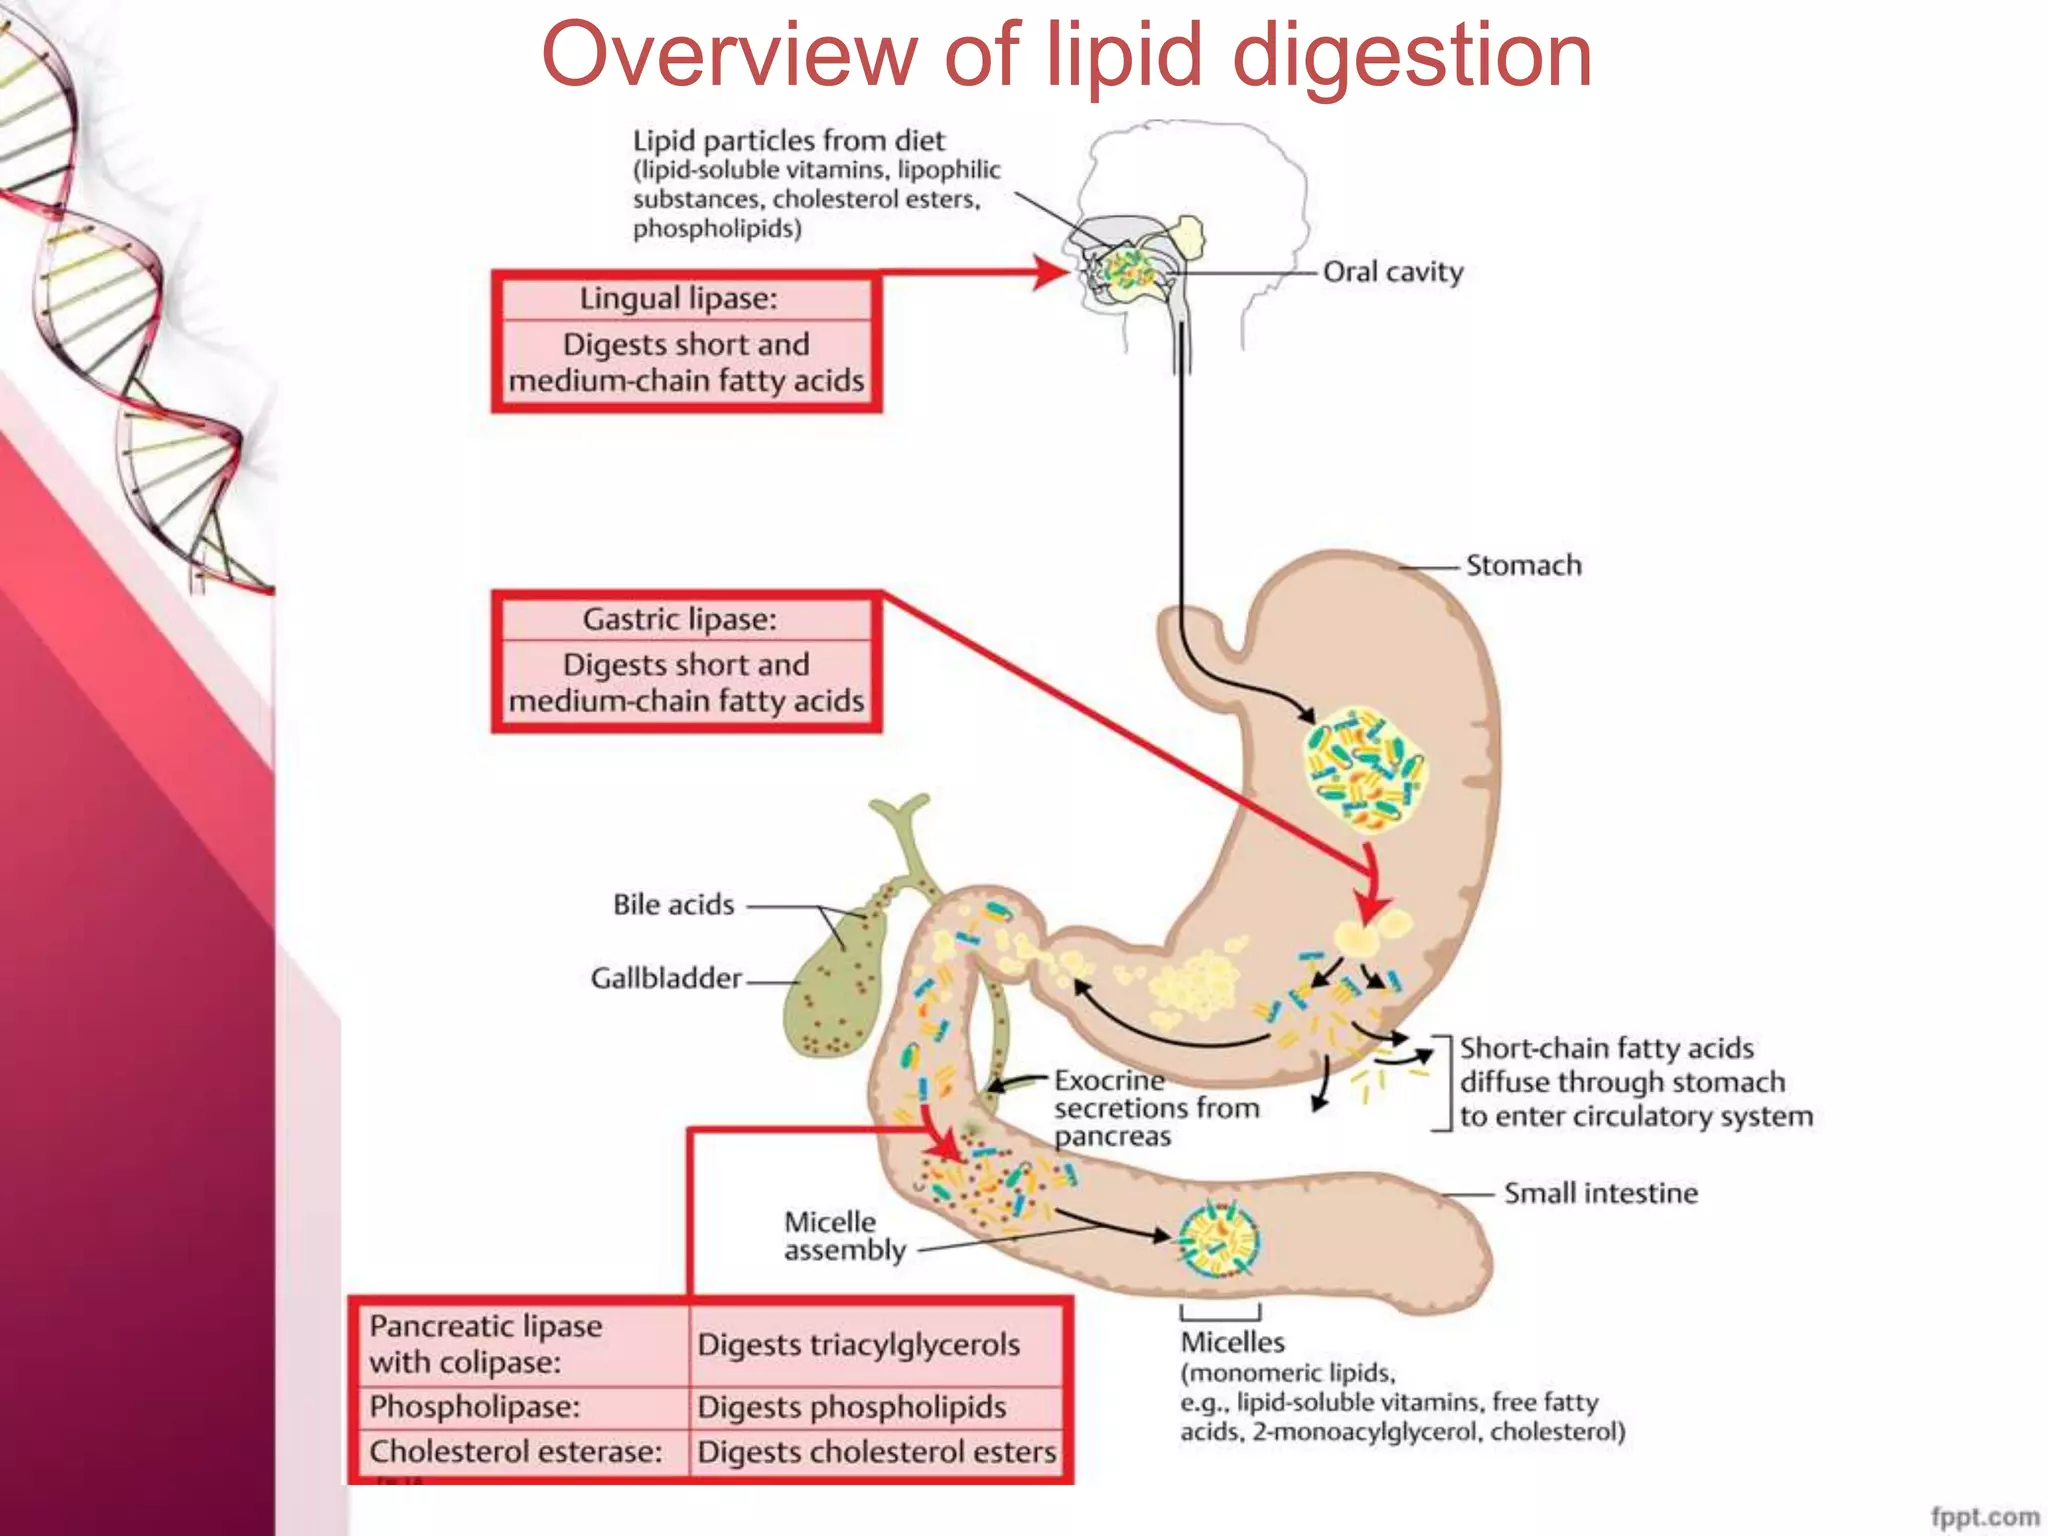
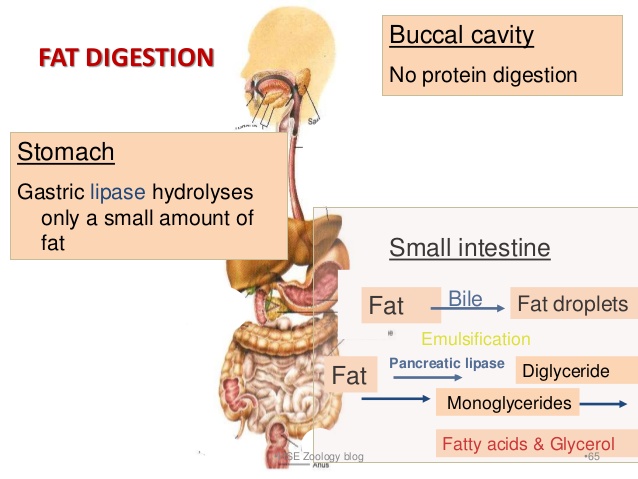
The primary site of lipid digestion is the small intestine, specifically the duodenum and jejunum. The stomach does begin the process with some mechanical churning and minimal gastric lipase activity, but the bulk of chemical breakdown occurs in the small intestine after bile and pancreatic secretions are introduced. The process starts mechanically in the mouth, where chewing and salivary mixing begin to emulsify fats at a very coarse level. Lingual lipase is secreted by glands on the tongue and begins acting on triglycerides immediately. This enzyme is particularly important in infants, whose pancreatic function is not yet fully developed. In adults, lingual lipase contributes maybe ten to fifteen percent of total lipid digestion under normal conditions. That number climbs significantly during fasting states or in patients with pancreatic insufficiency. From the mouth, fats travel to the stomach. Here, the stomach's acidic environment and muscular contractions help break fat globules into smaller particles. Gastric lipase continues its work in this acidic milieu, but its contribution is modest. Most triglycerides remain largely intact after leaving the stomach. The key transformation happens when chyme enters the duodenum and encounters two critical players: bile from the gallbladder and pancreatic lipase from the pancreas.
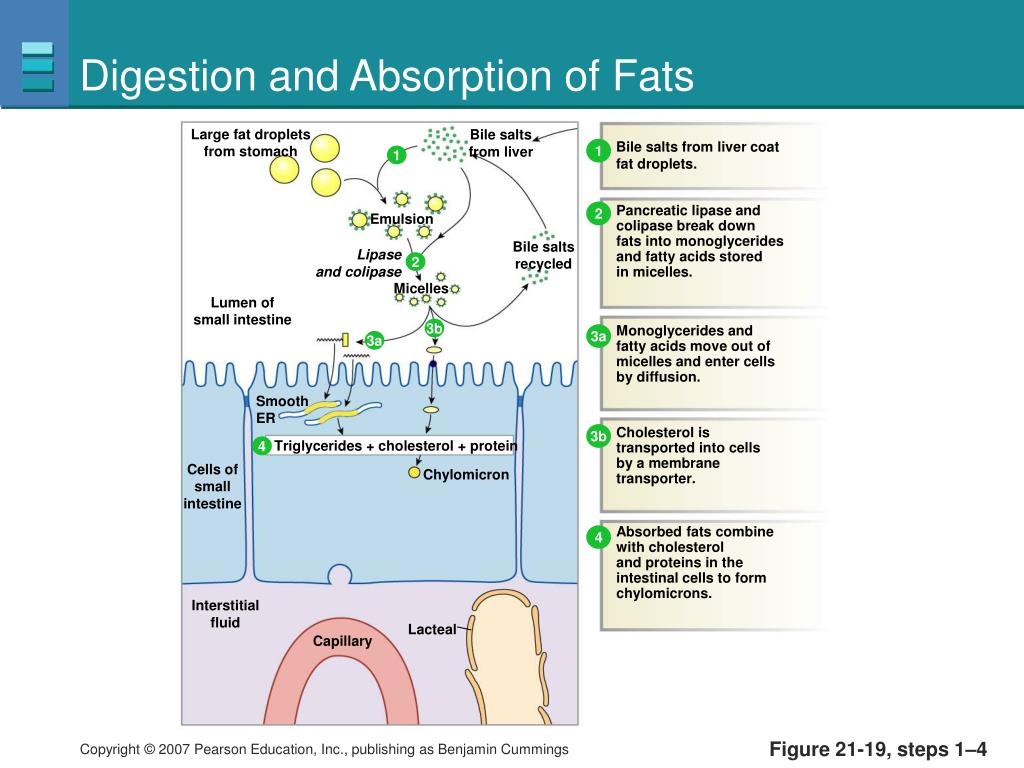
Bile salts are amphipathic molecules that act as biological detergents. They surround fat droplets and reduce surface tension, breaking large globules into tiny micelles. This process dramatically increases the surface area available for enzymatic attack. Without adequate bile, pancreatic lipase simply cannot reach the interior of fat droplets efficiently. A patient with gallbladder removal, for instance, may experience fat malabsorption because bile is no longer stored and concentrated for release during meals. Instead, it drips continuously into the intestine, which is less effective at handling a large fatty load all at once. Pancreatic lipase is the workhorse enzyme. It cleaves the sn-1 and sn-3 positions of triglycerides, releasing free fatty acids and monoglycerides. These products are then incorporated into mixed micelles along with bile salts, phospholipids, and cholesterol. The micelles ferry these lipid products through the aqueous environment of the intestinal lumen to the brush border of enterocytes, where absorption occurs.
Get the Full Details
Why This Matters in Practice
The location of lipid digestion is not just an academic detail. It has real implications for clinical practice and patient outcomes. Consider someone presenting with steatorrhea—fatty, floating stools that are difficult to flush. The cause could be anywhere along the digestive tract, and knowing exactly where each step occurs helps you narrow the differential diagnosis quickly. I encountered a case a few years back involving a patient who had undergone a partial gastrectomy. They reported severe diarrhea and weight loss after eating even modest amounts of fat. Standard workups showed normal pancreatic function and no evidence of bile acid malabsorption. The issue turned out to be rapid gastric emptying. Food was bypassing the stomach too quickly, dumping a concentrated load of fat into the small intestine before bile and pancreatic enzymes could adequately respond. The timing mismatch was the problem, not any single organ's function. The workaround was dietary modification combined with a medication that slows gastric emptying. We reduced the fat content of meals and split them into more frequent, smaller portions. The patient also took acarbose, which slows carbohydrate absorption and incidentally slows the overall transit of chyme through the upper GI tract. Within three weeks, symptoms improved dramatically. This case reinforced for me that lipid digestion is as much about timing and coordination as it is about enzymes and bile.
Common Misunderstandings
One persistent misconception is that the large intestine plays any significant role in lipid digestion. It does not. By the time contents reach the colon, virtually all digestible lipids have already been absorbed in the small intestine. The colon handles water reabsorption and houses bacteria that ferment undigested carbohydrates, but fats passing through are essentially waste at that point. Another common error is assuming that bile production equals bile function. The liver produces bile constantly, but the gallbladder stores and concentrates it. After cholecystectomy, bile is still produced but lacks the concentrated burst needed to efficiently emulsify a fatty meal. This is why some patients report difficulty tolerating high-fat foods after gallbladder removal, even though digestion can eventually adapt over several months as the bile ducts gradually accommodate increased storage capacity. People also tend to overestimate the role of stomach acid in fat digestion. While acid denatures proteins and activates pepsin, it has minimal direct effect on triglyceride breakdown. The acidic pH actually inhibits pancreatic lipase, which functions optimally at a near-neutral pH around 7 to 8. This is why the duodenum rapidly neutralizes incoming gastric acid with bicarbonate secretion from the pancreas and Brunner's glands. If that neutralization fails, as it can in conditions like Zollinger-Ellison syndrome, pancreatic lipase activity drops significantly and fat malabsorption follows.
The Absorption Step
Once micelles deliver free fatty acids and monoglycerides to the enterocyte surface, absorption occurs through simple diffusion across the brush border membrane. Short-chain fatty acids (fewer than twelve carbon atoms) can diffuse directly into the portal blood, but long-chain fatty acids follow a more complex pathway. Inside the enterocyte, they are re-esterified into triglycerides, packaged into chylomicrons, and released into the lymphatic system via the lacteals. This lymphatic route bypasses the liver initially, which is why intravenous lipid emulsions used in parenteral nutrition require different formulations than dietary fats. The efficiency of this entire process depends on proper coordination between gastric emptying, bile release, and pancreatic secretion. Disruption at any point can lead to malabsorption, nutrient deficiencies, or gastrointestinal distress. A thorough understanding of where and how lipid digestion occurs is therefore essential for anyone working in gastroenterology, nutrition, or related clinical fields.